Tuberculosis (TB)
What Tuberculosis Is
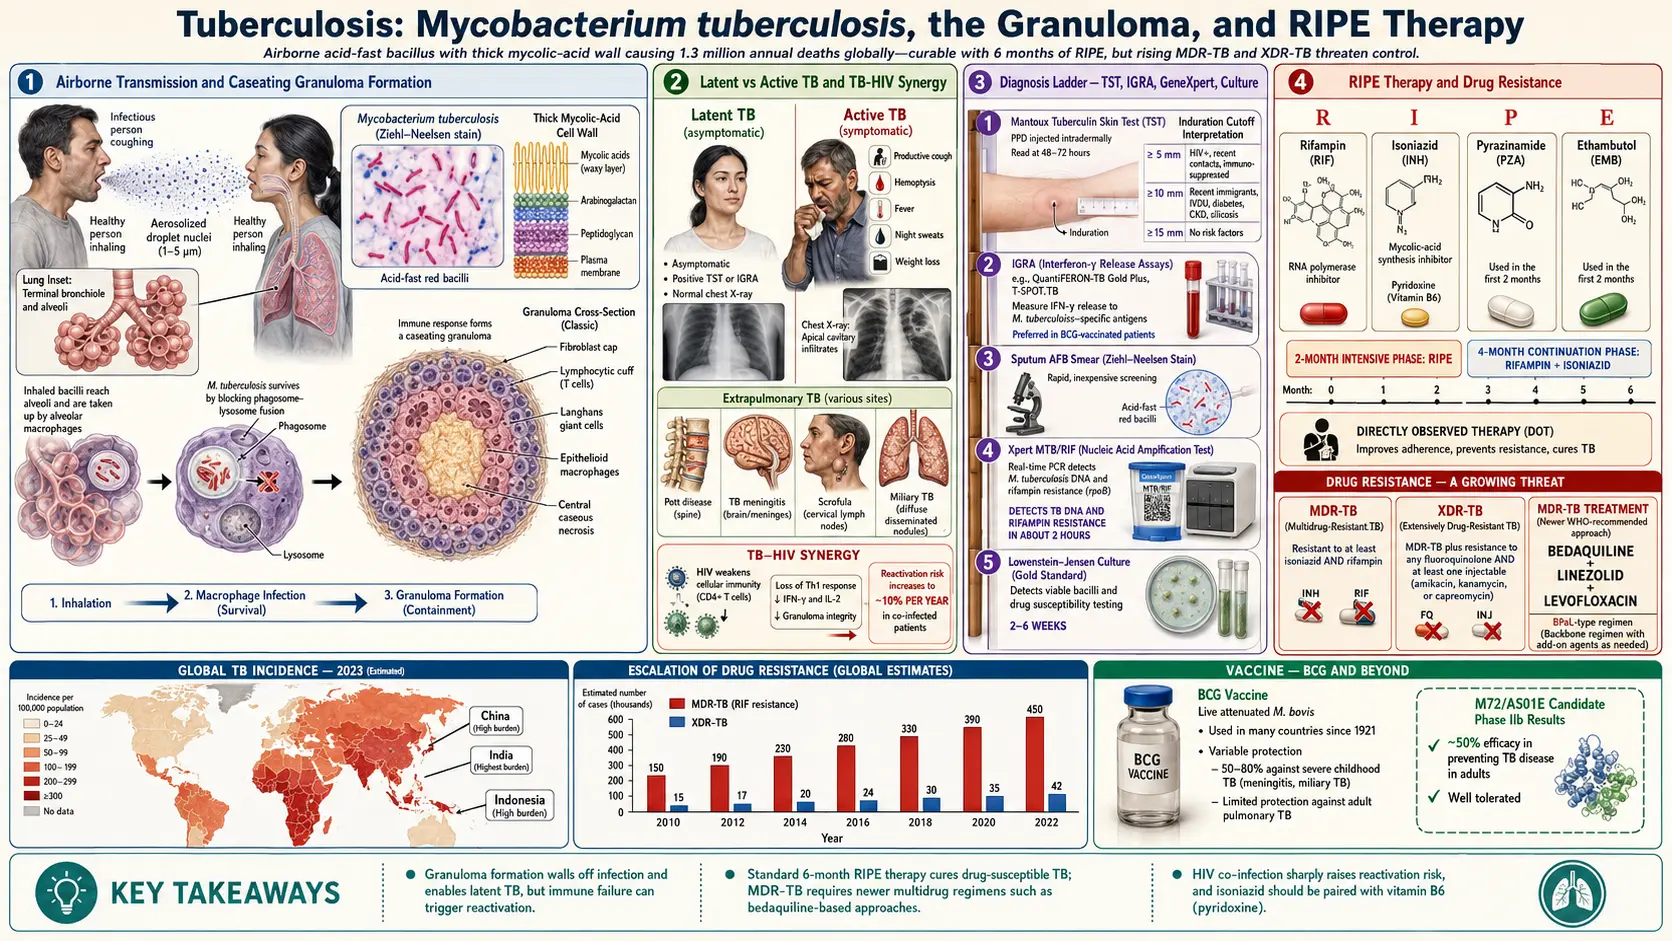
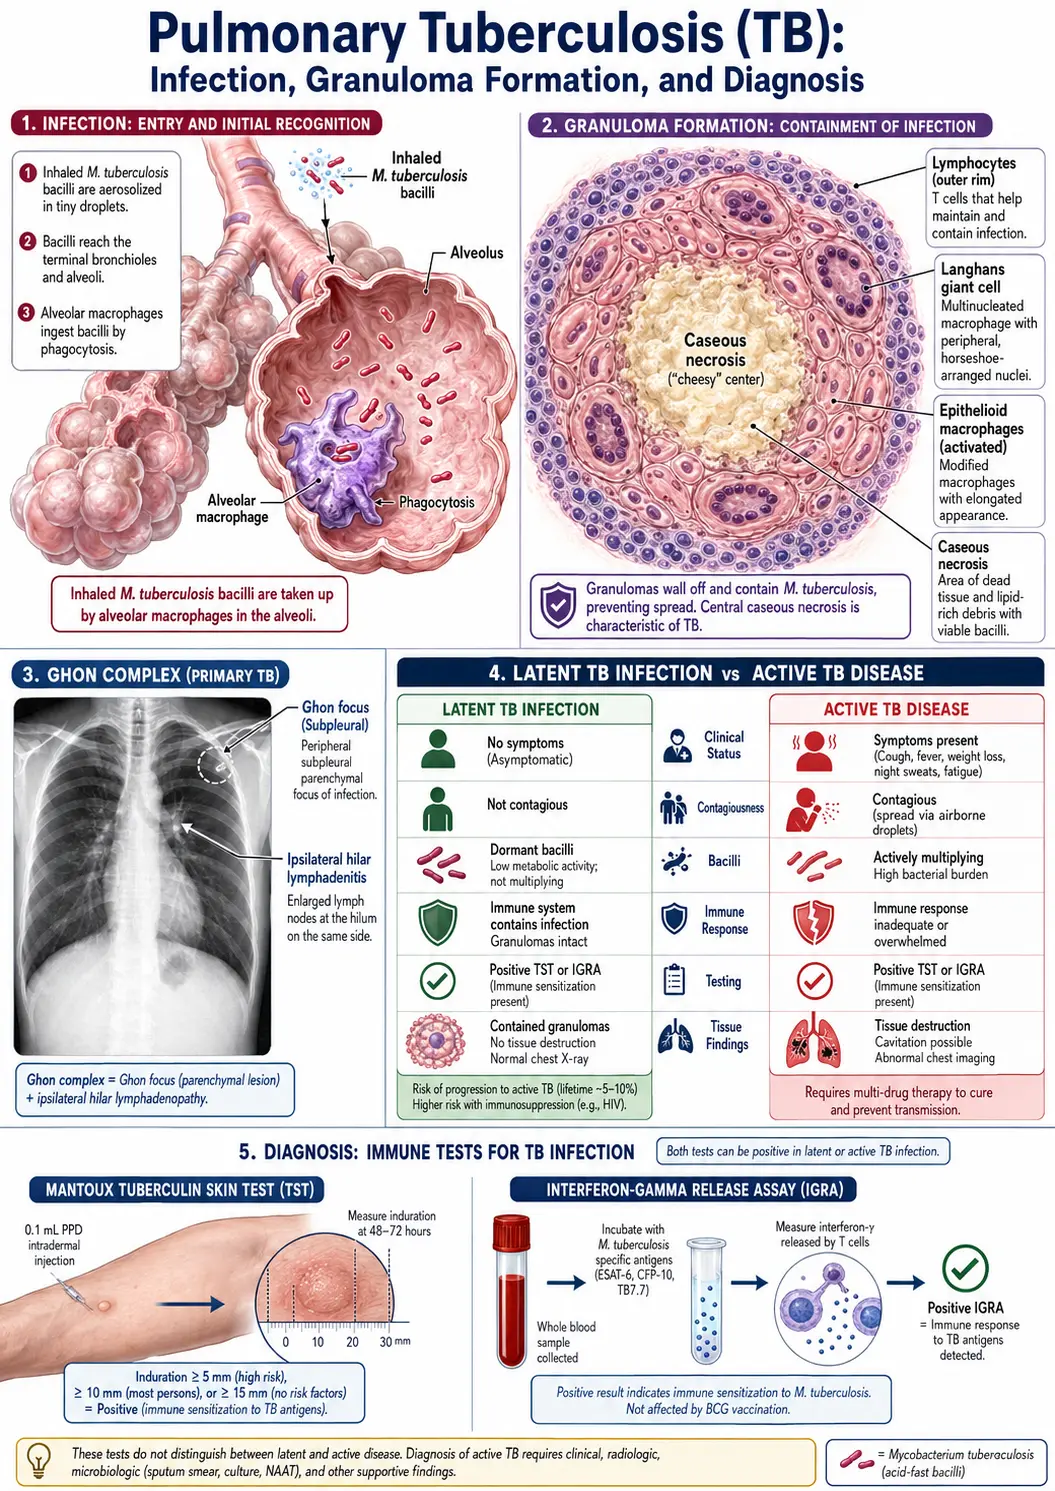
Tuberculosis (TB) is an infectious disease caused by the bacterium Mycobacterium tuberculosis. It primarily affects the lungs but can spread to other parts of the body, such as the kidneys, spine, and brain. Tuberculosis can be latent or active, with active tuberculosis being contagious and requiring treatment.
How Common Tuberculosis Is Worldwide
The World Health Organization (WHO) estimates that 10.7 million people fell ill with tuberculosis in 2024 (5.8 million men, 3.7 million women and 1.2 million children) and that 1.23 million people died of it, including 150,000 people with HIV. WHO describes tuberculosis as the world’s leading cause of death from a single infectious agent. About a quarter of the world’s population is estimated to have been infected with tuberculosis bacteria; people with this silent infection do not feel sick and are not contagious, and about 5–10% of them eventually develop tuberculosis disease (WHO fact sheet; Houben and Dodd 2016).
Types of Tuberculosis
1. Latent Tuberculosis
- No symptoms: The bacteria remain inactive in the body and do not cause illness.
- Not contagious
- Can become active: Without treatment, latent tuberculosis can progress to active tuberculosis.
2. Active Tuberculosis
- Shows symptoms and can spread to others.
- Requires immediate treatment to prevent complications and transmission.
Symptoms of Active Tuberculosis
Common symptoms include:
- Persistent cough: Lasting three weeks or longer, sometimes with blood-tinged sputum.
- Chest pain
- Unintentional weight loss
- Fatigue
- Fever and chills
- Night sweats
- Loss of appetite
Causes and Transmission
- Caused by Mycobacterium tuberculosis
- Airborne transmission: tuberculosis spreads when an infected person coughs, sneezes, or talks, releasing respiratory droplets containing the bacteria.
- Close contact with someone who has active tuberculosis increases the risk of infection.
Risk Factors
- Weakened immune system: People with human immunodeficiency virus (HIV)/acquired immunodeficiency syndrome (AIDS), diabetes, or those undergoing immunosuppressive therapy are more susceptible.
- Close contact with someone who has active tuberculosis.
- Living or working in high-risk environments: Such as prisons, shelters, or healthcare facilities.
- Substance abuse: Drug and alcohol use can weaken the immune system.
- Poor nutrition
Diagnosis
- Tuberculosis skin test (Mantoux test): A small amount of tuberculin is injected under the skin to see if a reaction occurs.
- Tuberculosis blood tests: Such as the interferon-gamma release assays (IGRAs).
- Chest X-ray: Helps detect lung damage associated with active tuberculosis.
- Sputum tests: Microscopic examination and culture to identify tuberculosis bacteria.
Treatment Options
- Antibiotic regimen:
- First-line drugs: Include isoniazid, rifampin, ethambutol, and pyrazinamide.
- Duration: The standard course for drug-sensitive tuberculosis lasts 6 months, and longer courses are used for some types and severities of tuberculosis.
- Four-month options: In a 2021 trial of 2,516 people with newly diagnosed lung tuberculosis in 13 countries, a 4-month regimen in which rifapentine replaced rifampin and moxifloxacin replaced ethambutol worked as well as the standard 6 months (15.5% vs 14.6% unfavourable outcomes); a 4-month rifapentine regimen without moxifloxacin did not reach that bar (Dorman 2021). In the SHINE trial of 1,204 children in Uganda, Zambia, South Africa and India with non-severe tuberculosis, 4 months of the standard children’s drugs worked as well as 6 months (3% vs 3% unfavourable outcomes; Turkova 2022).
- Directly observed therapy (DOT): Healthcare providers supervise patients taking their medication to ensure adherence.
- Treatment of latent (silent) infection: In the PREVENT TB trial of people at high risk, 3 months of once-weekly rifapentine plus isoniazid prevented tuberculosis as well as 9 months of daily isoniazid (0.19% vs 0.43% developed tuberculosis). More people finished the 3-month course (82.1% vs 69.0%), and liver injury was less common (0.4% vs 2.7%), although stopping because of side effects was slightly more common (4.9% vs 3.7%; Sterling 2011).
Drug-Resistant Tuberculosis
Drug-resistant tuberculosis occurs when the bacteria do not respond to the standard treatment due to resistance to certain medications.
1. Multidrug-Resistant TB (MDR-TB)
- Resistant to isoniazid and rifampin, the two most potent tuberculosis drugs.
- Requires alternative treatment: older second-line regimens lasted 9 to 20 months and caused more side effects. Since 2022 WHO guidelines have prioritized a 6-month all-oral regimen (see below).
2. Extensively Drug-Resistant TB (XDR-TB)
- Definition revised by WHO in January 2021: tuberculosis that meets the definition of MDR or rifampicin-resistant tuberculosis and is also resistant to any fluoroquinolone and to at least one more “Group A” drug (WHO’s most potent second-line group: levofloxacin, moxifloxacin, bedaquiline and linezolid).
- More challenging to treat and requires specialized medications.
3. Pre-Extensively Drug-Resistant TB (Pre-XDR-TB)
- Defined by WHO for the first time in 2021: MDR or rifampicin-resistant tuberculosis that is also resistant to any fluoroquinolone (Viney 2021).
The 6-Month All-Oral Regimen
The TB-PRACTECAL trial (Belarus, South Africa and Uzbekistan, people aged 15 and over) compared a 24-week all-oral regimen of bedaquiline, pretomanid, linezolid and moxifloxacin (BPaLM) with a 9-to-20-month standard regimen for rifampin-resistant lung tuberculosis. In the main analysis, 11% of the BPaLM group and 48% of the standard-care group had an unfavourable outcome (death, treatment failure, stopping treatment, loss to follow-up or relapse). Serious or grade 3 and higher side effects occurred in 19% vs 59%. Recruitment was stopped early (Nyang’wa 2022). WHO reports that its 2022 guidelines prioritized this 6-month regimen (BPaLM/BPaL) as a treatment of choice, and that about 34,000 people with multidrug- or rifampicin-resistant tuberculosis started 6-month regimens in 2024, up from 5,653 in 2023 and 1,744 in 2022. WHO also reports that only about 2 in 5 people with multidrug-resistant tuberculosis accessed treatment in 2024.
Prevention Strategies
- Close contact with someone who has active, untreated tuberculosis is the main route of infection, so less time near that person means less exposure.
- Protective measures: Masks worn in high-risk settings reduce exposure to the bacteria.
- Good ventilation: Helps reduce the concentration of tuberculosis bacteria in enclosed spaces.
- Early detection and treatment: Reduces the risk of spreading the disease.
- BCG vaccine: WHO reports that in certain countries the Bacille Calmette-Guérin (BCG) vaccine is given to babies or small children to prevent tuberculosis, and that it prevents deaths from tuberculosis and protects children from serious forms of the disease.
- Preventive treatment after exposure to drug-resistant TB: WHO reports that people exposed to multidrug-resistant tuberculosis may receive preventive treatment with levofloxacin.
Complications of Tuberculosis
- Lung damage: Can lead to permanent scarring and reduced lung function.
- Spread to other organs: Known as extrapulmonary tuberculosis, which can affect the kidneys, spine, brain, and other parts of the body.
- Spinal pain: tuberculosis in the spine (Pott's disease) can cause severe pain and deformities.
- Meningitis: tuberculosis affecting the membranes surrounding the brain, leading to life-threatening complications.
- Joint damage: tuberculosis arthritis can affect the hips and knees.
Key Research Papers
Historical Background
Robert Koch identified Mycobacterium tuberculosis as the causative agent of tuberculosis on March 24, 1882, a discovery for which he received the 1905 Nobel Prize in Physiology or Medicine. The introduction of streptomycin in 1944 by Albert Schatz, Elizabeth Bugie, and Selman Waksman marked the beginning of effective antibiotic treatment for tuberculosis.
Key Research Papers
Every citation below has been re-checked against the PubMed record. An earlier version of this list attached a DOI to each entry, and those DOIs were shuffled — each one resolved to a real paper, but not the one it was labelled as. The most striking mismatch: the Conradie drug-resistant tuberculosis trial linked to a placebo-controlled trial of bezafibrate in primary biliary cholangitis. Links are now numeric PubMed IDs.
- Pai M, Behr MA, Dowdy D, et al. Tuberculosis. Nature Reviews Disease Primers. 2016;2:16076. — PubMed PMID: 27784885
- Zumla A, Raviglione M, Hafner R, von Reyn CF. Tuberculosis. New England Journal of Medicine. 2013;368(8):745-755. — PubMed PMID: 23425167
- Lawn SD, Zumla AI. Tuberculosis. The Lancet. 2011;378(9785):57-72. — PubMed PMID: 21420161
- Dorman SE, Nahid P, Kurbatova EV, et al. Four-month rifapentine regimens with or without moxifloxacin for tuberculosis. New England Journal of Medicine. 2021;384(18):1705-1718. The trial behind the four-month regimen now offered as an alternative to six months. — PubMed PMID: 33951360
- Sterling TR, Villarino ME, Borisov AS, et al. Three months of rifapentine and isoniazid for latent tuberculosis infection. New England Journal of Medicine. 2011;365(23):2155-2166. The basis of the 12-dose weekly regimen for latent infection. — PubMed PMID: 22150035
- Diacon AH, Pym A, Grobusch MP, et al. Multidrug-resistant tuberculosis and culture conversion with bedaquiline. New England Journal of Medicine. 2014;371(8):723-732. — PubMed PMID: 25140958
- Conradie F, Diacon AH, Ngubane N, et al. Treatment of highly drug-resistant pulmonary tuberculosis. New England Journal of Medicine. 2020;382(10):893-902. The Nix-TB trial of bedaquiline, pretomanid and linezolid. — PubMed PMID: 32130813
- Boehme CC, Nabeta P, Hillemann D, et al. Rapid molecular detection of tuberculosis and rifampin resistance. New England Journal of Medicine. 2010;363(11):1005-1015. The Xpert MTB/RIF validation study. — PubMed PMID: 20825313
- Gandhi NR, Moll A, Sturm AW, et al. Extensively drug-resistant tuberculosis as a cause of death in patients co-infected with tuberculosis and HIV in a rural area of South Africa. The Lancet. 2006;368(9547):1575-1580. — PubMed PMID: 17084757
- Houben RMGJ, Dodd PJ. The global burden of latent tuberculosis infection: a re-estimation using mathematical modelling. PLoS Medicine. 2016;13(10):e1002152. The source of the widely quoted “one quarter of the world” figure. — PubMed PMID: 27780211
- Horsburgh CR Jr, Barry CE 3rd, Lange C. Treatment of tuberculosis. New England Journal of Medicine. 2015;373(22):2149-2160. Added: the paper whose DOI was previously attached to the Pai citation. — PubMed PMID: 26605929
- Turkova A, Wills GH, Wobudeya E, et al. Shorter treatment for nonsevere tuberculosis in African and Indian children. New England Journal of Medicine. 2022;386(10):911-922. The SHINE trial. — PubMed PMID: 35263517
- Nyang'wa BT, Berry C, Kazounis E, et al. A 24-week, all-oral regimen for rifampin-resistant tuberculosis. New England Journal of Medicine. 2022;387(25):2331-2343. The TB-PRACTECAL trial. — PubMed PMID: 36546625
- Viney K, Linh NN, Gegia M, et al. New definitions of pre-extensively and extensively drug-resistant tuberculosis: update from the World Health Organization. European Respiratory Journal. 2021;57(4):2100361. — PubMed PMID: 33833074
- World Health Organization. Tuberculosis: key facts (fact sheet, updated 4 March 2026). Source of the 2024 burden figures, the BCG vaccine statement and the 6-month regimen figures. — WHO fact sheet
- World Health Organization. WHO consolidated guidelines on tuberculosis. Module 4: treatment — drug-resistant tuberculosis treatment. Geneva: WHO. — WHO guideline An earlier version of this page cited these guidelines as an article in The Lancet Infectious Diseases 2019;19(11):e348-e364. WHO guidelines are published by WHO, not in that journal; the reference has been pointed at the source document.
PubMed Topic Searches
The following PubMed topic searches retrieve current peer-reviewed literature on Tuberculosis. Each link opens a live PubMed query so you always see the most recent publications.
- PubMed: Tuberculosis review
- PubMed: Mycobacterium tuberculosis pathogenesis
- PubMed: Multidrug resistant tuberculosis MDR-TB
- PubMed: Bedaquiline tuberculosis treatment
- PubMed: Isoniazid rifampin tuberculosis
- PubMed: Latent tuberculosis infection treatment
- PubMed: BCG vaccine tuberculosis efficacy
- PubMed: Tuberculosis HIV coinfection
- PubMed: GeneXpert tuberculosis diagnosis
- PubMed: WHO tuberculosis global report
- PubMed: Extrapulmonary tuberculosis
- PubMed: Vitamin D tuberculosis
Connections
- Infectious Disease
- Human Immunodeficiency Virus/Acquired Immunodeficiency Syndrome
- Immune Boosting
- Vitamin D3
- Zinc
- Garlic
- Andrographis
- Meningitis
- Hepatitis B
- Hepatitis C
- Hepatitis
- Diabetes
- Fatigue
- Chest Pain
- Loss of Appetite
- Cellulitis
- Clostridium Difficile
- Eucalyptus
- Biologics TNF IL23 Integrin Inhibitors
- Herbs covered on this site that discuss this condition: Black Turmeric (Curcuma caesia) · Neem (Azadirachta indica) · Pau d'Arco (Tabebuia impetiginosa / Handroanthus impetiginosus)
- Pneumonia