⚠ Evidence warning: Clinical trials or other evidence do not support the claim that modified-release indomethacin at bedtime controls morning stiffness better than standard dosing at comparable total doses. This page keeps it as a report of what people, websites or other media say.
Morning Stiffness Management for Ankylosing Spondylitis
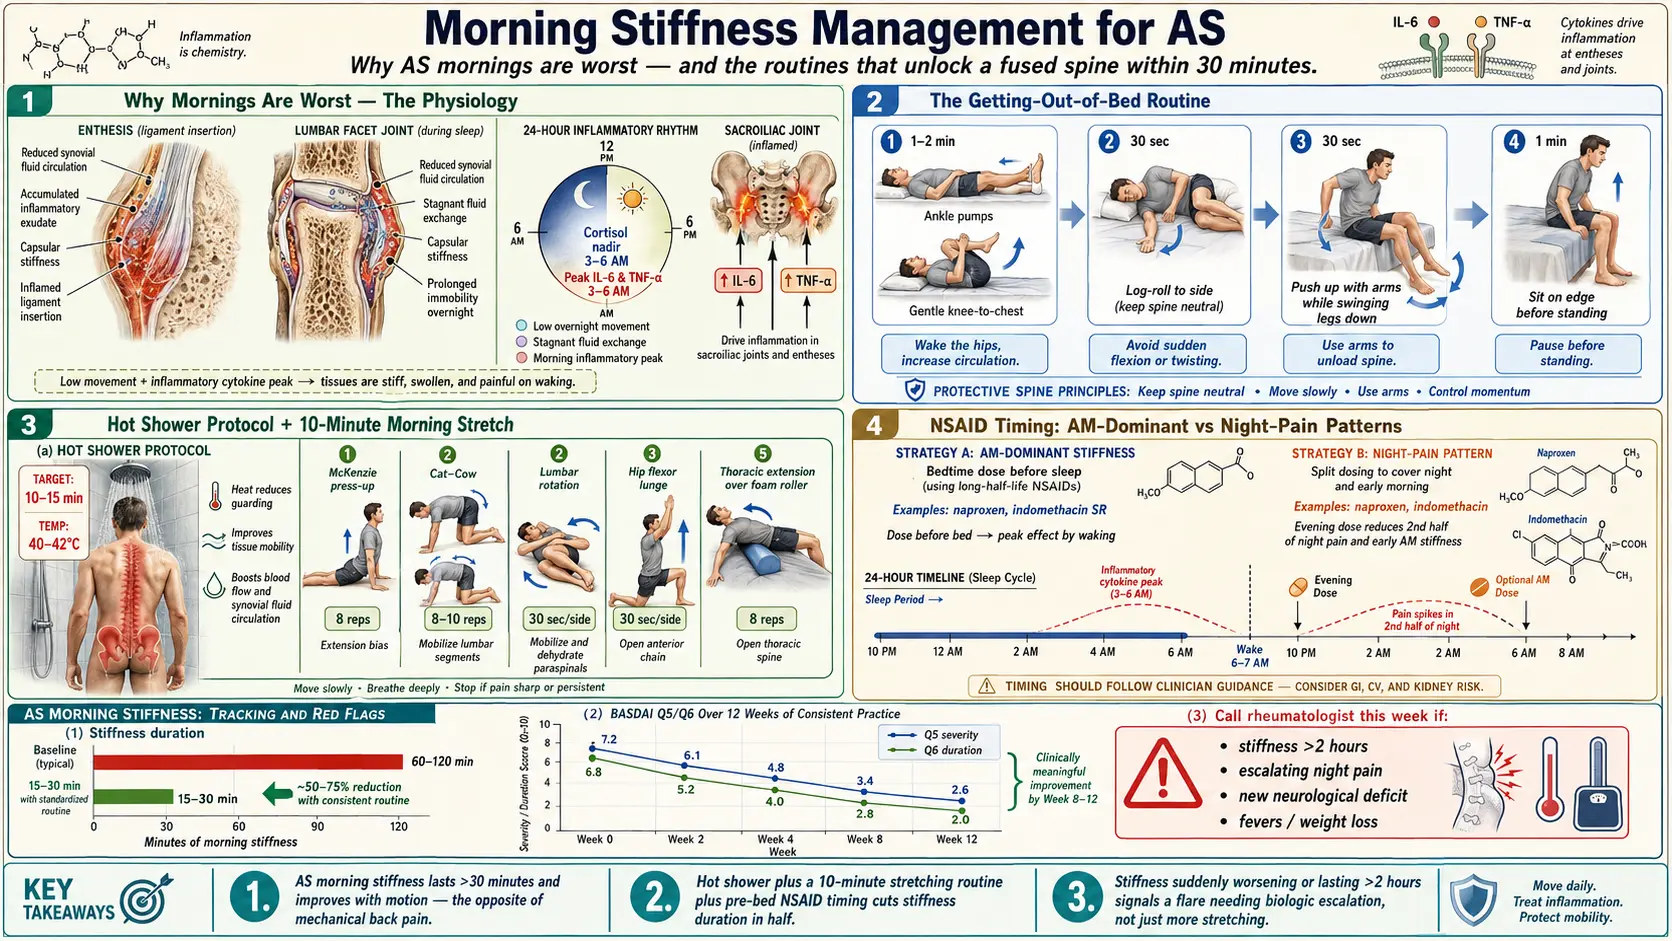
Table of Contents
- Why Ankylosing Spondylitis Morning Stiffness Is Different
- The Physiology — Why Mornings Are Worst
- The Getting-Out-of-Bed Routine Patients Describe
- How a Hot Shower Is Used for Morning Stiffness
- A 10-Minute Morning Stretching Sequence Physiotherapists Describe
- Evening and Sleep Factors Linked to Morning Stiffness
- Nonsteroidal Anti-Inflammatory Drug Timing — AM-Dominant vs Night-Pain Patterns
- Heat Tools Used for Ankylosing Spondylitis Stiffness
- Workplace Adjustments People With Ankylosing Spondylitis Use
- When Stiffness Worsens — The Flare Signal
- How Stiffness Is Tracked
- Warning Signs Doctors Treat as Urgent
- Key Research Papers
- Connections
- Featured Videos
Why Ankylosing Spondylitis Morning Stiffness Is Different
People with ankylosing spondylitis often describe waking up feeling like a plank of wood — spine locked, hips jammed, ribs tight enough that a deep breath feels like work. Morning stiffness is the single most characteristic symptom of ankylosing spondylitis, and the ASAS (Assessment of SpondyloArthritis international Society) criteria use it to separate inflammatory back pain from ordinary mechanical back pain.
Four features distinguish the ankylosing spondylitis (AS) pattern:
- Duration longer than 30 minutes — typically 45 minutes to two hours on bad days. Mechanical back pain loosens within 5–15 minutes of getting up.
- Worse at rest, better with movement. Walking, stretching, and a hot shower help. This is the opposite of a disc injury.
- Second-half-of-the-night awakening. Many ankylosing spondylitis patients wake at 3–5 a.m. with pain that forces them up to move before they can fall back asleep.
- Alternating buttock pain. Deep, dull pain that switches sides from week to week — a signature of sacroiliitis.
When three or more of these features are present in someone under 45, doctors treat the pattern as inflammatory back pain until shown otherwise. Each feature is a useful diagnostic clue for a rheumatologist.
The Physiology — Why Mornings Are Worst
Morning stiffness in ankylosing spondylitis is not a stretching problem. It is an inflammation problem that follows a clock. The cytokines most implicated in ankylosing spondylitis — tumor necrosis factor-alpha, interleukin-6 (IL-6), and IL-17 — peak between roughly 2 a.m. and 7 a.m.
During sleep, several things stack up at once:
- Cytokine surge. Tumor necrosis factor (TNF) and interleukin-6 plasma levels climb overnight and peak near dawn, driving fresh inflammation in the sacroiliac joints, spinal entheses, and facet joints.
- Cortisol trough. The body's own anti-inflammatory cortisol bottoms out around midnight. For a few hours inflammation is at its highest and suppression at its lowest.
- Immobility. Joint fluid thickens and inflammatory exudate pools when joints are still. The spine and SI joints are especially vulnerable — large, poorly vascularized, and motionless.
- Cooling. Core temperature drops during sleep, slowing synovial fluid turnover and thickening periarticular tissue.
By 6 a.m. the spine has been quietly inflamed and immobilized for hours. The morning strategies described below aim at the same three things: raises tissue temperature, restores circulation, and blunts the pre-dawn cytokine peak with properly timed medication.
The Getting-Out-of-Bed Routine Patients Describe
Patients describe the first 60 seconds out of bed as the moment that can set the tone for the day.
Sitting straight up from the back. Lifting the torso flat-to-upright with the abdominal muscles loads the lumbar spine and SI joints at their stiffest moment — described as the most common trigger for a morning pain spike.
The log roll is the alternative physiotherapists describe:
- Both knees are bent so the feet are flat on the mattress.
- Shoulders and hips stay square, moving as one unit like a log.
- The whole body rolls slowly onto one side, shoulders and hips rotating together.
- The feet drop over the edge while the top arm pushes the torso up.
- The person arrives seated without twisting through the spine.
The routine continues with 30–60 seconds sitting on the edge of the bed — ankle circles and shoulder shrugs while blood returns to the legs — and then standing straight up rather than hinging forward off the knees.
The evening nonsteroidal anti-inflammatory drug (NSAID) question. For people who take a nonsteroidal anti-inflammatory drug and whose mornings are worst, practitioners describe the timing of the last dose as important. The idea practitioners describe is that a long-acting agent (modified-release indomethacin, extended-release diclofenac, meloxicam) taken at dinner or bedtime covers the 3–6 a.m. cytokine peak. Details in the nonsteroidal anti-inflammatory drug Strategy article.
How a Hot Shower Is Used for Morning Stiffness
Patients and therapists describe a hot morning shower as part of treatment rather than a luxury. Patients report that ten to fifteen minutes can collapse a two-hour stiffness window to 20 minutes — heat raises tissue temperature, lowers synovial fluid viscosity, dilates vessels feeding the SI joints, and damps pain signaling via gate-control effects.
- Water 40–42°C (104–108°F). Hot but not scalding.
- Ten to fifteen minutes. Under 8 minutes will not warm deep tissue; over 20 adds nothing.
- Sacroiliac joints first. The dimples above and lateral to the tailbone — where most ankylosing spondylitis starts. The back faces the stream for 4–5 minutes.
- Then lumbar, thoracic, and ribs. 2–3 minutes per region, tailbone to neck, with slow deep breaths while water runs down the sides of the chest.
- Movement under the water. Pelvic tilts, shoulder rolls, gentle spinal rotations; heat plus motion is described as working better than either alone.
- Optional contrast finish. 30–60 seconds cool (not cold) at the end. Some patients find the vascular pumping leaves them less stiff two hours later; others leave it out.
A handheld shower head ($30) aims the water pressure directly at the SI joints and ribs.
A 10-Minute Morning Stretching Sequence Physiotherapists Describe
The sequence is described for after the shower, while tissues are warm. Movements are slow and pain-guided, each repeated 5–10 times unless noted.
- Cat-cow on hands and knees (2 min). Drop belly, lift chest and tailbone (cow); round spine, tuck chin and pelvis (cat). Mobilizes every segment through its full sagittal range.
- Supine pelvic tilts (1 min). Lying on the back, knees bent, the lower back is flattened to the floor, held 3 seconds, and released. Reactivates abdominal-pelvic coordination.
- Knee-to-chest, single then double (1 min). Hold 10 seconds each. Opens the lumbar spine and SI joints.
- Thoracic rotations (2 min). Seated with hands behind head, rotate trunk left and right, 3 seconds at end range. Or side-lying "book opener" — top arm swept across to the floor behind. Ankylosing spondylitis freezes thoracic rotation first, which is why this movement is part of daily routines.
- Standing hamstring stretch (1 min). Heel on a low step, hinge forward with a flat back. Tight hamstrings pull the pelvis into posterior tilt — a classic ankylosing spondylitis postural collapse.
- Wall chest stretch (1 min). Forearm on a doorframe at shoulder height, step through. Counters forward-rounded posture.
- Prone press-up (1 min). Face-down, press onto forearms (or hands), look up slightly. Holds spinal extension — the range ankylosing spondylitis attacks first.
- Diaphragmatic breathing (1 min). Hands on lower ribs. In for 4, out for 6, pushing the ribs sideways into the hands. Chest expansion is lost early in ankylosing spondylitis; daily drills preserve it.
Of everything on this page, these eight daily movements are the part physiotherapy routines for ankylosing spondylitis put first. The full exercise and PT protocol builds strength and cardio on top.
Evening and Sleep Factors Linked to Morning Stiffness
Patients and practitioners describe much of morning stiffness as set the night before.
- Medium-firm mattress. Too-soft sags the spine all night; too-hard creates pressure points that keep the sleeper shifting. Firmer-grade memory foam is described as acceptable.
- Thin pillow — or none. Ankylosing spondylitis flexes the upper thoracic spine forward; a thick pillow locks that in and is described as accelerating the "question-mark" posture. The pillow commonly described is the thinnest one that keeps the head neutral.
- Side-sleep with a knee pillow. Keeps the pelvis level and takes rotational strain off the SI joints. Back sleeping is fine. Stomach sleeping is the worst — forces cervical extension and rotation all night.
- Warm shower or bath before bed. Raising core temperature 60–90 minutes before sleep is described as helping people fall asleep faster and keeping joints warmer longer.
- Light bedding. Heavy blankets pin joints in one position.
- Evening alcohol. Alcohol suppresses deep sleep, worsens pain perception, and adds to stomach irritation from nonsteroidal anti-inflammatory drugs (NSAIDs).
- Fluids earlier in the evening. Dehydration thickens synovial fluid, while a 2 a.m. bathroom trip interrupts the pre-dawn sleep that matters most.
Nonsteroidal Anti-Inflammatory Drug Timing — AM-Dominant vs Night-Pain Patterns
Nonsteroidal anti-inflammatory drugs remain first-line for ankylosing spondylitis and often work dramatically. Practitioners and patients describe when they are taken as possibly mattering as much as which one.
Morning-stiffness-dominant. The person sleeps reasonably well but wakes at 6–7 a.m. locked for 60–90 minutes. For this pattern practitioners describe an evening or bedtime dose of a long-acting nonsteroidal anti-inflammatory drug — modified-release indomethacin at dinner, or extended-release diclofenac at bedtime — with the aim of placing peak drug levels in the pre-dawn cytokine surge.
Night-pain-dominant. The person wakes at 2–4 a.m. in active pain. For this pattern practitioners describe a split dose — half with dinner, half with a protein snack at bedtime. Long-half-life agents like naproxen or meloxicam give smoother 24-hour coverage. Modified-release indomethacin at bedtime gave better morning stiffness control than standard dosing at comparable total doses.
Matching dose timing to the symptom pattern is a practice described by practitioners and patients; it is not a statement of the international guidelines.
The 2022 international ASAS-EULAR recommendations keep nonsteroidal anti-inflammatory drugs as the first-choice medicine for axial spondyloarthritis (the disease group that includes ankylosing spondylitis), discourage long-term glucocorticoids (steroid medicines) and conventional disease-modifying antirheumatic drugs (DMARDs) for disease limited to the spine, and set the threshold for biologic drugs (tumour necrosis factor or interleukin-17 inhibitors) or Janus kinase inhibitor drugs: an Ankylosing Spondylitis Disease Activity Score (ASDAS) of 2.1 or more after at least two nonsteroidal anti-inflammatory drugs have failed, together with a raised C-reactive protein, MRI inflammation of the sacroiliac joints, or sacroiliitis on X-ray.
The FDA-approved labels of nonsteroidal anti-inflammatory drugs such as naproxen carry a boxed warning: these drugs increase the risk of serious heart and blood-vessel events, including heart attack and stroke, which can be fatal, and of serious stomach and intestinal bleeding, ulcers and perforation, which can occur at any time without warning symptoms; older people and people with a past ulcer or gastrointestinal bleeding are at greater risk. The labels also list kidney injury with long-term use. Patients who track their pain over two weeks describe the diary as useful when dose timing is discussed with the prescriber. See the nonsteroidal anti-inflammatory drug Strategy article for dose ranges, gastrointestinal (GI) protection, and switching protocols.
Heat Tools Used for Ankylosing Spondylitis Stiffness
Heat is described by patients and therapists as the cheapest and most reliable non-drug comfort measure in ankylosing spondylitis.
- Electric heating pad. The workhorse. Moist-heat option and auto-off timer. 15–20 minutes on the SI joints or lumbar spine. Moist penetrates deeper than dry.
- Heated vest or back wrap. USB-powered ($50–$120) for cold commutes, outdoor work, or chilly offices — cold stiffens ankylosing spondylitis tissue disproportionately.
- Infrared sauna. Far-infrared warms deep tissue without the suffocating air. In a 2009 Dutch pilot study, 17 people with ankylosing spondylitis (and 17 with rheumatoid arthritis) had eight infrared sauna sessions over 4 weeks. Pain and stiffness fell significantly during each session; over the 4 weeks they also improved, but that change did not reach statistical significance. The sessions were well tolerated, with no adverse effects and no flare of disease activity. Home units run $1,500–$4,000; many gyms now have them.
- Paraffin wax bath. For small hand joints, especially with psoriatic overlap. $40–$80.
- Hot water bottle. Still works. Three-quarters full, wrapped in a towel, under the lumbar spine 15 minutes.
- Adhesive heat wraps. Air-activated 8-hour iron-oxidation patches for flights, drives, and workdays away from a heating pad.
Ice in the morning. Cold has a role in acute peripheral joint flares, but patients describe it as worsening axial (spinal) ankylosing spondylitis stiffness.
Workplace Adjustments People With Ankylosing Spondylitis Use
Patients describe eight hours in an office chair as undoing what the morning shower accomplished. Prolonged static posture is the daytime equivalent of overnight immobility.
- Walking breaks every 30 minutes. A timer, then standing, a 60-second walk and pelvic tilts before sitting back down — described as the single highest-impact workplace habit.
- Sit-stand desk. Typically alternated every 30–45 minutes. Electric desk $300–$600; countertop converter $150–$300.
- Lumbar roll or wedge cushion. Maintains the lordosis ankylosing spondylitis flattens; a wedge tilts the pelvis into neutral.
- Monitor at eye level. A laptop on a desk is a cervical-flexion trap; the ergonomic setup described puts the top of the screen at or just below eye line.
- Long flights. Travellers with ankylosing spondylitis describe an aisle seat, a walk every 60 minutes, an adhesive heat patch on the SI joints, and compression socks.
- Long drives. Stops every 90 minutes are described, with a 2-minute walk and a lean back against the car roof as a prone-press-up equivalent.
- Warm clothing. Fleece vest, under-desk space heater. Over-air-conditioned offices are an ankylosing spondylitis nightmare.
- Americans with Disabilities Act (ADA) accommodations. Ankylosing spondylitis can qualify as a disability under the ADA, which requires reasonable accommodations; those people with ankylosing spondylitis commonly request include a sit-stand desk, ergonomic seating, schedule flexibility for morning stiffness, and work-from-home on flare days. Many people raise these with their employer before a crisis.
When Stiffness Worsens — The Flare Signal
Knowing one's own baseline makes an early flare easier to spot. A flare signal is one or more of these, sustained 3–5 days:
- Stiffness duration jumps from 30–60 minutes to 90–180.
- Night pain returns — waking at 2–4 a.m. multiple nights in a row.
- Peripheral joint involvement — swollen knee, inflamed Achilles, sausage finger or toe (dactylitis).
- Fatigue spikes out of proportion to workload.
- Chest expansion feels reduced; deep breaths hurt at the ribs.
- Eye symptoms — pain, redness, light sensitivity, blurred vision — treated as a same-day eye emergency for possible uveitis.
What patients and practitioners describe during a building flare:
- Stretching continues, scaled back if needed — movement is described as most important during a flare.
- More heat — a second evening shower, a heating pad before bed.
- A check of nonsteroidal anti-inflammatory drug timing and adherence; missed doses are a common trigger.
- Extra attention to sleep, fluids and anti-inflammatory eating for 1–2 weeks.
- A flare lasting 2–3 weeks, or a newly involved peripheral joint, is the point at which rheumatologists usually reassess treatment. Under the 2022 ASAS-EULAR recommendations, a biologic or Janus kinase inhibitor is considered when the Ankylosing Spondylitis Disease Activity Score is 2.1 or more after at least two nonsteroidal anti-inflammatory drugs have failed, with a raised C-reactive protein, sacroiliac MRI inflammation or X-ray sacroiliitis.
How Stiffness Is Tracked
Rheumatologists measure stiffness with a validated questionnaire. The validated tool is the BASDAI (Bath Ankylosing Spondylitis Disease Activity Index) — six questions scored 0–10. Question 5 covers duration of morning stiffness; Question 6 covers severity. A BASDAI of 4 or above is high disease activity and a reason to reassess treatment.
A simple daily log works:
- Wake time
- Minutes until stiffness eased
- Severity 0–10
- Night awakenings
- What was done (shower, stretches, nonsteroidal anti-inflammatory drug timing, alcohol, prior-day exercise)
Two weeks of data reveals the pattern. It is the difference between "I feel stiff" and "I average 75 minutes of stiffness, waking twice a night, BASDAI 5.8." Symptom-tracking apps exist for this; a paper notebook records the same information.
Warning Signs Doctors Treat as Urgent
Most morning stiffness is managed at home. The signs below are ones doctors treat as urgent.
- New neurological symptoms below the waist — leg weakness, numbness, foot drop, loss of balance. A fused spine is vulnerable to cord compression from minor trauma. Urgent evaluation.
- Cauda equina warning signs — saddle anesthesia, new urinary or fecal incontinence. Hospitals treat this as an emergency.
- Fever plus worsening back pain. Ankylosing spondylitis itself does not cause fever. Doctors look for septic discitis, vertebral osteomyelitis, or (on biologics) opportunistic infection, and treat it as same-day.
- Sudden severe neck pain after even minor trauma. Advanced ankylosing spondylitis creates a brittle, fused spine that can fracture from trivial impact; doctors image it.
- Sudden eye pain, redness, or vision change. Acute anterior uveitis can damage vision permanently in 24–48 hours; it is treated as a same-day eye emergency.
- Cardiac-feeling chest pain — crushing, radiating, with sweating or shortness of breath. Ankylosing spondylitis raises cardiovascular risk, so this pain is not assumed to be rib inflammation.
Everything else — the plank-of-wood morning, the 90-minute unlock, the 3 a.m. shuffle — is the disease doing what it does. Patients describe the routines above as taking the edge off the daily misery, and a daily stiffness record as useful data for the rheumatologist.
Key Research Papers
- Ramiro S, Nikiphorou E, Sepriano A, et al. ASAS-EULAR recommendations for the management of axial spondyloarthritis: 2022 update. Ann Rheum Dis. 2023;82(1):19–34. — PubMed PMID: 36270658
- Braun J, Sieper J. Ankylosing spondylitis. Lancet. 2007;369(9570):1379–1390. — Landmark review including inflammatory back pain criteria and morning stiffness definition. — doi:10.1016/S0140-6736(07)60635-7
- Sieper J, Lenaerts J, Wollenhaupt J, et al. Efficacy and safety of infliximab plus naproxen versus naproxen alone in patients with early, active axial spondyloarthritis. Ann Rheum Dis. 2014. — doi:10.1136/annrheumdis-2012-203201
- Dougados M, Dijkmans B, Khan M, et al. Conventional treatments for ankylosing spondylitis. Ann Rheum Dis. 2002;61 Suppl 3:iii40–50. — doi:10.1136/ard.61.suppl_3.iii40
- Oosterveld FG, Rasker JJ, Floors M, et al. Infrared sauna in patients with rheumatoid arthritis and ankylosing spondylitis. A pilot study showing good tolerance, short-term improvement of pain and stiffness, and a trend towards long-term beneficial effects. Clin Rheumatol. 2009;28(1):29–34. — PubMed PMID: 18685882
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on ankylosing spondylitis morning stiffness, circadian inflammation, and management strategies:
- PubMed: Ankylosing spondylitis and morning stiffness
- PubMed: Inflammatory back pain criteria (ASAS)
- PubMed: Modified-release NSAIDs in ankylosing spondylitis
- PubMed: Circadian cytokines, TNF and IL-6 in rheumatic disease
- PubMed: Exercise therapy for ankylosing spondylitis stiffness
- PubMed: Hydrotherapy and heat therapy in spondyloarthritis
- PubMed: BASDAI and ankylosing spondylitis disease activity
- PubMed: Infrared sauna and inflammatory arthritis
Connections
- Rheumatology
- Ankylosing Spondylitis
- Human Leukocyte Antigen-B27 Explained
- Biologics Guide
- Ankylosing Spondylitis and Inflammatory Bowel Disease Overlap
- Exercise and PT Protocol
- Nonsteroidal Anti-Inflammatory Drug Strategy
- Starch-Free Diet and Ebringer
- Pregnancy and Ankylosing Spondylitis
- Uveitis and Eye Involvement
- Arthritis
- Crohn's Disease
- Ulcerative Colitis
- Inflammatory Bowel Disease
- Inflammatory Markers
- Vitamin D3