Human Leukocyte Antigen-B27 Explained
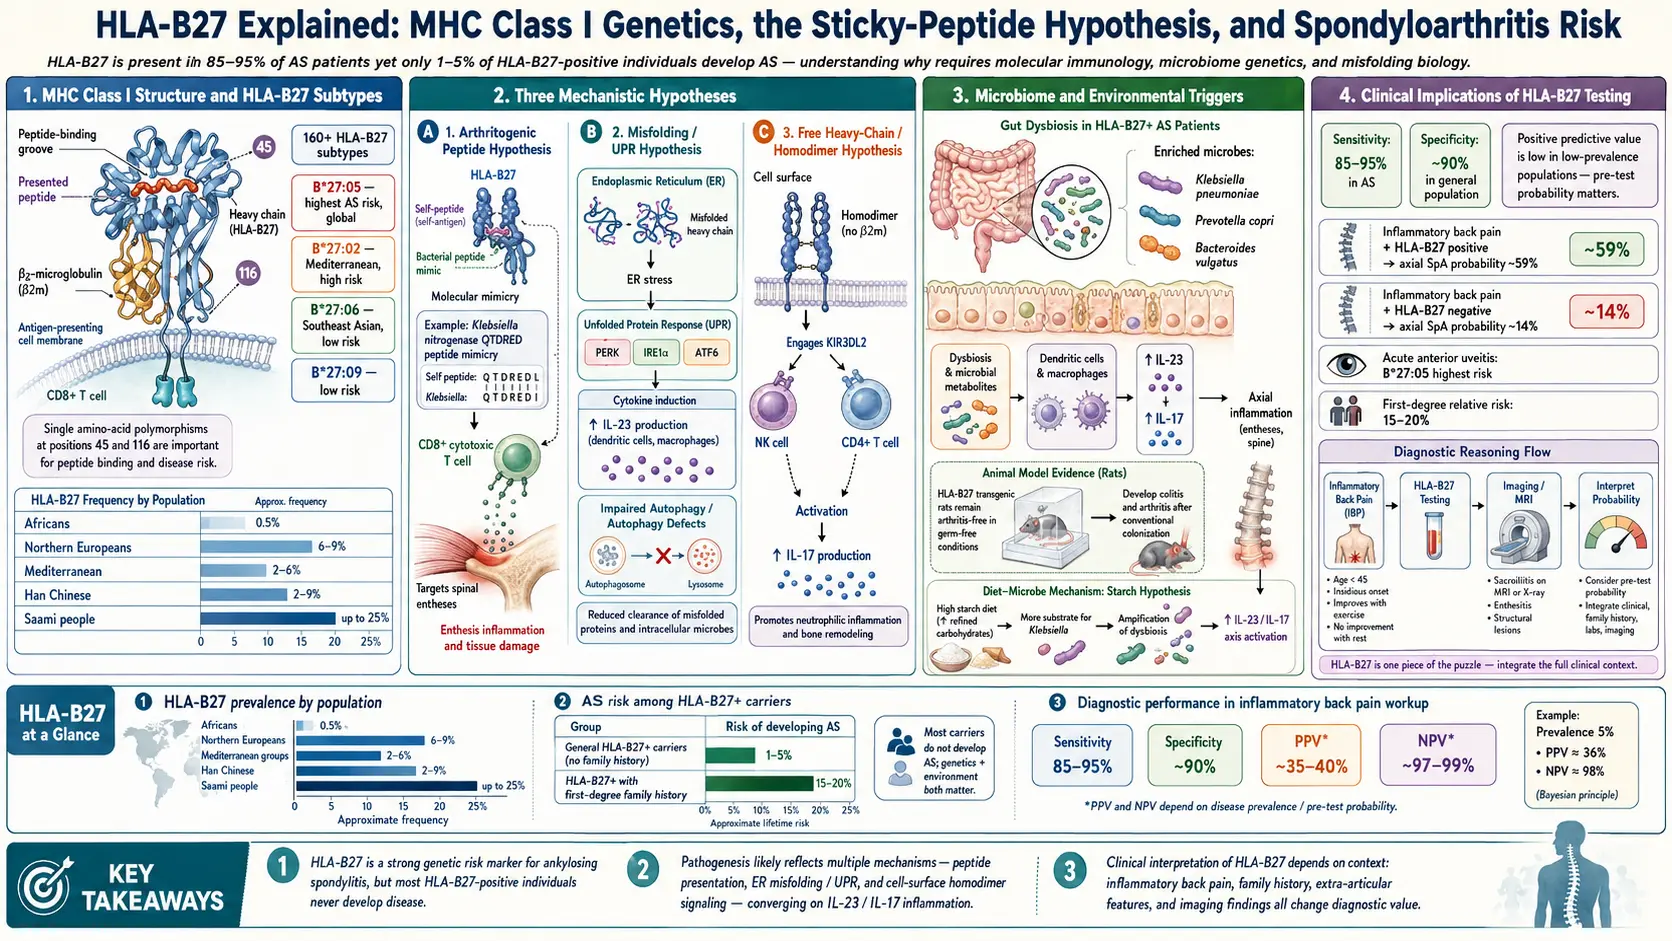
Table of Contents
- What Human Leukocyte Antigen-B27 Is
- The Ankylosing Spondylitis Connection by the Numbers
- Testing — How It Works
- Interpreting Your Result
- The 200+ Subtypes — Not All Equal
- Why Human Leukocyte Antigen-B27 Causes Ankylosing Spondylitis: The Three Leading Theories
- The Klebsiella Molecular Mimicry Angle
- Human Leukocyte Antigen-B27 and Other Related Diseases
- Extra-Articular Associations
- What a Positive Human Leukocyte Antigen-B27 Changes About Your Life
- Human Leukocyte Antigen-B27 Cannot Be Changed
- Testing Healthy Family Members
- Key Research Papers
- Connections
- Featured Videos
What Human Leukocyte Antigen-B27 Is
Human leukocyte antigen-B27 is a human leukocyte antigen — a protein sitting on the surface of almost every nucleated cell in your body. It is coded by a gene on the short arm of chromosome 6, inside the dense cluster of immune genes called the Major Histocompatibility Complex (MHC). Specifically, human leukocyte antigen-B27 is a class I MHC molecule, in the same family as human leukocyte antigen-A and human leukocyte antigen-C.
Its normal job is surveillance. Every cell continuously chops up a sample of the proteins it is producing and threads short peptide fragments (8–10 amino acids long) through its human leukocyte antigen-B molecule, presenting them on the cell surface like a tiny identification card. Passing CD8+ T cells inspect these cards. If the peptide looks foreign — viral, bacterial, or cancer-mutated — the T cell destroys the cell. If the peptide looks like normal self, the T cell moves on.
Human leukocyte antigen-B27 is just one of hundreds of human leukocyte antigen-B variants. Everyone inherits two human leukocyte antigen-B alleles (one from each parent), and the combination defines part of your immune fingerprint. Human leukocyte antigen-B27 is unusual only because of what it does — or fails to do — in the spines of the people who carry it.
The Ankylosing Spondylitis Connection by the Numbers
Human leukocyte antigen-B27 is the strongest known human leukocyte antigen-disease association in medicine. The raw statistics:
- 90–95% of ankylosing spondylitis (AS) patients carry human leukocyte antigen-B27.
- In the general population, prevalence varies enormously by ancestry: 6–8% of Caucasians, 4% of African Americans, 1% of Japanese, and up to 50% of Haida Native Americans on the Pacific Northwest coast.
- A carrier's lifetime risk of developing ankylosing spondylitis is only 5–16%.
- Family matters more than the gene alone. A Dutch study of people aged 45 or older found ankylosing spondylitis in 1.3% of human leukocyte antigen-B27-positive people in the general population, against 21% of human leukocyte antigen-B27-positive relatives of patients — a 16 times higher risk (van der Linden 1984).
That last number is the one most patients miss. Having human leukocyte antigen-B27 is necessary for ankylosing spondylitis in most people, but it is very far from sufficient. Roughly 85–95% of human leukocyte antigen-B27 carriers live a full life without ever developing spondyloarthritis. Something else — likely a combination of additional genes, gut microbes, and environmental exposures — pushes a minority across the threshold into disease.
Testing — How It Works
Human leukocyte antigen-B27 testing is a simple blood draw. The laboratory runs the sample on one of two platforms: flow cytometry, which uses a fluorescent antibody that binds human leukocyte antigen-B27 on white-blood-cell surfaces, or polymerase chain reaction (PCR), which amplifies the human leukocyte antigen-B gene directly from DNA and checks for the B27 sequence. Polymerase chain reaction is more specific; flow cytometry can occasionally cross-react with the closely related human leukocyte antigen-B7 allele and require confirmation.
The cost ranges from $50 to $150 at most U.S. commercial reference laboratories, and insurance typically covers it when ordered for ankylosing spondylitis workup. The relevant billing codes are CPT 86828 (human leukocyte antigen (HLA) antibody screening) or CPT 86812 (human leukocyte antigen typing, class I, single antigen).
You only need the test once in your life. Human leukocyte antigen-B27 status is genetic and cannot change. It is ordered by a primary care physician or rheumatologist, usually with the stated purpose "evaluation for spondyloarthritis," and it is a routine part of the workup for chronic inflammatory back pain.
Interpreting Your Result
A raw positive or negative is almost useless without the clinical picture. Four common scenarios:
Positive + ankylosing spondylitis symptoms. If you already have chronic inflammatory back pain (worse at rest, better with movement, lasting more than three months) plus magnetic resonance imaging (MRI) evidence of sacroiliitis, a positive human leukocyte antigen-B27 strongly supports the ankylosing spondylitis diagnosis. Combined with imaging, it usually closes the diagnostic question.
Positive + no symptoms. This is the most common scenario for family members who get tested. For a human leukocyte antigen-B27-positive person in the general population the lifetime risk of developing ankylosing spondylitis is put at 5–16%, so most carriers never develop it. For a positive relative of a patient the risk is higher (see Family screening below). No preventive (prophylactic) treatment is indicated; the practical point is that chronic back pain, if it ever appears, has a known possible cause.
Negative + ankylosing spondylitis symptoms. A negative human leukocyte antigen-B27 does not rule out ankylosing spondylitis. Between 5% and 10% of ankylosing spondylitis patients are human leukocyte antigen-B27 negative, with higher proportions in populations where B27 is rare (e.g., Middle Eastern or African cohorts). The diagnostic gold standard is magnetic resonance imaging of the sacroiliac joints, not genetics. When suspicion stays high, imaging is the next step in the standard workup.
Family screening. First-degree relatives (parents, siblings, children) of a human leukocyte antigen-B27-positive ankylosing spondylitis patient often carry the gene too: in a Dutch family study, 61 relatives tested positive and 40 negative, and 21% of the positive relatives aged 45 or older had ankylosing spondylitis, while none of the negative relatives had it (van der Linden 1984). A Swiss study that followed families for 35 years found that 48 of 177 human leukocyte antigen-B27-positive first-degree relatives — 27.1% — developed axial spondyloarthritis. Children of an affected mother were affected far more often (12 of 22, 54.5%) than children of an affected father (15 of 78, 19.2%), and children of patients whose sacroiliac (pelvic) joints showed changes on X-ray were affected more often (18.2%) than children of patients without such X-ray changes (4.0%) (van der Linden 2022). That is well above the general-population figure, though still a minority outcome.
The 200+ Subtypes — Not All Equal
"human leukocyte antigen-B27" is not one allele but a family. More than 200 sequence variants have been catalogued, named with a colon-separated suffix: B*27:01, B*27:02, B*27:03, and so on. A handful are clinically important:
- B*27:05 — the most common variant in people of European descent; strongly associated with ankylosing spondylitis.
- B*27:02 — seen in Mediterranean populations; also ankylosing spondylitis-associated.
- B*27:04 — the dominant East Asian variant; ankylosing spondylitis-associated.
- B*27:06 — common in Southeast Asia (Thailand, Indonesia); appears to be protective, meaning carriers rarely develop ankylosing spondylitis even though they are "human leukocyte antigen-B27 positive" by standard testing.
- B*27:09 — almost exclusive to Sardinia; also protective.
Standard clinical human leukocyte antigen-B27 testing reports only positive or negative. It does not distinguish which subtype you carry. Subtype resolution requires sequence-based human leukocyte antigen typing, usually only available through research labs or transplant centers. For most patients, subtyping does not change management, but it explains why some populations (particularly Southeast Asian) have high human leukocyte antigen-B27 prevalence yet low ankylosing spondylitis rates.
Why Human Leukocyte Antigen-B27 Causes Ankylosing Spondylitis: The Three Leading Theories
After fifty years of research, nobody has definitively proven the mechanism. Three hypotheses dominate the literature, and they are not mutually exclusive — all three may be partially right.
Arthritogenic Peptide Hypothesis
The oldest and most intuitive theory. Human leukocyte antigen-B27 has an unusually shaped peptide-binding groove that happens to present a specific self-peptide — possibly derived from joint cartilage, enthesis tissue, or gut epithelium. CD8+ T cells that recognize this peptide become autoreactive and attack the tissues where it appears. The starting trigger may be molecular mimicry: a bacterial peptide that closely resembles the self-peptide primes T cells during an infection, and those primed T cells then cross-react with self. Klebsiella pneumoniae is the most-studied candidate (see the starch-free diet article).
Misfolding Hypothesis
Human leukocyte antigen-B27 heavy chains fold inefficiently inside the endoplasmic reticulum of the cell that makes them. A fraction of every batch fails to pair properly with beta-2-microglobulin and instead misfolds or aggregates. The cell senses the pileup of misfolded protein and triggers the unfolded protein response (UPR), a stress pathway that activates inflammatory cytokines — particularly the IL-23/IL-17 axis. This is the same cytokine cascade targeted by modern ankylosing spondylitis biologics that block IL-17 (secukinumab, ixekizumab). Blocking IL-23 itself did not work in ankylosing spondylitis: in a 2018 trial of 159 patients, 15.0% on risankizumab 180 mg reached a 40% improvement score (ASAS40) at week 12, against 17.5% on placebo, which the researchers read as IL-23 possibly not being a relevant driver of the disease (Baeten 2018). See the biologics guide for how these drugs interrupt the pathway downstream.
Free Heavy Chain Hypothesis
On the surface of human leukocyte antigen-B27-positive cells, a minority of molecules appear not as the normal heterodimer (heavy chain plus beta-2-microglobulin) but as abnormal free heavy chain homodimers. These dysfunctional dimers bind receptors such as KIR3DL2 on natural killer cells and a subset of T-helper-17 cells. Binding activates these innate-like cells, feeding them survival signals and tilting them toward producing IL-17. This theory links human leukocyte antigen-B27 to innate immunity rather than classical CD8+ T-cell surveillance.
The Klebsiella Molecular Mimicry Angle
In the 1980s, Alan Ebringer and colleagues at King's College London noticed that short amino-acid sequences in two Klebsiella pneumoniae proteins (nitrogenase and pullulanase) closely resemble sequences in human leukocyte antigen-B27 itself and in human type I, III, and IV collagen. In laboratory studies, antibodies raised against Klebsiella cross-reacted with human leukocyte antigen-B27-positive cells and with connective tissue proteins.
Ebringer's group further argued that Klebsiella thrives in a gut environment rich in dietary starch, and proposed a low-starch diet to reduce the bacterial load and, with it, the immune cross-reaction. Small uncontrolled cohorts reported symptom improvement.
Mainstream rheumatology considers the Klebsiella hypothesis suggestive but not proven. Randomized controlled trials are lacking. The mechanism remains plausible, the dietary intervention is cheap and low-risk, and some patients swear by it — but it is not standard of care. See the starch-free diet page for the full protocol and evidence review.
Human Leukocyte Antigen-B27 and Other Related Diseases
Ankylosing spondylitis is the flagship human leukocyte antigen-B27 disease, but the entire spondyloarthropathy family clusters around the gene:
- Ankylosing spondylitis — 90–95% human leukocyte antigen-B27 positive.
- Reactive arthritis (formerly Reiter syndrome) — 60–80% positive. Triggered by gut or genitourinary infections.
- Psoriatic arthritis with axial involvement — 50–70% positive.
- Inflammatory bowel disease-associated spondyloarthropathy — 50–70% positive. See the ankylosing spondylitis & inflammatory bowel disease (IBD) overlap article.
- Acute anterior uveitis — about 50% positive. One of the most common non-AS presentations.
- Undifferentiated spondyloarthropathy — roughly 70% positive. A catch-all for patients with inflammatory features that do not yet meet criteria for a specific diagnosis.
Extra-Articular Associations
Human leukocyte antigen-B27 predisposes to a small set of conditions beyond the joints. They matter because they often appear years before or after spinal disease.
- Acute anterior uveitis — sudden painful red eye, light sensitivity, blurred vision. Can occur decades before ankylosing spondylitis back pain or long after diagnosis. Eye doctors treat it as urgent; untreated episodes can damage vision.
- Aortitis and aortic valve disease — inflammation of the ascending aorta leading, in rare cases, to aortic regurgitation.
- Immunoglobulin A (IgA) nephropathy — a kidney disorder in which immunoglobulin A antibodies deposit in the glomeruli; increased prevalence in human leukocyte antigen-B27 cohorts.
- Cardiac conduction abnormalities — most commonly atrioventricular (AV) block. An electrocardiogram (ECG) is the test that detects it in long-standing ankylosing spondylitis.
- Pulmonary apical fibrosis — a late, rare complication seen in advanced ankylosing spondylitis; mimics tuberculosis on chest imaging.
What a Positive Human Leukocyte Antigen-B27 Changes About Your Life
For most people, surprisingly little. A few practical points follow from it:
- Long-term vigilance. The warning sign is chronic inflammatory back pain — back pain that lasts more than three months, starts before age 45, is worse at rest, and improves with movement. It is the main reason for a medical evaluation in a carrier.
- Family risk. First-degree relatives often carry human leukocyte antigen-B27 themselves, and in a 35-year Swiss family study 27.1% of positive first-degree relatives developed axial spondyloarthritis (van der Linden 2022).
- Imaging. If inflammatory back pain does appear, magnetic resonance imaging (MRI) of the sacroiliac joints can show inflammation years before plain radiographs change.
- Eye symptoms. Uveitis is vision-threatening if untreated. Its signs — sudden eye pain, redness, light sensitivity — are treated by eye doctors as same-day urgent.
- Not a reason for panic. 85–95% of human leukocyte antigen-B27 carriers never develop ankylosing spondylitis. The gene is a probability, not a sentence.
Survival. In UK Biobank (407,480 people of European ancestry), carrying human leukocyte antigen-B27 was not linked to any change in survival (hazard ratio 1.0), in men or women, and did not raise the risk of death from vascular disease. In a Swiss cohort, people with ankylosing spondylitis did have higher death rates than the general population (standardised mortality ratio 1.37), highest in human leukocyte antigen-B27-positive women with the disease (1.77); people with non-radiographic axial spondyloarthritis had a lower death rate than the general population (0.44) (Li 2023).
Human Leukocyte Antigen-B27 Cannot Be Changed
No. Human leukocyte antigen-B27 is a fixed genetic variant you inherited at conception. Nothing — no diet, no supplement, no drug, no epigenetic intervention — can remove it or silence it.
What you can influence is the environment in which that gene operates:
- Gut health and infections. Researchers have proposed that fewer unnecessary antibiotic courses, prompt treatment of gut (enteric) infections and a diverse microbiome may reduce the inflammatory triggers that push human leukocyte antigen-B27 toward disease.
- Exercise and posture. Regular movement, extension-based physiotherapy, and daily spinal mobility work slow the progression of spinal fusion once ankylosing spondylitis is established. See the exercise and PT protocol.
- Diet. The Klebsiella-starch hypothesis remains controversial; the low-starch diet costs little, and its proponents describe it as low-risk.
- Biologic therapy timing. Evidence is growing that earlier initiation of tumor necrosis factor (TNF) or IL-17 inhibitors may alter long-term disease trajectory. See the biologics guide.
Testing Healthy Family Members
Routine testing of healthy relatives is not standard practice. A positive result in a healthy person changes very little about their care — the warning signs (inflammatory back pain, uveitis) are the same for everyone. Reasons people give for testing include:
- Planning a family and wanting a risk estimate for children.
- Already developing symptoms suggestive of ankylosing spondylitis (inflammatory back pain over three months, onset before age 45).
- A personal desire for certainty that the anxiety of not knowing outweighs.
Insurance considerations. A positive human leukocyte antigen-B27 is part of your medical record and may affect some life insurance, disability insurance, or long-term care applications. The U.S. Genetic Information Nondiscrimination Act (GINA) protects against employment and health-insurance discrimination but does not cover life, disability, or long-term care insurance. State laws vary. For this reason some people arrange life, disability or long-term care coverage before being tested. It is a real trade-off.
Key Research Papers
- International Genetics of Ankylosing Spondylitis Consortium (IGAS), Cortes A, Hadler J, Pointon JP, et al. Identification of multiple risk variants for ankylosing spondylitis through high-density genotyping of immune-related loci. Nat Genet. 2013;45(7):730–738. — doi:10.1038/ng.2667 · PubMed PMID: 23749187
- Colbert RA, Tran TM, Layh-Schmitt G. HLA-B27 misfolding and ankylosing spondylitis. Mol Immunol. 2014;57(1):44–51. — doi:10.1016/j.molimm.2013.07.013 · PubMed PMID: 23993278
- Bowness P. HLA-B27. Annu Rev Immunol. 2015;33:29–48. — doi:10.1146/annurev-immunol-032414-112110 · PubMed PMID: 25861975
- Rashid T, Wilson C, Ebringer A. The link between ankylosing spondylitis, Crohn's disease, Klebsiella, and starch consumption. Clin Dev Immunol. 2013;2013:872632. — doi:10.1155/2013/872632 · PubMed PMID: 23781254 (Klebsiella-AS link reference.)
- van der Linden SM, Valkenburg HA, de Jongh BM, Cats A. The risk of developing ankylosing spondylitis in HLA-B27 positive individuals. A comparison of relatives of spondylitis patients with the general population. Arthritis Rheum. 1984;27(3):241–249. — doi:10.1002/art.1780270301 · PubMed PMID: 6608352
- van der Linden SM, Khan MA, Li Z, Baumberger H, Zandwijk HV, Khan MK, Villiger PM, Brown MA. Recurrence of axial spondyloarthritis among first-degree relatives in a prospective 35-year-follow-up family study. RMD Open. 2022;8(2):e002208. — doi:10.1136/rmdopen-2022-002208 · PubMed PMID: 35868737
- Baeten D, Østergaard M, Wei JC, Sieper J, Järvinen P, Tam LS, Salvarani C, Kim TH, Solinger A, Datsenko Y, Pamulapati C, Visvanathan S, Hall DB, Aslanyan S, Scholl P, Padula SJ. Risankizumab, an IL-23 inhibitor, for ankylosing spondylitis: results of a randomised, double-blind, placebo-controlled, proof-of-concept, dose-finding phase 2 study. Ann Rheum Dis. 2018;77(9):1295–1302. — doi:10.1136/annrheumdis-2018-213328 · PubMed PMID: 29945918
- Li Z, Khan MK, van der Linden SM, Winkens B, Villiger PM, Baumberger H, van Zandwijk H, Khan MA, Brown MA. HLA-B27, axial spondyloarthritis and survival. Ann Rheum Dis. 2023;82(12):1558–1567. — doi:10.1136/ard-2023-224434 · PubMed PMID: 37679034
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on human leukocyte antigen-B27 biology, disease association, and management:
- PubMed: HLA-B27 and ankylosing spondylitis
- PubMed: HLA-B27 subtypes and protective variants
- PubMed: HLA-B27 misfolding and the unfolded protein response
- PubMed: HLA-B27, Klebsiella, and molecular mimicry
- PubMed: HLA-B27 and acute anterior uveitis
- PubMed: HLA-B27 family screening and first-degree relative risk
- PubMed: HLA-B27 population prevalence and ancestry
- PubMed: HLA-B27 free heavy chains and KIR3DL2
Connections
- Rheumatology
- Ankylosing Spondylitis
- Biologics Guide
- Ankylosing Spondylitis and Inflammatory Bowel Disease Overlap
- Exercise and PT Protocol
- Nonsteroidal Anti-Inflammatory Drug Strategy
- Morning Stiffness Management
- Starch-Free Diet and Ebringer
- Pregnancy and Ankylosing Spondylitis
- Uveitis and Eye Involvement
- Arthritis
- Crohn's Disease
- Ulcerative Colitis
- Psoriasis
- Klebsiella Pneumoniae
- Inflammatory Markers
- Extraintestinal Manifestations of Inflammatory Bowel Disease
- Chronic Low Back Pain Evidence Based Care
- Genetic Testing HLA DQ2 and DQ8