⚠ Evidence warning: Clinical trials or other evidence do not support the claims that exercise is a disease-modifying intervention that disrupts spinal fusion, that people who exercise keep mobility and independence for decades longer, that most progression happens at work, that every rheumatologist points to the pool first, the stated timelines for improvement, and that exercise plus biologics changes the disease course. This page keeps it as a report of what people, websites or other media say.
Exercise and PT Protocol for Ankylosing Spondylitis
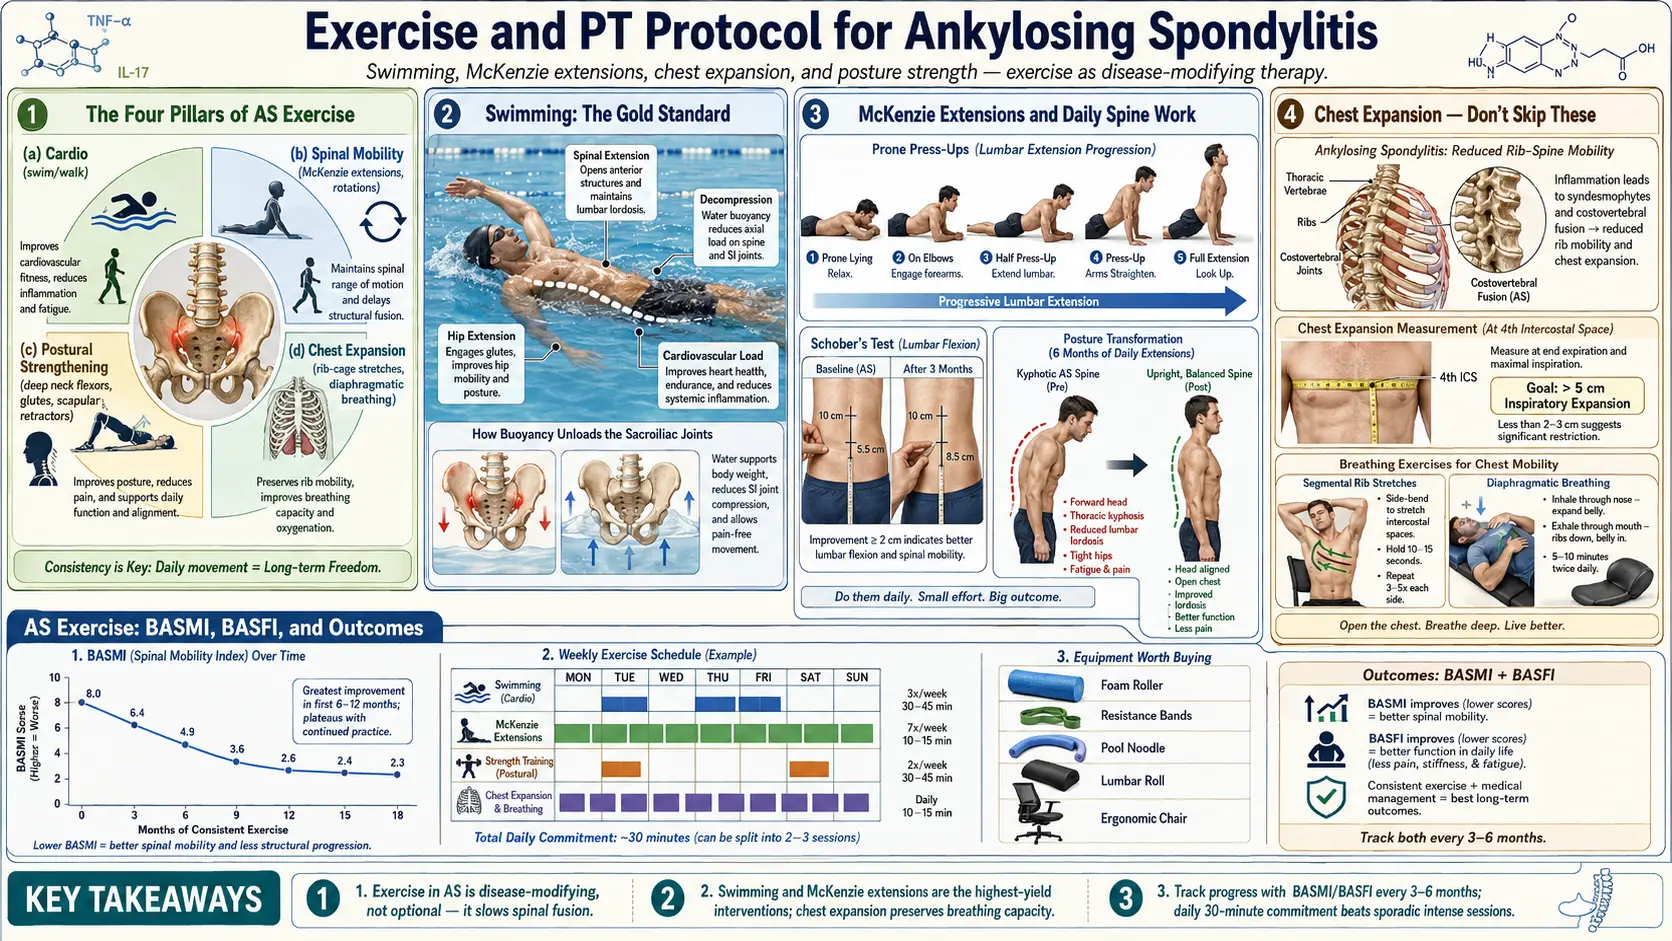
Table of Contents
- What Exercise Does in Ankylosing Spondylitis
- The Four Pillars of Ankylosing Spondylitis Exercise
- Swimming and Pool Exercise
- McKenzie Extension Exercises
- Posture-Correction Strength Work
- Yoga for Ankylosing Spondylitis
- A Sample Weekly Schedule — McKenzie + Strength + Swim
- Chest Expansion Exercises
- How Progress Is Measured: BASMI, BASFI and BASDAI
- Exercise During a Flare
- How High-Impact Activities Affect the Spine
- Low-Cost Equipment
- Working With a Physical Therapist
- Workplace Strategies
- Timeline: What the Trials Measured
- Exercise Organisations and Resources
- Key Research Papers
- Connections
- Featured Videos
1. What Exercise Does in Ankylosing Spondylitis
Most forms of arthritis improve with rest. Ankylosing spondylitis does the opposite: stiffness typically eases with movement and worsens with rest. Physiotherapists and patient groups often call ankylosing spondylitis (AS) a "use-it-or-lose-it" disease. Ankylosing spondylitis (AS) is a "use-it-or-lose-it" disease, and that phrase is not a motivational slogan — it is a structural fact about how inflamed axial tissues behave when they stop moving.
In ankylosing spondylitis, chronic inflammation at entheses (where ligaments and tendons attach to bone) and facet joints drives new bone formation along the margins of the vertebrae. When an inflamed enthesis or facet joint goes unused, the chronic inflammation drives new bone formation along the margins. Over months and years, those bony bridges (syndesmophytes) extend, meet, and fuse adjacent vertebrae. Many physiotherapists describe inactivity as speeding this up, and movement — especially extension — as working against it; that is a practice view rather than a trial result.
Movement — specifically, extension — disrupts it. Long-term cohort studies consistently show that ankylosing spondylitis patients who exercise regularly retain spinal mobility and functional independence for decades longer than sedentary patients, even when baseline disease severity is matched. Exercise is not an adjunct to biologic therapy; it is a parallel disease-modifying intervention. Every inch of spinal extension you preserve is an inch of independence you keep. In this view, exercise is not "working out"; it is a structural intervention against a progressive fusion process. Skip a week of swimming and you are not just losing fitness — you are giving inflamed tissue a window to calcify.
What the trials show: a 2019 Cochrane review (14 randomised trials, 1,579 people with ankylosing spondylitis, most also taking drug or biologic treatment) found that, compared with no exercise programme, exercise programmes probably slightly improve physical function (about 1.3 points better on the 0–10 BASFI scale) and may reduce pain (about 2.1 points on a 0–10 scale), measured at the end of the programme. Compared with usual care, they probably made little or no difference to function or pain. The reviewers were uncertain whether exercise programmes improve spinal mobility, and only one trial followed people for more than 24 weeks after the programme ended.
The 2022 ASAS-EULAR recommendations (the international guidance for axial spondyloarthritis, updating the 2016 version) place non-drug management, including exercise, among the first steps, alongside anti-inflammatory painkillers (non-steroidal anti-inflammatory drugs, NSAIDs) as the first-choice drug. Biologic drugs (tumour necrosis factor (TNF) inhibitors or interleukin-17 (IL-17) inhibitors) or Janus kinase (JAK) inhibitors come next for people whose disease stays active after at least two NSAIDs.
2. The Four Pillars of Ankylosing Spondylitis Exercise
Exercise programmes for ankylosing spondylitis usually combine four categories. The exercises used most often in the Cochrane trials were those for strength, flexibility, stretching and breathing. Drop any one and the others lose value.
- Extension and mobility — moving the spine in all directions, with a bias toward extension, which is the range ankylosing spondylitis usually takes first.
- Cardiovascular — low-impact, sustained activity to keep aerobic capacity as the chest wall stiffens.
- Strength — postural muscles especially: core, back extensors, rhomboids, mid-traps, glutes.
- Deep breathing — the rib joints at the spine (costovertebral) and breastbone (sternocostal) are vulnerable to fusion; expansion exercises are used to keep them moving.
Some physiotherapists suggest that people with only 20 minutes a day split it: 10 minutes of extension/mobility work plus 10 minutes of swimming, strength, or breathing, rotating the second block across the week.
3. Swimming and Pool Exercise
Pool exercise is one of the most common parts of ankylosing spondylitis rehabilitation. Every rheumatologist and ankylosing spondylitis-experienced physical therapist will point you at the pool first, and the reasons are mechanical, not sentimental. In a randomised trial of 69 people with ankylosing spondylitis, 4 weeks of pool exercise (20 sessions, 5 per week, in water at 32–33 °C) improved pain and quality of life more than a home exercise booklet. Both groups improved in spinal mobility, chest expansion, BASMI, BASFI and BASDAI at weeks 4 and 12. A 2008 Cochrane review found that a 3-week inpatient spa-exercise course followed by weekly group physiotherapy did better than group physiotherapy alone (see section 13).
How it works
Buoyancy offloads the spine, so people can move through ranges that are painful on land. Water provides graded resistance in all directions, training muscles without impact. Physiotherapists describe extension-dominant strokes as working against the flexion pattern ankylosing spondylitis imposes over years of hunching.
Strokes commonly used
- Backstroke — often described as the most suitable stroke. The spine is held in extension, shoulders open, neck neutral to slightly extended.
- Elementary backstroke — slower, gentler on shoulders, often used during flares.
- Sidestroke — spares the neck, works obliques.
Strokes some programmes modify
- Breaststroke — involves heavy cervical flexion and extension cycling that can aggravate an already stiff neck.
- Freestyle — workable for people who can rotate to breathe without pain; a snorkel is an option when neck rotation is limited.
Frequency, temperature, tools
Programmes commonly describe 3–5 sessions per week, 30–45 minutes each, in warm water (82–88°F / 28–31°C); cold pools are reported to increase stiffness and spasm. Hydrotherapy pools around 92°F are often used during flares; the trial above used 32–33 °C water.
Common pool tools: a pull buoy to isolate the upper body, a kickboard for legs-only work, and short fins that encourage hip extension without demanding ankle range.
4. McKenzie Extension Exercises
The McKenzie Method, developed by New Zealand physiotherapist Robin McKenzie, uses repeated end-range extension of the spine. In ankylosing spondylitis programmes it is used as a counter to the flexed posture the disease tends to produce.
The four core movements
- Press-ups (prone extensions) — lying face down, hands flat under the shoulders, the chest is pressed up while the pelvis stays on the floor. Held 2–3 seconds, 10 reps.
- Standing backbends — hands on the lower back, feet shoulder-width, a gentle lean back into extension. 10 reps. Often used as a desk-break movement.
- Cat-cow — on hands and knees, alternating between an arched-back extension and a rounded-back flexion, moving every segment through its range. 10 cycles.
- Foam roller extension — lying on the back with a foam roller across the upper-mid back, arms overhead, the upper spine draped over the roller, which is moved inch by inch from mid-back to the shoulder blades.
Programmes typically describe doing these daily, often twice a day — on waking (when morning stiffness is worst) and before bed — for a total of 10–15 minutes, with no equipment cost beyond a foam roller. This is the cheapest, highest-leverage thing you will ever do for your spine.
5. Posture-Correction Strength Work
Ankylosing spondylitis pushes the body toward a rounded upper back (thoracic kyphosis), a forward head, and pelvic tilt. Strength programmes target the muscles that pull against each of these.
Upper body (postural)
- Rhomboid and mid-trap rows — with bands, cables, or a low-row machine, squeezing the shoulder blades together at the end of the movement.
- Face pulls — a rope pulled toward the forehead with the arms rotating outward; widely used as a posture exercise for desk workers.
- Wall angels — slow "snow angels" pressed flat against a wall; they also show plainly how much upper-back mobility is left.
Core without spinal flexion
- Dead bug — lying on the back, extending the opposite arm and leg. Deep core work without crunching.
- Bird dog — on hands and knees, opposite arm and leg out, spine neutral. Trains resistance to rotation.
- Plank — short holds (20–40 sec) with the ribs pulled down and the lower back kept from sagging.
Lower body + posterior chain
- Glute bridges — opens the hips, works the glutes, counters forward pelvic tilt.
- Hip flexor stretches (couch stretch) — one shin up a wall, front foot flat, torso upright, held 90 seconds per side. Tight hip flexors pull the pelvis forward and deepen the lower-back curve; programmes for desk workers often include this daily.
- Quad stretches — same logic; tight quads tilt the pelvis forward.
Programmes commonly describe 3 sessions per week, 30–45 minutes, with moderate loads, slow tempo and full range, and leave heavy spinal loading out until posture is stable.
6. Yoga for Ankylosing Spondylitis
Yoga teachers and physiotherapists describe yoga as a good fit for ankylosing spondylitis when the style is gentle and poses are modified; vigorous styles are reported to inflame the sacroiliac (SI) joints.
Poses commonly used
Extension-dominant, chest-opening shapes: cobra, upward-facing dog, sphinx, bridge, fish pose, locust, camel, and — once mobility permits — king cobra and wheel. These work against the ankylosing spondylitis flexion pattern.
Poses and styles often modified or left out
- Aggressive forward folds — approached gradually, without forcing the range.
- Binding twists — bound revolved poses stress the sacroiliac joints, which are already the centre of ankylosing spondylitis inflammation.
- Hot yoga — dehydration plus aggressive flows is described as a poor fit for ankylosing spondylitis.
- Power vinyasa — repeated chaturanga loads the shoulders and compresses the neck.
Props, styles, teachers
Props — blocks, bolsters, straps, chairs — are used generously to prevent compensating movements. Styles most often named for ankylosing spondylitis are Iyengar (prop-heavy, precise alignment), gentle Hatha, and restorative, at 2–3 sessions per week. Teachers vary in their experience with ankylosing spondylitis or inflammatory arthritis, and many people tell the teacher about their condition before the first class.
7. A Sample Weekly Schedule — McKenzie + Strength + Swim
This is an example of a weekly template that covers all four pillars. Physical therapists build programmes individually; the trials in the Cochrane review lasted a median of 12 weeks.
- Monday: 30-min swim (backstroke focus) + 10-min morning McKenzie.
- Tuesday: strength training (upper back + core: rows, face pulls, dead bug) + evening McKenzie.
- Wednesday: 30-min swim or yoga (Iyengar) + morning and evening McKenzie.
- Thursday: strength training (lower body + posterior chain: bridges, hip flexor stretches, bird dog) + evening McKenzie.
- Friday: yoga (restorative or gentle Hatha) + morning McKenzie.
- Saturday: long swim (45–60 min) or a hike on soft terrain.
- Sunday: rest day — McKenzie only, morning and evening.
In this template McKenzie appears every day as the fixed core; the swim/strength/yoga rotation is the part that moves around work and family life.
8. Chest Expansion Exercises
Fusion of the rib joints (costovertebral and sternocostal) is one of the less discussed consequences of ankylosing spondylitis. When the ribs stop moving, lung capacity drops, exercise tolerance falls, and pneumonia risk rises. Breathing exercises were among the exercise types used most often in the Cochrane trials.
The drills
- Diaphragmatic breathing — lying on the back, hand on the belly, inhaling 4 seconds to expand the belly, exhaling 6 seconds. 10 cycles, twice daily.
- Rib-cage expansion with a band — a resistance band looped around the lower chest, inhaling against the band, then exhaling and releasing. 10 reps.
- Thoracic rotation — book openers — lying on one side, knees bent, the top arm "opens" like a book, with the eyes following it. 10 per side.
- Supine windshield wipers — lying on the back, knees bent, feet together, the knees drop side to side while the shoulders stay flat.
Measuring chest expansion
Chest expansion is measured with a tape measure at nipple level (fourth intercostal space) as deep inhale minus full exhale. Normal adult expansion is greater than 5 cm; ankylosing spondylitis progression is suspected below 2.5 cm. Some people record it monthly, because a falling number can show rib joints tightening before breathing tests (spirometry) change.
9. How Progress Is Measured: BASMI, BASFI and BASDAI
Three validated scores, all free to calculate, give an objective read on the course of the disease. They are also the outcome measures used in the exercise trials described on this page.
- BASMI (Bath Ankylosing Spondylitis Metrology Index) — a 5-measure spinal mobility score: cervical rotation, tragus-to-wall distance, lumbar side flexion, lumbar forward flexion (modified Schober), and intermalleolar distance. Scored 0–10; higher is worse. Usually measured by a physical therapist, often every 6 months.
- BASFI (Bath Ankylosing Spondylitis Functional Index) — a 10-question self-reported function score. Each answer is on a 0–10 scale and the scores are averaged. Many people track it monthly.
- BASDAI (Bath Ankylosing Spondylitis Disease Activity Index) — 6 questions on fatigue, pain, stiffness. The usual activity score at rheumatology visits.
Free online calculators exist for all three. Dated forms show a trend over time, and many people bring that trend to rheumatology appointments. A flat or improving BASMI over 12 months on the current regimen is taken as a sign that a programme is working.
10. Exercise During a Flare
Physiotherapists describe stopping all movement during a flare as counterproductive: deconditioning sets in within days, and stiffness builds. The inflamed tissues you "rest" are the same ones that fuse when still.
- Gentle movement continues. Walking, warm-water swimming, and restorative yoga are the usual choices.
- Reduced load: roughly 30% of normal duration, 50% of normal intensity is a commonly described rule of thumb.
- Heat before exercise — a heating pad on the lower back for 10 minutes, or a warm shower — is reported to reduce stiffness markedly.
- Ice after acute flare sessions — 10–15 minutes on the most inflamed area.
- A longer morning routine: 15–20 minutes of gentle stretching before getting out of bed. See Morning Stiffness Management for the full wake-up routine.
11. How High-Impact Activities Affect the Spine
Some activities sit in a gray zone: how they affect a person depends on disease stage, how much of the spine has fused, and the symptom pattern.
- Running — possible, but pounding stresses the sacroiliac joints. Runners with ankylosing spondylitis often use soft surfaces (trails, track), replace shoes every 300–500 miles, and walk first to warm up.
- Contact sports — a serious hazard when the neck (cervical spine) is involved. A fused cervical spine fractures rather than flexes under impact, and neck fractures in ankylosing spondylitis are disproportionately fatal.
- Weightlifting — moderate loads are widely used. Heavy spinal compression (loaded back squats, heavy conventional deadlifts) carries more risk in advanced disease; trap-bar or goblet variants load the spine less.
- Cycling — the flexed road-bike posture is the same shape ankylosing spondylitis tends to lock the spine into. Upright bikes, recumbents, or hybrid geometry with raised handlebars keep the spine more upright than drop handlebars.
12. Low-Cost Equipment
A home gym is not needed. A short list of cheap tools covers most of the exercises on this page.
- Pull buoy + kickboard — about $20 combined.
- Foam roller — a basic 36-inch high-density roller ($25–$35), or a textured roller for firmer pressure.
- Resistance bands — a set of bands covers rows, face pulls, and rib-expansion drills.
- Yoga blocks + strap — around $20; they make many poses reachable without forcing.
- Stability ball — some people alternate it with a desk chair 20–30 minutes at a time.
- Mattress — medium-firm rather than plush is the usual description. See Morning Stiffness Management for specifics.
- Ergonomic workstation — standing desk, monitor at eye level, chair with lumbar support.
13. Working With a Physical Therapist
A good physical therapist is worth more than any piece of equipment. A physical therapist measures BASMI, spots compensating movements a person cannot see, and adjusts the load. The 2008 Cochrane review of physiotherapy for ankylosing spondylitis (11 trials, 763 people) found:
- Home or supervised exercise programmes did better than no programme (low-quality evidence; spinal mobility differences of 5–50%).
- Supervised group physiotherapy gave small extra gains over an individual home programme (spinal mobility 7.5–18%; patient global assessment 1.46 cm better; moderate-quality evidence).
- A 3-week inpatient spa-exercise course followed by 37 weeks of weekly group physiotherapy did better than weekly group physiotherapy alone for pain (18%), physical function (24%) and patient global assessment (27%).
How people reach a physical therapist and what it involves:
- Referral — usually through the rheumatologist. Physical therapists experienced with ankylosing spondylitis are often preferred, because general orthopedic programmes are sometimes flexion-biased, which practitioners say can make ankylosing spondylitis worse.
- The first 6–12 sessions usually set baseline measurements, teach form, and individualize the home programme.
- Insurance in the US often covers 30–60 visits per calendar year, frequently with prior authorization rules.
- Credentials physical therapists may hold include the APTA-recognized Certified Orthopaedic Specialist (OCS), Certified Manual Therapist, or Certified Functional Manual Therapist (CFMT).
- Hydrotherapy-equipped clinics with a warm therapy pool on site offer the pool-based programmes described in section 3. Such clinics are the gold standard for early-intensive ankylosing spondylitis rehab.
14. Workplace Strategies
Long working weeks spent in a flexed, seated posture are where many people with ankylosing spondylitis say they lose the most ground. Most ankylosing spondylitis progression happens during 40-hour weeks spent in a flexed posture. The workplace is where the disease wins or loses ground.
- Sit-stand desk — alternating positions every 30–60 minutes. Neither sitting nor standing all day is healthy; changing is.
- Walking meetings when the meeting does not need a screen.
- Hourly stretch breaks — 30–60 seconds of standing backbends each hour, often prompted by a timer, add up to 8+ minutes of extension per workday.
- Monitor and keyboard height — screen top at eye level, elbows at 90°, wrists neutral.
- Car posture — a lumbar roll, little seat recline, and a stop every 90 minutes on long drives for extension work.
15. Timeline: What the Trials Measured
People often ask when results appear. In the 2019 Cochrane review, exercise programmes lasted a median of 12 weeks (most between 8 and 16 weeks), and every trial measured results at the end of the programme. That is when the gains in function and pain described in section 1 were seen. Only three trials (146 people) reported medium-term follow-up and one trial (63 people) followed people beyond 24 weeks, so how long the benefits last is not well known.
In the pool trial (section 3), improvements were measured at weeks 4 and 12. Subjective improvement — reduced stiffness, better sleep, more morning mobility — typically appears in 8–12 weeks of consistent practice. You will notice it before the tape measure does. Objective BASMI improvement takes 6–12 months of consistent work and may plateau thereafter. Some spinal fusion is irreversible; exercise programmes aim to preserve the movement a person has, not to reverse bony bridges.
In the Cochrane trials most participants were also taking drug or biologic treatment. The best long-term outcomes appear in cohort data on patients who combine regular exercise with biologic therapy. Exercise plus biologics is a different disease course. See the Biologics Guide for how tumor necrosis factor (TNF) inhibitors and IL-17 blockers fit alongside an exercise programme.
16. Exercise Organisations and Resources
Shared routines and groups help many people keep exercising. Free resources include:
- NASS (National Ankylosing Spondylitis Society, UK) — a patient charity that publishes free exercise videos.
- Spondylitis Association of America (SAA) — a patient organisation with an exercise guide, local support groups, and aquatic programme directories.
- Online exercise videos — free video channels with routines aimed at ankylosing spondylitis.
- Pain-education apps — apps offering pain-neuroscience education and guided practices for chronic pain.
Key Research Papers
- van der Heijde D, et al. 2016 update of the ASAS-EULAR management recommendations for axial spondyloarthritis. Annals of the Rheumatic Diseases. 2017. — doi:10.1136/annrheumdis-2016-210770
- Regnaux JP, Davergne T, Palazzo C, et al. Exercise programmes for ankylosing spondylitis. Cochrane Database of Systematic Reviews. 2019;10(10):CD011321. — PubMed PMID: 31578051
- Dagfinrud H, et al. Physiotherapy interventions for ankylosing spondylitis. Cochrane Database of Systematic Reviews. 2008. PubMed PMID: 18254008
- Ramiro S, Nikiphorou E, Sepriano A, et al. ASAS-EULAR recommendations for the management of axial spondyloarthritis: 2022 update. Annals of the Rheumatic Diseases. 2023;82(1):19-34. — PubMed PMID: 36270658
- Dundar U, Solak O, Toktas H, et al. Effect of aquatic exercise on ankylosing spondylitis: a randomized controlled trial. Rheumatology International. 2014;34(11):1505-1511. — PubMed PMID: 24626605
PubMed Topic Searches
Curated PubMed topic searches — each link opens a live query so you always see the most recent literature.
- PubMed: Ankylosing spondylitis exercise therapy
- PubMed: Ankylosing spondylitis hydrotherapy
- PubMed: BASMI / BASFI outcome measures
- PubMed: Ankylosing spondylitis and yoga
- PubMed: Spinal mobility in axial spondyloarthritis
- PubMed: Physiotherapy for spondylitis
- PubMed: Chest expansion in AS
- PubMed: McKenzie extension therapy
Connections
- Rheumatology
- Ankylosing Spondylitis
- Human Leukocyte Antigen-B27 Explained
- Biologics Guide
- Ankylosing Spondylitis and Inflammatory Bowel Disease Overlap
- Nonsteroidal Anti-Inflammatory Drug Strategy
- Morning Stiffness Management
- Starch-Free Diet and Ebringer
- Pregnancy and Ankylosing Spondylitis
- Uveitis and Eye Involvement
- Arthritis
- Tendinitis
- Chronic Pain
- Chronic Fatigue Syndrome
- Inflammatory Markers
- Exercise Pacing and Graded Movement