Pregnancy and Ankylosing Spondylitis
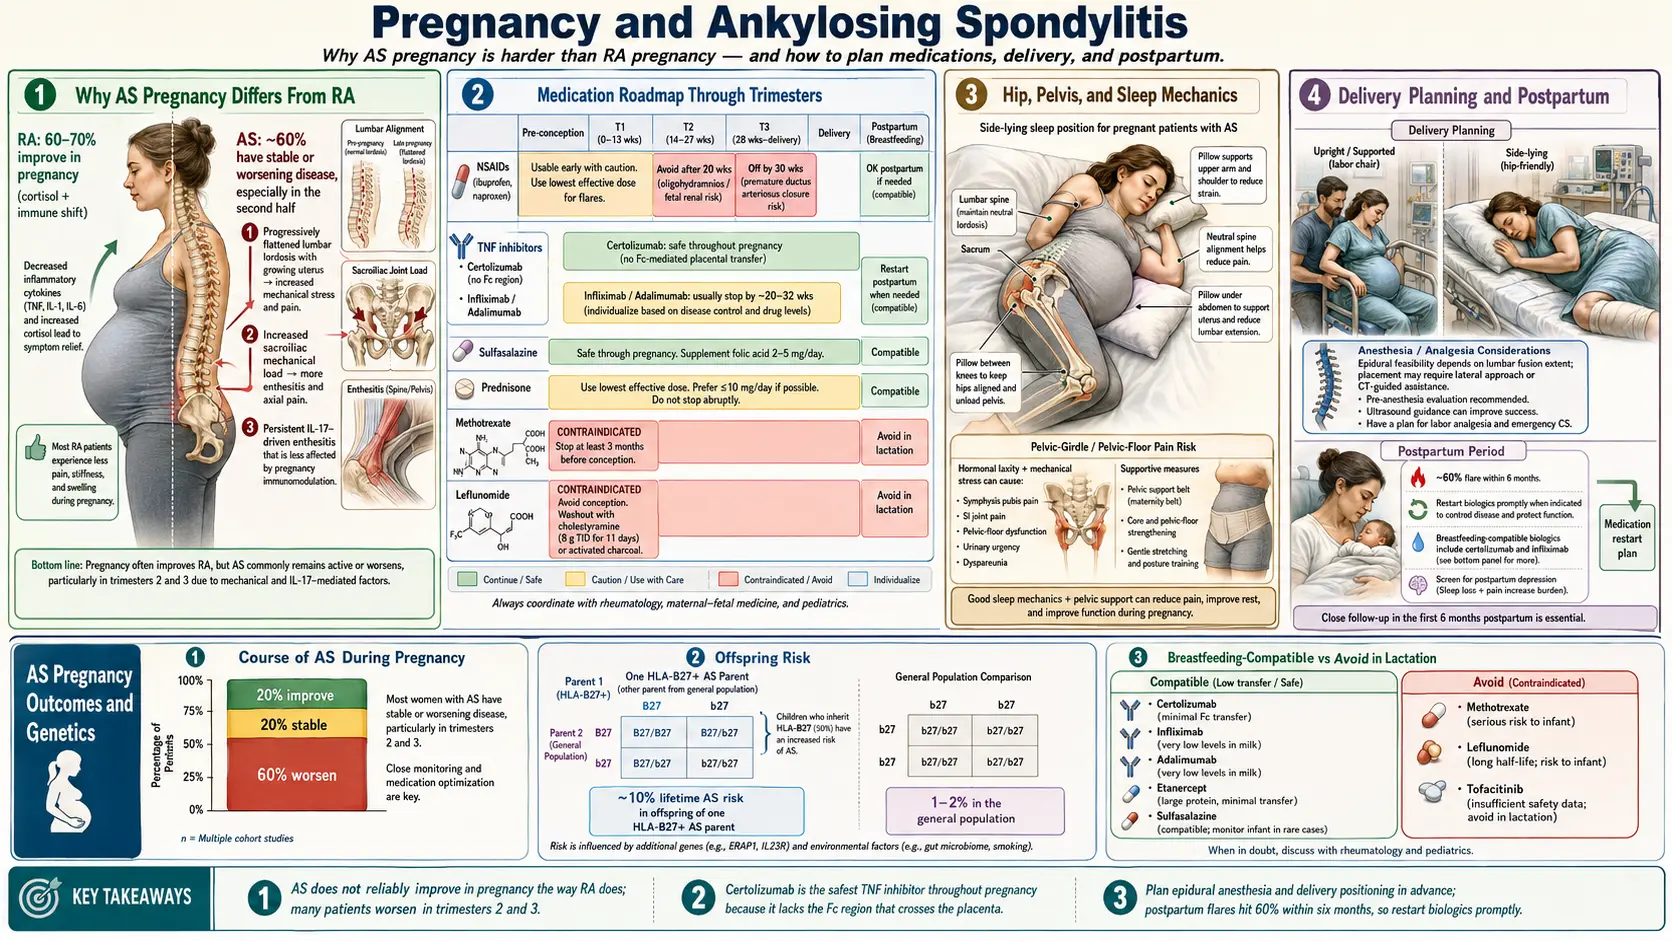
Pregnancy with ankylosing spondylitis (AS) is different from pregnancy with rheumatoid arthritis — and for someone told it would all get better once she conceived, only to find her back pain worsening at 22 weeks, the worsening is real and is not a personal failure. The old obstetric reassurance — "autoimmune disease improves in pregnancy" — was built on rheumatoid arthritis (RA) data. It does not reliably apply to spondyloarthritis. This article walks through what is known about the course of pregnancy, which medications are continued and which are stopped, how delivery is planned, and what is known about flares after the birth.
Table of Contents
- Why Ankylosing Spondylitis Pregnancy Is Different From Rheumatoid Arthritis Pregnancy
- Pre-Conception Planning
- Nonsteroidal Anti-Inflammatory Drugs in Pregnancy
- Biologics in Pregnancy
- The EULAR Guidance on Antirheumatic Drugs in Pregnancy
- Managing Flares When Most Drugs Are Off the Table
- Hip, Pelvis, and Spine Mechanics
- Sleep Positioning
- Delivery Planning
- Postpartum Flare Risk
- Breastfeeding and Medications
- Fertility — Hers and His
- Genetic Counseling and the Baby’s Risk
- Mental Health, Sleep Loss, and PPD
- Key Research Papers
- Connections
- Featured Videos
Why Ankylosing Spondylitis Pregnancy Is Different From Rheumatoid Arthritis Pregnancy
For decades, rheumatology textbooks taught a simple rule: autoimmune disease improves in pregnancy because the maternal immune system shifts from a Th1 to a Th2 pattern to tolerate the fetus. That rule was built almost entirely on rheumatoid arthritis, where about 60% of patients do improve, often dramatically, by the second trimester.
Ankylosing spondylitis does not follow the same pattern. A 2024 review of axial spondyloarthritis pregnancies reports that 25–80% of women with ankylosing spondylitis have disease flares during pregnancy, particularly around 20 weeks; the wide range reflects how differently the studies defined and measured disease activity. The classic worsening window is the 20–28 week range, when mechanical load on the pelvis peaks, inflammatory back pain is magnified by a loosened symphysis and sacroiliac joints, and many patients have already stopped nonsteroidal anti-inflammatory drugs (NSAIDs).
Why the difference? Two likely reasons. First, ankylosing spondylitis is driven largely by the IL-23/IL-17 axis, which is not as strongly suppressed by pregnancy hormones as the Th1/tumor necrosis factor (TNF) pathways that dominate rheumatoid arthritis. Second, much of ankylosing spondylitis pain is mechanical on top of inflammatory — the sacroiliac joints and lumbar spine take far more direct strain from a growing uterus than the small joints of the hands.
When pregnancy has not been the "break" from ankylosing spondylitis that counseling promised, the disease is behaving the way it commonly does. The mismatch is in the counseling, not in the patient.
Pre-Conception Planning
Planning usually begins three to six months before conception. Active, uncontrolled ankylosing spondylitis at the time of conception correlates with more difficult pregnancies and higher rates of preterm birth and low birth weight. The usual target in practice is low disease activity (ASDAS < 2.1 or BASDAI < 4) for at least three months, preferably six, before trying. The 2020 American College of Rheumatology (ACR) reproductive health guideline likewise supports pre-pregnancy counseling so that conception happens while the disease is quiet and while the patient takes pregnancy-compatible medicines.
A 2024 review of pregnancy in axial spondyloarthritis found higher rates of preterm birth, low birth weight and elective caesarean section than in healthy women, while describing the data as scarce and discordant; the authors note that the higher caesarean rate may reflect local practice more than a medical need caused by the disease.
Items commonly covered before conception:
- Medication review with the rheumatologist. Methotrexate is stopped at least three months before conception because it causes birth defects (teratogenic). Leflunomide is cleared with a cholestyramine washout. Sulfasalazine, hydroxychloroquine, azathioprine, and most tumor necrosis factor inhibitors can continue. JAK inhibitors (tofacitinib, upadacitinib) are stopped.
- Switching to a pregnancy-compatible biologic in advance for anyone on something less well-studied. A move to certolizumab pegol three months before trying leaves time to confirm it is controlling the disease.
- Folate — at least 400 mcg daily, and 800 mcg is commonly used after sulfasalazine (which interferes with folate metabolism), started three months before conception.
- Vitamin D — a 25-OH vitamin D level is commonly checked, with a target of at least 30 ng/mL. Ankylosing spondylitis patients are frequently low.
- DXA bone-density scan after long-term nonsteroidal anti-inflammatory drug (NSAID) use, prior prednisone, or with low body weight. Pregnancy and lactation both transiently reduce bone density, and ankylosing spondylitis patients are already at higher fracture risk.
- Maternal-fetal medicine (MFM) consultation alongside a rheumatologist who is comfortable managing biologics in pregnancy. Co-management by the two specialties is the standard of care.
Nonsteroidal Anti-Inflammatory Drugs in Pregnancy
Nonsteroidal anti-inflammatory drugs — the backbone of day-to-day ankylosing spondylitis management — become the single biggest medication question of pregnancy. The 2024 EULAR update takes a more restrictive approach to NSAIDs in pregnancy than earlier guidance.
First trimester and early second trimester (up to roughly 20 weeks). Short-course, lowest-effective-dose nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, diclofenac) are generally considered acceptable if truly needed, though some guidelines now favour minimizing use even in early pregnancy. There is a small, debated signal for first-trimester miscarriage risk with sustained use. Intermittent, symptom-driven dosing is generally regarded as safer than daily scheduled therapy.
From 20 weeks. In October 2020, the U.S. Food and Drug Administration (FDA) issued a Drug Safety Communication recommending avoiding nonsteroidal anti-inflammatory drugs at 20 weeks or later in pregnancy, rather than the 30 weeks previously described in NSAID prescribing information, because of the risk of fetal kidney problems leading to oligohydramnios (low amniotic fluid). The FDA reviewed the medical literature and case reports: low amniotic fluid was usually seen after days to weeks of treatment, but has been reported as soon as 48 hours after starting an NSAID, and in most cases it reversed within 3 to 6 days of stopping the drug. Where a health care professional judges an NSAID necessary between 20 and 30 weeks, the FDA advice is the lowest effective dose for the shortest time, with ultrasound monitoring of amniotic fluid if treatment goes beyond 48 hours.
From about 30 weeks. At around 30 weeks, nonsteroidal anti-inflammatory drugs can cause premature closure of the ductus arteriosus, a critical fetal vessel, which is why NSAID labels already advised against them from 30 weeks. Closure in utero can cause fetal heart failure and pulmonary hypertension in the newborn.
Low-dose aspirin (81 mg) is a separate category: the FDA recommendation does not apply to it. It is used in pregnancy for certain conditions, such as preeclampsia prevention, under the direction of a health care professional, and it has a different safety profile from therapeutic-dose nonsteroidal anti-inflammatory drugs.
In practice this creates a 20-week nonsteroidal anti-inflammatory drug cut-off, and a non-NSAID strategy is usually planned well before it.
Biologics in Pregnancy
This is where the last decade of research has changed the picture. Several tumor necrosis factor inhibitors now have enough human pregnancy data to be considered compatible throughout pregnancy, and one — certolizumab pegol — has a structural feature that often makes it the first choice when a woman with ankylosing spondylitis is planning a pregnancy or is already pregnant.
Tumor Necrosis Factor Inhibitors
- Certolizumab pegol — often preferred throughout pregnancy. Certolizumab is a Fab′ fragment attached to polyethylene glycol; it lacks the Fc portion of a normal immunoglobulin G (IgG) antibody. Placental transfer of immunoglobulin G uses the neonatal Fc receptor (FcRn), so no Fc means almost no active transport to the fetus. The prospective CRIB study (Mariette and colleagues, 2018) followed 16 women treated in late pregnancy: of 14 infants with usable results, 13 had no measurable certolizumab at birth and 1 had a minimal level (0.042 μg/mL), and 3 of 15 umbilical-cord samples had measurable drug (at most 0.048 μg/mL). The authors concluded that the results support continuing certolizumab during pregnancy when it is considered necessary.
- Etanercept — compatible; lower placental transfer than adalimumab or infliximab because of structural differences, though it still crosses via FcRn in the third trimester. Often continued through the second trimester and sometimes to delivery.
- Adalimumab and infliximab — compatible through conception and most of pregnancy. They are complete IgG1 antibodies and are actively transported across the placenta in the third trimester, so infant drug levels at birth can exceed maternal levels. Many rheumatologists stop adalimumab around 28–32 weeks and infliximab around 20–24 weeks to minimize neonatal exposure, while others continue them when disease activity requires it. The main implication is the infant vaccination schedule: live vaccines (rotavirus, BCG) are deferred for the first 6 months of life when the mother was on a full-transfer tumor necrosis factor inhibitor in the third trimester.
- Golimumab — limited pregnancy data. The 2024 EULAR update states that all tumor necrosis factor inhibitors, golimumab among them, can be used throughout pregnancy, based on an individual risk-benefit assessment.
IL-17 Inhibitors
Secukinumab and ixekizumab — limited human pregnancy data. The 2024 EULAR update states that biologics other than tumor necrosis factor inhibitors may be used in pregnancy if needed. Where ankylosing spondylitis is controlled only by an IL-17 inhibitor, a common pre-conception option is switching to certolizumab for the pregnancy and resuming the IL-17 drug after delivery.
JAK Inhibitors
Tofacitinib, upadacitinib, baricitinib — contraindicated in pregnancy. Small molecules cross the placenta freely, and animal studies show teratogenicity. The 2016 EULAR points to consider listed tofacitinib among the drugs stopped before a planned pregnancy because of insufficient fetal-safety data; the washout commonly described before attempting conception is about one week.
Older Disease-Modifying Antirheumatic Drugs (DMARDs)
Sulfasalazine is compatible with pregnancy (folate is usually added). Methotrexate must be stopped before conception because of proven teratogenicity, and leflunomide is stopped before a planned pregnancy because of insufficient fetal-safety data (2016 EULAR points to consider).
The EULAR Guidance on Antirheumatic Drugs in Pregnancy
Three documents set out current guidance on antirheumatic drugs around pregnancy:
- The 2016 EULAR points to consider (Götestam Skorpen and colleagues), from the European League Against Rheumatism (now the European Alliance of Associations for Rheumatology), found antimalarials, sulfasalazine, azathioprine, ciclosporin, tacrolimus, colchicine, intravenous immunoglobulin and glucocorticoids compatible with pregnancy and lactation. Methotrexate, mycophenolate mofetil and cyclophosphamide required stopping before conception because of proven teratogenicity; leflunomide and tofacitinib were stopped before a planned pregnancy for lack of safety data. Among biologics, tumor necrosis factor inhibitors were the best studied and appeared reasonably safe with first- and second-trimester use.
- The 2020 American College of Rheumatology reproductive health guideline (Sammaritano and colleagues) made 131 graded recommendations and 12 good-practice statements, built around planned pregnancy, conception during quiet disease on pregnancy-compatible medicines, and shared decisions with obstetric teams; many recommendations are conditional because data are limited.
- The 2024 EULAR update (Rüegg and colleagues, published 2025) lists antimalarials (such as hydroxychloroquine), azathioprine, colchicine, cyclosporine, sulfasalazine and tacrolimus as compatible with pregnancy. It states that all tumor necrosis factor inhibitor biologics can be used throughout pregnancy and that other biologics may be used if needed, each on an individual risk-benefit assessment, and it takes a more restrictive approach to NSAIDs and glucocorticoids in pregnancy. For breastfeeding it lists antimalarials, azathioprine, colchicine, cyclosporine, glucocorticoids, intravenous immunoglobulin, NSAIDs, sulfasalazine and tacrolimus as compatible, and all biologics. For fathers it lists methotrexate, leflunomide, sulfasalazine, mycophenolate, NSAIDs, glucocorticoids and biologics among the compatible options.
Two points run through current practice:
- Active disease at conception predicts worse pregnancy outcomes than continued biologic therapy does. Controlled disease matters more than drug avoidance.
- Live vaccines are deferred in infants whose mothers received full-transfer biologics in the third trimester.
A plan to stop every medicine for pregnancy, without regard to which drugs these documents list as compatible, does not match current guidance.
Managing Flares When Most Drugs Are Off the Table
The worst stretch is often weeks 22–32: nonsteroidal anti-inflammatory drugs are gone, the third-trimester biologic dose may have been held, and mechanical load on the pelvis is peaking. Approaches used during this stretch:
- Aquatic therapy. Warm-water (88–92°F) pool exercise unloads the SI joints, reduces stiffness, and is considered safe throughout pregnancy. Many physical therapy clinics and community pool programs run prenatal water classes.
- Prenatal physical therapy. A physical therapist experienced in spondyloarthritis can teach extension-based and pelvic-stabilization exercises that target ankylosing spondylitis specifically, not just generic prenatal posture. See the exercise and PT protocol.
- Heat. Heating pads and warm showers are considered safe on the back and hips. Heat on the abdomen and hot tubs are generally not used, because of the concern about raising core temperature.
- Acetaminophen (paracetamol). Widely used throughout pregnancy at the standard 1 g up to four times daily. Not a strong anti-inflammatory but helpful for mechanical flare pain and mild-to-moderate stiffness.
- Short prednisone bursts. For a severe flare, a 5–7 day course of 10–20 mg prednisone is a commonly used option. Long-term prednisone raises gestational diabetes, hypertension, and preterm birth risk, and the 2024 EULAR update takes a more restrictive approach to glucocorticoids in pregnancy; a short rescue course is used when nothing else is working, usually co-managed with the obstetric or maternal-fetal medicine team.
- Local corticosteroid injections. SI joint or trochanteric bursa injections with a low-dose steroid (triamcinolone) are considered acceptable when the benefit is significant.
- TENS units. Non-pharmacologic, safe, and useful for nighttime lumbar pain.
Hip, Pelvis, and Spine Mechanics
Pregnancy drops a near-perfect mechanical storm on an ankylosing spondylitis-affected spine. Relaxin loosens the symphysis and SI joints. The uterus shifts the center of gravity forward, tilting the pelvis and deepening the lumbar curve. Gait widens. Stair-climbing recruits the gluteus medius harder. In a person without ankylosing spondylitis, this is manageable; in a person with chronic SI joint inflammation, it is often the trigger for the 20-week flare.
Measures used to reduce mechanical load:
- Sacroiliac or maternity support belts. Worn low across the sacrum and pubic symphysis, these are used to stabilize the SI joints during walking and standing.
- Supportive footwear. Structured walking shoes with arch support, rather than flats or high heels, are used to reduce pelvic tilt.
- Chair and car ergonomics. A lumbar roll, knees slightly lower than hips, and standing up at least every 30 minutes reduce the strain of sitting.
- Daily prenatal physical therapy. Ten minutes a day of pelvic tilts, bird-dogs, and wall-supported standing hip extensions is a typical programme for preserving remaining spinal mobility.
- Even loading. Carrying a toddler on one hip or a bag slung on one shoulder loads the pelvis unevenly.
Sleep Positioning
Sleep gets harder in ankylosing spondylitis pregnancy than in almost any other situation — inflammatory stiffness and mechanical back pain stack on top of the normal third-trimester discomfort. A setup many people describe:
- Firm mattress. Soft mattresses let the pelvis sag, torquing the SI joints; a firm topper is a common fix for an old, soft mattress.
- Body pillow or long wedge. Side-lying with a pillow supporting the belly keeps the lumbar spine neutral rather than rotated.
- Pillow between the knees. Keeps the pelvis level and reduces SI joint shear.
- Small rolled towel under the waist. For patients whose natural side-lying posture collapses the lumbar curve, a thin roll at the waist preserves alignment.
- Left side commonly advised after 20 weeks for blood flow to the placenta, though short stretches on the right are described as fine if SI pain forces a switch.
- Log-rolling out of bed. Knees bent, roll to the side, push up with the arms. Sitting straight up from lying on the back is a core crunch that aggravates the SI joints.
Delivery Planning
Ankylosing spondylitis alone is not an indication for C-section. Vaginal delivery is the default and is generally well-tolerated even in women with fused spines, provided anesthesia planning happens in advance.
Three pieces of planning are usually in place before labor:
- Anesthesia consultation at 28–34 weeks. Meeting the anesthesia team before labor, not during it, is the usual practice for patients with ankylosing spondylitis. With spinal fusion, prior spine surgery, or significant lumbar rigidity, epidural placement may be technically difficult or impossible at the usual L3–L4 or L4–L5 interspace. Options include an epidural at a higher level, a combined spinal-epidural, ultrasound-guided placement, or — if neuraxial anesthesia is not feasible — intravenous (IV) or inhaled analgesia, pudendal block, or general anesthesia for C-section.
- Cervical spine mobility assessment. General anesthesia requires intubation, and a fused or rigid cervical spine complicates intubation and may require a fiberoptic approach, which is why neck mobility is assessed and recorded in advance.
- Labor positioning plan. Hands-and-knees, side-lying, and birth ball positions are often more tolerable than flat-on-back for ankylosing spondylitis patients, and are often planned with the labor and delivery team in advance.
If C-section is chosen for obstetric reasons, spinal anesthesia has the same technical challenges as epidural and needs the same advance planning. Anesthesia teams commonly have a written plan in the chart by 36 weeks.
Postpartum Flare Risk
The postpartum period is widely described as a high-risk time for ankylosing spondylitis flares, although a 2024 review found the published data on postpartum flares heterogeneous, with rates differing widely between studies. The drivers stack: pregnancy immune tolerance ends abruptly, estrogen and progesterone crash, sleep is shattered, breastfeeding adds physical load, and any biologic that was held for the third trimester has not yet been restarted.
Common elements of a postpartum plan:
- Early return to the biologic. Certolizumab, etanercept, and adalimumab can all be restarted within days of delivery (and in many cases were never stopped); the aim is to restart before a flare begins.
- Return to daily physical therapy or exercise once cleared by the obstetric team (typically 2–6 weeks depending on delivery). Aquatic therapy is again the easiest re-entry.
- A short prednisone prescription on hand for rescue use is part of some plans.
- Sleep backup in the first 12 weeks. Partner night feeds, family help, pumped milk so a partner can take the 2 AM feed — sleep deprivation is both a flare trigger and a postpartum depression trigger, and the two amplify each other.
- A rheumatology visit at 4–6 weeks postpartum, rather than at 3 months, catches a flare in progress early.
Breastfeeding and Medications
Breastfeeding with ankylosing spondylitis is generally compatible with the medications that matter most; the 2024 EULAR update considers all biologics compatible with breastfeeding:
- Certolizumab pegol — the CRADLE study measured certolizumab in breast milk from 17 nursing mothers: 77 of 137 samples (56%) had no measurable drug, the estimated infant dose was 0.15% of the mother’s dose (below 10% is considered unlikely to be of clinical concern), and the drug’s polyethylene glycol part was not detected in 134 of 137 samples. Oral bioavailability of the drug is very low, so the infant gut absorbs essentially none of it. Compatible with breastfeeding.
- Etanercept, adalimumab, infliximab, golimumab — all transfer to milk at very low levels and are degraded in the infant gut. Compatible.
- Secukinumab, ixekizumab — limited data, but covered by the 2024 EULAR statement that all biologics are compatible with breastfeeding.
- Ibuprofen — very low milk transfer, short half-life. Commonly the preferred nonsteroidal anti-inflammatory drug in breastfeeding. Naproxen is acceptable but has a longer half-life. Aspirin is generally not used because of the concern about Reye syndrome in the infant.
- Prednisone — compatible. At doses above 20 mg, some clinicians suggest waiting 4 hours after a dose before nursing, though the clinical relevance is marginal.
- Sulfasalazine — compatible in full-term healthy infants; caution in preterm or glucose-6-phosphate dehydrogenase-deficient infants.
- Methotrexate, leflunomide, JAK inhibitors — not compatible with breastfeeding.
The LactMed database (free from the U.S. National Institutes of Health, NIH) has evidence-based summaries for every one of these drugs and is the single best reference for any specific question.
Fertility — Hers and His
Ankylosing spondylitis itself does not reduce female fertility. Time-to-pregnancy in women with controlled ankylosing spondylitis is similar to the general population. Active, uncontrolled inflammation may modestly reduce fertility and increase miscarriage risk, one of the reasons low disease activity is the target before trying.
For male ankylosing spondylitis patients planning a pregnancy with their partner, two drug notes:
- Sulfasalazine — the U.S. drug label states that low sperm count (oligospermia) and infertility have been observed in men treated with sulfasalazine, and that withdrawal of the drug appears to reverse these effects. The 2024 EULAR update nonetheless lists sulfasalazine among the drugs compatible for men planning a pregnancy.
- Methotrexate and tumor necrosis factor inhibitors do not meaningfully impair male fertility based on current evidence; the 2024 EULAR update lists methotrexate, leflunomide and biologics as compatible for men planning a pregnancy.
Genetic Counseling and the Baby’s Risk
The question every ankylosing spondylitis parent asks: what is the child’s risk?
- Human leukocyte antigen-B27 inheritance. If one parent is human leukocyte antigen-B27 positive (heterozygous, the usual case), each child has a 50% chance of inheriting human leukocyte antigen-B27. If the parent is homozygous for B27 (rare), every child inherits it.
- Ankylosing spondylitis risk in the child. Inheriting human leukocyte antigen-B27 is not the same as developing ankylosing spondylitis. A child of an ankylosing spondylitis parent has roughly a 5–10% lifetime risk of developing ankylosing spondylitis — meaningful, but still a 90–95% chance of not developing it.
- If both parents have ankylosing spondylitis (uncommon but it happens), risk rises further — but there is no proven genetic counseling reason to avoid pregnancy on this basis alone.
- Testing children. Routine human leukocyte antigen-B27 testing of children of ankylosing spondylitis parents is not standard practice. A positive result in an asymptomatic child changes nothing about care, so testing is usually done when and if symptoms of inflammatory back pain appear.
Formal genetic counseling is an option for families with a history of severe ankylosing spondylitis or other human leukocyte antigen-B27 diseases, or when both partners carry the gene. See the human leukocyte antigen-B27 explained article for the full genetics.
Mental Health, Sleep Loss, and PPD
The combination of an unpredictable flare, a newborn, and shredded sleep puts ankylosing spondylitis mothers at substantially elevated risk for postpartum depression (PPD) and anxiety. This is not weakness and it is not surprising — it is a predictable physiological consequence of a stressor stack, and it is treatable.
- Repeated screening. The Edinburgh Postnatal Depression Scale (EPDS) can be done by the obstetric or primary care team at 2, 6, and 12 weeks postpartum, not just once.
- Flare and depression are separate problems. Untreated ankylosing spondylitis pain masquerades as depression, and untreated depression worsens pain perception; each needs its own treatment.
- Selective serotonin reuptake inhibitors (SSRIs) are compatible with breastfeeding. Sertraline and paroxetine have the most data. Breastfeeding by itself does not rule out treatment for depression.
- Help at home. Meal trains, overnight doulas, partner-led feeds, grandparent shifts — every hour of uninterrupted sleep works as a therapeutic intervention.
- Peer support. The Spondylitis Association of America (SAA), a patient charity, and online ankylosing spondylitis pregnancy groups bring together women who have been through this, which eases the isolation.
Intrusive thoughts, thoughts of self-harm, or being unable to care for the baby are signs that health services treat as urgent. The obstetric team, the rheumatologist, and the U.S. national Maternal Mental Health Hotline (1-833-TLC-MAMA) all take these calls. This is a medical problem, not a moral one.
Key Research Papers
- Götestam Skorpen C, Hoeltzenbein M, Tincani A, et al. The EULAR points to consider for use of antirheumatic drugs before pregnancy, and during pregnancy and lactation. Ann Rheum Dis. 2016;75(5):795–810. — PubMed PMID: 26888948
- Rüegg L, Pluma A, Hamroun S, et al. EULAR recommendations for use of antirheumatic drugs in reproduction, pregnancy, and lactation: 2024 update. Ann Rheum Dis. 2025;84(6):910–926. — PubMed PMID: 40287311
- Sammaritano LR, Bermas BL, Chakravarty EE, et al. 2020 American College of Rheumatology Guideline for the Management of Reproductive Health in Rheumatic and Musculoskeletal Diseases. Arthritis Care Res (Hoboken). 2020;72(4):461–488. — PubMed PMID: 32090466
- Mariette X, Förger F, Abraham B, et al. Lack of placental transfer of certolizumab pegol during pregnancy: results from CRIB, a prospective, postmarketing, pharmacokinetic study. Ann Rheum Dis. 2018;77(2):228–233. — doi:10.1136/annrheumdis-2017-212196
- Clowse ME, Förger F, Hwang C, et al. Minimal to no transfer of certolizumab pegol into breast milk: results from CRADLE, a prospective, postmarketing, multicentre, pharmacokinetic study. Ann Rheum Dis. 2017;76(11):1890–1896. — PubMed PMID: 28814432
- Filippini M, Fontana G, Bizioli P, et al. Pregnancy in patients affected by axial-spondyloarthritis: a narrative review of disease activity and obstetric outcomes. Reumatismo. 2024;76(3). — PubMed PMID: 39282784
- Ostensen M, Husby G. Ankylosing spondylitis and pregnancy. Rheum Dis Clin North Am. 1989;15(2):241–54. — PubMed PMID: 2657890 (Foundational work on AS disease activity through pregnancy and postpartum.)
- U.S. Food and Drug Administration. FDA recommends avoiding use of NSAIDs in pregnancy at 20 weeks or later because they can result in low amniotic fluid. Drug Safety Communication, October 15, 2020. — fda.gov Drug Safety Communication
PubMed Topic Searches
Further reading on ankylosing spondylitis, spondyloarthritis, and pregnancy. These PubMed topic searches return current peer-reviewed work:
- PubMed: Ankylosing spondylitis and pregnancy
- PubMed: Spondyloarthritis pregnancy outcomes
- PubMed: Certolizumab pegol placental transfer
- PubMed: Biologics and breastfeeding in rheumatic disease
- PubMed: NSAIDs, oligohydramnios, and ductus arteriosus in pregnancy
- PubMed: Postpartum flare in spondyloarthritis
- PubMed: EULAR reproductive recommendations in rheumatic disease
- PubMed: Epidural anesthesia in ankylosing spondylitis and spinal fusion
Connections
- Rheumatology
- Ankylosing Spondylitis
- Human Leukocyte Antigen-B27 Explained
- Biologics Guide
- Ankylosing Spondylitis and Inflammatory Bowel Disease Overlap
- Exercise and PT Protocol
- Nonsteroidal Anti-Inflammatory Drug Strategy
- Morning Stiffness Management
- Starch-Free Diet and Ebringer
- Uveitis and Eye Involvement
- Arthritis
- Lupus
- Infertility
- Preeclampsia
- Gestational Diabetes
- Depression