Nonsteroidal Anti-Inflammatory Drug Strategy for Ankylosing Spondylitis
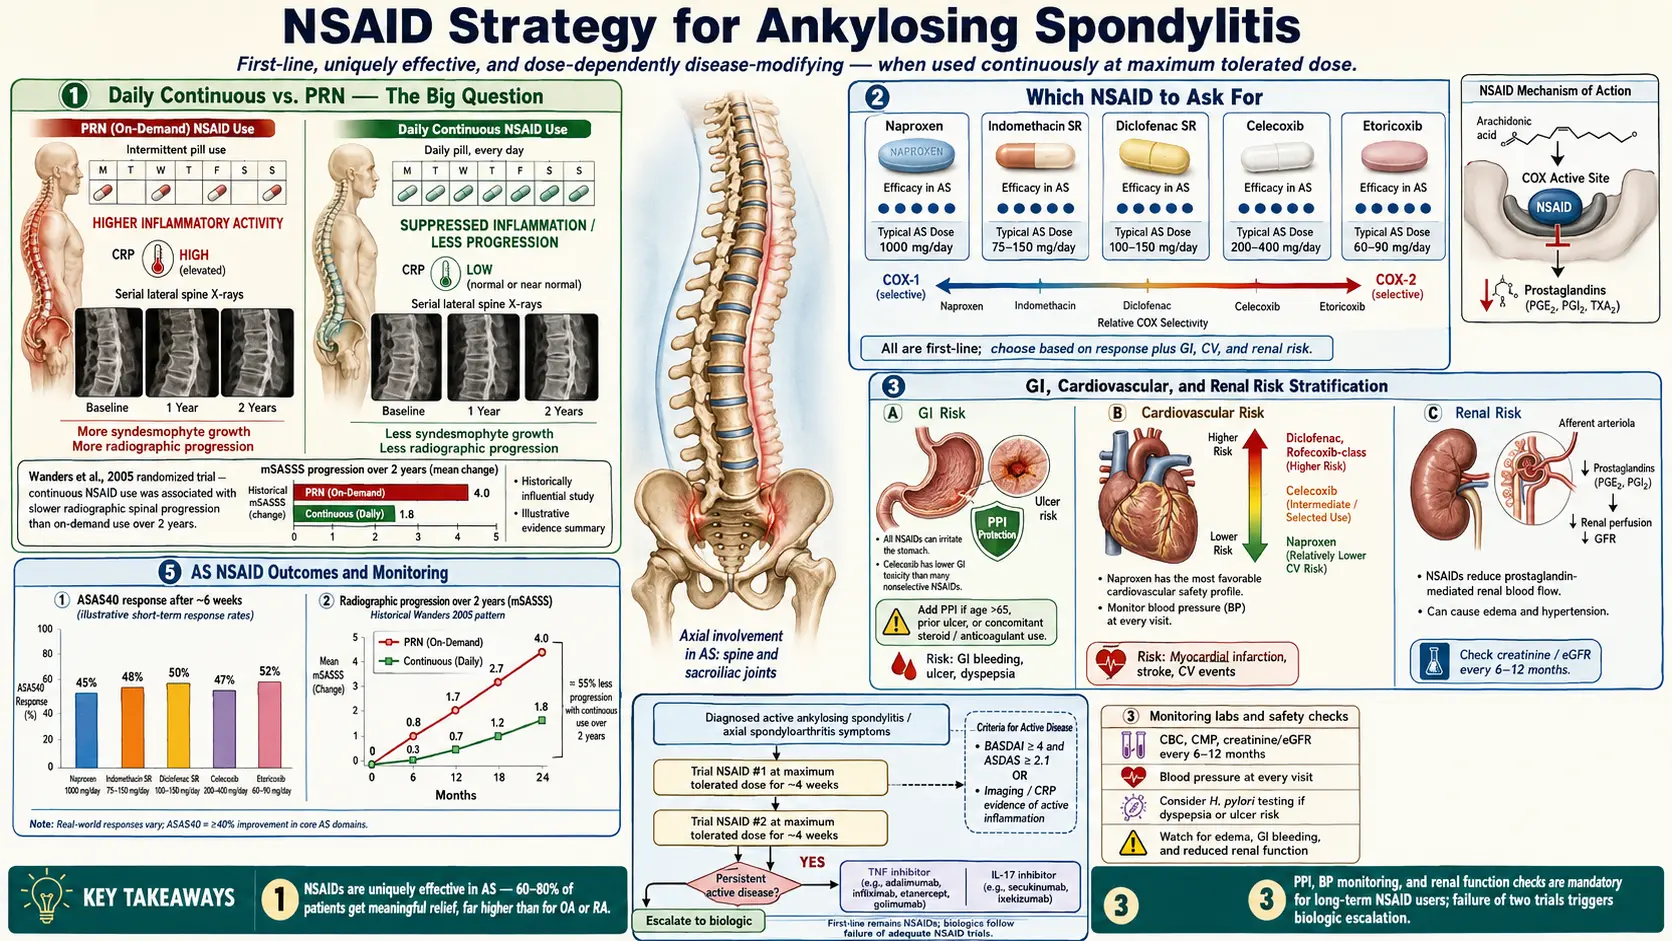
Table of Contents
- Nonsteroidal Anti-Inflammatory Drugs Are First-Line for Ankylosing Spondylitis — And More Effective Than for Other Arthritides
- Daily Continuous vs. As-Needed Use
- The Common Nonsteroidal Anti-Inflammatory Drugs — Drug-by-Drug
- Trial-and-Error Reality
- Dosing for Ankylosing Spondylitis Specifically
- Gastrointestinal Protection — Critical for Long-Term Nonsteroidal Anti-Inflammatory Drug Users
- Cardiovascular Risk
- Renal Risk
- Other Side Effects
- Nonsteroidal Anti-Inflammatory Drug Failure — Moving to Biologics
- Nonsteroidal Anti-Inflammatory Drugs + Biologics
- Topical Nonsteroidal Anti-Inflammatory Drugs — Adjunct Option
- Acetaminophen + Nonsteroidal Anti-Inflammatory Drugs
- Alternative Anti-Inflammatories
- Monitoring Schedule
- Nonsteroidal Anti-Inflammatory Drugs in Pregnancy
- Key Research Papers
- Connections
- Featured Videos
1. Nonsteroidal Anti-Inflammatory Drugs Are First-Line for Ankylosing Spondylitis — And More Effective Than for Other Arthritides
One of the diagnostic clues for ankylosing spondylitis is that the inflammatory back pain responds unusually well to nonsteroidal anti-inflammatory drugs (NSAIDs) — more reliably, and more dramatically, than back pain from mechanical causes or even most other inflammatory arthritides. Most ankylosing spondylitis (AS) patients see greater than 50% pain reduction within 48 hours of starting a therapeutic dose.
The corollary matters clinically: when suspected ankylosing spondylitis does not respond meaningfully to a full-dose nonsteroidal anti-inflammatory drug (NSAID) after two weeks of an adequate dose, rheumatologists reconsider the diagnosis before labelling the person a nonsteroidal anti-inflammatory drug non-responder. Seronegative fibromyalgia, mechanical back pain, and non-radiographic axial spondyloarthritis (SpA) in its earliest stages can mimic ankylosing spondylitis but don’t share the same robust nonsteroidal anti-inflammatory drug response.
This is why every major guideline — the 2019 American College of Rheumatology/Spondylitis Association of America/Spondyloarthritis Research and Treatment Network (ACR/SAA/SPARTAN) recommendations and the 2022 Assessment of SpondyloArthritis international Society–European Alliance of Associations for Rheumatology (ASAS-EULAR) update — lists nonsteroidal anti-inflammatory drugs as the first-line pharmacologic therapy for active ankylosing spondylitis. In these guidelines they come before biologics, before disease-modifying antirheumatic drugs (DMARDs), and before anything injectable.
2. Daily Continuous vs. As-Needed Use
A common question in ankylosing spondylitis is whether a nonsteroidal anti-inflammatory drug is taken every day no matter what, or only when it hurts (as needed, written PRN, from the Latin pro re nata). For most of the 2000s and early 2010s, the common answer was “every day, forever, to slow the fusion.” The trial evidence has since become mixed, and the guideline now depends on whether the disease is active or stable.
- Wanders 2005 trial (215 patients) compared continuous daily use (all started on celecoxib) with on-demand use over 2 years and found less radiographic progression in the continuous group: the spinal X-ray score (modified Stoke Ankylosing Spondylitis Spine Score, mSASSS) worsened by 0.4 units with continuous use versus 1.5 units with on-demand use (P = 0.002). This single trial defined the “take it every day” dogma for over a decade.
- ENRADAS trial (Sieper 2016), a smaller randomized controlled trial (RCT; 167 patients enrolled) using diclofenac, did not replicate the Wanders finding. Progression was numerically higher with continuous diclofenac (1.28 versus 0.79 mSASSS units, not a significant difference), and the authors concluded that continuous treatment did not reduce radiographic progression compared with on-demand treatment.
- The 2019 ACR/SAA/SPARTAN guideline conditionally recommends continuous nonsteroidal anti-inflammatory drug treatment over on-demand treatment for adults with active ankylosing spondylitis, and on-demand treatment over continuous treatment for adults with stable disease. It describes the evidence that continuous use slows spinal fusion as inconsistent: one celecoxib trial suggested less progression, one diclofenac trial showed no difference.
In practice: the guideline split matches daily use to active disease with daily symptoms, and as-needed use to stable disease with occasional flares. For stable disease, the 2019 panel judged that the potential toxicities of continuous nonsteroidal anti-inflammatory drug treatment outweighed the uncertain benefit of less radiographic progression. The gastrointestinal (GI), cardiovascular (CV), and kidney risks of chronic dosing are described in sections 6–8.
3. The Common Nonsteroidal Anti-Inflammatory Drugs — Drug-by-Drug
The 2019 ACR/SAA/SPARTAN guideline does not recommend any particular nonsteroidal anti-inflammatory drug as the preferred choice. The drugs differ in dosing schedule, half-life and side-effect profile:
Meloxicam
Dose: 7.5–15 mg daily. Once-daily dosing with a long half-life (15–20 hours on average, FDA label), which gives consistent 24-hour coverage from a single pill. Moderate cyclooxygenase-2 (COX-2) selectivity puts gastrointestinal risk between ibuprofen and celecoxib. A very common starting choice in ankylosing spondylitis because of the convenient dosing and balanced profile.
Naproxen
Dose: 500 mg twice daily. Cheap, over-the-counter (OTC) at lower strengths, long half-life. Critically, naproxen has the best cardiovascular safety profile of any nonsteroidal anti-inflammatory drug — the lowest myocardial infarction (MI) and stroke risk in large meta-analyses. Often chosen for people with ankylosing spondylitis who have known cardiovascular disease or elevated cardiovascular risk.
Celecoxib
Dose: 200 mg daily or twice daily. A selective cyclooxygenase-2 inhibitor, which means the lowest gastrointestinal ulcer and bleeding risk among nonsteroidal anti-inflammatory drugs. Often used in people with prior ulcer disease or concurrent inflammatory bowel disease (see ankylosing spondylitis and inflammatory bowel disease (IBD) Overlap) — unlike traditional nonsteroidal anti-inflammatory drugs, celecoxib does not appear to flare inflammatory bowel disease (the 2019 ACR/SAA/SPARTAN guideline, citing very low-quality evidence, does not recommend any particular nonsteroidal anti-inflammatory drug as preferred for lowering the risk of worsening inflammatory bowel disease symptoms). In the PRECISION trial of 24,081 people with arthritis at raised heart risk, celecoxib at moderate doses was not worse than naproxen or ibuprofen for cardiovascular safety (see section 7).
Indomethacin
Dose: 25–50 mg three to four times daily. Historically considered the most potent nonsteroidal anti-inflammatory drug for ankylosing spondylitis specifically, and still the one many older rheumatologists reach for when others fail. The downside is a higher rate of gastrointestinal toxicity and central nervous system (CNS) side effects — headache, dizziness, and a “spaced-out” feeling are common. Often tried as a third-line nonsteroidal anti-inflammatory drug after meloxicam and naproxen.
Diclofenac
Dose: 75 mg twice daily (or 50 mg three times daily). Effective but carries the highest cardiovascular risk of the common nonsteroidal anti-inflammatory drugs — comparable in some analyses to the withdrawn rofecoxib. That cardiovascular risk is the main drawback of oral diclofenac. The topical gel is used for enthesitis (see section 12).
Ibuprofen
Dose: 400–800 mg three to four times daily. Over-the-counter, cheap, familiar. Often a first trial, but dosing three to four times a day is inconvenient and gastrointestinal risk at the doses needed for ankylosing spondylitis is higher than meloxicam or celecoxib. Most patients end up switching.
Etoricoxib
Dose: 60–90 mg daily. Highly cyclooxygenase-2 selective, strong evidence in ankylosing spondylitis specifically, widely used in Europe, UK, and Canada. Not U.S. Food and Drug Administration-approved in the US — so U.S. rheumatologists cannot prescribe it, even though it appears in many European studies.
Piroxicam
Dose: 20 mg daily. Very long half-life (about 50 hours, FDA label) — the longest of the drugs on this list — allows once-daily dosing, but elevated gastrointestinal and cardiovascular risk relative to alternatives. Rarely a first choice now.
4. Trial-and-Error Reality
Here is the part no trial result captures well: different ankylosing spondylitis patients respond best to different nonsteroidal anti-inflammatory drugs in a way that is largely idiosyncratic. Two patients with identical imaging and identical C-reactive protein (CRP) can have dramatically different responses to, say, meloxicam vs. indomethacin. The genetic and pharmacokinetic reasons are still not fully understood.
The standard approach is therefore empirical:
- One nonsteroidal anti-inflammatory drug is usually tried for 2–4 weeks at the maximum tolerated dose.
- If response is inadequate, the usual next step is a structurally different nonsteroidal anti-inflammatory drug, rather than one propionic acid derivative (the chemical family of ibuprofen and naproxen) swapped for another.
- Most rheumatologists trial 2–3 different nonsteroidal anti-inflammatory drugs before declaring true nonsteroidal anti-inflammatory drug failure and escalating to biologics.
Patients often keep a simple symptom log during each trial: morning stiffness duration, nighttime awakenings, and a global score in the style of the Bath Ankylosing Spondylitis Disease Activity Index (BASDAI). Without data, the “did this actually help?” question gets very fuzzy by week three.
5. Dosing for Ankylosing Spondylitis Specifically
Ankylosing spondylitis doses often run higher than the doses used for rheumatoid arthritis or osteoarthritis:
- Meloxicam: max 15 mg daily (vs rheumatoid arthritis (RA) typical dose 7.5 mg)
- Naproxen: 500 mg twice daily continuous
- Celecoxib: 200 mg twice daily for active disease (not just 200 mg once daily)
- Indomethacin: 150–200 mg/day divided
- Ibuprofen: 2400–3200 mg/day divided
Evening dosing is often overlooked. The classic ankylosing spondylitis inflammatory pattern is pain and stiffness worst in the second half of the night — the 3 AM wakeup. A bedtime nonsteroidal anti-inflammatory drug dose (or the largest dose of the day shifted to bedtime) covers that window, and practitioners describe a marked drop in morning stiffness. See Morning Stiffness Management.
6. Gastrointestinal Protection — Critical for Long-Term Nonsteroidal Anti-Inflammatory Drug Users
Chronic nonsteroidal anti-inflammatory drug use causes gastric and duodenal ulcers. The annual ulcer complication rate (bleeding, perforation, obstruction) on traditional nonsteroidal anti-inflammatory drugs is roughly 1–2%, with cumulative risk rising each year. Long-term users therefore usually have a stomach-protection plan.
- Proton pump inhibitors (PPIs) are the cornerstone: omeprazole 20–40 mg, pantoprazole 40 mg, or esomeprazole 20–40 mg once daily. Proton pump inhibitors reduce nonsteroidal anti-inflammatory drug-induced ulcers by 80–90%.
- Misoprostol works mechanistically but is rarely used now — diarrhea and cramping limit tolerability.
- Celecoxib’s cyclooxygenase-2 selectivity gives it roughly half the ulcer rate of traditional nonsteroidal anti-inflammatory drugs, and many patients on celecoxib alone without high gastrointestinal risk factors do not take a proton pump inhibitor (PPI). In the PRECISION trial, gastrointestinal events were significantly less common with celecoxib than with naproxen or ibuprofen.
- Helicobacter pylori (H. pylori) eradication before chronic nonsteroidal anti-inflammatory drugs: testing, and treatment if positive, is common practice. H. pylori + nonsteroidal anti-inflammatory drugs is a synergistic ulcer machine.
The proton pump inhibitor caveat. Long-term proton pump inhibitors are not free. Documented issues include vitamin B12 deficiency, reduced calcium absorption and fracture risk, hypomagnesemia, increased enteric infection rates, and small intestinal bacterial overgrowth — see small intestinal bacterial overgrowth (SIBO). Some clinicians use periodic “proton pump inhibitor holidays” after 6–12 months of trouble-free nonsteroidal anti-inflammatory drug use in patients without a prior ulcer history.
7. Cardiovascular Risk
All nonsteroidal anti-inflammatory drugs except aspirin raise the risk of myocardial infarction, stroke, and heart failure to varying degrees.
- Lowest risk: naproxen
- Moderate risk: ibuprofen, celecoxib at U.S. Food and Drug Administration-approved doses
- Highest risk: diclofenac, rofecoxib (withdrawn 2004)
The largest head-to-head safety trial, PRECISION, enrolled 24,081 people with osteoarthritis or rheumatoid arthritis at raised cardiovascular risk, who took the study drug for about 20 months on average (mean daily doses: celecoxib 209 mg, naproxen 852 mg, ibuprofen 2,045 mg). Cardiovascular death, nonfatal heart attack or nonfatal stroke occurred in 2.3% on celecoxib, 2.5% on naproxen and 2.7% on ibuprofen. At these moderate doses celecoxib was not worse than either drug for cardiovascular safety, and it had significantly fewer gastrointestinal events than both.
Absolute risk increase: roughly 0.5–1% additional cardiovascular event per year in average-risk patients, and considerably higher in those with established cardiovascular disease. For a 30-year-old with no CV risk factors, this is small. For a 65-year-old post-MI patient, it is not.
For people with cardiovascular disease who need a nonsteroidal anti-inflammatory drug for ankylosing spondylitis, naproxen or celecoxib 200 mg/day at the lowest effective dose is the usual compromise. The celecoxib label’s boxed warning states that nonsteroidal anti-inflammatory drugs raise the risk of serious cardiovascular thrombotic events, including heart attack and stroke, which can be fatal; the risk may occur early in treatment and may increase with duration of use. The label also lists celecoxib as contraindicated in the setting of coronary artery bypass graft (CABG) surgery.
8. Renal Risk
Nonsteroidal anti-inflammatory drugs reduce renal blood flow by inhibiting prostaglandin-mediated afferent arteriolar vasodilation. In healthy kidneys this is usually tolerated; in borderline kidneys it precipitates injury.
- Baseline creatinine and estimated glomerular filtration rate (eGFR) before starting chronic nonsteroidal anti-inflammatory drug therapy.
- Annual creatinine + estimated glomerular filtration rate during chronic use — more often in older patients or those on diuretics or angiotensin-converting enzyme inhibitors (ACE inhibitors).
- Common stopping points: estimated glomerular filtration rate drops more than 30%, acute kidney injury develops, or new proteinuria appears.
- Contraindicated: chronic kidney disease (CKD) stage 4–5, cirrhosis with ascites, heart failure stage C–D.
- Hydration. Adequate water intake is protective; dehydration plus nonsteroidal anti-inflammatory drug plus diuretic is the classic acute kidney injury (AKI) setup.
9. Other Side Effects
- Hypertension: all nonsteroidal anti-inflammatory drugs raise blood pressure by an average of 2–5 mmHg. Blood pressure is usually monitored in people with borderline or treated hypertension.
- Nonsteroidal anti-inflammatory drug-exacerbated respiratory disease: some people with asthma get bronchospasm from aspirin and other nonsteroidal anti-inflammatory drugs. A 2015 meta-analysis found aspirin-exacerbated respiratory disease in about 7% of adults with asthma (7.15%) and about 15% (14.89%) of those with severe asthma. The celecoxib label lists it as contraindicated in patients with aspirin-sensitive asthma and in anyone with a history of asthma, hives or other allergic-type reactions after taking aspirin or other nonsteroidal anti-inflammatory drugs.
- Bleeding risk: additive with anticoagulants, antiplatelets, selective serotonin reuptake inhibitors (SSRIs), which is why the full medication list matters.
- Tinnitus: dose-related; classic with high-dose salicylates but possible with any nonsteroidal anti-inflammatory drug.
- Rash: occasional. Celecoxib’s boxed warning covers serious cardiovascular and gastrointestinal events; sulfonamide (sulfa) allergy appears on its label as a contraindication — it is contraindicated in patients who have shown allergic-type reactions to sulfonamides. Practitioners report that actual cross-reactivity in sulfa-allergic patients is minimal in practice.
10. Nonsteroidal Anti-Inflammatory Drug Failure — Moving to Biologics
The criteria for moving from nonsteroidal anti-inflammatory drugs to biologics (tumor necrosis factor (TNF) inhibitors, interleukin-17 (IL-17) inhibitors, Janus kinase (JAK) inhibitors) are well defined:
- Inadequate response after 2 different nonsteroidal anti-inflammatory drugs at maximum tolerated dose for 2–4 weeks each, OR
- Active disease markers — elevated C-reactive protein, BASDAI > 4 — despite nonsteroidal anti-inflammatory drugs, OR
- Intolerable side effects preventing adequate dosing, OR
- Peripheral arthritis, enthesitis, or dactylitis inadequately controlled by nonsteroidal anti-inflammatory drugs.
Realistic time from starting nonsteroidal anti-inflammatory drugs to starting a biologic in a patient who ultimately needs one: 2–6 months. Two years of cycling nonsteroidal anti-inflammatory drugs while radiographic damage progresses is the delay these criteria are meant to prevent. See Biologics Guide.
11. Nonsteroidal Anti-Inflammatory Drugs + Biologics
Starting a biologic does not mean stopping nonsteroidal anti-inflammatory drugs. Combined treatment is common, especially in the first 12–16 weeks while the biologic takes full effect. Many patients later reduce the nonsteroidal anti-inflammatory drug dose — or drop it to as-needed use — once the biologic brings BASDAI and C-reactive protein down. Others stay on both indefinitely for symptom control. For adults with stable ankylosing spondylitis taking a tumor necrosis factor inhibitor (TNFi) together with a nonsteroidal anti-inflammatory drug, the 2019 ACR/SAA/SPARTAN guideline conditionally recommends continuing the TNF inhibitor alone over continuing both (based on very low-quality evidence).
12. Topical Nonsteroidal Anti-Inflammatory Drugs — Adjunct Option
- Diclofenac gel 1% — now over-the-counter; useful for localized enthesitis (heel, Achilles, lateral epicondyle, knee).
- Diclofenac patches 1.3% — prescription; convenient for a single painful joint.
Topicals deliver local drug concentrations with a small fraction of systemic exposure, sparing most of the GI, CV, and renal risk. The limitation is that topicals don’t reach the axial spine or sacroiliac joints adequately — they are used as an add-on for peripheral symptoms, not a replacement for oral nonsteroidal anti-inflammatory drugs in axial disease.
13. Acetaminophen + Nonsteroidal Anti-Inflammatory Drugs
Acetaminophen (paracetamol) alone is inadequate for ankylosing spondylitis. Ankylosing spondylitis is an inflammatory disease, and acetaminophen has essentially no anti-inflammatory action — it doesn’t meaningfully reduce swelling, stiffness, or radiographic progression.
It is, however, a reasonable add-on for breakthrough pain: 500–1000 mg as needed, max 3 g/day (the old 4 g ceiling has been revised downward by most hepatology guidance). It works as a bridge for bad days, not as a disease-modifying treatment.
14. Alternative Anti-Inflammatories
- Turmeric / curcumin standardized to 95% curcuminoids, 500 mg two to three times daily. Modest anti-inflammatory effect in trials — gentler than prescription nonsteroidal anti-inflammatory drugs, nowhere near as potent. See Turmeric.
- Boswellia serrata standardized to boswellic acids. Similar story — real but modest effect. See Boswellia.
- Omega-3 fatty acids 2–4 g eicosapentaenoic acid (EPA)+docosahexaenoic acid (DHA) daily — modest anti-inflammatory, also cardioprotective, which pairs well with the CV considerations above.
These are adjuncts, not substitutes. In active ankylosing spondylitis with high C-reactive protein, they will not control the disease on their own. They may allow a slightly lower nonsteroidal anti-inflammatory drug dose.
15. Monitoring Schedule
- Before starting: complete blood count (CBC), comprehensive metabolic panel (CMP), eGFR, liver function tests (LFTs), blood pressure.
- 1 month in: CBC and creatinine to catch early problems.
- Every 6 months: CBC, CMP, eGFR, LFTs.
- Annually: H. pylori testing if chronic nonsteroidal anti-inflammatory drugs without proton pump inhibitor; blood pressure check.
- Symptom red flags — signs that hospitals treat as urgent, and the point at which the drug is stopped: black or tarry stool, coffee-ground emesis, new iron-deficiency anemia, severe abdominal pain, marked ankle swelling, sharp drop in urine output.
16. Nonsteroidal Anti-Inflammatory Drugs in Pregnancy
Nonsteroidal anti-inflammatory drug labels (celecoxib’s, for example) warn that use at about 20 weeks of pregnancy or later may cause fetal kidney problems leading to low amniotic fluid (oligohydramnios) and, in some cases, kidney impairment in the newborn. Use between about 20 and 30 weeks is limited, and use from about 30 weeks onward is avoided, because of those risks and the risk of premature closure of the fetal ductus arteriosus. Earlier in pregnancy, use is usually avoided if possible and kept to short courses when necessary. Acetaminophen is the safer analgesic during pregnancy. See Pregnancy and ankylosing spondylitis for the full pregnancy-specific medication strategy.
Key Research Papers
- Wanders A, et al. Nonsteroidal antiinflammatory drugs reduce radiographic progression in patients with ankylosing spondylitis: a randomized clinical trial. Arthritis & Rheumatism. 2005;52(6):1756-1765. — doi:10.1002/art.21054
- Sieper J, et al. Effect of continuous versus on-demand treatment of ankylosing spondylitis with diclofenac over 2 years on radiographic progression of the spine (ENRADAS). Annals of the Rheumatic Diseases. 2016;75(8):1438-1443. — doi:10.1136/annrheumdis-2015-207897
- Ward MM, Deodhar A, Gensler LS, et al. 2019 Update of the American College of Rheumatology/Spondylitis Association of America/Spondyloarthritis Research and Treatment Network Recommendations for the Treatment of Ankylosing Spondylitis and Nonradiographic Axial Spondyloarthritis. Arthritis & Rheumatology. 2019;71(10):1599-1613. — doi:10.1002/art.41042
- Ramiro S, et al. ASAS-EULAR recommendations for the management of axial spondyloarthritis: 2022 update. Annals of the Rheumatic Diseases. 2023;82(1):19-34. — PubMed PMID: 36270658
- Nissen SE, Yeomans ND, Solomon DH, et al. Cardiovascular Safety of Celecoxib, Naproxen, or Ibuprofen for Arthritis. New England Journal of Medicine. 2016;375(26):2519-2529. — PubMed PMID: 27959716
- Rajan JP, Wineinger NE, Stevenson DD, White AA. Prevalence of aspirin-exacerbated respiratory disease among asthmatic patients: A meta-analysis of the literature. Journal of Allergy and Clinical Immunology. 2015;135(3):676-681.e1. — PubMed PMID: 25282015
PubMed Topic Searches
Curated PubMed topic searches — each link opens a live query so you always see the most recent literature.
- PubMed: NSAID in ankylosing spondylitis
- PubMed: Celecoxib in axial spondyloarthritis
- PubMed: NSAIDs and radiographic progression in spondyloarthritis
- PubMed: Indomethacin in ankylosing spondylitis
- PubMed: NSAID gastrointestinal protection
- PubMed: COX-2 selective inhibitors and cardiovascular risk
- PubMed: Naproxen cardiovascular safety
- PubMed: Meloxicam in spondyloarthritis
Connections
- Rheumatology
- Ankylosing Spondylitis
- Human Leukocyte Antigen-B27 Explained
- Biologics Guide
- Ankylosing Spondylitis and Inflammatory Bowel Disease Overlap
- Exercise and PT Protocol
- Morning Stiffness Management
- Starch-Free Diet and Ebringer
- Pregnancy and Ankylosing Spondylitis
- Uveitis and Eye Involvement
- Arthritis
- Peptic Ulcer Disease
- Small Intestinal Bacterial Overgrowth
- Cardiovascular Disease
- Estimated Glomerular Filtration Rate Kidney Function
- Inflammatory Markers
- Turmeric