Preeclampsia
Table of Contents
1. Overview
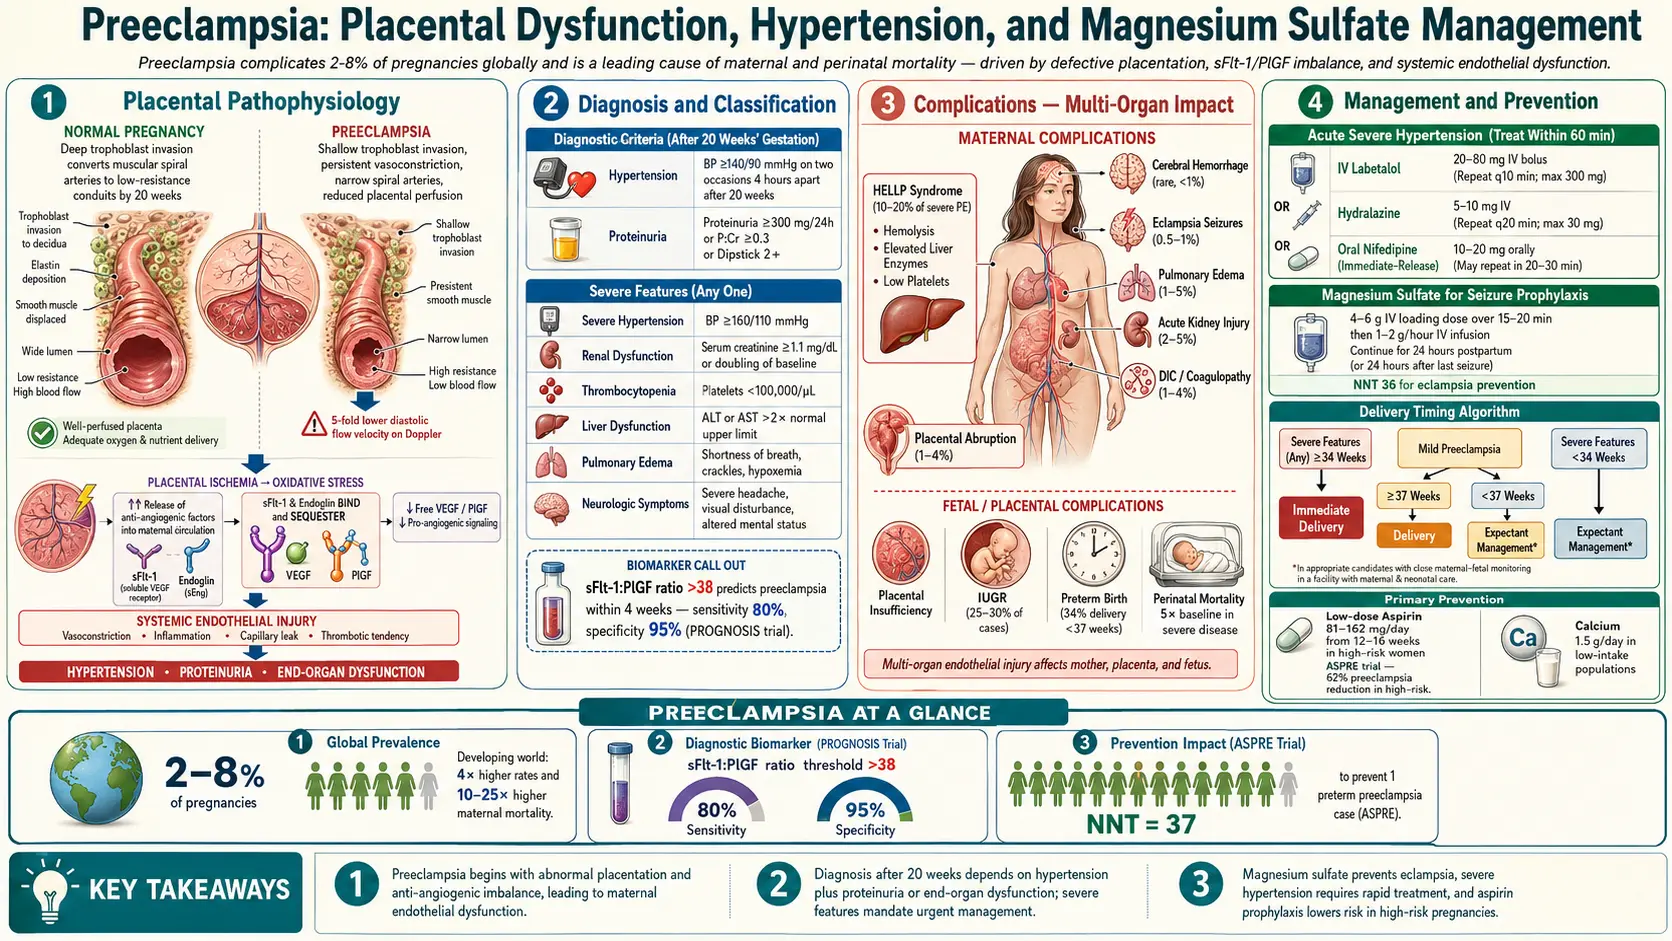
Preeclampsia is a multisystem hypertensive disorder of pregnancy defined by new-onset hypertension (systolic blood pressure of 140 mmHg or greater, or diastolic blood pressure (BP) of 90 mmHg or greater) after 20 weeks of gestation with proteinuria or, in the absence of proteinuria, with severe features including thrombocytopenia, renal insufficiency, impaired liver function, pulmonary edema, or new-onset headache unresponsive to medication or visual disturbances.
Preeclampsia exists within a spectrum of hypertensive disorders of pregnancy that includes gestational hypertension, preeclampsia with and without severe features, HELLP syndrome (Hemolysis, Elevated Liver enzymes, Low Platelets), and eclampsia. It is a leading cause of maternal and perinatal morbidity and mortality globally, and its only definitive treatment remains delivery of the fetus and placenta.
2. Epidemiology
Preeclampsia complicates approximately 2–8% of pregnancies worldwide, accounting for an estimated 76,000 maternal deaths and 500,000 perinatal deaths annually. Incidence varies significantly by geographic region, population characteristics, and diagnostic criteria. Rates are highest in low- and middle-income countries where access to antenatal care and emergency obstetric services is limited.
In the United States, preeclampsia affects approximately 3–4% of pregnancies, but incidence has increased by approximately 25% over the past two decades, paralleling rising rates of obesity, hypertension, and assisted reproductive technology use. Black women are disproportionately affected, with incidence approximately 60% higher than in White women and case fatality rates three to four times higher, reflecting disparities in access to care, comorbidities, and potentially biological differences in placentation.
Early-onset preeclampsia (before 34 weeks gestation) accounts for approximately 10% of cases but carries disproportionately severe maternal and perinatal outcomes. Late-onset preeclampsia (after 34 weeks) is more common but generally less severe.
3. Pathophysiology
Preeclampsia is fundamentally a placental disease mediated by abnormal trophoblastic invasion of the maternal spiral arteries and subsequent systemic endothelial dysfunction.
Stage 1: Defective Trophoblast Invasion
In normal implantation, extravillous cytotrophoblasts invade the maternal decidua and myometrium, remodeling spiral arteries from high-resistance, low-flow muscular vessels into dilated, low-resistance conduits capable of supplying the exponentially increasing blood flow demands of the growing placenta. In preeclampsia, this physiological transformation is incomplete: spiral arteries retain their muscular media and remain narrow, high-resistance vessels. This defective remodeling produces placental ischemia, particularly under the metabolic demands of the second and third trimesters.
Stage 2: Systemic Endothelial Dysfunction
Ischemic and oxidatively stressed placental tissue releases an imbalanced repertoire of pro- and anti-angiogenic factors into the maternal circulation:
- sFlt-1 (soluble FMS-like tyrosine kinase-1): A circulating anti-angiogenic protein that acts as a decoy receptor, sequestering free VEGF (vascular endothelial growth factor) and PlGF (placental growth factor), preventing them from binding their endothelial receptors and maintaining normal endothelial function.
- sEng (soluble endoglin): A circulating anti-angiogenic factor that inhibits TGF-beta signaling in endothelium, contributing to vasoconstriction and vascular permeability.
Elevated sFlt-1 and sEng, combined with reduced free PlGF, produce generalized maternal endothelial dysfunction characterized by: (1) vasospasm and hypertension, (2) increased vascular permeability leading to edema and proteinuria, (3) activation of the coagulation cascade with microthrombus formation, and (4) end-organ ischemia (renal, hepatic, cerebral, uteroplacental).
Renal Pathology: Glomerular Endotheliosis
The characteristic renal lesion of preeclampsia is glomerular endotheliosis: swelling and vacuolization of glomerular endothelial cells obliterating the capillary lumen. This produces reduced glomerular filtration rate (GFR), sodium retention, hyperuricemia, and the characteristic proteinuria of 300 mg or more per 24 hours.
Inflammatory and Immunological Components
Exaggerated systemic maternal inflammatory response, characterized by neutrophil and monocyte activation, elevated tumor necrosis factor-alpha, interleukin-6 (IL-6), and IL-8, and reduced regulatory T-cell function, contributes to endothelial activation and vascular injury. Aberrant immune tolerance to paternal (fetal) alloantigens at the maternal-fetal interface may underlie the primigravid and partner-change associations with preeclampsia.
4. Etiology and Risk Factors
High-Risk Factors (single factor sufficient for aspirin prophylaxis per U.S. Preventive Services Task Force)
- History of preeclampsia (recurrence risk 20–25%; higher in early-onset disease)
- Multifetal gestation (twin risk 3×, triplet risk 9× singleton)
- Chronic hypertension (superimposed preeclampsia risk 15–25%)
- Type 1 or Type 2 diabetes mellitus
- Renal disease
- Autoimmune conditions (systemic lupus erythematosus (SLE), antiphospholipid syndrome)
Moderate-Risk Factors (multiple factors needed to recommend aspirin)
- Nulliparity (two- to threefold increased risk)
- Obesity (body mass index (BMI) above 30): each unit increase in pre-pregnancy body mass index associated with approximately 6% increased preeclampsia risk
- Age 35 or older at delivery
- Black race (biological and structural factors both implicated)
- Low socioeconomic status and food insecurity
- Family history of preeclampsia (mother or sister)
- Interpregnancy interval greater than 10 years
- Donor egg or donor sperm (reduced immune tolerance)
- Thrombophilias (factor V Leiden, prothrombin gene mutation)
- In vitro fertilization
Placental and Fetal Factors
- Molar pregnancy (exaggerated trophoblastic mass)
- Hydrops fetalis
- Triploidy
5. Clinical Presentation
Preeclampsia Without Severe Features
- Blood pressure 140/90 mmHg or greater on two occasions at least 4 hours apart after 20 weeks
- Proteinuria: 300 mg or greater on 24-hour collection, protein:creatinine ratio of 0.3 or greater, or 2+ on dipstick (least preferred)
- OR in absence of proteinuria: any severe feature (see below)
Preeclampsia With Severe Features (any of the following)
- Severe-range blood pressure: systolic 160 mmHg or greater or diastolic 110 mmHg or greater on two occasions 4 hours apart (or immediately if both values are severe with clinical decision to treat)
- Thrombocytopenia: platelet count below 100,000/microliter
- Renal insufficiency: serum creatinine above 1.1 mg/dL or doubling of baseline creatinine
- Impaired liver function: liver transaminases twice normal upper limit; severe persistent right upper quadrant or epigastric pain unresponsive to medications
- Pulmonary edema
- New-onset headache unresponsive to medication and not accounted for by alternative diagnoses
- Visual disturbances (scotomata, photopsia, diplopia, blurring)
HELLP Syndrome
HELLP represents a severe variant with Hemolysis (microangiopathic hemolytic anemia: lactate dehydrogenase (LDH) above 600 international units (IU)/L, abnormal peripheral smear), Elevated Liver enzymes (aspartate aminotransferase (AST)/alanine aminotransferase (ALT) twice upper normal limit), and Low Platelets (below 100,000/microliter). Presents in approximately 10–20% of preeclampsia with severe features; can occur without hypertension or proteinuria in up to 20% of cases. Epigastric pain, nausea, and malaise are typical presenting complaints.
Eclampsia
New-onset grand mal (generalized tonic-clonic) seizures in a woman with preeclampsia not attributable to other causes. May occur antepartum (50%), intrapartum (25%), or postpartum (25%), up to 6 weeks after delivery. Preceded by severe features in most but not all cases; up to 20% of eclampsia occurs without antecedent hypertension or proteinuria.
6. Diagnosis
Blood Pressure Measurement
Accurate blood pressure measurement is foundational. Readings are taken with the person seated after 5 minutes of rest, using a cuff of the right size. Automated oscillometric devices validated for use in pregnancy (a validated automatic upper-arm blood pressure monitor) are used for consistency. Ambulatory blood pressure monitoring (ABPM) distinguishes white coat hypertension (20–30% of apparently hypertensive pregnancies) from sustained hypertension.
Urinary Protein Assessment
Preferred: spot protein:creatinine ratio (cutoff 0.3) or 24-hour urine collection (cutoff 300 mg). Dipstick proteinuria is unreliable and reserved for resource-limited settings only. Nephrotic-range proteinuria (above 3 g/24 hours) carries worse prognosis but does not by itself change management.
Laboratory Investigations
- Complete blood count with differential and platelet count
- Comprehensive metabolic panel (creatinine, blood urea nitrogen (BUN), liver function tests (LFTs), albumin)
- Lactate dehydrogenase, uric acid (hyperuricemia above 6 mg/dL correlates with disease severity)
- Peripheral blood smear (for hemolysis assessment in HELLP)
- Coagulation studies (prothrombin time (PT), activated partial thromboplastin time (aPTT), fibrinogen): indicated if platelets below 100,000 or HELLP suspected
Fetal Assessment
- Non-stress test (NST) or biophysical profile (BPP)
- Umbilical artery Doppler velocimetry: absent or reversed end-diastolic flow in the umbilical artery identifies fetuses at highest risk for adverse outcomes
- Estimated fetal weight by ultrasound: fetal growth restriction present in approximately 30% of early-onset preeclampsia
Angiogenic Biomarkers
The sFlt-1:PlGF ratio has emerged as a powerful diagnostic and prognostic biomarker. In the PROGNOSIS study (validation group of 550 women with suspected preeclampsia at 24 to 36+6 weeks), a ratio of 38 or lower ruled out preeclampsia in the following week 99.3% of the time (negative predictive value). A ratio above 38 predicted preeclampsia within 4 weeks only 36.7% of the time (positive predictive value), so a high ratio is a warning sign rather than a diagnosis. A ratio above 85 is associated with a high probability of delivery within 2 weeks due to preeclampsia. The ratio is commercially available in Europe and is U.S. Food and Drug Administration-cleared for risk stratification in the US. PlGF-based testing (automated sFlt-1/PlGF immunoassays) is increasingly integrated into early-onset preeclampsia screening protocols.
First-Trimester Preeclampsia Screening
The Fetal Medicine Foundation (FMF) combined first-trimester screening algorithm (11–13+6 weeks) integrates mean arterial pressure (MAP), uterine artery pulsatility index (UtA-PI), serum PlGF, and maternal history. In the SPREE screening study (16,747 pregnancies in seven English hospitals), maternal factors plus MAP and PlGF detected 69.0% of preterm preeclampsia (delivery before 37 weeks), and adding UtA-PI raised detection to 82.4%, compared with 40.8% for the NICE checklist method at its 10.3% screen-positive rate. The ASPRE trial used this screening to select high-risk women for aspirin.
7. Treatment and Obstetric Management
Delivery: The Only Definitive Treatment
Delivery is the only definitive cure for preeclampsia. Timing is determined by gestational age, severity of maternal and fetal disease, and institutional capacity for neonatal care.
Gestational Age-Based Management Thresholds
- 37 weeks or greater: Delivery indicated for all preeclampsia (with or without severe features); induction of labor is preferred over expectant management. In the HYPITAT trial (756 women at 36–41 weeks with gestational hypertension or mild preeclampsia), a poor maternal outcome occurred in 31% with induction versus 44% with expectant monitoring (relative risk 0.71, about 29% lower), and the authors advised induction beyond 37 weeks.
- 34–36+6 weeks (late preterm): Delivery indicated for preeclampsia with severe features. Expectant management may be appropriate for carefully selected cases of preeclampsia without severe features in centers with adequate monitoring capability.
- Less than 34 weeks (severe features present): Immediate stabilization of maternal condition (antihypertensive therapy, magnesium sulfate seizure prophylaxis, corticosteroids for fetal lung maturity), then delivery after 48 hours if feasible. Expectant management beyond 34 weeks is not recommended for severe features. ACOG and SMFM recommend against expectant management at any gestational age for HELLP syndrome, eclampsia, uncontrolled severe-range blood pressure, renal failure, or pulmonary edema.
- Less than 23–24 weeks (previable): Delivery is recommended for severe features; neonatal survival is generally not achievable; maternal health takes priority.
Antihypertensive Therapy
Severe-range blood pressure (160/110 mmHg or greater) requires urgent treatment within 30–60 minutes to prevent maternal stroke. First-line agents:
- Labetalol intravenous (IV): 20 mg bolus, repeat every 10 minutes (maximum 300 mg) or infusion 1–2 mg/min. The labetalol injection label lists bronchial asthma as a contraindication.
- Hydralazine intravenous: 5–10 mg bolus every 20–30 minutes (maximum 20 mg). Reflex tachycardia and unpredictable response.
- Nifedipine oral (immediate-release): 10–20 mg; onset 15–30 minutes. The sublingual route is not used because it can drop blood pressure too fast (precipitous hypotension). Concurrent use with magnesium sulfate was historically cautioned but is now considered safe.
- Oral antihypertensives for sustained control (non-severe blood pressure): Labetalol, nifedipine XL, and methyldopa are used for non-severe-range blood pressure in expectant management. Angiotensin-converting enzyme inhibitors (ACE inhibitors) and angiotensin receptor blockers (ARBs) are contraindicated in pregnancy.
Magnesium Sulfate
The gold standard for eclampsia seizure prophylaxis and treatment. Loading dose: 4–6 g intravenous over 15–20 minutes; maintenance: 1–2 g/hour infusion, continued for 24–48 hours postpartum. For eclamptic seizure: additional 2–4 g bolus; diazepam or lorazepam if seizure persists. Signs of toxicity: loss of deep tendon reflexes (first sign, at 7–10 mEq/L), respiratory depression (above 10 mEq/L), cardiac arrest (above 15 mEq/L). Calcium gluconate 1 g intravenous is the antidote. In renal insufficiency the dose is reduced and urine output is monitored.
Corticosteroids
Betamethasone 12 mg intramuscular (IM) every 24 hours for two doses (or dexamethasone 6 mg IM every 12 hours for four doses) to accelerate fetal lung maturity when delivery is anticipated before 36+6 weeks. In HELLP, high-dose dexamethasone (10 mg intravenous every 12 hours) may transiently improve platelet counts and transaminases, facilitating safe delivery, though does not alter maternal outcome.
Mode of Delivery
Vaginal delivery is preferred when maternal and fetal status permit. Cesarean delivery is indicated for obstetric indications (fetal malpresentation, prior classical uterine incision, unfavorable cervix with deteriorating maternal condition) rather than preeclampsia diagnosis alone. Spinal anesthesia is preferred over general anesthesia; epidural anesthesia is acceptable if platelet count is above 70,000–80,000/microliter.
Postpartum Management
Approximately 25% of eclamptic seizures occur postpartum, most within 48 hours but up to 6 weeks later. Magnesium sulfate is continued for 24–48 hours postpartum, and blood pressure medicine as needed. Nonsteroidal anti-inflammatory drug (NSAID) use in the puerperium may worsen hypertension, a concern raised mainly for severe preeclampsia. Labetalol, nifedipine, and methyldopa are compatible with breastfeeding (lactation).
8. Complications
Maternal Complications
- Eclampsia: Tonic-clonic seizures; risk of intracranial hemorrhage, aspiration pneumonia, placental abruption
- HELLP syndrome: Subcapsular liver hematoma with risk of hepatic rupture (catastrophic, mortality 50%); disseminated intravascular coagulation (DIC)
- Stroke and hypertensive encephalopathy
- Acute kidney injury: Acute tubular necrosis; cortical necrosis in severe prolonged cases
- Pulmonary edema: From increased capillary permeability and left ventricular dysfunction
- Placental abruption
- Disseminated intravascular coagulation (DIC)
- Long-term cardiovascular risk: In a 2007 meta-analysis of about 3.5 million women, a history of preeclampsia was linked to a 3.7-fold risk of high blood pressure (after about 14 years), a 2.16-fold risk of ischemic heart disease, a 1.81-fold risk of stroke and a 1.79-fold risk of blood clots in the veins, with no increase in cancer. A 2017 meta-analysis of more than 6.4 million women found a 4.19-fold risk of heart failure.
Fetal and Neonatal Complications
- Fetal growth restriction (FGR)
- Placental insufficiency and non-reassuring fetal status
- Preterm birth (iatrogenic and spontaneous)
- Stillbirth (risk increased three- to fourfold)
- Neonatal complications of prematurity (respiratory distress syndrome, intraventricular hemorrhage, necrotizing enterocolitis)
- Long-term neurodevelopmental sequelae of extreme prematurity
9. Prognosis
The prognosis for mother and infant depends critically on gestational age at onset, severity of disease, quality of obstetric care, and interval from diagnosis to delivery. Term preeclampsia without severe features carries excellent short-term maternal prognosis with prompt delivery. Early-onset severe preeclampsia before 28 weeks carries significantly elevated maternal and perinatal mortality and morbidity.
Recurrence risk is approximately 20–25% overall; up to 55% for women with preeclampsia requiring delivery before 28 weeks. Long-term maternal cardiovascular risk is substantially elevated: the 2007 meta-analysis concluded that a history of preeclampsia "should be considered when evaluating risk of cardiovascular disease in women", and a 2017 meta-analysis pointed to lifelong monitoring of cardiovascular risk factors (hypertension, dyslipidemia, diabetes, obesity).
10. Prevention
Low-Dose Aspirin
The cornerstone of preeclampsia prevention. Aspirin 81–162 mg daily (ACOG recommends 81 mg; NICE recommends 75–150 mg), initiated between 12 and 16 weeks gestation (preferably before 16 weeks) and continued until 36–37 weeks. In the ASPRE trial, 1,776 high-risk women identified by first-trimester combined screening took aspirin 150 mg a day or placebo from 11–14 weeks until 36 weeks; preterm preeclampsia (delivery with preeclampsia before 37 weeks) occurred in 1.6% on aspirin versus 4.3% on placebo (odds ratio 0.38, about 62% lower odds). The 2021 evidence review for the U.S. Preventive Services Task Force (16 trials, 14,093 women) found a 15% lower risk of preeclampsia with aspirin (relative risk 0.85), with lower risks of perinatal death (0.79), preterm birth (0.80) and poor fetal growth (0.82), and no clear increase in bleeding after birth. The U.S. Preventive Services Task Force (USPSTF) (2021) recommends low-dose aspirin (81 mg a day) after 12 weeks of pregnancy for people at high risk of preeclampsia (one or more high-risk factors or multiple moderate-risk factors; Grade B recommendation), concluding "with moderate certainty that there is a substantial net benefit" for preeclampsia, preterm birth, poor fetal growth and perinatal death.
Calcium Supplementation
In populations with low dietary calcium intake (below 600 mg/day), the World Health Organization (WHO) recommends 1.5–2 g elemental calcium daily in pregnancy. In the 2018 Cochrane review, high-dose calcium (at least 1 g a day) lowered preeclampsia risk by about 55% across all women studied (relative risk 0.45; 13 trials, 15,730 women) and by about 64% in women with low-calcium diets (relative risk 0.36), with no clear effect in women whose diets already had enough calcium (i.e., most high-income countries). The reviewers rated this low-quality evidence and noted the effect may be overestimated by small-study effects; in the largest trial the reduction was modest (8%).
Other Interventions
- Weight optimization before pregnancy (body mass index 18.5–24.9 kg/m2)
- Tight glycemic control in pre-existing diabetes
- Antihypertensive therapy for chronic hypertension: the CHIPS trial supports treating to a diastolic blood pressure of 85 mmHg, and the 2022 CHAP trial (2,408 pregnant women with mild high blood pressure from before pregnancy) found that treating to below 140/90 mmHg lowered serious pregnancy complications (preeclampsia with severe features, preterm birth before 35 weeks, placental abruption, or fetal or newborn death) from 37.0% to 30.2% (adjusted risk ratio 0.82) and any preeclampsia from 31.1% to 24.4%, with no increase in small-for-gestational-age babies (11.2% versus 10.4%)
- Heparin prophylaxis for women with antiphospholipid syndrome (reduces superimposed preeclampsia and adverse pregnancy outcomes)
- Smoking cessation (paradoxically, smoking appears to reduce preeclampsia incidence but dramatically worsens fetal outcomes and overall health)
11. Recent Research and Advances
sFlt-1:PlGF ratio-guided management: The PROGNOSIS trial established the clinical utility of the sFlt-1:PlGF ratio for short-term prediction of preeclampsia onset. The ratio enables individualized decisions about hospitalization, surveillance intensity, and delivery timing. A ratio below 38 provides a one-week "safe window" that can spare an unnecessary preterm delivery.
ASPRE trial and first-trimester screening: First-trimester combined screening with targeted aspirin prophylaxis reduces preterm preeclampsia by 62%, validating the FMF algorithm for widespread clinical implementation. Post-market effectiveness studies are confirming these benefits in real-world settings.
CHIPS trial (Control of Hypertension in Pregnancy Study): Demonstrated that "tight control" of maternal hypertension (diastolic blood pressure target 85 mmHg) versus "less tight control" (100 mmHg) reduces severe maternal hypertension without increasing pregnancy loss or neonatal morbidity, establishing a new standard for antihypertensive management in pregnancy.
Anti-sFlt-1 therapy (aflibercept analog, recombinant PlGF): Investigational therapies targeting the sFlt-1/PlGF imbalance are in early clinical trials. Apheresis (filtering the mother's plasma through a column) to remove sFlt-1 has been tested in small pilot studies. In a 2016 pilot study, a dextran-sulfate apheresis column in 11 women with very preterm preeclampsia lowered sFlt-1 by 18% on average; pregnancy continued 8 days after one treatment and 15 days after several, compared with 3 days in 22 untreated women. In a 2026 single-arm pilot trial, a column carrying antibodies against sFlt-1 was used in 16 women; in the 9 who had repeated sessions, each session lowered sFlt-1 by about 17% and mean blood pressure by about 4 mmHg, and pregnancy continued a median of 10 days after admission. Side effects included mild low blood calcium in 3 women. The authors state that controlled trials are needed.
Hydroxychloroquine: Hydroxychloroquine is being studied in pregnant women with antiphospholipid syndrome or antiphospholipid antibodies. The HYPATIA trial (hydroxychloroquine versus placebo added to standard treatment) published its protocol in 2017.
Postpartum cardiovascular risk management: Structured postpartum follow-up programs (cardiometabolic testing at 6 weeks, 6 months, and annually thereafter) are being implemented to translate the population-level epidemiological association between preeclampsia and long-term cardiovascular disease into actionable preventive care.
Key Research Papers
- ACOG Practice Bulletin No. 222: Gestational Hypertension and Preeclampsia. Obstet Gynecol. 2020;135(6):e237–e260. — doi:10.1097/AOG.0000000000003891
- Magee LA, Brown MA, Hall DR, et al. The 2021 International Society for the Study of Hypertension in Pregnancy classification, diagnosis and management recommendations for international practice. Pregnancy Hypertens. 2022;27:148–169. — doi:10.1016/j.preghy.2021.09.008
- Rolnik DL, Wright D, Poon LC, et al. Aspirin versus Placebo in Pregnancies at High Risk for Preterm Preeclampsia (ASPRE). N Engl J Med. 2017;377(7):613–622. — doi:10.1056/NEJMoa1704559
- Zeisler H, Llurba E, Chantraine F, et al. Predictive value of the sFlt-1:PlGF ratio in women with suspected preeclampsia (PROGNOSIS). N Engl J Med. 2016;374(1):13–22. — doi:10.1056/NEJMoa1414838
- Magee LA, von Dadelszen P, Rey E, et al. Less-tight versus tight control of hypertension in pregnancy (CHIPS). N Engl J Med. 2015;372(5):407–417. — doi:10.1056/NEJMoa1404595
- Mutter WP, Karumanchi SA. Molecular mechanisms of preeclampsia. Microvasc Res. 2008;75(1):1–8. — doi:10.1016/j.mvr.2007.04.009
- Levine RJ, Maynard SE, Qian C, et al. Circulating angiogenic factors and the risk of preeclampsia. N Engl J Med. 2004;350(7):672–683. — doi:10.1056/NEJMoa031884
- Redman CW, Sargent IL. Latest advances in understanding preeclampsia. Science. 2005;308(5728):1592–1594. — doi:10.1126/science.1111726
- Bellamy L, Casas JP, Hingorani AD, Williams DJ. Pre-eclampsia and risk of cardiovascular disease and cancer in later life: systematic review and meta-analysis. BMJ. 2007;335(7627):974. — doi:10.1136/bmj.39335.385301.BE
- WHO recommendations for prevention and treatment of pre-eclampsia and eclampsia. Geneva: World Health Organization; 2011. ISBN 978 92 4 154833 5.
- Duley L, Meher S, Jones L. Drugs for treatment of very high blood pressure during pregnancy. Cochrane Database Syst Rev. 2013;(7):CD001449. — doi:10.1002/14651858.CD001449.pub3
- Hofmeyr GJ, Lawrie TA, Atallah AN, Torloni MR. Calcium supplementation during pregnancy for preventing hypertensive disorders and related problems. Cochrane Database Syst Rev. 2018;10:CD001059. — doi:10.1002/14651858.CD001059.pub5
- Karumanchi SA, Granger JP. Preeclampsia and pregnancy-related hypertensive disorders. Hypertension. 2016;67(2):238–242. — doi:10.1161/hypertensionaha.115.05024
- Henderson JT, Vesco KK, Senger CA, et al. Aspirin use to prevent preeclampsia and related morbidity and mortality: updated evidence report and systematic review for the US Preventive Services Task Force. JAMA. 2021;326(12):1192–1206. — doi:10.1001/jama.2021.8551
- US Preventive Services Task Force, Davidson KW, Barry MJ, et al. Aspirin Use to Prevent Preeclampsia and Related Morbidity and Mortality: US Preventive Services Task Force Recommendation Statement. JAMA. 2021;326(12):1186–1191. — PubMed PMID: 34581729
- Koopmans CM, Bijlenga D, Groen H, et al. Induction of labour versus expectant monitoring for gestational hypertension or mild pre-eclampsia after 36 weeks' gestation (HYPITAT): a multicentre, open-label randomised controlled trial. Lancet. 2009;374(9694):979–988. — PubMed PMID: 19656558
- Tan MY, Wright D, Syngelaki A, et al. Comparison of diagnostic accuracy of early screening for pre-eclampsia by NICE guidelines and a method combining maternal factors and biomarkers: results of SPREE. Ultrasound Obstet Gynecol. 2018;51(6):743–750. — PubMed PMID: 29536574
- Tita AT, Szychowski JM, Boggess K, et al. Treatment for Mild Chronic Hypertension during Pregnancy. N Engl J Med. 2022;386(19):1781–1792. — PubMed PMID: 35363951
- Wu P, Haththotuwa R, Kwok CS, et al. Preeclampsia and Future Cardiovascular Health: A Systematic Review and Meta-Analysis. Circ Cardiovasc Qual Outcomes. 2017;10(2):e003497. — PubMed PMID: 28228456
- Thadhani R, Hagmann H, Schaarschmidt W, et al. Removal of Soluble Fms-Like Tyrosine Kinase-1 by Dextran Sulfate Apheresis in Preeclampsia. J Am Soc Nephrol. 2016;27(3):903–913. — PubMed PMID: 26405111
- Thadhani R, Hiemstra TF, Vatish M, et al. Targeted removal of soluble Fms-like tyrosine kinase 1 in very preterm preeclampsia: a pilot trial. Nat Med. 2026;32(6):2173–2181. — PubMed PMID: 42045577
- Schreiber K, Breen K, Cohen H, et al. HYdroxychloroquine to Improve Pregnancy Outcome in Women with AnTIphospholipid Antibodies (HYPATIA) Protocol: A Multinational Randomized Controlled Trial of Hydroxychloroquine versus Placebo in Addition to Standard Treatment in Pregnant Women with Antiphospholipid Syndrome or Antibodies. Semin Thromb Hemost. 2017;43(6):562–571. — PubMed PMID: 28609801
- Phipps EA, Thadhani R, Benzing T, Karumanchi SA. Pre-eclampsia: pathogenesis, novel diagnostics and therapies. Nat Rev Nephrol. 2019;15(5):275–289. — doi:10.1038/s41581-019-0119-6
- Featured Videos
PubMed Topic Searches
The following PubMed topic searches aggregate the current peer-reviewed literature. Each link opens a live PubMed query — results update as new studies are indexed.
- PubMed: Preeclampsia
- PubMed: Severe preeclampsia management
- PubMed: HELLP syndrome
- PubMed: Eclampsia magnesium sulfate
- PubMed: Magpie trial preeclampsia
- PubMed: Low dose aspirin preeclampsia prevention
- PubMed: SFlt-1 PlGF ratio
- PubMed: Chronic hypertension pregnancy
- PubMed: Preeclampsia placental pathology
- PubMed: Postpartum preeclampsia
- PubMed: Preeclampsia cardiovascular risk
- PubMed: Preeclampsia recurrence
Connections
- Reproductive Medicine
- Hypertension
- Magnesium
- Calcium
- Gestational Diabetes
- Vitamin D3
- Pregnancy and Hashimoto's
- Hashimoto's Thyroiditis
- Stroke
- Edema
- Obesity
- Creatinine
- Diabetes
- Anemia
- Heart Failure
- Thrombocytopenia
- Cardiovascular Disease
- Acute Kidney Injury
- Disseminated Intravascular Coagulation
- Cardiology