⚠ Evidence warning: Clinical trials or other evidence do not support the claims that breathing, humming and cold water on the face raise vagal tone and calm a flare, as credited to polyvagal practice. This page keeps it as a report of what people, websites or other media say.
Visceral Hypersensitivity and the Brain-Gut Axis in Irritable Bowel Syndrome (IBS)
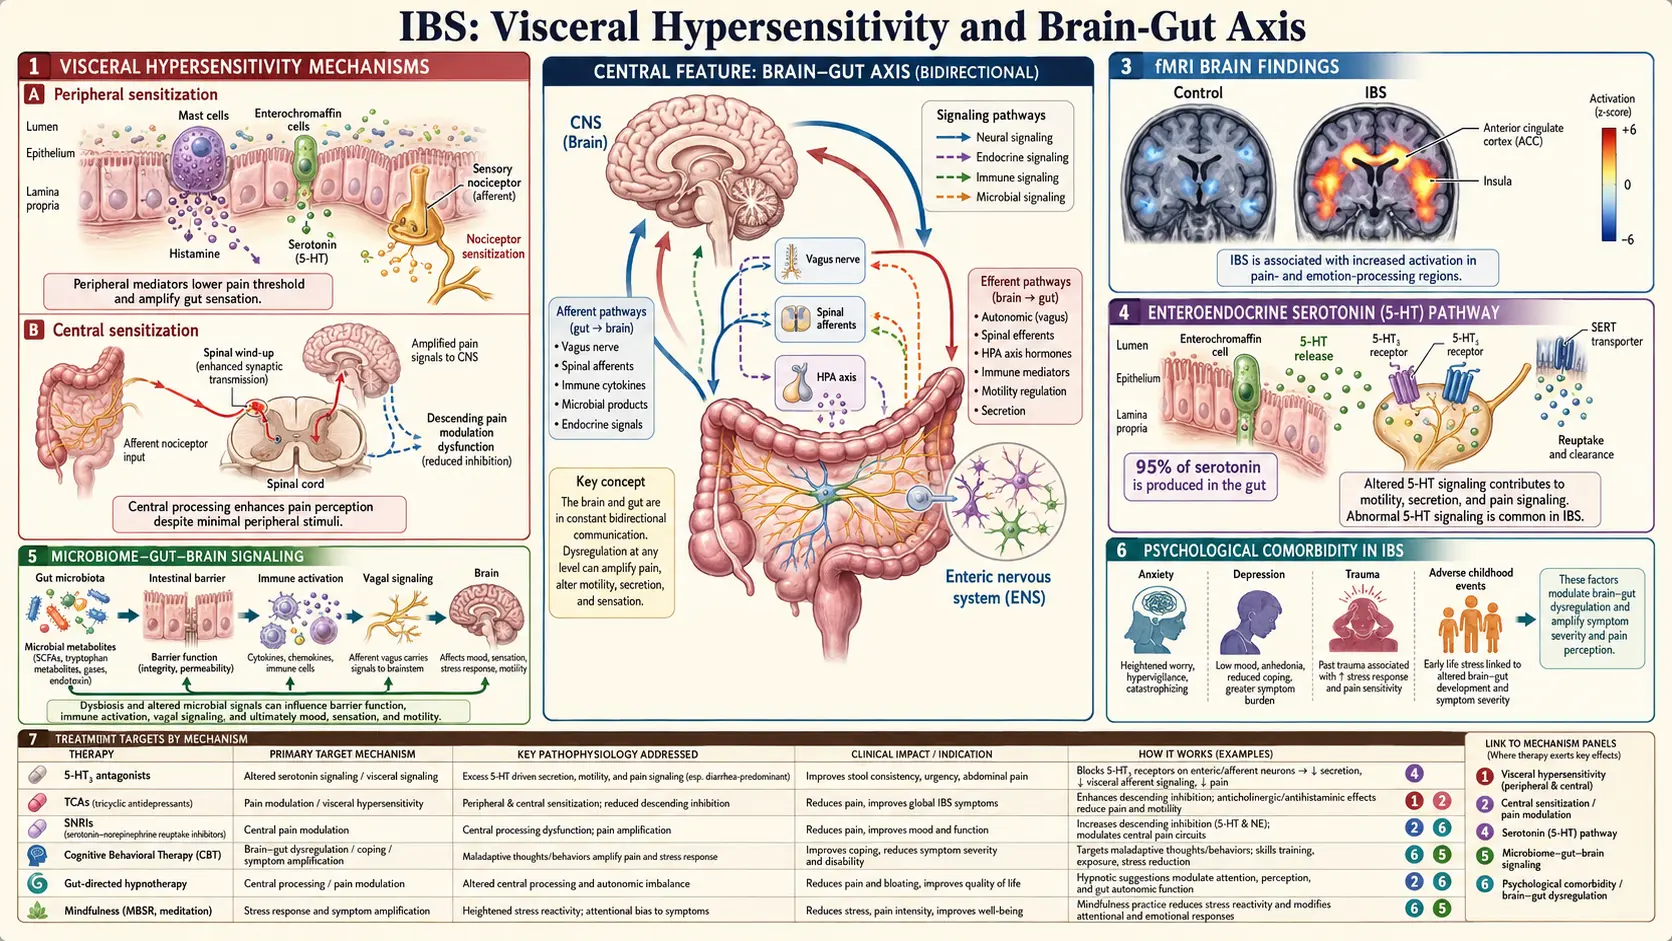
Table of Contents
- What Visceral Hypersensitivity Actually Is
- The Barostat Studies — Measuring a "Real" Pain Threshold
- The Biology: TRPV1, Mast Cells, and 5-HT3
- The Brain-Gut-Microbiome Axis
- The Enteric Nervous System — Your "Second Brain"
- How Stress Actually Triggers an Irritable Bowel Syndrome Flare
- Central Sensitization and the Overlap Conditions
- Why Low-Dose Selective Serotonin Reuptake Inhibitors and Tricyclic Antidepressants Help
- Gut-Directed Hypnotherapy — Why It Works
- Vagal Tone, HRV, and Polyvagal Theory
- Diet, Microbiome, and Upstream Signaling
- Early-Life Adversity and the ACE Connection
- The Post-Infectious Shift to Hyperalgesia
- Low-Cost Practices People Use
- Both Things Are True
- Key Research Papers
- Connections
- Featured Videos
What Visceral Hypersensitivity Actually Is
Your gut is constantly doing things. Food moves through it. Gas bubbles form and migrate. The muscular wall contracts and relaxes. The colon stretches when stool arrives. In healthy digestion, almost none of this reaches conscious awareness — the nervous system filters out the noise and only speaks up when something genuinely needs your attention.
In many people with irritable bowel syndrome (IBS), that filter appears to be broken. The same volume of gas, the same stretch of the bowel wall, the same normal peristaltic contraction registers as pain, urgency, bloating, or cramping. Your gut is not doing anything abnormal. Your nervous system is reporting normal events as alarming ones. This is visceral hypersensitivity, and it is the single best-validated biological finding in irritable bowel syndrome.
It matters because it reframes the entire illness. Irritable bowel syndrome is not "nothing wrong." It is not anxiety wearing digestive clothes. It is a real, measurable change in how the nerves of the gut and the pain-processing regions of the brain calibrate signals. The pain is real. The mechanism is real. And because the mechanism is neurological rather than structural, treatments aimed at the nervous system work — often better than anything aimed at the gut itself.
The Barostat Studies — Measuring a "Real" Pain Threshold
How do researchers prove that gut nerves are over-reactive rather than that patients are simply "complaining more"? The gold-standard tool is the rectal barostat. A small balloon is placed in the rectum and inflated in carefully controlled steps while the subject reports the volume at which they first feel the balloon, then discomfort, then pain.
The findings have been replicated across dozens of labs since the 1970s:
- Irritable bowel syndrome patients first perceive balloon distension at significantly lower volumes than healthy controls.
- The volume required to produce discomfort and pain is often described as 30–60% lower in irritable bowel syndrome than in matched controls. In a foundational balloon study published in 1973, inflating a balloon to 60 ml in the pelvic colon caused pain in 55% of 67 patients and in 6% of 16 controls.
- The share of patients who test abnormal varies by study. A 1995 study of 100 patients reported altered rectal perception in 94%. A 2007 study of 109 patients found it in 61%, and the rest tested normal (normosensitive); those with altered perception more often reported moderate or severe pain and bloating.
- Five patient groups totaling 1,144 people with irritable bowel syndrome or functional dyspepsia, reported in 2018, showed gut symptoms growing more severe as sensitivity rose. The effect sizes were small to medium, and the link held after correcting for anxiety and depression.
- The effect is reproducible even when subjects are blinded to the inflation steps — ruling out simple suggestibility.
- Functional magnetic resonance imaging (MRI) during distension shows irritable bowel syndrome brains activate pain-processing regions (anterior cingulate cortex, insula, thalamus) at distension levels that barely register in controls.
In short: as a group, people with irritable bowel syndrome have a lower pain threshold for gut distension, and it is measurable on a machine. Some patients with the diagnosis have normal rectal thresholds. The nervous-system change is not a metaphor.
The Biology: TRPV1, Mast Cells, and 5-HT3
Under the microscope, several mechanisms combine to lower the threshold.
TRPV1 channels are the same heat-and-capsaicin receptors that make chili peppers feel hot. They sit on sensory nerve endings in the gut wall. In irritable bowel syndrome, TRPV1 expression is increased, and the channels open in response to milder stimuli. Biopsy studies of irritable bowel syndrome colons consistently show elevated TRPV1-positive nerve fibers in the mucosa.
Mast cells are immune cells that live right next to visceral nerves. When they degranulate, they release histamine, tryptase, and prostaglandins directly onto nearby nerve endings, sensitizing them. Irritable bowel syndrome patients have more mast cells in the colonic mucosa, and the mast cells cluster closer to nerves than in healthy controls. This is part of why some irritable bowel syndrome overlaps clinically with mast cell activation syndrome (MCAS).
Serotonin (5-HT) is the molecule most people associate with mood — but roughly 90% of the body's serotonin is made in the gut, not the brain. Enterochromaffin cells in the intestinal lining release serotonin in response to food and stretch, and this serotonin drives motility, secretion, and sensation through the 5-HT3 receptor on sensory nerves. Diarrhea-predominant irritable bowel syndrome (IBS-D) patients tend to have elevated postprandial serotonin; constipation-predominant irritable bowel syndrome (IBS-C) patients may have reduced signaling. This is why a 5-HT3 antagonist (alosetron) reduces diarrhea and pain, and a 5-HT4 agonist (prucalopride, tegaserod) helps constipation. In the United States, the April 2019 re-approval of tegaserod was limited to women under 65 without heart disease or added cardiovascular risk factors, and the Food and Drug Administration withdrew its approval as of January 9, 2023, after the applicant reported the product was no longer marketed. See the irritable bowel syndrome medications guide.
Food can sensitize gut nerves, at least in mice. A 2021 study found that in mice a bacterial infection or bacterial toxins led to food-specific immunoglobulin E (IgE) antibodies limited to the intestine. Later eating of that food increased gut pain through mast cells and histamine H1 receptors. In patients with irritable bowel syndrome, injecting gluten, wheat, soy or milk proteins into the lining of the lower bowel caused local swelling and mast cell activation. The chain of events was shown in mice; the human part is a local injection test, not proof that this is what happens in patients.
The Brain-Gut-Microbiome Axis
Modern irritable bowel syndrome research talks less about "the brain" and "the gut" as separate organs and more about a continuous brain-gut-microbiome axis — a bidirectional communication network with at least four lanes of traffic:
- The vagus nerve. The tenth cranial nerve wanders from the brainstem down through the neck, chest, and abdomen, reaching the colon. Roughly 80% of vagal fibers carry signals upward from gut to brain; only 20% carry instructions downward. Your gut talks to your brain far more than your brain talks to your gut.
- The enteric nervous system (ENS). A mesh of 200–600 million neurons embedded in the gut wall that can coordinate digestion without any brain input at all (see the next section).
- The hypothalamic-pituitary-adrenal (HPA) axis. The hypothalamic-pituitary-adrenal stress system releases corticotropin-releasing hormone and cortisol, which modulate gut permeability, motility, and immune activity.
- Microbial metabolites. Gut bacteria ferment dietary fiber into short-chain fatty acids (SCFAs) — butyrate, propionate, acetate — that feed colon cells, reduce inflammation, and cross into circulation where they influence brain function. Microbes also produce neurotransmitters directly, including gamma-aminobutyric acid (GABA), dopamine, and serotonin precursors.
The practical point for an irritable bowel syndrome patient: a flare is not a one-direction event. Stress alters microbiome composition within hours. An altered microbiome changes what metabolites reach the brain. Those metabolites change mood and pain perception. Mood and pain perception change eating, sleeping, and vagal tone. And around it goes.
New research on an ear-clip vagus nerve stimulator. A 4-week single-center, single-blind trial in China randomized people with constipation-type irritable bowel syndrome to active stimulation through the ear or a sham version, with 20 people in each group. The active group improved more on pain score, symptom severity, spontaneous bowel movements and rectal sensation. Three people on active stimulation and two on sham had manageable adverse events. It is one small study.
The Enteric Nervous System — Your "Second Brain"
The enteric nervous system contains more neurons than the entire spinal cord. It uses every major neurotransmitter the brain uses — serotonin, dopamine, acetylcholine, gamma-aminobutyric acid, nitric oxide. It coordinates peristalsis, secretion, blood flow, and immune signaling locally. If the vagus nerve is severed, the gut continues to digest food on its own. This is why it earned the nickname the "second brain" (popularized by Michael Gershon's book of the same name).
In irritable bowel syndrome, the ENS is hypersensitive and can become dysregulated in its own right. Inflammation from an infection or immune trigger can remodel enteric neurons, lowering their firing thresholds for years. This "peripheral sensitization" layer exists alongside the central (brain) sensitization, and together they sustain symptoms long after any original trigger is gone.
How Stress Actually Triggers an Irritable Bowel Syndrome Flare
"Stress makes it worse" is the most eye-rolling advice an irritable bowel syndrome patient hears, because it usually comes with the implication that the problem is your failure to relax. The mechanism is not psychological. It is a chain of measurable physiological events:
- Stress activates the hypothalamic-pituitary-adrenal axis. The hypothalamus releases CRH (corticotropin-releasing hormone), which triggers the adrenal glands to pump out cortisol and the locus coeruleus to release norepinephrine.
- Stress hormones and mast cells raise intestinal permeability. In a 2014 study of healthy volunteers, public speaking raised small-intestine permeability only in those whose cortisol rose, corticotropin-releasing hormone alone reproduced the effect, and the mast-cell stabilizer disodium cromoglycate blocked both, which suggests that mast cells are involved. Tight junctions between gut epithelial cells loosen. Larger molecules slip through the barrier that should have stayed in the lumen.
- Mucosal mast cells are activated. The mast cells degranulate, dumping histamine and tryptase onto nearby nerve endings.
- Sensitized nerves fire more. Normal gas and peristalsis now register as cramping and urgency.
- The brain hears the noise and amplifies it. Anxiety about the flare feeds back into step 1.
Stress is not "all in your head" because the cascade includes your adrenal glands, your gut lining, and your immune cells. But stress starts in the brain, which is why brain-directed treatments legitimately interrupt it.
Central Sensitization and the Overlap Conditions
The same pain-amplifying mechanism that affects the gut in irritable bowel syndrome also affects the muscles in fibromyalgia, the pelvic floor in endometriosis, the bladder wall in interstitial cystitis, and the trigeminal nerve in chronic migraine. Rheumatologists and pain specialists call this pattern central sensitization — the central nervous system has turned up the gain on pain signals coming from many body regions at once.
This is why the same person so often has several of these diagnoses:
- Irritable bowel syndrome + fibromyalgia is one of the most-studied comorbidities in medicine (overlap roughly 30–70% depending on the cohort).
- Endometriosis and irritable bowel syndrome coexist in a high fraction of pelvic-pain patients; the chronic pelvic pain may outlast adequate endometriosis surgery because pelvic nerves are centrally sensitized (see pelvic floor therapy and central sensitization).
- Chronic migraine, TMJ pain, and irritable bowel syndrome cluster in the same patients.
- Autonomic overlap syndromes like postural orthostatic tachycardia syndrome (POTS) and myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS) share gut symptoms and sensitivity phenotypes.
For a detailed explanation of the underlying mechanism, see the fibromyalgia deep dive on central sensitization. Understanding this connection is useful because a treatment that calms central sensitization for one condition (low-dose tricyclic antidepressants (TCAs), for example, or graded aerobic exercise) will often help the others, too.
Why Low-Dose Selective Serotonin Reuptake Inhibitors and Tricyclic Antidepressants Help
When a gastroenterologist suggests a low-dose tricyclic antidepressant (TCA) like amitriptyline 10–25 mg at bedtime, or a selective serotonin reuptake inhibitor (SSRI) like sertraline, the most common patient reaction is frustration: "So you think this is depression?"
No — the mechanism is different. These drugs are prescribed for irritable bowel syndrome at doses too low to reliably treat depression (a TCA antidepressant dose is typically 75–150 mg). At low doses they work as central pain modulators: they raise descending inhibitory signals from the brainstem to the spinal cord, essentially turning down the volume knob on visceral pain inputs. Tricyclic antidepressants also have direct anticholinergic effects that slow gut transit, helpful in diarrhea-predominant irritable bowel syndrome.
The American College of Gastroenterology gives a strong recommendation for tricyclic antidepressants in irritable bowel syndrome, with an effect size comparable to or larger than many gut-directed drugs. Selective serotonin reuptake inhibitors (SSRIs) help a subset — particularly those with prominent constipation and anxiety — and serotonin-norepinephrine reuptake inhibitors (duloxetine) are useful when fibromyalgia or chronic pain coexists. The medications guide covers dosing, side effects, and how to choose among them.
The largest tricyclic trial. ATLANTIS, run in 55 English general practices, randomized 463 people whose symptoms continued despite first-line treatment to low-dose amitriptyline (10 mg a day, adjusted by the patient up to 30 mg) or placebo for 6 months. Amitriptyline did better by 27 points on the symptom severity score (95% confidence interval 7.1 to 46.9). Side effects led 13% to stop amitriptyline and 9% to stop placebo.
How the options rank. A 2026 network meta-analysis of 68 trials and 6,694 people compared treatments with a waiting list, as the risk of symptoms not improving. Serotonin-norepinephrine reuptake inhibitors ranked first (relative risk 0.49, six trials, none at low risk of bias), tricyclic antidepressants second (0.60, 15 trials) and dynamic psychotherapy third (0.62). Cognitive behavioral therapy, self-management, selective serotonin reuptake inhibitors and gut-directed hypnotherapy also beat a waiting list. The authors rate certainty in the evidence as low or very low for most comparisons.
Gut-Directed Hypnotherapy — Why It Works
Gut-directed hypnotherapy is not stage hypnosis, and it is not a placebo handwave. It is a structured protocol (typically 7–12 sessions following the Manchester or North Carolina scripts) that uses guided imagery and suggestion to change how the brain processes visceral signals. Brain imaging reports describe changes in anterior cingulate cortex and insula activation after a completed course — the same regions that light up abnormally during barostat distension. In a 2013 imaging study of women with moderate-to-severe irritable bowel syndrome, people who improved after hypnotherapy and people who improved after an educational program both showed a quieter insula, and symptoms fell by a similar amount in the two groups, so the change is not unique to hypnosis. Its published summary names the insula, not the anterior cingulate.
Response rates of 50–75% are often quoted, with benefits reported to persist for years after treatment ends. The IMAGINE randomized trial in 11 Dutch hospitals (354 people randomized) found lower figures: adequate relief at 3 months in 40.8% with individual sessions, 33.2% with group sessions and 16.7% with the control program, and at 12 months in 40.8%, 49.5% and 22.6%. Group delivery counted as no worse than individual delivery. A 2020 network meta-analysis found a relative risk of 0.67 for remaining symptomatic after gut-directed hypnotherapy, but its authors rate the trials at high risk of bias and say the benefit of psychological therapies has likely been overestimated. A 2025 meta-analysis gave a standardized effect of 0.73 on overall symptoms with a range (−0.09 to 1.55) that includes no effect, and 0.41 (0.05 to 0.77) for group delivery.
For severe, refractory irritable bowel syndrome, practitioners describe it as one of the most effective interventions ever studied, comparable to the best drug therapies. In IMAGINE, eight unexpected serious adverse reactions were reported, and the ethics committee judged them not related to the therapy. The sibling article on gut-directed hypnotherapy and cognitive behavioral therapy (CBT) covers protocols, app options, and how to find a qualified practitioner.
Vagal Tone, HRV, and Polyvagal Theory
Heart rate naturally speeds up slightly on each inhale and slows on each exhale. The size of that beat-to-beat variation is called heart rate variability (HRV), and it is the best non-invasive proxy for vagal tone — the moment-to-moment strength of your parasympathetic nervous system.
Irritable bowel syndrome patients, on average, have lower HRV than controls. Low HRV correlates with worse symptom severity, more post-meal pain, and more anxiety. This is not definitive proof of causation, but it dovetails with everything else: if your parasympathetic tone is low, your gut's natural "rest and digest" brake is weak, and your sympathetic stress response dominates.
The good news is that HRV is trainable. Slow breathing at roughly five to six breaths per minute (inhale for five to six seconds, exhale for five to six seconds) maximally increases vagal output and raises HRV over weeks of practice. Consumer heart-rate-variability biofeedback apps and wearables measure progress.
Polyvagal theory, proposed by Stephen Porges, is the most popular framing of vagal tone in the patient community: the idea that the vagus has two branches (a primitive "freeze" branch and a newer "social engagement" branch) and that trauma shifts you into the freeze state. It is a compelling and often helpful way to think about the body, but polyvagal theory's specific anatomical claims are contested in peer-reviewed neuroanatomy. The clinical practices that come out of it — slow breathing, humming, cold exposure to the face, safe social connection — are well supported even though the theoretical scaffolding is debated. The practices can be used without accepting the theory.
Diet, Microbiome, and Upstream Signaling
Changing what you eat changes which microbes flourish. Which microbes flourish changes which metabolites reach your bloodstream and brain. Diet is therefore not just "fuel" — it is an upstream lever on the entire brain-gut axis.
- Low-FODMAP, done properly as a 2–6 week elimination followed by structured reintroduction, reduces fermentation, gas, and distension — lowering the mechanical signal that sensitized nerves amplify. See the low-FODMAP guide.
- Fiber matters for short-chain fatty acid (SCFA) production. Butyrate from microbial fermentation of soluble fiber nourishes colonocytes and has direct anti-inflammatory effects. Chronically low-fiber diets starve the microbes that keep the gut lining healthy.
- Specific probiotics have been studied in irritable bowel syndrome (Bifidobacterium infantis 35624, for example) with modest benefit. This is not a universal prescription — see the peppermint and herbals page.
Diet is a partial, upstream lever. It does not replace nervous-system treatment, but it reduces the load on an already overreactive system.
Early-Life Adversity and the ACE Connection
Adverse Childhood Experiences (ACEs) — abuse, neglect, household dysfunction before age 18 — correlate with adult irritable bowel syndrome at roughly 2–4 times the rate of controls in multiple large cohort studies. The mechanism plausibly involves long-term calibration of the hypothalamic-pituitary-adrenal stress axis during development: a child in a chronically unsafe environment grows up with a stress response set to higher baseline activity and a gut that has matured in that hormonal bath.
This is not a claim that every irritable bowel syndrome patient has trauma, and it is not a claim that if you had a happy childhood your irritable bowel syndrome is not "real." It is simply that ACEs are one identifiable risk factor among many, and for patients whose irritable bowel syndrome began in childhood or alongside chronic anxiety, trauma-informed therapy (not just symptom-focused cognitive behavioral therapy) can be a legitimate piece of treatment.
The Post-Infectious Shift to Hyperalgesia
Roughly 10% of people who get a significant bout of food poisoning or gastroenteritis develop post-infectious irritable bowel syndrome. A 2017 meta-analysis of 45 studies gives the fuller numbers: 10.1% at 12 months after the infection and 14.5% after more than 12 months, 13.8% after a bacterial infection and 41.9% after a protozoal or parasitic one. The risk was 4.2-fold higher in people infected in the past 12 months than in those who had not been, and it was higher in women (odds ratio 2.2). The infection is long gone, but the gut nerves never re-calibrate. Mast cell density stays elevated for months to years. Sensory nerve fibers that sprouted during the inflammation remain. Anti-vinculin antibodies (produced in response to bacterial cytolethal distending toxin) cross-react with gut nerves and impair motility.
This is visceral hypersensitivity in its clearest causal form: a defined trigger, a measurable immunological fingerprint, and a persistent change in gut-nerve behavior. It is worth knowing about because the treatment priorities shift — mast-cell stabilizers, prokinetics, and sometimes rifaximin if small intestinal bacterial overgrowth (SIBO) has emerged — and the prognosis is better than people fear. See the post-infectious irritable bowel syndrome article for the full workup.
Low-Cost Practices People Use
People with irritable bowel syndrome use the following for the nervous-system side of the illness, without waiting for a specialist. They are cheap and described as low-risk, and the evidence behind them varies:
- Diaphragmatic breathing, twice daily. Usually described as five minutes morning and evening, with one hand on the chest and one on the belly so that only the belly hand moves, breathing in for a count of five and out for six. Practitioners report that this alone meaningfully raises vagal tone in weeks.
- HRV biofeedback. Free and paid apps pair with a chest strap or a phone camera. The usual description is 10–20 minutes a day of paced breathing with live feedback.
- Yoga, tai chi, or qigong. Slow movement, extended exhales, and parasympathetic activation. Irritable bowel syndrome-specific yoga trials show symptom improvement comparable to low-FODMAP.
- Walking after meals. Usually ten to twenty minutes. Described as improving gastric emptying, reducing postprandial bloat, and modestly raising HRV.
- Sleep. Sleep deprivation lowers pain thresholds across every chronic-pain condition ever studied. Seven to eight hours is the range usually cited.
- Cold water on the face. Splashing cold water on the forehead and cheeks triggers the mammalian dive reflex and a sharp vagal pulse. People use it to interrupt an acute anxiety-flare cascade.
- Dedicated gut-directed apps or therapy. See the hypnotherapy and cognitive behavioral therapy page for app options and how to find a gastrointestinal-psychology clinician.
Both Things Are True
This page comes down to two statements:
It is not in your head — meaning the pain is real. As groups, people with irritable bowel syndrome show measurably hyperreactive gut nerves, measurably lower pain thresholds on a machine that does not care whether anyone believes in them, and measurably more mast cells (raised counts in 30 of 36 biopsy studies reviewed in 2019, no difference in 5). Individual results vary, and some patients test normal.
And your brain is part of the treatment — meaning the nervous-system side of this illness is a legitimate target. Hypnotherapy, cognitive behavioral therapy, low-dose neuromodulators, HRV training, breathing practice, and sleep are not consolation prizes for people whose "real" treatment failed. They are mechanistically appropriate first-line interventions for a mechanistically neurological condition.
Patients who grasp both halves of that sentence at the same time tend to do best. The ones who fight off any suggestion of a brain component spend years chasing structural explanations that are not there. The ones who accept "it's all anxiety" stop pursuing legitimate pharmacologic and dietary help. The truth is both, at once, without apology.
Key Research Papers
- Mayer EA. Gut feelings: the emerging biology of gut-brain communication. Nat Rev Neurosci. 2011;12(8):453–466. — doi:10.1038/nrn3071
- Drossman DA. Functional gastrointestinal disorders: history, pathophysiology, clinical features, and Rome IV. Gastroenterology. 2016;150(6):1262–1279. — doi:10.1053/j.gastro.2016.02.032
- Enck P, Aziz Q, Barbara G, et al. Irritable bowel syndrome. Nat Rev Dis Primers. 2016;2:16014. — doi:10.1038/nrdp.2016.14
- Farmer AD, Aziz Q. Visceral pain hypersensitivity in functional gastrointestinal disorders. Br Med Bull. 2009;91:123–136. — doi:10.1093/bmb/ldp026 (Review on central mechanisms of visceral pain.)
- Ritchie J. Pain from distension of the pelvic colon by inflating a balloon in the irritable colon syndrome. Gut. 1973;14(2):125–132. — PubMed PMID: 4696535 (Foundational balloon-distension study demonstrating lowered pain thresholds in irritable colon syndrome; the balloon went through a sigmoidoscope into the pelvic colon.)
- Mertz H, Naliboff B, Munakata J, Niazi N, Mayer EA. Altered rectal perception is a biological marker of patients with irritable bowel syndrome. Gastroenterology. 1995;109(1):40–52. — PubMed PMID: 7797041
- Posserud I, Syrous A, Lindström L, Tack J, Abrahamsson H, Simrén M. Altered rectal perception in irritable bowel syndrome is associated with symptom severity. Gastroenterology. 2007;133(4):1113–1123. — PubMed PMID: 17919487
- Simrén M, Törnblom H, Palsson OS, et al. Visceral hypersensitivity is associated with GI symptom severity in functional GI disorders: consistent findings from five different patient cohorts. Gut. 2018;67(2):255–262. — PubMed PMID: 28104632
- Krammer L, Sowa AS, Lorentz A. Mast Cells in Irritable Bowel Syndrome: A Systematic Review. J Gastrointestin Liver Dis. 2019;28(4):463–472. — PubMed PMID: 31826052
- Aguilera-Lizarraga J, Florens MV, Viola MF, et al. Local immune response to food antigens drives meal-induced abdominal pain. Nature. 2021;590(7844):151–156. — PubMed PMID: 33442055
- Sayuk GS, Tack J. Tegaserod: What's Old Is New Again. Clin Gastroenterol Hepatol. 2022;20(10):2175–2184. — PubMed PMID: 35123085
- Food and Drug Administration. Teva Branded Pharmaceutical Products R and D, Inc., et al.; Withdrawal of Approval of 35 New Drug Applications. Federal Register. December 8, 2022;87 FR 75276. — Federal Register 2022-26661
- Liu J, Lv C, Yin M, et al. Efficacy and Safety of Transcutaneous Auricular Vagus Nerve Stimulation in Patients With Constipation-Predominant Irritable Bowel Syndrome: A Single-Center, Single-Blind, Randomized Controlled Trial. Am J Gastroenterol. 2024;120(9):2139–2153. — PubMed PMID: 39689011
- Vanuytsel T, van Wanrooy S, Vanheel H, et al. Psychological stress and corticotropin-releasing hormone increase intestinal permeability in humans by a mast cell-dependent mechanism. Gut. 2014;63(8):1293–1299. — PubMed PMID: 24153250
- Ford AC, Wright-Hughes A, Alderson SL, et al. Amitriptyline at Low-Dose and Titrated for Irritable Bowel Syndrome as Second-Line Treatment in primary care (ATLANTIS): a randomised, double-blind, placebo-controlled, phase 3 trial. Lancet. 2023;402(10414):1773–1785. — PubMed PMID: 37858323
- Khasawneh M, Thakur ER, Goodoory VC, Moayyedi P, Black CJ, Ford AC. Efficacy of gut-brain neuromodulators and brain-gut behaviour therapies for irritable bowel syndrome: systematic review and network meta-analysis. Gut. 2026 (online ahead of print). — PubMed PMID: 42362221
- Lowén MB, Mayer EA, Sjöberg M, et al. Effect of hypnotherapy and educational intervention on brain response to visceral stimulus in the irritable bowel syndrome. Aliment Pharmacol Ther. 2013;37(12):1184–1197. — PubMed PMID: 23617618
- Flik CE, Laan W, Zuithoff NPA, et al. Efficacy of individual and group hypnotherapy in irritable bowel syndrome (IMAGINE): a multicentre randomised controlled trial. Lancet Gastroenterol Hepatol. 2019;4(1):20–31. — PubMed PMID: 30473202
- Black CJ, Thakur ER, Houghton LA, Quigley EMM, Moayyedi P, Ford AC. Efficacy of psychological therapies for irritable bowel syndrome: systematic review and network meta-analysis. Gut. 2020;69(8):1441–1451. — PubMed PMID: 32276950
- Adler EC, Levine EH, Ibarra AN, et al. Gut-Directed Hypnotherapy for Irritable Bowel Syndrome: A Systematic Review and Meta-Analysis. Neurogastroenterol Motil. 2025;37(7):e70037. — PubMed PMID: 40179285
- Klem F, Wadhwa A, Prokop LJ, et al. Prevalence, Risk Factors, and Outcomes of Irritable Bowel Syndrome After Infectious Enteritis: A Systematic Review and Meta-analysis. Gastroenterology. 2017;152(5):1042–1054. — PubMed PMID: 28069350
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on visceral hypersensitivity, the brain-gut axis, and related irritable bowel syndrome neuroscience:
- PubMed: Visceral hypersensitivity in IBS
- PubMed: Brain-gut axis and irritable bowel syndrome
- PubMed: Rectal barostat and IBS pain thresholds
- PubMed: TRPV1, mast cells, and IBS
- PubMed: Serotonin, 5-HT3, and IBS
- PubMed: Gut-directed hypnotherapy for IBS
- PubMed: Heart rate variability and vagal tone in IBS
- PubMed: Central sensitization, fibromyalgia, and IBS overlap
- PubMed: Adverse childhood experiences and IBS
- PubMed: Tricyclic antidepressants as neuromodulators in IBS
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Irritable Bowel Syndrome
- Post-Infectious Irritable Bowel Syndrome
- Gut-Directed Hypnotherapy and Cognitive Behavioral Therapy
- Low-FODMAP Diet for Irritable Bowel Syndrome
- Irritable Bowel Syndrome Medications Guide
- Peppermint, Probiotics, and Herbals
- Irritable Bowel Syndrome and Small Intestinal Bacterial Overgrowth Overlap
- Rome IV Subtypes
- Fibromyalgia
- Central Sensitization
- Chronic Pain
- Postural Orthostatic Tachycardia Syndrome
- Mast Cell Activation Syndrome
- Chronic Fatigue Syndrome
- Endometriosis
- Pelvic Floor Therapy and Central Sensitization
- Gut-Brain Axis
- Anxiety