Irritable Bowel Syndrome (IBS) and Small Intestinal Bacterial Overgrowth (SIBO) Overlap
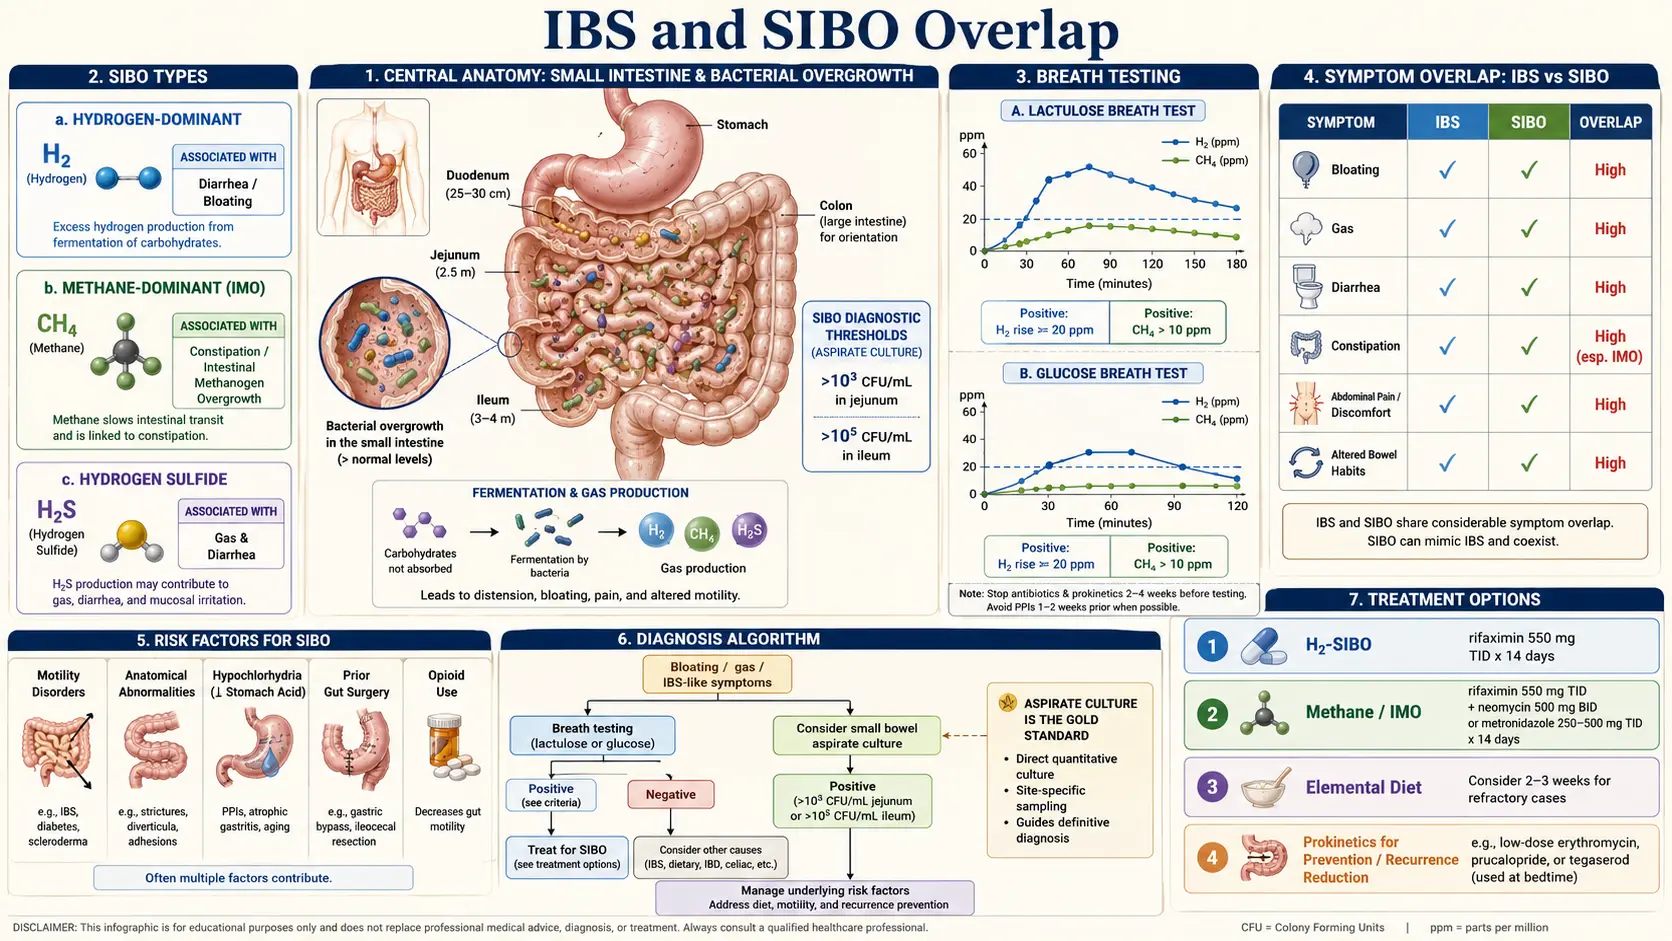
Table of Contents
- Why This Overlap Matters
- The Pimentel Studies — Where This All Started
- Cause, Consequence, or Co-Traveler?
- When a Breath Test Is Considered
- How the Test Actually Works
- Interpreting Your Results
- Why Diarrhea-Predominant Irritable Bowel Syndrome Maps to Hydrogen and Constipation-Predominant Irritable Bowel Syndrome Maps to Methane
- Rifaximin in Diarrhea-Predominant Irritable Bowel Syndrome — The TARGET Trials
- Treating Methane-Dominant IMO
- Treating the Small Intestinal Bacterial Overgrowth vs. Treating the Irritable Bowel Syndrome
- Finding the Root Cause
- Realistic Expectations — Why Relapse Is the Rule
- The Research on Repeated Antibiotic Courses
- Key Research Papers
- Connections
- Featured Videos
Why This Overlap Matters
For people told they have irritable bowel syndrome whose standard treatment — fiber, peppermint oil, an antispasmodic, maybe an antidepressant — has not helped, one open question is whether part of the irritable bowel syndrome (IBS) is actually small intestinal bacterial overgrowth (SIBO) hiding under the irritable bowel syndrome label. For a sizable fraction of irritable bowel syndrome patients, it is. Treating the overgrowth changes the game — sometimes dramatically, sometimes only for a while, but often enough that missing the diagnosis is one of the costliest oversights in gastrointestinal (GI) care.
Irritable bowel syndrome is a syndrome, which means it is defined by symptoms, not by a cause. Small intestinal bacterial overgrowth is a diagnosis, defined by an abnormal bacterial population in a place (the small intestine) where bacteria are normally relatively sparse. The two labels describe different things, and a person can carry both. The question is how often, and what follows from it.
The Pimentel Studies — Where This All Started
The modern irritable bowel syndrome-SIBO story begins at Cedars-Sinai in Los Angeles, with a gastroenterologist named Mark Pimentel. In a landmark 2000 paper and a series of follow-ups through the 2000s, Pimentel and colleagues took consecutive irritable bowel syndrome patients and put them through a lactulose breath test. The results reshaped an entire field:
- In the 2000 paper, an open-label case series, 157 of 202 people with irritable bowel syndrome (78%), of all subtypes, had an abnormal lactulose breath test read as overgrowth — the fingerprint of a hydrogen-producing bacterial overgrowth in the small bowel. Later work tied the hydrogen pattern to diarrhea-predominant irritable bowel syndrome (IBS-D).
- Patients with constipation-predominant irritable bowel syndrome (IBS-C) overwhelmingly produced excess methane instead — the signature of archaeal overgrowth, now formally called intestinal methanogen overgrowth (IMO).
- When the overgrowth was treated with antibiotics, irritable bowel syndrome symptoms improved in parallel with the breath-test numbers — for many, the first real relief in years.
The 2003 American Journal of Gastroenterology paper that formalized these findings became one of the most-cited pieces of irritable bowel syndrome research of the decade. It also ignited a debate that is still simmering — because not every group has been able to reproduce the 78% figure. Later studies using glucose breath tests (which sample only the proximal small bowel) landed closer to 30–40%. Study design, test choice, and diagnostic cutoffs all matter.
Cause, Consequence, or Co-Traveler?
There are three camps in the medical literature, and they still argue at conferences.
Camp 1 — small intestinal bacterial overgrowth causes irritable bowel syndrome. This is the Pimentel position. If you fix the overgrowth, the syndrome resolves; therefore the bacteria were driving the symptoms all along. Antibiotics help because they treat the actual disease.
Camp 2 — small intestinal bacterial overgrowth is a downstream consequence. In this view the underlying problem is slow or disordered motility in the small intestine, perhaps autoimmune. Bacteria accumulate because the small bowel is not sweeping itself clean. Kill the bacteria and they come back, because the motility defect is still there.
Camp 3 — It is a co-traveler, not the same disease. Some irritable bowel syndrome is truly about visceral hypersensitivity and the brain-gut axis (see the visceral hypersensitivity article). Some is post-infectious autoimmunity. Some is pelvic-floor dyssynergia. Small intestinal bacterial overgrowth is one of several overlapping conditions, not the umbrella diagnosis.
The practical truth is probably that all three camps are partially right for different patients. That is why breath testing matters in this approach — it is used to sort which pattern a given person fits, so treatment can follow the biology instead of guessing.
When a Breath Test Is Considered
A small intestinal bacterial overgrowth breath test is commonly considered in people with irritable bowel syndrome-type symptoms plus one or more of these features:
- Bloating that dominates the day — a flat abdomen in the morning that distends dramatically by afternoon, often visibly, often painfully.
- Symptoms that flare within 30–90 minutes of eating, especially carbohydrate-rich meals.
- Diarrhea with foul gas (suggests hydrogen-sulfide overgrowth).
- Unexplained constipation, particularly slow-transit constipation that does not respond to fiber or standard laxatives (suggests methane/IMO).
- A known risk factor: past food poisoning, abdominal surgery, opiate use, proton-pump-inhibitor use over months or years, hypothyroidism, diabetes, scleroderma, or a diagnosis of postural orthostatic tachycardia syndrome (POTS) or Ehlers-Danlos.
- A previous good-enough trial of standard irritable bowel syndrome therapy (fiber, antispasmodic, low-FODMAP, a selective serotonin reuptake inhibitor/TCA) that did not work.
Breath tests are available through a gastroenterologist or as an at-home kit from commercial labs: two-gas tests (lactulose or glucose, measuring hydrogen and methane) and a commercial breath test measuring hydrogen, methane and hydrogen sulfide. In-clinic testing is also available at many gastrointestinal practices and hospital gastrointestinal labs; the logistics are identical, just the kit sits in a clinic rather than a kitchen.
How the Test Actually Works
The principle is simple. Bacteria in your small intestine ferment carbohydrate. The gases they produce — hydrogen, methane, and hydrogen sulfide — are absorbed into the bloodstream, carried to the lungs, and exhaled. If you drink a standardized sugar and then measure breath gas every 15–20 minutes, you get a time-course that shows when and how much gas is being produced along your gut.
Two substrates are in common use:
- Lactulose — a non-absorbable sugar that travels the full length of the small bowel. Better for detecting distal overgrowth. More prone to false positives from rapid transit reaching the colon.
- Glucose — absorbed in the first 60–90 cm of the small bowel. More specific for proximal overgrowth but misses distal disease.
The collection window is 2 to 3 hours, with samples every 15 or 20 minutes. Preparation matters: a 24-hour low-fermentable-carbohydrate prep the day before, a 12-hour overnight fast, no antibiotics for four weeks prior, no probiotics or laxatives for a week, no smoking or exercise the morning of the test. Without this preparation the result is hard to read.
Interpreting Your Results
The 2017 North American Consensus (Rezaie and colleagues, American Journal of Gastroenterology) set the cutoffs most modern labs use:
- Hydrogen-positive small intestinal bacterial overgrowth — a rise of ≥20 ppm above baseline within 90 minutes of substrate ingestion.
- Intestinal methanogen overgrowth (IMO) — any methane value ≥10 ppm at any time point. Methane does not need a "rise" the way hydrogen does; methanogens are slow and steady producers, so a flat elevated line counts.
- Hydrogen sulfide (three-gas test only) — a rise of ≥3 ppm, or a flat-line elevation pattern. Often correlates with severe diarrhea and foul-smelling gas.
A "double peak" pattern on a lactulose test — an early peak in the small bowel and a later peak in the colon — was once taught as the classic small intestinal bacterial overgrowth signature. The 2017 consensus largely dropped the two-peak requirement and moved to the simpler 20-ppm/90-minute rule because the double peak was inconsistent and hard to score reliably.
Why Diarrhea-Predominant Irritable Bowel Syndrome Maps to Hydrogen and Constipation-Predominant Irritable Bowel Syndrome Maps to Methane
This is the piece that makes the biology click. Hydrogen is produced by many kinds of bacteria. When hydrogen builds up in the small bowel, it increases osmotic pull, accelerates transit, and — combined with the bacterial metabolites that go with it — causes watery, urgent diarrhea with bloating. Hence the diarrhea-predominant irritable bowel syndrome pattern.
Methane is produced by a single dominant group of microbes — archaea, primarily Methanobrevibacter smithii. Methane is itself a motility inhibitor. Animal and human studies have shown that methane gas slows small-bowel and colonic transit, contributing to constipation. The more methane on your breath test, the slower your gut tends to move. This is why constipation-predominant irritable bowel syndrome so often maps to methane/IMO — the gas is not a side effect of the constipation, it is part of what causes it.
Hydrogen sulfide is the newest of the three. It is produced by sulfate-reducing bacteria and by the breakdown of sulfur-containing foods (eggs, garlic, cruciferous vegetables). Clinically it tracks with diarrhea and the "rotten egg" gas that patients describe with embarrassment. It was not measured on routine breath tests until a commercial three-gas breath test appeared in 2020.
Rifaximin in Diarrhea-Predominant Irritable Bowel Syndrome — The TARGET Trials
The single most important set of diarrhea-predominant irritable bowel syndrome treatment data of the past 20 years is the TARGET program — three large randomized controlled trials of rifaximin. TARGET-1 and TARGET-2 were published together in The New England Journal of Medicine in 2011. TARGET-3 followed.
The protocol is straightforward: rifaximin 550 mg orally three times a day for 14 days. Rifaximin is a non-absorbed antibiotic — over 99% of the dose stays in the gut lumen, so systemic side effects are minimal. In TARGET-1 and TARGET-2, roughly 40–41% of rifaximin-treated patients reported adequate relief of global irritable bowel syndrome symptoms in the month after treatment, versus 31–32% on placebo. Bloating response was similar. The drug received U.S. Food and Drug Administration (FDA) approval for diarrhea-predominant irritable bowel syndrome on the strength of these data.
TARGET-3 then answered the harder question: what happens when symptoms come back? The trial showed that repeat rifaximin courses worked in patients who had responded to the first course, and the effect held up over multiple cycles. That is the realistic clinical pattern for most diarrhea-predominant irritable bowel syndrome patients with hydrogen-positive breath tests — responders respond again, typically several months between courses.
Cost is the real-world obstacle. Rifaximin in the United States runs roughly $2,000–$2,500 for a 14-day course. With prior authorization (usually after documenting diarrhea-predominant irritable bowel syndrome plus a failed trial of standard therapy) most major insurers cover it. Manufacturer copay programs and international pharmacies can cut costs substantially for uninsured patients. See the rifaximin protocols article for dosing details, insurance tactics, and combination regimens.
Treating Methane-Dominant IMO
Methane responds differently. Rifaximin alone clears methane in only a minority of IMO patients because archaea are genetically and metabolically distinct from bacteria. The combination most often cited comes from a 2010 retrospective chart review (Low and colleagues) of people with methane on a lactulose breath test: rifaximin 400 mg three times a day + neomycin 500 mg twice a day for 10 days. Neomycin targets the archaea that rifaximin alone leaves behind. In that review, 85% of people on the combination had a clinical response, versus 56% on rifaximin alone; methane cleared from the breath test in 87% on the combination, versus 28% on rifaximin alone and 33% on neomycin alone.
An alternative to neomycin is metronidazole 250–500 mg TID for 14 days, often chosen because it is cheaper and more easily prescribed. Some clinicians pair rifaximin with allicin (a concentrated garlic extract) as a natural antimicrobial with anti-archaeal activity. Both approaches have supportive case series but less trial data than the rifaximin-neomycin pairing.
For details on herbal antimicrobials as a standalone or adjunctive approach, see the herbal antimicrobials article. For the nuclear option — an elemental diet — see the elemental diet article.
Treating the Small Intestinal Bacterial Overgrowth vs. Treating the Irritable Bowel Syndrome
When the breath test is positive and the symptoms match, clinicians who follow this approach usually treat the small intestinal bacterial overgrowth first — and sometimes the irritable bowel syndrome dissolves entirely once the overgrowth is gone. But not always. Three realistic scenarios:
Scenario A — small intestinal bacterial overgrowth treatment fixes everything. Roughly a third of breath-test-positive irritable bowel syndrome patients get a complete or near-complete response to a properly dosed rifaximin course and stay well for months. These are the clearest wins. The diagnosis was small intestinal bacterial overgrowth; the irritable bowel syndrome label was a placeholder.
Scenario B — small intestinal bacterial overgrowth treatment helps a lot but not completely. The bloating drops, the diarrhea eases, but residual pain and urgency remain. This is very common. It suggests two things are going on — the overgrowth and an underlying visceral-hypersensitivity or brain-gut component. The standard irritable bowel syndrome toolkit still applies: low-FODMAP (see the low-FODMAP guide), an antispasmodic or peppermint oil, gut-directed hypnotherapy, maybe a low-dose TCA.
Scenario C — small intestinal bacterial overgrowth treatment helps little. Either the test was a false positive, or the symptoms were never primarily small intestinal bacterial overgrowth-driven. Care then usually returns to irritable bowel syndrome-focused treatment, since further antibiotic courses have no overgrowth to act on.
Finding the Root Cause
Small intestinal bacterial overgrowth usually has an underlying cause. The single most productive question in a small intestinal bacterial overgrowth work-up is why. The leading root causes (covered in depth in the small intestinal bacterial overgrowth root causes article):
- Post-infectious autoimmunity. An episode of food poisoning triggers antibodies against a bacterial toxin called CdtB. Because CdtB resembles a human protein called vinculin that lives in the interstitial cells of Cajal (the pacemaker cells of the gut), the immune system cross-reacts and damages the gut's own motility machinery. The Cedars-Sinai team developed a commercial blood test for anti-CdtB and anti-vinculin antibodies to identify this subtype. Anywhere from a third to two-thirds of diarrhea-predominant irritable bowel syndrome cases appear to be post-infectious. See the post-infectious irritable bowel syndrome article.
- Migrating motor complex (MMC) dysfunction. The MMC is the "housekeeper wave" that sweeps the small intestine clean between meals. When it is weak or absent, bacteria accumulate. The MMC is damaged by post-infectious autoimmunity, opiates, and chronic stress.
- Ileocecal valve dysfunction. A leaky or incompetent valve between small bowel and colon lets colonic bacteria back-flow upstream.
- Adhesions and structural issues. Scarring from surgery, endometriosis, or inflammatory bowel disease can create pockets where bacteria stagnate.
- Hypothyroidism. Low thyroid slows gut transit. Correcting thyroid levels often reduces small intestinal bacterial overgrowth recurrence.
- Scleroderma and other connective-tissue diseases. Smooth-muscle damage in the small bowel leads to severe, relapsing small intestinal bacterial overgrowth that is notoriously hard to clear.
- Chronic proton pump inhibitor (PPI) use. Stomach acid is an important bacterial filter. Long-term acid suppression removes that filter.
Identifying the root cause does not always give a clean fix, but it shows what is driving the overgrowth and which long-term strategies matter.
Realistic Expectations — Why Relapse Is the Rule
Relapse is common. In a 2008 study of 80 people whose overgrowth had cleared after rifaximin (Lauritano and colleagues), the glucose breath test was positive again in 12.6% at 3 months, 27.5% at 6 months and 43.7% at 9 months; older age, a past appendectomy and long-term proton pump inhibitor use were linked to the return. Practitioners report a higher relapse rate in people with a strong post-infectious or scleroderma root cause, and a much lower one when a modifiable cause (proton pump inhibitor use, opiates, hypothyroidism) is fixed.
Relapse is not failure. It is the natural history of a condition whose root cause — usually a motility problem — has not been cured, only treated. The goal of long-term management is to stretch the interval between treatments and to reduce symptom burden in between. The tools that do that work:
- Prokinetics. Low-dose medications that restore the migrating motor complex. Prucalopride (2 mg nightly), low-dose erythromycin (50–100 mg nightly), or low-dose naltrexone are the mainstays. Taken nightly, they measurably reduce relapse rates. See the prokinetics article.
- Meal spacing. Practitioners describe four to five hours between meals, without constant snacking, because the MMC runs only between meals.
- Targeted diet. A moderately-reduced-fermentable-carb diet (not lifelong strict low-FODMAP) during symptom flares.
- Root-cause maintenance. Practitioners point to treating low thyroid, stopping long-term proton pump inhibitors (PPIs) where possible, treating adhesions, and regular physical activity.
The Research on Repeated Antibiotic Courses
It is tempting, after the first rifaximin course works, to simply re-run it every time symptoms come back. Some patients do exactly that for years. The problem is that antibiotic cycling without root-cause work has diminishing returns.
Each round doses the same bacteria with the same drug. Resistance is not yet a large-scale problem with rifaximin because so little is absorbed, but response rates do tend to slip for some patients over multiple cycles. Repeated courses also cost thousands of dollars and disrupt the microbiome each time, while the driver — a motility defect or an immune-mediated process — remains. Whatever caused the last relapse is still present for the next one.
Practitioners who treat small intestinal bacterial overgrowth describe pairing an antibiotic course with two parallel efforts: looking for the root cause (post-infectious serology, thyroid, structural imaging if indicated) and starting a prokinetic after the course finishes. They report that patients who do both see remission intervals stretch from months to years, while those who only repeat antibiotics tend to stay in a three-month cycle.
In that practice view, fast relapse after three cycles points to an unaddressed root cause rather than to a fourth course.
Key Research Papers
- Pimentel M, Chow EJ, Lin HC. Normalization of lactulose breath testing correlates with symptom improvement in irritable bowel syndrome: a double-blind, randomized, placebo-controlled study. Am J Gastroenterol. 2003;98(2):412–419. — PubMed PMID: 12591062 · doi:10.1111/j.1572-0241.2003.07234.x
- Pimentel M, et al. Rifaximin therapy for patients with irritable bowel syndrome without constipation (TARGET-1 and TARGET-2). N Engl J Med. 2011;364(1):22–32. — PubMed PMID: 21208106 · doi:10.1056/NEJMoa1004409
- Rezaie A, et al. Hydrogen and methane-based breath testing in gastrointestinal disorders: the North American Consensus. Am J Gastroenterol. 2017;112(5):775–784. — PubMed PMID: 28323273 · doi:10.1038/ajg.2017.46
- Pimentel M, et al. Development and validation of a biomarker for diarrhea-predominant irritable bowel syndrome in human subjects (anti-CdtB and anti-vinculin). PLoS One. 2015;10(5):e0126438. — PubMed PMID: 25970536 · doi:10.1371/journal.pone.0126438
- Pimentel M, Chow EJ, Lin HC. Eradication of small intestinal bacterial overgrowth reduces symptoms of irritable bowel syndrome. Am J Gastroenterol. 2000;95(12):3503–3506. — PubMed PMID: 11151884 · doi:10.1111/j.1572-0241.2000.03368.x
- Lauritano EC, Gabrielli M, Scarpellini E, et al. Small intestinal bacterial overgrowth recurrence after antibiotic therapy. Am J Gastroenterol. 2008;103(8):2031–2035. — PubMed PMID: 18802998 · doi:10.1111/j.1572-0241.2008.02030.x
- Low K, Hwang L, Hua J, et al. A combination of rifaximin and neomycin is most effective in treating irritable bowel syndrome patients with methane on lactulose breath test. J Clin Gastroenterol. 2010;44(8):547–550. — PubMed PMID: 19996983 · doi:10.1097/MCG.0b013e3181c64c90
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on the irritable bowel syndrome–small intestinal bacterial overgrowth overlap, breath testing, and treatment:
- PubMed: IBS and SIBO breath testing
- PubMed: Rifaximin and the TARGET trials
- PubMed: Methane, constipation, and intestinal methanogen overgrowth
- PubMed: Hydrogen sulfide SIBO and diarrhea
- PubMed: Anti-CdtB, anti-vinculin, and post-infectious IBS
- PubMed: Migrating motor complex and SIBO
- PubMed: Prokinetics and SIBO relapse prevention
- PubMed: Lactulose vs. glucose breath testing for SIBO
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Irritable Bowel Syndrome
- Small Intestinal Bacterial Overgrowth
- Elemental Diet
- Small Intestinal Bacterial Overgrowth Root Causes
- Herbal Antimicrobials
- Rifaximin Protocols
- Prokinetics and Relapse Prevention
- Low-FODMAP Diet for Small Intestinal Bacterial Overgrowth
- Small Intestinal Bacterial Overgrowth Breath Test Guide
- Hydrogen vs Methane vs Hydrogen Sulfide
- Post-Infectious Irritable Bowel Syndrome
- Rome IV Subtypes
- Low-FODMAP Diet for Irritable Bowel Syndrome
- Visceral Hypersensitivity and Brain-Gut Axis
- Irritable Bowel Syndrome Medications Guide
- Postural Orthostatic Tachycardia Syndrome
- Constipation
- Bloating