⚠ Evidence warning: Clinical trials or other evidence do not support the claim that low-dose naltrexone and other prokinetics reduce relapse, that the blood test predicts rifaximin response, and that tinidazole or nitazoxanide resolves lingering symptoms. This page keeps it as a report of what people, websites or other media say.
Post-Infectious Irritable Bowel Syndrome (IBS)
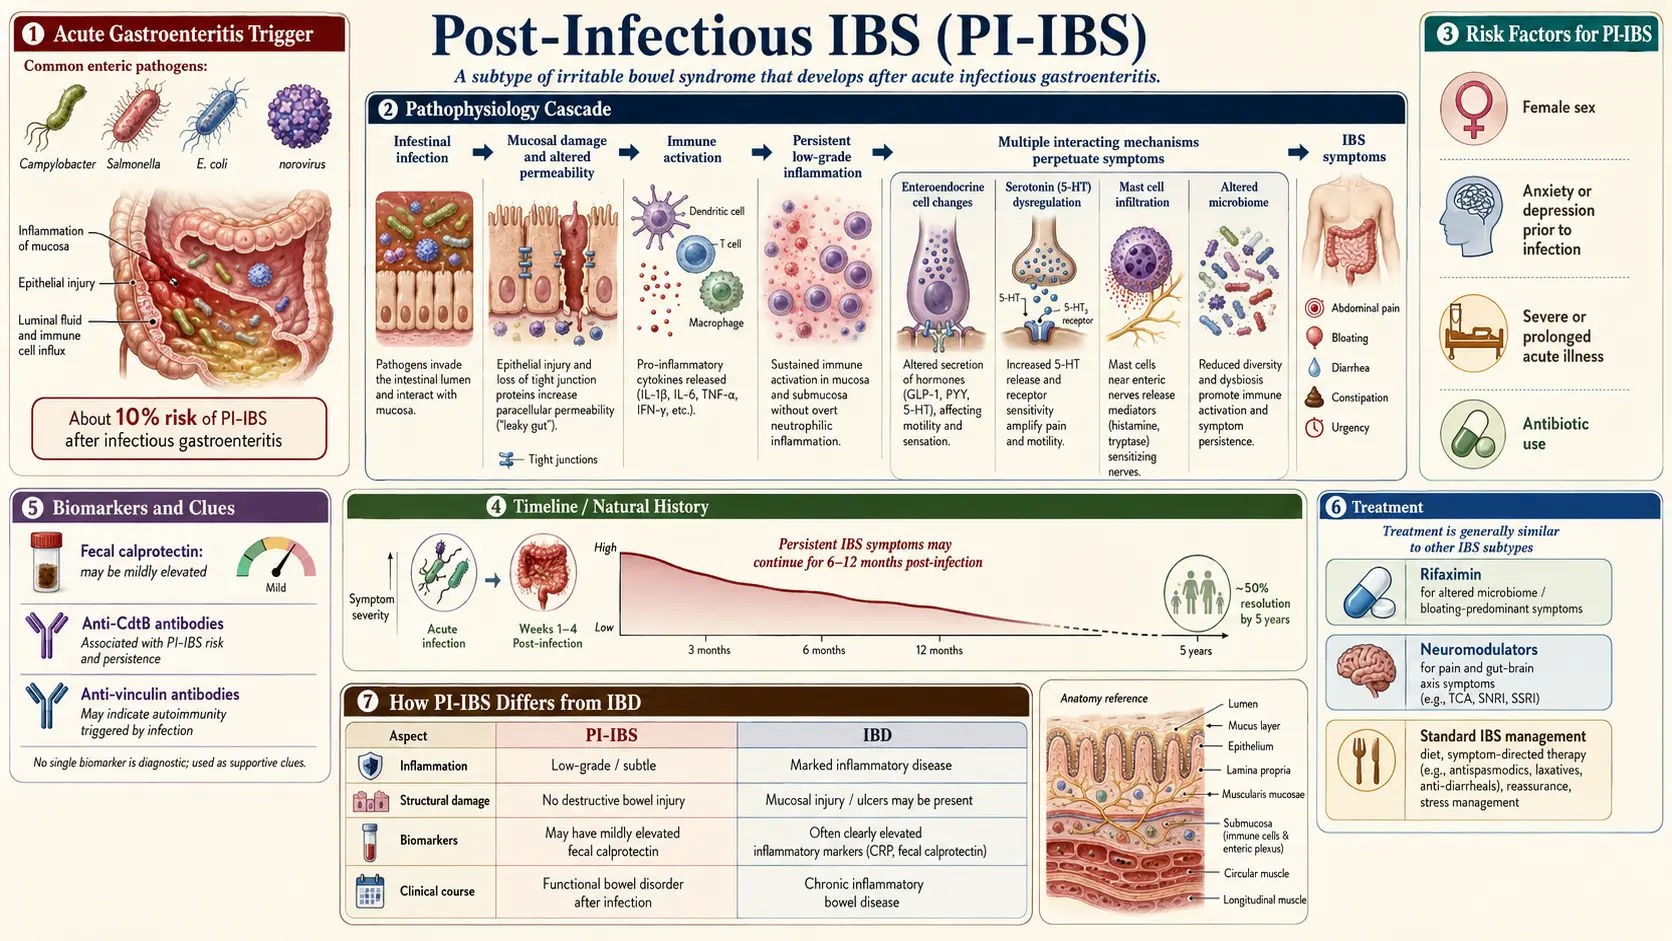
Table of Contents
- What Post-Infectious Irritable Bowel Syndrome Is
- The Numbers — How Common and Who Gets It
- The Walkerton Outbreak — The Definitive Study
- Risk Factors — Who Is Most Likely to Develop PI-IBS
- Which Pathogens Cause It
- Symptom Pattern — How PI-IBS Looks and Feels
- The CdtB – Vinculin Mechanism
- The Anti-CdtB and Anti-Vinculin Blood Test
- Travel History — The Missing Clue
- Post-Giardia Irritable Bowel Syndrome and the Bergen Outbreak
- Overlaps — Myalgic Encephalomyelitis/Chronic Fatigue Syndrome, Lyme, Alpha-Gal
- Treatment — What Actually Works
- Time Course — How Long It Lasts
- Key Research Papers
- Connections
- Featured Videos
What Post-Infectious Irritable Bowel Syndrome Is
Post-infectious IBS (PI-IBS) is irritable bowel syndrome that starts, to the day, after an episode of acute gastroenteritis — food poisoning, traveler's diarrhea, a bout with a parasite, or a waterborne outbreak. Before the infection you digested food normally. You had the "stomach flu" or that three-day nightmare on a Mexico beach, and the acute illness resolved — but the bathroom urgency, bloating, cramping, and unpredictable stools never quite went away. Six months later, a year later, you still do not trust a long car ride or a restaurant meal.
That is not a coincidence, and it is not "in your head." PI-IBS is now recognized as the best-understood subtype of irritable bowel syndrome, with a concrete triggering event, a proposed biological mechanism, and a commercial blood test marketed for it (its limits are covered below). About one in ten people who get acute infectious gastroenteritis go on to develop chronic irritable bowel syndrome-type symptoms that meet Rome criteria at six to twelve months. For many of them, the infection was the single hinge between a normal gut and a decade of misery.
This article walks through what the condition is, who gets it, how it is thought to damage the gut, what the testing shows, and what has been tried against the otherwise long natural history. It is written for people whose irritable bowel syndrome (IBS) began after a specific illness they can still date.
The Numbers — How Common and Who Gets It
The headline statistic, replicated across dozens of cohorts and summarized in the Klem et al. 2017 meta-analysis of more than 21,000 patients: roughly 10% of people who suffer acute infectious gastroenteritis have irritable bowel syndrome at 12 months (10.1%), and 14.5% more than 12 months afterward. The risk was 4.2 times that of people who had no infection within the first 12 months (95% confidence interval 3.1–5.7) and 2.3 times beyond 12 months (1.8–3.0). An earlier pooled analysis put the odds at 5.86 times (Thabane et al., 2007). Background rates vary with the definition: Walkerton's controls had 10.1%.
The germ and the person both change the figure. In Klem's analysis, 41.9% of people whose enteritis was caused by protozoa or parasites developed irritable bowel syndrome, against 13.8% after bacterial infection. Risk was also higher in women (odds ratio 2.2) and with antibiotic exposure (1.7), anxiety (2), depression (1.5) and somatization, meaning physical symptoms driven by distress (4.1). The authors note considerable differences among the studies.
Definitions change the count as well. In a Minnesota group with laboratory-confirmed Campylobacter, 17% met the stricter Rome IV criteria at 6–9 months, and adding the older Rome III pain frequency brought the count to 30%. Only 31% of those contacted answered the survey (Breen-Lyles et al., 2023).
Put differently: walk into any gastroenterology clinic and ask new irritable bowel syndrome patients when their symptoms started. Between 6% and 17% will name a specific episode of gastroenteritis as the onset — often a memorable one like a food-poisoning outbreak, a cruise-ship norovirus, or a foreign trip. PI-IBS is not a rare curiosity. It is one of the most common mechanisms by which people enter chronic irritable bowel syndrome.
The Walkerton Outbreak — The Definitive Study
In May 2000, the municipal water supply of Walkerton, Ontario — a town of about 5,000 people — was contaminated with E. coli O157:H7 and Campylobacter jejuni after heavy rains washed livestock runoff into a shallow well. Roughly 2,300 residents became acutely ill; seven died. Because the exposed population was an entire town with known medical records, the outbreak became a natural experiment in what happens after acute bacterial gastroenteritis.
John Marshall and colleagues at McMaster University followed the Walkerton cohort for eight years. Their 2006 paper, published in Gastroenterology, reported that 36.2% of Walkerton residents with clinically suspected acute gastroenteritis (168 of 464) met irritable bowel syndrome criteria about two years after the outbreak, against 10.1% of unexposed controls. Their 2010 paper, published in Gut, reported prevalence falling from 28.3% at two to three years to 15.4% at eight years among those who had been ill, still about three times the odds of controls (odds ratio 3.12), and many more had subclinical symptoms. Independent risk factors at eight years were female gender, younger age, prior anxiety or depression, and fever or weight loss during the acute illness.
Walkerton, together with Robin Spiller's UK bacterial-gastroenteritis cohort (a 2002 follow-up in Gut of 192 people over six years, with 14 post-infective cases, of whom 6 had recovered; Neal et al., 2002), established beyond reasonable doubt that acute enteric infection is a causal trigger for a substantial fraction of chronic irritable bowel syndrome. These are not "stressed people who happened to have food poisoning." The gut itself was changed by the infection.
Risk Factors — Who Is Most Likely to Develop PI-IBS
Not everyone who gets gastroenteritis ends up with PI-IBS. The risk varies with the person and with what happened during the acute illness. Consistent predictors across multiple cohorts:
- Female sex. Women are roughly twice as likely as men to develop PI-IBS after the same infection. Hormonal modulation of pain processing and gut motility is the leading suspect.
- Younger age at infection. People under 60 develop PI-IBS at much higher rates than older adults, possibly because aging gut mucosa mounts a less vigorous antibody response.
- Severity of the acute illness. Longer diarrhea (greater than seven days), fever, bloody stools, and weight loss during the acute infection each roughly double the PI-IBS risk.
- Psychological distress at the time of infection. Anxiety, depression, or high life stress in the month around the acute illness is a replicated risk factor. This does not mean irritable bowel syndrome is "psychological" — it means a stressed nervous system permits central sensitization to lock in after the gut injury.
- Antibiotic use during or after the infection. Paradoxically, antibiotics given for the gastroenteritis (or any antibiotic given in the surrounding months) increase PI-IBS risk, likely by flattening the protective microbiome and allowing dysbiosis to take hold.
- Bacterial rather than viral pathogens. Bacterial infections carry a higher PI-IBS risk than viral ones. Viral gastroenteritis (norovirus, rotavirus) produces PI-IBS at meaningfully lower rates, though not zero. Protozoal infections (Giardia) are among the strongest triggers of all.
Which Pathogens Cause It
The culprits are the usual enteric infection suspects, ranked roughly by PI-IBS risk in the literature:
- Campylobacter jejuni — the single most-studied trigger. Causes about 10–15% PI-IBS at one year.
- Shigella — high PI-IBS rates, especially in travel-associated infections.
- Salmonella — the canonical "food poisoning" bacterium; solid PI-IBS association.
- Shiga-toxin-producing E. coli — includes O157:H7, which with Campylobacter jejuni was a Walkerton pathogen.
- Enterotoxigenic E. coli (ETEC) — a common organism behind traveler's diarrhea.
- Clostridioides difficile — a review of 15 studies and 1,218 patients put irritable bowel syndrome after this infection at 21.1% (8.2–35.7%), mostly diarrhea-predominant (46.3%) and mixed (33.3%), and noted publication bias (Saha et al., 2022).
- Giardia lamblia — protozoal, not bacterial; produces some of the highest PI-IBS rates on record (see the Bergen outbreak below).
- Norovirus and viral gastroenteritis — lower risk, roughly 4–5% PI-IBS, but not negligible given how common norovirus is.
- COVID-19 — a 2023 analysis of 10 studies and 2,763 patients found 12% had irritable bowel syndrome afterward. In three prospective studies the odds were 12.92 times those of controls, with wide uncertainty (3.58–46.60) (Marasco et al., 2023).
Symptom Pattern — How PI-IBS Looks and Feels
PI-IBS tends to look different from the constipation-predominant irritable bowel syndrome that runs in families or appears gradually in adolescence. The typical PI-IBS patient describes:
- Diarrhea-predominant or mixed-type irritable bowel syndrome — rarely pure constipation.
- Urgency. The sudden, drop-everything need to find a bathroom, often within minutes of eating. Many patients map every gas station between home and work.
- Bloating and visible distension. A flat morning belly that balloons through the day.
- Post-prandial cramping — pain or griping within 30–60 minutes of a meal, partially relieved by a bowel movement.
- Food intolerances that were not there before. Dairy, gluten, onions, and high-FODMAP foods suddenly become triggers. Practitioners usually attribute this to an overlap with small intestinal bacterial overgrowth (see the sibling irritable bowel syndrome & small intestinal bacterial overgrowth (SIBO) overlap and low-FODMAP diet articles).
- A clearly remembered start date. Patients with PI-IBS can usually say "before the Mexico trip in 2019 I was fine" with certainty. Non-PI irritable bowel syndrome patients usually cannot.
The CdtB – Vinculin Mechanism
For thirty years, the stumbling block in PI-IBS research was the mechanism. The infection is long gone. Stool cultures are negative. Biopsies look almost normal. So what, precisely, is broken?
In a series of papers culminating in 2015, Mark Pimentel and colleagues at Cedars-Sinai proposed a mechanism. Most invasive enteric bacteria (Campylobacter, Salmonella, Shigella, E. coli, several others) secrete a toxin called cytolethal distending toxin, subunit B (CdtB). CdtB damages host DNA and, crucially, triggers a durable antibody response. Your immune system makes anti-CdtB antibodies to clear the infection — and those antibodies often stick around for years after the bacteria are gone.
According to this work, a portion of CdtB is a molecular mimic for a human protein called vinculin. Vinculin is a cell-adhesion protein expressed densely in the gut's neural infrastructure — specifically in the interstitial cells of Cajal (ICC), the pacemaker cells that generate the small intestine's migrating motor complex (MMC). The MMC is the "housekeeping wave" that sweeps bacteria and debris from the small bowel into the colon between meals, roughly every 90 to 120 minutes, and it is what keeps the small intestine normally near-sterile.
The proposed chain comes from a post-infectious animal model, in which antibodies to CdtB cross-react with vinculin in the gut and produce an irritable-bowel-like picture (Pimentel et al., 2015). Human data are thinner: in stomach tissue from 45 stomach-cancer patients, higher anti-vinculin antibody went with fewer interstitial cells of Cajal, which is an association only (Kim et al., 2020). In the hypothesis, antibodies attack the interstitial cells of Cajal. ICC density drops. The MMC weakens or disappears. Small-intestinal contents stop being swept downstream. Bacteria migrate up from the colon and colonize the small bowel — the textbook setup for small intestinal bacterial overgrowth (SIBO). Fermentation of food in the small bowel produces the bloating, urgency, and post-prandial distress that defines PI-IBS.
Supporters of this hypothesis read the overlap of PI-IBS, small intestinal bacterial overgrowth, and diarrhea-predominant irritable bowel syndrome as stages of one disease. That has not been shown in people.
The Anti-CdtB and Anti-Vinculin Blood Test
The CdtB – vinculin work produced a commercial blood test for irritable bowel syndrome. It measures two immunoglobulin G (IgG) antibody levels:
- Anti-CdtB — proposed as a sign of prior invasive bacterial gastroenteritis.
- Anti-vinculin — proposed as a sign of the cross-reaction described above.
A result is considered strongly positive when both antibodies are elevated. The validation study tested diarrhea-predominant irritable bowel syndrome in general, not PI-IBS, against inflammatory bowel disease, celiac disease and healthy people, with no constipation group. Anti-CdtB had specificity of 91.6% and sensitivity of 43.7%; anti-vinculin had specificity of 83.8% and sensitivity of 32.6%. Both were less specific against celiac disease (Pimentel et al., 2015). Sensitivity is low, so a negative does not rule PI-IBS out. Independent groups have not all reproduced this: an Australian study "did not confirm" that the antibodies separate irritable bowel syndrome with diarrhea from organic gut disease (Talley et al., 2019), and a Norwegian study found no anti-CdtB difference after Giardia infection (Hanevik et al., 2022).
Practitioners who use the test report three things. It gives patients a concrete, biological explanation (huge psychologically, after years of being told "it's just irritable bowel syndrome"). They report that it predicts small intestinal bacterial overgrowth susceptibility, on the idea that vinculin damage permits overgrowth to recur. And they report that it predicts response to rifaximin, the non-absorbed antibiotic used for small intestinal bacterial overgrowth — describing double-positive patients who respond well and relapse every few months, the pattern they would expect from lasting ICC damage.
The test costs around $150–$250 and is rarely covered by insurance.
Travel History — The Missing Clue
Practitioners in this area call one question the most undervalued in an irritable bowel syndrome workup: where was the person, and what happened, in the weeks before the symptoms began?
Patients who spent a week in Bali, Mexico, India, or Southeast Asia in 2018, 2019, or 2021 and came home with Bali belly, Montezuma's revenge, or Delhi belly are often still carrying the symptoms years later without connecting the dots. The acute illness felt like a bad week and then resolved. The chronic bathroom problem that started right afterward felt like a separate issue. In PI-IBS it is not.
Travel-associated enterotoxigenic E. coli, Campylobacter, and Shigella are among the most common triggers worldwide. The antibody test has not been studied by travel history, and its sensitivity in diarrhea-predominant irritable bowel syndrome was 43.7% and 32.6%. The treatment pathway clinicians describe is rifaximin, prokinetics and low-FODMAP (see rifaximin protocol).
Post-Giardia Irritable Bowel Syndrome and the Bergen Outbreak
In autumn 2004, the municipal water supply of Bergen, Norway — a city of about 250,000 — was contaminated with Giardia lamblia. Roughly 1,300 confirmed cases (and thousands of likely unreported ones) developed acute giardiasis. Norwegian researchers, led by Kurt Hanevik and colleagues, followed the cohort for more than a decade.
The results were striking. At three years, 46% of the Giardia-exposed group met criteria for irritable bowel syndrome, compared with 14% of controls. At six years the irritable bowel syndrome rate was still about 40% (39.4%; Hanevik et al., 2014). At ten years it was 43% against 14% of controls (adjusted odds ratio 4.74), not significantly changed from six years (Litleskare et al., 2018). Post-Giardia irritable bowel syndrome also carries a high rate of co-occurring chronic fatigue — 26% against 11% of controls at ten years, down from 31% at six — a pattern that sits at the boundary of PI-IBS and myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS). A 2022 antibody study in people who developed these conditions after Giardia infection found no anti-CdtB difference from healthy controls, so the toxin-antibody account has not been shown for this parasite (Hanevik et al., 2022).
The practical implication practitioners draw: when irritable bowel syndrome started after drinking from a stream, using untreated well water, traveling in areas where Giardia is endemic, or eating contaminated food, they order a stool polymerase chain reaction (PCR) panel looking specifically for Giardia, Cryptosporidium, and Blastocystis, even years out. They report that tinidazole or nitazoxanide occasionally clears a low-grade persistent infection and resolves symptoms.
Overlaps — Myalgic Encephalomyelitis/Chronic Fatigue Syndrome, Lyme, Alpha-Gal
PI-IBS sits inside a broader family of post-infectious chronic illnesses. The patterns overlap, and many patients have more than one label.
Myalgic encephalomyelitis/chronic fatigue syndrome (ME/CFS). A substantial fraction of myalgic encephalomyelitis/chronic fatigue syndrome patients can date their illness to a specific infection — Epstein-Barr, enterovirus, Giardia, or another gut pathogen. Gut symptoms are common in myalgic encephalomyelitis/chronic fatigue syndrome and often meet irritable bowel syndrome criteria. The Bergen post-Giardia cohort was notable for exactly this overlap. See the Chronic Fatigue Syndrome overview and the Post-Viral Triggers deep dive.
Lyme disease. Tick-borne Borrelia infection produces gastrointestinal symptoms in roughly a quarter of acute cases, and chronic or post-treatment Lyme syndrome frequently includes irritable bowel syndrome-pattern bowel complaints. If you live in an endemic region and your irritable bowel syndrome began after a summer of tick exposure or an unexplained febrile illness, see Lyme Disease.
Alpha-Gal syndrome. A tick-induced immunoglobulin E (IgE) antibody to the sugar galactose-alpha-1,3-galactose produces delayed reactions to mammalian meat — often with urgent diarrhea, cramping, and urgency three to six hours after eating. It mimics diarrhea-predominant irritable bowel syndrome perfectly and is routinely missed. If your symptoms cluster after red-meat meals, see Alpha-Gal Syndrome.
Treatment — What Actually Works
PI-IBS is one of the few irritable bowel syndrome subtypes with a mechanistically targeted treatment plan. In rough order of evidence:
Rifaximin. A non-absorbed antibiotic that sits in the small bowel and reduces bacterial overgrowth. Two trials, TARGET 1 and TARGET 2, tested a single 2-week course in irritable bowel syndrome without constipation: 40.7% had adequate relief of global symptoms against 31.7% on placebo (Pimentel et al., 2011). TARGET 3 tested repeat treatment in diarrhea-predominant irritable bowel syndrome: 1,074 people (44.1%) responded to open-label rifaximin, and 692 of them (64.4%) relapsed. On a repeat course, 38.1% responded against 31.5% on placebo; abdominal pain responded in 50.6% against 42.2%, while stool consistency did not differ (51.8% against 50.0%) (Lembo et al., 2016). These trials did not select people for post-infectious onset. Practitioners report that patients positive on both antibodies respond especially well. See the sibling rifaximin protocol for full dosing.
Prokinetics. On the view that the core injury in PI-IBS is impaired MMC function, clinicians who focus on small intestinal bacterial overgrowth report that drugs that stimulate the MMC between meals reduce relapse. They use low-dose naltrexone (2.5–4.5 mg at bedtime), prucalopride, and off-label low-dose erythromycin to stretch the interval between rifaximin courses.
Low-FODMAP diet. A short-term elimination of fermentable carbohydrates lowers gas production and symptom severity while the underlying biology is addressed. It is not a forever diet — long-term FODMAP restriction starves beneficial microbes. See the sibling low-FODMAP diet article for the three-phase protocol.
Low-dose naltrexone. Beyond its prokinetic role, practitioners report that low-dose naltrexone modulates the low-grade gut inflammation and visceral hypersensitivity that persist after enteric infection. They describe the dose as small, the cost low and side effects minimal, and point to case series and small trials in irritable bowel syndrome and Crohn's.
Glutamine. A randomized placebo-controlled trial in people with diarrhea-predominant irritable bowel syndrome and a leaky gut after an enteric infection gave glutamine 5 g three times a day for 8 weeks. A drop of 50 points or more in the symptom score occurred in 43 of 54 (79.6%) against 3 of 52 (5.8%) on placebo, with no serious adverse events. It is one trial, and the authors ask for larger ones (Zhou et al., 2019).
Gut-directed hypnotherapy. PI-IBS installs a layer of central sensitization — the spinal cord and brain amplify pain signals from a gut that has already healed. Gut-directed hypnotherapy (Manchester protocol, smartphone app, or in-person) is one of the few interventions with randomized-trial evidence in irritable bowel syndrome. In randomized trials, 40.8% responded to individual and 33.2% to group sessions against 16.7% of controls at 3 months (Flik et al., 2019), and in a 2026 trial 48% in person and 33% by smartphone against 22% on psychoeducation (Snijkers et al., 2026). An uncontrolled clinic series of 204 people rating themselves reported 71% initially responding, with benefits lasting at least five years (Gonsalkorale et al., 2003). None of these selected people for post-infectious onset. It is not "it's all in your head" — it is rewiring the pain-processing circuitry that the infection helped recruit.
Other causes looked for. A stool polymerase chain reaction panel for Giardia, Blastocystis, and Dientamoeba, plus bile-acid testing in diarrhea-predominant irritable bowel syndrome, plus (when indicated) a glucose or lactulose breath test for small intestinal bacterial overgrowth, completes the workup practitioners describe.
Time Course — How Long It Lasts
Untreated, the natural history of PI-IBS is slow. In Walkerton, prevalence fell from 28.3% at two to three years to 15.4% at eight years (Marshall et al., 2010). In Spiller's UK cohort, fewer than half had recovered by six years (Neal et al., 2002). The Bergen post-Giardia cohort has an even longer tail: 40% at six years and 43% at ten (Litleskare et al., 2018).
Practitioners report that treatment shortens this timeline. They describe patients who combine rifaximin, a prokinetic, a temporary low-FODMAP phase, and gut-directed hypnotherapy reporting major improvement within three to six months. Relapses happen, and they describe a relapse-and-retreat cycle that keeps people functional.
Recognizing the pattern is the step these practitioners stress most. An irritable bowel syndrome workup that stops at "we think it's irritable bowel syndrome, try fiber" can mean a decade of suffering. An irritable bowel syndrome workup that asks "when did this start, and what happened?" opens the door to a treatable disease.
Key Research Papers
- Marshall JK, et al. Eight year prognosis of postinfectious irritable bowel syndrome following waterborne bacterial dysentery. Gut. 2010;59(5):605–611. — PubMed PMID: 20427395
- Marshall JK, et al. Incidence and epidemiology of irritable bowel syndrome after a large waterborne outbreak of bacterial dysentery. Gastroenterology. 2006;131(2):445–450. — PubMed PMID: 16890598
- Neal KR, et al. Prognosis in post-infective irritable bowel syndrome: a six year follow up study. Gut. 2002;51(3):410–413. — PubMed PMID: 12171965
- Spiller R, Garsed K. Postinfectious irritable bowel syndrome. Gastroenterology. 2009;136(6):1979–1988. — doi:10.1053/j.gastro.2009.02.074
- Pimentel M, et al. Development and validation of a biomarker for diarrhea-predominant irritable bowel syndrome in human subjects. PLoS ONE. 2015;10(5):e0126438. — doi:10.1371/journal.pone.0126438
- Klem F, et al. Prevalence, risk factors, and outcomes of irritable bowel syndrome after infectious enteritis: a systematic review and meta-analysis. Gastroenterology. 2017. — doi:10.1053/j.gastro.2016.12.039
- Thabane M, et al. Systematic review and meta-analysis: The incidence and prognosis of post-infectious irritable bowel syndrome. Aliment Pharmacol Ther. 2007;26(4):535–544. — PubMed PMID: 17661757
- Breen-Lyles M, et al. Impact of Rome IV criteria on the prevalence of post-infection irritable bowel syndrome. Neurogastroenterol Motil. 2023;35(5):e14532. — PubMed PMID: 36633303
- Saha S, et al. Postinfection Irritable Bowel Syndrome Following Clostridioides difficile Infection: A Systematic-review and Meta-analysis. J Clin Gastroenterol. 2022;56(2):e84–e93. — PubMed PMID: 34049374
- Marasco G, et al. Meta-analysis: Post-COVID-19 functional dyspepsia and irritable bowel syndrome. Aliment Pharmacol Ther. 2023;58(1):6–15. — PubMed PMID: 37038318
- Kim JH, et al. Association between interstitial cells of Cajal and anti-vinculin antibody in human stomach. Korean J Physiol Pharmacol. 2020;24(2):185–191. — PubMed PMID: 32140042
- Talley NJ, et al. Circulating Anti-cytolethal Distending Toxin B and Anti-vinculin Antibodies as Biomarkers in Community and Healthcare Populations With Functional Dyspepsia and Irritable Bowel Syndrome. Clin Transl Gastroenterol. 2019;10(7):e00064. — PubMed PMID: 31356481
- Hanevik K, et al. No difference in serum levels of B-cell activating receptor and antibodies against cytolethal distending toxin B and flagellin in post-infectious irritable bowel syndrome and chronic fatigue syndrome after Giardia infection. JGH Open. 2022;6(3):185–188. — PubMed PMID: 35355666
- Hanevik K, et al. Irritable bowel syndrome and chronic fatigue 6 years after giardia infection: a controlled prospective cohort study. Clin Infect Dis. 2014;59(10):1394–1400. — PubMed PMID: 25115874
- Litleskare S, et al. Prevalence of Irritable Bowel Syndrome and Chronic Fatigue 10 Years After Giardia Infection. Clin Gastroenterol Hepatol. 2018;16(7):1064–1072. — PubMed PMID: 29378314
- Pimentel M, et al. Rifaximin therapy for patients with irritable bowel syndrome without constipation. N Engl J Med. 2011;364(1):22–32. — PubMed PMID: 21208106
- Lembo A, et al. Repeat Treatment With Rifaximin Is Safe and Effective in Patients With Diarrhea-Predominant Irritable Bowel Syndrome. Gastroenterology. 2016;151(6):1113–1121. — PubMed PMID: 27528177
- Zhou Q, et al. Randomised placebo-controlled trial of dietary glutamine supplements for postinfectious irritable bowel syndrome. Gut. 2019;68(6):996–1002. — PubMed PMID: 30108163
- Flik CE, et al. Efficacy of individual and group hypnotherapy in irritable bowel syndrome (IMAGINE): a multicentre randomised controlled trial. Lancet Gastroenterol Hepatol. 2019;4(1):20–31. — PubMed PMID: 30473202
- Snijkers JTW, et al. In-person therapist-delivered hypnotherapy versus smartphone-based self-guided hypnotherapy in IBS: a multicentre three-armed randomised controlled trial. Gut. 2026. — PubMed PMID: 42502003
- Gonsalkorale WM, et al. Long term benefits of hypnotherapy for irritable bowel syndrome. Gut. 2003;52(11):1623–1629. — PubMed PMID: 14570733
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on post-infectious irritable bowel syndrome biology, biomarkers, and management:
- PubMed: Post-infectious irritable bowel syndrome
- PubMed: Walkerton outbreak and long-term IBS
- PubMed: Anti-CdtB and anti-vinculin antibodies in IBS
- PubMed: Campylobacter and post-infectious IBS
- PubMed: Post-Giardia IBS and the Bergen cohort
- PubMed: Interstitial cells of Cajal, MMC, and SIBO
- PubMed: Rifaximin for IBS-D (TARGET 3)
- PubMed: Low-dose naltrexone in functional bowel disease
- PubMed: Gut-directed hypnotherapy for IBS
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Irritable Bowel Syndrome
- Post-Viral Triggers
- Alpha-Gal Syndrome
- Lyme Disease
- Chronic Fatigue Syndrome
- Irritable Bowel Syndrome and Small Intestinal Bacterial Overgrowth Overlap
- Small Intestinal Bacterial Overgrowth
- Low-FODMAP Diet for Irritable Bowel Syndrome
- Visceral Hypersensitivity and Brain-Gut Axis
- Gut-Directed Hypnotherapy and Cognitive Behavioral Therapy
- Irritable Bowel Syndrome Medications Guide
- Peppermint, Probiotics, and Herbals
- Rome IV Subtypes
- Anxiety
- Gut-Brain Axis
- Bloating
- Inflammatory Bowel Disease
- Breath Test Guide
- Infectious Disease