⚠ Evidence warning: Clinical trials or other evidence do not support the claims that pelvic physical therapy is the single most effective and first-line treatment, that duloxetine is often effective for pelvic pain, and that low-dose naltrexone has growing evidence behind it. This page keeps it as a report of what people, websites or other media say.
Pelvic Floor Therapy and Central Sensitization in Endometriosis
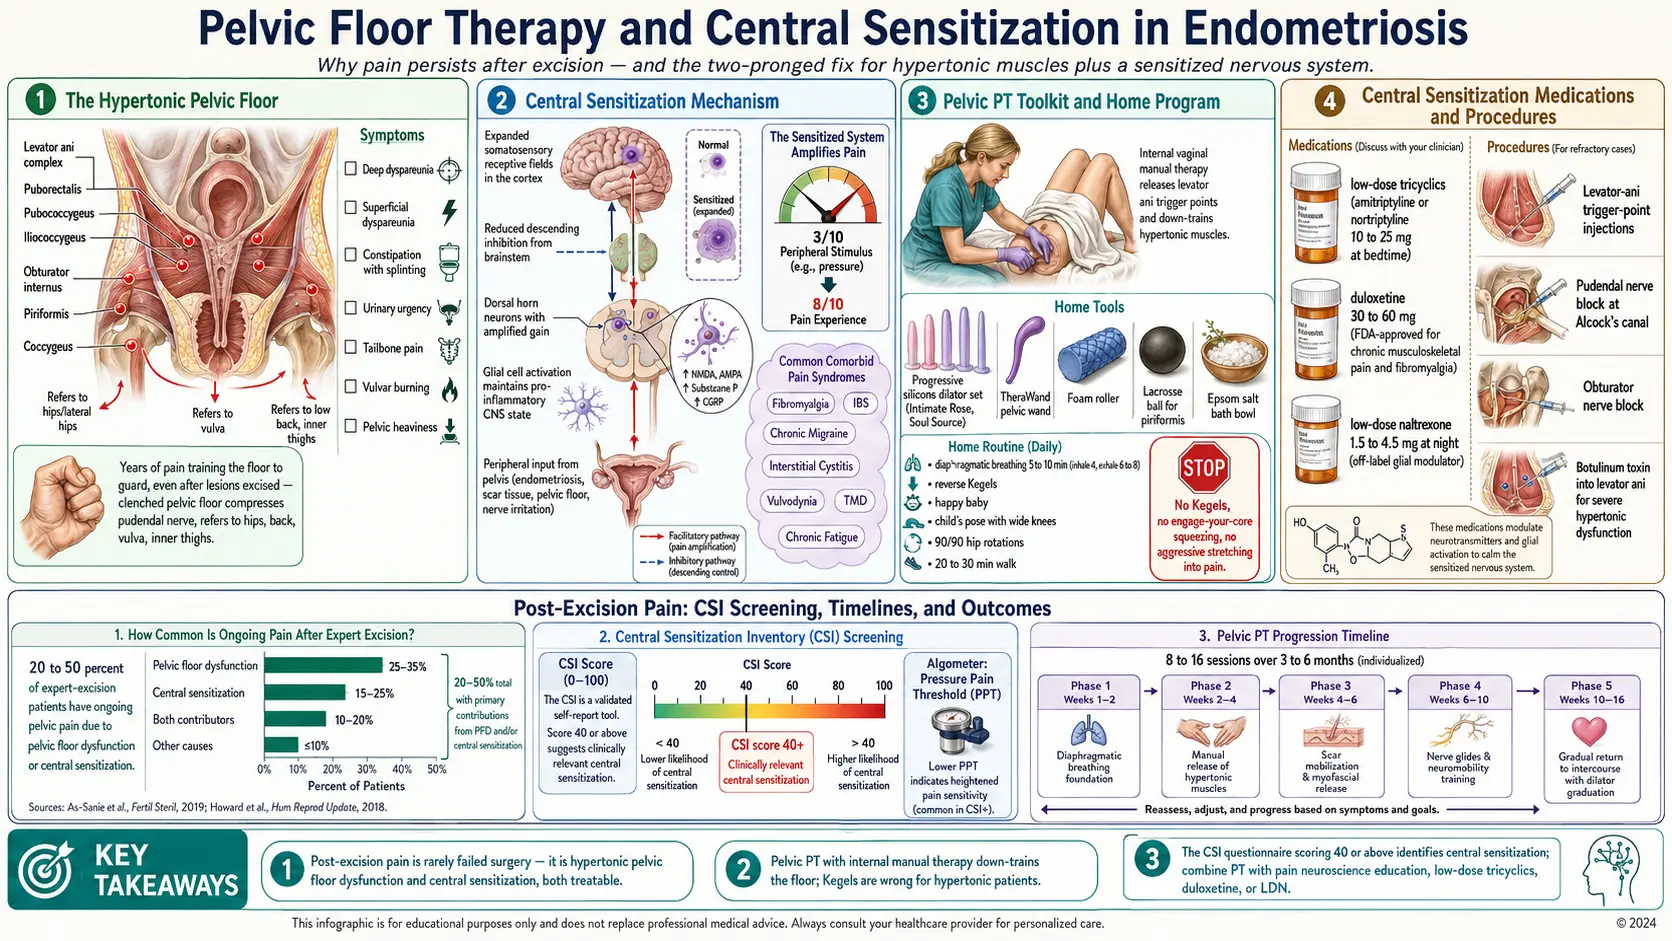
Table of Contents
- The Post-Excision Disappointment
- Two Overlapping Drivers
- Pelvic Floor Dysfunction — What It Is
- Symptoms of a Hypertonic Pelvic Floor
- Central Sensitization — What It Is
- Screening — Central Sensitization Inventory and Pressure Pain Thresholds
- Pelvic Physical Therapy — What It Actually Is
- Finding a Qualified Pelvic Physical Therapist
- What the First Session Looks Like
- Manual Techniques
- Home Tools
- Home Exercises
- What Pelvic Therapists Caution Against
- Central Sensitization Management
- Nerve Blocks and Trigger Point Injections
- Timeline Expectations
- When to Escalate
- Key Research Papers
- Connections
- Featured Videos
The Post-Excision Disappointment
You spent years convincing doctors your pain was real. You finally found a skilled excision surgeon, recovered from laparoscopy, and expected the curtain to lift. Then, somewhere between weeks six and twelve post-op, you realized the pain was still there. The crushing period pain may be genuinely gone — but the deep dyspareunia, the burning in your lower pelvis, the ache behind the pubic bone, the feeling of a clenched fist inside you: those survived the surgery.
If that is where you are, you are not broken and your surgery did not "fail." Roughly 20–50% of patients who undergo expert excision have meaningful ongoing pelvic pain afterward. The lesions are gone, the pathology report is clean, and yet the symptoms continue. This is not a sign the disease was missed or the surgeon was incompetent. It is a sign endometriosis does something cutting out tissue cannot reverse — it trains the muscles of your pelvis and the wiring of your nervous system to generate pain on their own.
A placebo-surgery trial shows both sides of this. Among 39 women with endometriosis, 16 of 20 (80%) improved after excision against 6 of 19 (32%) after diagnostic surgery alone at 6 months. The authors report a placebo response of about 30%, and about 20% of women did not report improvement after surgery (Abbott 2004).
Two mechanisms produce this residual pain, and both are treatable.
Two Overlapping Drivers
Post-excision pelvic pain is almost never one thing. The two engines that keep it running are pelvic floor dysfunction — chronic involuntary tightening of the muscles of your pelvis — and central sensitization, a rewiring of the brain and spinal cord that amplifies incoming signals. The two feed each other. Tight muscles send a low-level pain signal upstream, which trains the central nervous system (CNS) to expect pain. The sensitized central nervous system then interprets ordinary sensations — a tampon, a bowel movement, a full bladder, intercourse — as painful, which triggers reflexive guarding, which tightens the floor further.
Cutting out lesions does not break this loop on its own. Practitioners describe interrupting it at both ends: muscle and nerve, body and brain.
Pelvic Floor Dysfunction — What It Is
Your pelvic floor is a hammock of muscles slung between the pubic bone and the tailbone. The main layers are the levator ani complex (puborectalis, pubococcygeus, iliococcygeus), the obturator internus along the inner hip, the piriformis deep in the buttock, and the coccygeus near the tailbone. They support the bladder, uterus, and rectum, close the urethra and anus, and reflexively guard whenever something hurts in the abdomen or pelvis.
That reflexive guarding is the problem. Every flare, every painful period, every painful bowel movement, every painful attempt at intercourse tells your pelvic floor to clench. Multiply that by years — often decades, because endometriosis is diagnosed on average seven to ten years late — and the muscles forget how to let go. What started as a protective response becomes hypertonic pelvic floor dysfunction: a floor stuck in the "on" position, even after the lesions are gone.
Hypertonic floors do not just ache. They compress nerves (the pudendal nerve runs directly through the floor), trap blood flow, pull on the pubic symphysis, and refer pain out to the hips, low back, tailbone, vulva, and inner thighs. Many patients describe it as "a clenched fist I can't unclench."
Symptoms of a Hypertonic Pelvic Floor
A hypertonic pelvic floor has a recognizable fingerprint. You may have some or all of:
- Deep dyspareunia — pain with deep penetration during intercourse, often described as "hitting a wall" or "running into something bruised."
- Superficial dyspareunia — burning or tearing at the vaginal opening with initial penetration.
- Constipation and painful bowel movements, a feeling of incomplete emptying, or the need to "splint" with a hand on the perineum.
- Urinary urgency, frequency, or hesitancy — the sensation of needing to go without being able to start, or feeling like you never fully empty.
- Tailbone (coccyx) pain, especially sitting on hard surfaces.
- Hip pain, groin pain, low back pain that moves and never quite localizes.
- Burning vulvar pain or generalized vestibule tenderness.
- Pain with tampon insertion, pelvic exams, or cervical cancer screening.
- A baseline feeling of heaviness, pressure, or fullness in the pelvis that does not correlate with your cycle.
If you recognized more than three of those, the floor is almost certainly part of what is still hurting.
Central Sensitization — What It Is
Central sensitization is what happens when your nervous system turns up the gain on pain. Under normal conditions, a 3/10 stimulus produces a 3/10 signal. In a sensitized system, the dorsal horn of the spinal cord amplifies that same signal so it arrives at the brain as an 8/10. The threshold for pain drops, pain lingers longer after a stimulus ends, and sensations that should not hurt — light touch, warm water, clothing pressure — begin to.
The mechanism is real biology, not imagination or weakness. Repeated nociceptive input produces measurable changes: increased excitability of spinal cord neurons, decreased descending inhibition from the brainstem, expansion of receptive fields in the somatosensory cortex, and glial cell activation that maintains a pro-inflammatory state in the central nervous system. These changes outlive the original tissue injury — which is why patients who had endometriosis excised cleanly can still hurt for months or years afterward.
Central sensitization also explains why endometriosis travels with a cluster of comorbid pain syndromes: fibromyalgia, irritable bowel syndrome (IBS), chronic migraine, interstitial cystitis, vulvodynia, temporomandibular disorder, chronic fatigue. They share the same amplification mechanism. If you have endometriosis plus two or three of those, you almost certainly have central sensitization on top of whatever peripheral pathology remains.
Screening — Central Sensitization Inventory and Pressure Pain Thresholds
There is a validated self-administered questionnaire for this called the Central Sensitization Inventory (CSI). It has 25 items scored 0–4. A total score of 40 or above suggests clinically relevant central sensitization. It is free, takes five minutes, and is available through most pain-management clinics or online, and a clinician can read the completed form at an appointment. In the study that set the cut-off, a score of 40 picked out 81% of people with central sensitivity syndromes and correctly cleared 75% of a comparison group. The inventory is a screening tool, not a diagnosis (Neblett 2013).
Scores may also predict how hormone treatment goes. In a study of 114 women with endometriosis, 40.4% scored 40 or above on the inventory. After 6 months of hormone treatment, those women had higher odds of less than a 30% fall in pain for chronic pelvic pain (odds ratio 3.058), deep pain with sex (4.098) and painful bowel movements (4.545). This was an observational study at one center (Raimondo 2026).
A trained pelvic physical therapist or pain physician can also measure pressure pain thresholds with a handheld algometer at standardized body points. Lowered thresholds at sites far from the pelvis (the forearm, the shin) — not just at the pelvic floor itself — indicate that the amplification is central, not local.
Pelvic Physical Therapy — What It Actually Is
"Pelvic physical therapy" sounds like it might mean Kegels in a gym. It is nothing like that. Pelvic physical therapy is a subspecialty practiced by clinicians with advanced post-graduate training in pelvic anatomy, internal manual techniques, and pain science. A qualified pelvic physical therapist treats you with external hands-on work (hips, abdomen, diaphragm, low back) plus internal vaginal work — and in some cases internal rectal work — to reach the floor directly.
If that sounds intense, it is. It is also the single most effective intervention for hypertonic pelvic floor dysfunction. For endometriosis patients with ongoing pain, pelvic physical therapy is not optional adjunct therapy — it is first-line treatment.
What trials show so far is modest. In a small randomized trial of women with deep endometriosis, 30 completed the study: 17 who had five physiotherapy sessions and 13 with no intervention. Urinary, bowel and sexual function did not differ significantly between the groups, while the authors report improvement in superficial pain with sex, chronic pelvic pain and muscle relaxation, with high treatment satisfaction (Del Forno 2023).
Finding a Qualified Pelvic Physical Therapist
Not every physical therapy clinic with a "pelvic health" banner on the website does this work in depth. These are the markers practitioners describe:
- Professional association directory. The American Physical Therapy Association maintains a searchable directory of members of its Academy of Pelvic Health Physical Therapy (
aptapelvichealth.org). - Post-graduate pelvic rehabilitation training. Private training institutes teach this work, and some keep practitioner directories searchable by zip code.
- Internal-release certified. Not every clinic performs internal vaginal manual therapy, and the treatment described on this page depends on it.
- Endometriosis experience. Clinics differ in how many endometriosis patients they see per week. A physical therapist who sees endometriosis patients weekly is described as thinking differently than one who sees incontinence and postpartum clients.
- Trauma-informed. A good pelvic physical therapist moves at your pace, explains every technique before performing it, and stops instantly when asked. Trauma-informed practice is a trained skill, not a marketing term.
What the First Session Looks Like
The first visit is usually 60–90 minutes and is mostly conversation and external assessment. An extensive intake covers medical, surgical, and menstrual history, bowel and bladder habits, sexual function, and pain map. The physical therapist watches you breathe, walk, and move. External palpation of the hips, abdomen, and low back comes next.
The internal exam — if you consent and are ready — happens at the end of the first visit or at the second. You are draped, knees up, and the physical therapist inserts one gloved, lubricated finger to assess tone, tenderness, and trigger points in each major pelvic floor muscle. It is not a gynecologic exam: no speculum, no cervical contact. You can stop at any point. Many patients report it is far less uncomfortable than a pap smear.
You will leave with a short home program — usually diaphragmatic breathing, a hip mobility drill, and one or two stretches. Session one is orientation, not heroics.
Manual Techniques
Once treatment begins, a rotating toolkit is typical:
- Myofascial release — sustained pressure on tight fascial bands along the abdomen, hip flexors, inner thighs, and superficial pelvic floor.
- Trigger point release — focused pressure on hyperirritable muscle knots, both external (obturator, piriformis) and internal (levator ani).
- Scar mobilization — massage across laparoscopy port sites. Scars that look fine on the surface can tether deeper fascia and refer pain for years.
- Visceral mobilization — gentle manipulation of the abdominal viscera to restore glide between the uterus, bladder, bowel, and peritoneum. Especially relevant for adhesion-prone endometriosis patients.
- Nerve glides — movements that gently slide the pudendal and obturator nerves through their sheaths, reducing entrapment pain.
Home Tools
Between sessions, the work continues at home with a small equipment list:
- Silicone dilators (progressive set of four to seven sizes). Practitioners describe 10–15 minutes daily with water-based lubricant, starting at the largest size that causes no pain.
- Pelvic wand — a curved silicone tool for trigger points out of finger reach.
- Foam roller for external work on hip flexors, glutes, and mid-back.
- Lacrosse ball for piriformis and obturator trigger points against a wall or floor.
- Epsom salt baths — people describe 20 minutes in warm water with 1–2 cups of Epsom salts, three to five evenings a week, and call heat and quiet nervous-system medicine.
Home Exercises
For a hypertonic floor, the goal of exercise is down-training — teaching the muscles to let go — not strengthening. A typical daily routine:
- Diaphragmatic breathing — the pelvic floor moves in sync with the diaphragm. On a deep belly breath, both descend and lengthen. Five to ten minutes of slow belly breathing (inhale 4, exhale 6–8) is the foundation of the entire program.
- Reverse Kegels — the intentional opposite of a Kegel. The floor is gently bulged or released downward, as if starting to urinate, paired with the exhale.
- Happy baby, child's pose (wide knees), butterfly stretch — passive openers for the pelvic outlet, with breathing into the pelvis for 2–3 minutes each.
- Hip mobility work — 90/90 hip rotations, pigeon, figure-four — to unload obturator and piriformis.
- Walking — 20–30 minutes daily at an easy pace. Down-regulates arousal and promotes pelvic blood flow without loading the floor.
What Pelvic Therapists Caution Against
Most generic "pelvic health" advice on the internet is written for the opposite problem — weak, leaking floors after childbirth — and pelvic therapists describe it as actively harmful for a hypertonic floor. They caution against:
- Kegels. They describe squeezing an already-clenched muscle as making it tighter, and reserve Kegels for people a qualified pelvic physical therapist has examined and prescribed them for.
- "Squeeze and hold" protocols — yoga, pilates, or fitness cues to "engage your core" or "lift your pelvic floor" continuously.
- Aggressive stretching that pushes into pain. The floor responds to pain with more guarding, so they describe staying at the edge of sensation, not past it.
- Heavy lifting and high-impact loading during active flares — until the floor has been retrained.
- Holding urine or stool past the urge. Chronic pushback trains the floor to stay contracted.
Central Sensitization Management
Pelvic physical therapy alone is often not enough when the nervous system has been amplifying pain for a decade or more. A parallel track targets the central piece directly:
- Pain neuroscience education. Understanding how pain actually works is, surprisingly, therapeutic. Pain researchers have written plain-language books on it, and free video talks cover the same material. Patients who grasp that pain is generated by the brain's interpretation of signals — not a direct readout of tissue damage — need less medication and report less disability.
- Graded exercise / graded exposure. Steady increases in activity below the flare threshold — for example, walking 20 minutes on a day when 40 would be possible — so the nervous system relearns that movement is safe.
- Cognitive behavioral therapy for chronic pain. Targets catastrophizing, fear-avoidance, and hypervigilance. Strong evidence base.
- Mindfulness-based stress reduction (MBSR). Eight-week protocols are widely available and produce measurable reductions in pain interference.
- Low-dose tricyclics — amitriptyline or nortriptyline 10–25 mg at bedtime, far below antidepressant doses. Quiet dorsal-horn amplification, improve sleep, cheap.
- Serotonin-norepinephrine reuptake inhibitors (SNRIs) — duloxetine 30–60 mg, U.S. Food and Drug Administration-approved for chronic musculoskeletal pain and fibromyalgia; often effective for central sensitization in pelvic pain.
- Low-dose naltrexone — 1.5–4.5 mg at night. Off-label, growing evidence in fibromyalgia, irritable bowel syndrome, and chronic pelvic pain via glial modulation. Compounded; $30–$60 per month.
Gabapentin has been used off-label for chronic pelvic pain. In the GaPP2 trial (306 women with chronic pelvic pain and no obvious pelvic disease at laparoscopy, 16 weeks), worst pain fell 1.4 points on gabapentin and 1.2 on placebo on a numerical pain scale (p=0.47). Serious adverse events were more common on gabapentin (7% against 2%), as were dizziness, drowsiness and visual disturbances. This trial did not study endometriosis (Horne 2020).
Nerve Blocks and Trigger Point Injections
When physical therapy plus home work plus central-pain medication still leaves you stuck, procedural interventions can unlock progress. Performed by pain specialists, gynecologists with pelvic pain fellowships, or interventional radiologists:
- Trigger point injections — local anesthetic (with or without steroid) into the worst knots in levator ani, obturator internus, or piriformis. Unblocks stuck physical therapy progress.
- Pudendal nerve block — anesthetic around the pudendal nerve at Alcock's canal; both diagnostic and therapeutic for pudendal neuralgia.
- Obturator nerve block — for persistent inner-thigh / deep-groin pain.
- Botulinum toxin injection into levator ani — for severe hypertonic dysfunction unresponsive to manual therapy. Effects last 3–6 months and buy a window for physical therapy to retrain the pattern.
Trial results for botulinum toxin differ. A small randomized trial in women with endometriosis pain and pelvic floor spasm (100 units of botulinum toxin or saline placebo) found benefit at 1 month in 11 of 15 against 4 of 14 (p=0.027), and adverse events were non-serious (Karp 2026). A meta-analysis of 5 randomized trials (329 participants) in women with pelvic floor tension myalgia and persistent pelvic pain found no differences in pain, pain with sex, sexual function or vaginal manometry; its authors concluded the randomized data do not support botulinum toxin for these conditions and asked for trials with a true placebo (Knapman 2024).
Timeline Expectations
Realistic expectations matter here, because practitioners describe this as where most patients quit. Meaningful change in pelvic floor dysfunction typically takes 3–6 months of weekly physical therapy plus daily home work. Some patients feel 30% better after one or two sessions; others feel worse for several weeks before they feel better, because releasing a long-compensating floor exposes other imbalances.
Rewiring central sensitization takes longer — 6–18 months — and progress is nonlinear. The trend is what matters, not any single day. Consistency, sleep, and steady down-regulation of life stressors predict recovery better than any single drug or procedure.
When to Escalate
After six months of competent pelvic physical therapy, a fair medication trial, and reasonable pacing, with pain still running a person's life, practitioners re-examine the peripheral picture. A careful workup at that point looks for:
- Missed or recurrent endometriosis — particularly deep infiltrating lesions on the uterosacral ligaments, cul-de-sac, bowel, or diaphragm. Some patients seek a second opinion from a high-volume excision surgeon.
- Post-surgical adhesions tethering bowel, ovary, or pelvic sidewall.
- Adenomyosis — often missed on exam and only reliably diagnosed on high-quality pelvic magnetic resonance imaging (MRI). See the adenomyosis overlap page.
- Interstitial cystitis / bladder pain syndrome — frequently occurs alongside endometriosis; hydrodistention under anesthesia can confirm.
- Vulvodynia — localized or generalized vulvar burning, often comorbid and treatable with specific topical and oral therapies.
- Pudendal neuralgia — sharp burning in a pudendal distribution, worse sitting and relieved standing. Diagnostic block confirms.
The core message: if your pain did not go away after excision, it is not because you are broken or the surgery "didn't work." Endometriosis trains the nervous system and the muscles of the pelvis in ways that cutting out lesions alone does not undo. The tools to undo that training exist and they work.
Key Research Papers
- Aredo JV, Heyrana KJ, Karp BI, Shah JP, Stratton P. Relating chronic pelvic pain and endometriosis to signs of sensitization and myofascial pain and dysfunction. Semin Reprod Med. 2017. — doi:10.1055/s-0036-1597123
- Woolf CJ. Central sensitization: implications for the diagnosis and treatment of pain. Pain. 2011. — doi:10.1016/j.pain.2010.09.030
- Wurn BF, Wurn LJ, King CR, Heuer MA, Roscow AS, Scharf ES, Shuster JJ. Treating female infertility and improving IVF pregnancy rates with a manual physical therapy technique. MedGenMed. 2004;6(2):51. — PubMed PMID: 15266276 (An uncontrolled series of 53 infertile patients treated with manual therapy, reporting pregnancy and in vitro fertilization outcomes; it did not study pelvic floor physical therapy for endometriosis pain.)
- Becker CM, et al. ESHRE guideline: endometriosis. Hum Reprod Open. 2022. — doi:10.1093/hropen/hoac009
- Abbott J, Hawe J, Hunter D, Holmes M, Finn P, Garry R. Laparoscopic excision of endometriosis: a randomized, placebo-controlled trial. Fertil Steril. 2004;82(4):878–884. — PubMed PMID: 15482763
- Neblett R, Cohen H, Choi Y, Hartzell MM, Williams M, Mayer TG, Gatchel RJ. The Central Sensitization Inventory (CSI): establishing clinically significant values for identifying central sensitivity syndromes in an outpatient chronic pain sample. J Pain. 2013;14(5):438–445. — PubMed PMID: 23490634
- Raimondo D, Bertoldo L, Aguzzi A, Ramelli G, Arcilesi M, Maletta M, Doglioli M, Neola D, Paccapelo A, Scarperi S, Cobellis L, Seracchioli R, Raffone A. Central Sensitization and Hormonal Therapy Failure for Endometriosis-Related Pain Symptoms: A Prospective Study. J Minim Invasive Gynecol. 2026. — PubMed PMID: 42365867
- Del Forno S, Cocchi L, Arena A, Pellizzone V, Lenzi J, Raffone A, Borghese G, Paradisi R, Youssef A, Casadio P, Raimondo D, Seracchioli R. Effects of Pelvic Floor Muscle Physiotherapy on Urinary, Bowel, and Sexual Functions in Women with Deep Infiltrating Endometriosis: A Randomized Controlled Trial. Medicina (Kaunas). 2023;60(1):67. — PubMed PMID: 38256327
- Horne AW, Vincent K, Hewitt CA, Middleton LJ, Koscielniak M, Szubert W, Doust AM, Daniels JP; GaPP2 collaborative. Gabapentin for chronic pelvic pain in women (GaPP2): a multicentre, randomised, double-blind, placebo-controlled trial. Lancet. 2020;396(10255):909–917. — PubMed PMID: 32979978
- Karp BI, Tandon HK, Sinaii N, Aredo JV, Phan VT, Salmeri N, Shah JP, Merideth MA, Stratton P. Botulinum toxin for endometriosis-associated chronic pelvic pain: a randomised, double-masked, parallel, phase 2 trial. EClinicalMedicine. 2026;91:103740. — PubMed PMID: 41551998
- Knapman BL, Li FG, Deans R, Nesbitt-Hawes E, Maheux-Lacroix S, Abbott J. Botulinum Toxin for the Management of Pelvic Floor Tension Myalgia and Persistent Pelvic Pain: A Systematic Review and Meta-analysis. Obstet Gynecol. 2024;143(1):e7–e17. — PubMed PMID: 37797336
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on pelvic floor dysfunction, central sensitization, and endometriosis pain:
- PubMed: Pelvic floor dysfunction and endometriosis
- PubMed: Central sensitization and chronic pelvic pain
- PubMed: Pelvic physical therapy and dyspareunia
- PubMed: Myofascial release for pelvic pain
- PubMed: Central Sensitization Inventory validation
- PubMed: Low-dose naltrexone in chronic pain
- PubMed: Pudendal neuralgia diagnosis and treatment
- PubMed: Botulinum toxin for pelvic floor dysfunction
Connections
- Reproductive Medicine
- Adenomyosis Overlap
- Endometriosis
- Laparoscopy: Excision vs Ablation
- Fibromyalgia
- Chronic Pain
- Interstitial Cystitis
- Migraine
- Diagnosis Delay and Imaging
- Hormonal Therapy Options
- Fertility and Endometriosis
- Endo Belly and Gut Connection
- Diet and Lifestyle
- Bladder and Bowel Endometriosis
- Irritable Bowel Syndrome
- Infertility
- Central Sensitization Explained
- Chronic Fatigue Syndrome
- Uterine Fibroids