Peppermint, Probiotics & Herbals for Irritable Bowel Syndrome (IBS)
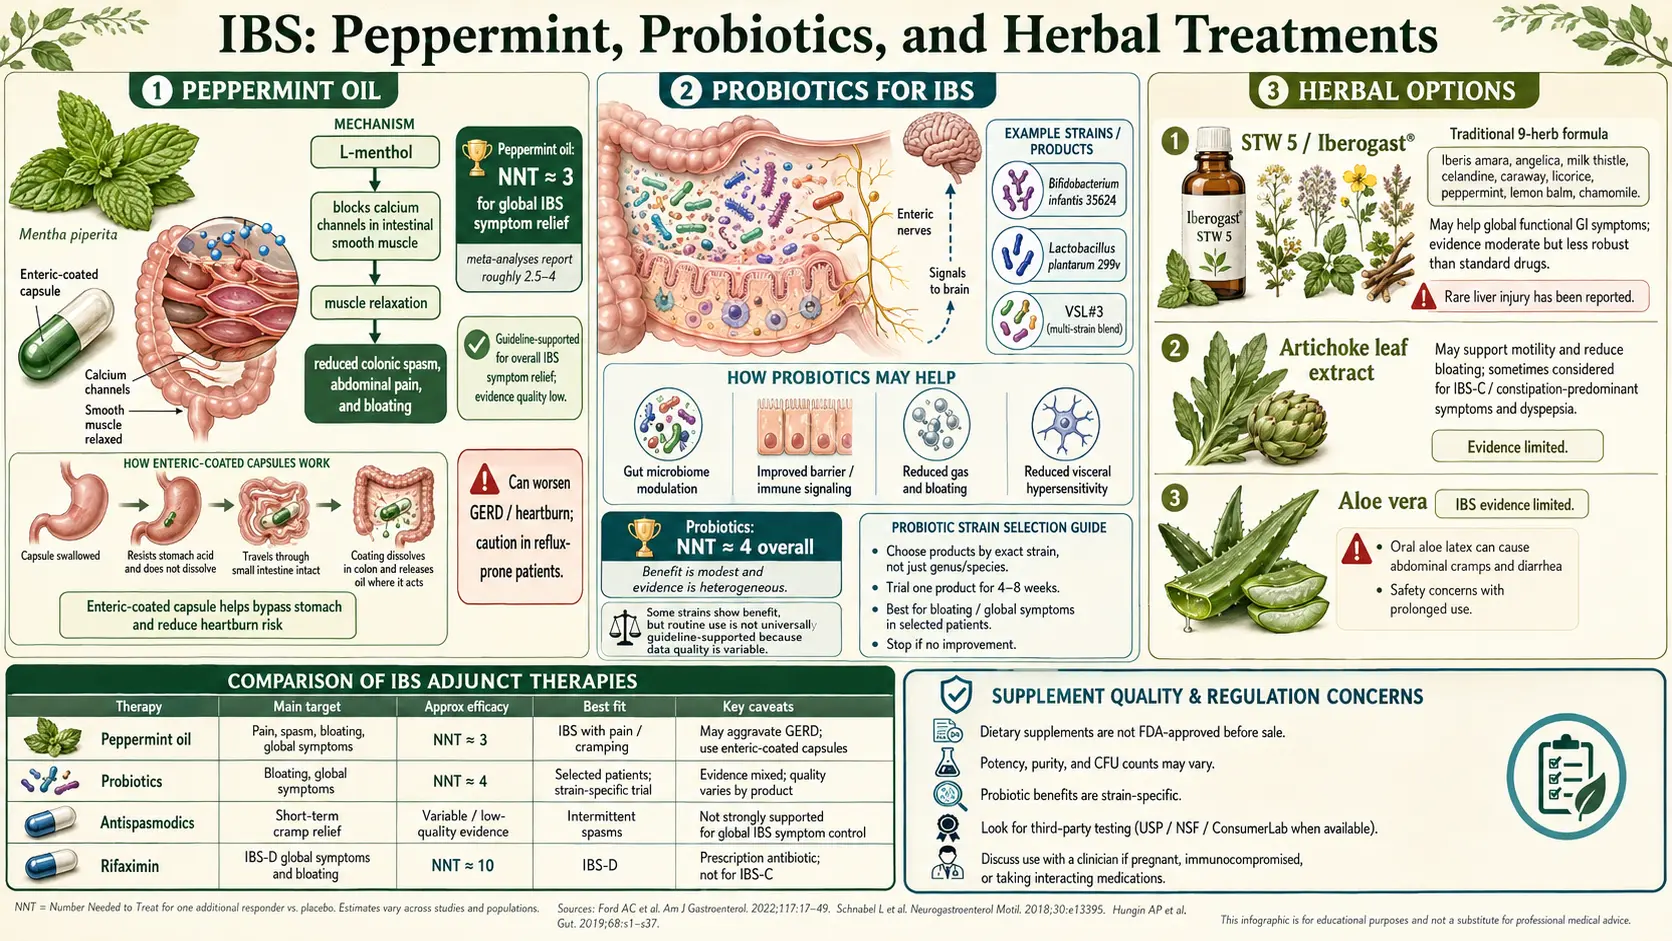
Table of Contents
- Why Herbal and Probiotic Options Are Studied
- Enteric-Coated Peppermint Oil: The Trial Evidence
- Peppermint Oil Formulations in the Trials
- Peppermint Side Effects & Interactions
- Probiotics: What the Guidelines Say
- Bifidobacterium infantis 35624
- The High-Dose Eight-Strain Mixture
- Lactobacillus plantarum 299v & a Liquid Multi-Strain Probiotic
- Saccharomyces boulardii & Spore-Forming Bacillus
- Probiotics, Small Intestinal Bacterial Overgrowth and Product Variation
- A Nine-Herb Combination Product
- Triphala, Artichoke Leaf, Curcumin & Chinese Herbal Formulas
- Slippery Elm, Marshmallow Root & the Mucilage Herbs
- Psyllium, Bran & PHGG: The Fibre Trials
- Prebiotics: What the Meta-Analysis Found
- Ginger, Chamomile & Fennel
- Supplement Quality and Regulation
- Pregnancy: What Is Known
- When Symptoms Point Beyond Irritable Bowel Syndrome
- Key Research Papers
- Connections
- Featured Videos
Why Herbal and Probiotic Options Are Studied
Many people with irritable bowel syndrome (IBS) try non-prescription options — peppermint oil capsules, probiotics, herbal combinations, fibre — before or alongside prescription drugs. The evidence behind them varies widely. Some have several placebo-controlled trials and pooled analyses; some rest on a single small trial; some have none. This article sets out what the trials and the major guidelines report for each.
In short: the 2021 American College of Gastroenterology (ACG) guideline gives peppermint oil a conditional recommendation based on low-quality evidence, as summarised in a 2024 review of the irritable bowel syndrome guidelines (Papale 2024). For probiotics, the ACG guideline suggests against their use for global irritable bowel syndrome symptoms, and the 2020 American Gastroenterological Association (AGA) probiotics guideline recommends their use in irritable bowel syndrome only in the context of a clinical trial (Marlicz 2021). Soluble fibre (psyllium) has the most consistent fibre evidence; wheat bran does not.
Products on sale differ from one another and from the preparations tested in trials, so a trial result applies to the preparation and dose that was studied.
Enteric-Coated Peppermint Oil: The Trial Evidence
The main constituent of peppermint oil is menthol. In laboratory studies on guinea-pig intestinal muscle and other animal tissue, menthol and peppermint oil blocked calcium channels, an action the authors proposed may underlie their use in irritable bowel syndrome; they noted it may not be the only mechanism (Hawthorn 1988).
The Khanna et al. 2014 meta-analysis, published in the Journal of Clinical Gastroenterology, identified nine randomized trials with 726 patients. Peppermint oil was significantly better than placebo for global improvement of irritable bowel syndrome symptoms (5 studies, 392 patients, relative risk 2.23) and for improvement in abdominal pain (5 studies, 357 patients, relative risk 2.14). Adverse events were more common with peppermint oil but were mild and transient; the most common was heartburn.
An earlier meta-analysis, Ford et al. 2008 in the BMJ, pooled four trials of peppermint oil versus placebo in 392 patients (relative risk of persistent symptoms 0.43) and reported a number needed to treat of 2.5 to prevent one patient having persistent symptoms. The same review reported a number needed to treat of 5 for antispasmodic drugs and 11 for fibre.
Later trials were less consistent. A 2022 update of that meta-analysis (Ingrosso 2022) pooled 10 randomized trials with 1,030 patients: peppermint oil was more effective than placebo for global symptoms (number needed to treat 4) and abdominal pain (number needed to treat 7), adverse events were more frequent, and the authors rated the quality of evidence as very low.
- Dutch trial (Weerts 2020). In 190 patients with irritable bowel syndrome given 182 mg of small-intestinal-release peppermint oil, 182 mg of ileocolonic-release peppermint oil, or placebo for 8 weeks, neither formulation met the primary endpoint (abdominal pain response: 46.8% and 41.3% versus 34.4% with placebo) or the co-primary endpoint of overall relief. The small-intestinal-release capsule did improve the secondary measures of abdominal pain, discomfort and irritable bowel syndrome severity.
- U.S. trial (Nee 2021). In a 6-week trial of enteric-coated peppermint oil 180 mg three times daily versus placebo, both groups improved substantially, and the difference between them was not statistically significant.
Guidelines. The 2021 ACG guideline makes a conditional recommendation for peppermint oil (low quality of evidence). The 2022 AGA guidelines on the drug treatment of irritable bowel syndrome with diarrhoea and irritable bowel syndrome with constipation make conditional recommendations for antispasmodics (low certainty); a 2024 review lists peppermint oil within that AGA antispasmodic recommendation (Papale 2024). The AGA abstracts themselves name antispasmodics, not peppermint oil.
Peppermint Oil Formulations in the Trials
- Sustained small-intestinal release. A 4-week U.S. trial of a peppermint oil formulation designed for sustained release in the small intestine, taken three times daily, randomized 72 patients with irritable bowel syndrome-M or diarrhea-predominant irritable bowel syndrome (IBS-D); total symptom scores fell by 40% with peppermint oil versus 24.3% with placebo (Cash 2016).
- Small-intestinal versus ileocolonic release. The Dutch trial above compared the two release sites directly; the authors concluded their findings did not support further development of the ileocolonic-release capsule (Weerts 2020).
- Standard enteric-coated capsules. The U.S. trial above used 180 mg three times daily and found no significant difference from placebo (Nee 2021).
These trials tested specific formulations at specific doses; the results do not show that one commercial product is better than another.
Peppermint Side Effects & Interactions
- Heartburn and reflux. Heartburn was the most commonly reported adverse event in the Khanna 2014 meta-analysis. A 2024 review notes that peppermint relaxes the lower esophageal sphincter and can worsen reflux in people with hiatal hernia and gastroesophageal reflux disease (Tetali 2024).
- Adverse events overall. In the 2022 meta-analysis, adverse events were more frequent with peppermint oil than with placebo (relative risk 1.57); in the Dutch trial they were mild but more common in both peppermint groups.
- Drug interactions. In human liver microsomes, peppermint oil and menthol inhibited the drug-metabolising enzyme cytochrome P450 3A4 (CYP3A4), and in 12 healthy volunteers 600 mg of peppermint oil increased exposure to the blood-pressure drug felodipine; the authors wrote that the mechanism needs further investigation (Dresser 2002). In rats, peppermint oil tripled the peak blood level of the transplant drug cyclosporine (Wacher 2002) — an animal finding, not a human one. The research raises a concern for people taking medicines metabolised by cytochrome P450 3A4.
- Iron absorption. In adults, peppermint tea taken with a bread meal reduced non-haem iron absorption by 84% (Hurrell 1999). That study tested the tea, not capsules of the oil.
Probiotics: What the Guidelines Say
The 2021 ACG guideline suggests against probiotics for the treatment of global irritable bowel syndrome symptoms (conditional recommendation, very low quality of evidence). The 2020 AGA probiotics guideline recommends the use of probiotics in irritable bowel syndrome only in the context of a clinical trial, describing the evidence as a knowledge gap (Marlicz 2021, a review of the guidelines; Su 2020).
The AGA technical review behind that guideline found 55 trials with 5,301 patients that tested 44 different probiotic species, strains or combinations — so for most probiotics, the evidence comes from a single trial. Several single trials reported benefit, the certainty of evidence was low or very low, and the panel found registered trials that had never been published, raising the possibility of publication bias. It concluded that no single strain or combination had been studied in a sufficiently rigorous manner (Preidis 2020).
Effects differ by strain, so a result for one strain does not transfer to another. The sections below describe the strains with published irritable bowel syndrome trials.
Bifidobacterium infantis 35624
O'Mahony et al. 2005, in Gastroenterology, randomized 77 people with irritable bowel syndrome to B. infantis 35624 or Lactobacillus salivarius UCC4331, each at 1 × 10¹⁰ live bacteria in a malted milk drink, or to the malted milk drink alone, for eight weeks. Scores for abdominal pain or discomfort, bloating or distension, and bowel-movement difficulty were significantly lower than placebo with B. infantis 35624 for most weeks. At baseline, patients had an abnormal ratio of the cytokines interleukin-10 (IL-10) and IL-12, which B. infantis 35624 alone normalised.
Whorwell et al. 2006 tested an encapsulated form in 362 women with irritable bowel syndrome in primary care at three doses for 4 weeks. Only the 1 × 10⁸ CFU dose was significantly better than placebo for abdominal pain and several other symptoms; the 1 × 10⁶ and 1 × 10¹⁰ doses were not, and the highest dose had formulation problems. The authors noted that this shows the need for clinical data on the final dosage form and dose.
The High-Dose Eight-Strain Mixture
This mixture combines eight strains of Lactobacillus, Bifidobacterium and Streptococcus thermophilus (Preidis 2020). Two small trials from one research group tested it in irritable bowel syndrome:
- Kim 2003: 25 patients with diarrhoea-predominant irritable bowel syndrome received 450 billion bacteria a day or placebo for 8 weeks. There were no significant differences in transit, bowel function or satisfactory global symptom relief; abdominal bloating fell within the probiotic group.
- Kim 2005: 48 patients with irritable bowel syndrome and bloating; flatulence scores fell and colonic transit slowed with the mixture, while relief of bloating, stool symptoms and abdominal pain did not differ from placebo.
Pooling two trials (73 adults), the AGA technical review found the mixture may decrease abdominal pain, with very low certainty of evidence (Preidis 2020).
Lactobacillus plantarum 299v & a Liquid Multi-Strain Probiotic
Lactobacillus plantarum 299v was tested in two 4-week trials. Niedzielin et al. 2001 randomized 40 patients to a liquid suspension or placebo; all 20 in the probiotic group reported resolution of abdominal pain, compared with 11 on placebo. Ducrotté et al. 2012 randomized 214 patients to one capsule daily or placebo; pain severity, pain frequency and bloating were lower with the probiotic. The AGA technical review lists L. plantarum 299v among probiotics shown in a single trial to improve global symptoms and abdominal pain (Preidis 2020).
A liquid multi-strain probiotic was tested for 12 weeks in 186 adults with irritable bowel syndrome (Sisson 2014). Symptom severity scores fell by 63.3 points with the probiotic versus 28.3 with placebo, a statistically significant difference; quality of life did not improve significantly, and no serious adverse events were reported.
Saccharomyces boulardii & Spore-Forming Bacillus
Saccharomyces boulardii is a yeast used as a probiotic. In the AGA technical review, three trials of S. boulardii in 232 adults with irritable bowel syndrome showed no difference from placebo in abdominal pain scores (very low certainty of evidence) (Preidis 2020).
Spore-forming Bacillus probiotics are a separate category. The AGA technical review lists Bacillus coagulans MTCC 5856 among probiotics that improved abdominal pain in a single adult irritable bowel syndrome trial (Preidis 2020). A 30-day study of a spore-based Bacillus product in healthy adults, not people with irritable bowel syndrome, reported a 42% reduction in blood endotoxin after a meal (McFarlin 2017).
Probiotics, Small Intestinal Bacterial Overgrowth and Product Variation
- Small intestinal bacterial overgrowth (SIBO). The trials summarised here did not report results for people with small intestinal bacterial overgrowth, so they do not show how probiotics affect that group. Small intestinal bacterial overgrowth and its treatment, including herbal antimicrobials for small intestinal bacterial overgrowth, are covered on the small intestinal bacterial overgrowth pages.
- Product variation. Benefit in irritable bowel syndrome trials was specific to strain, dose and formulation: in the Whorwell 2006 trial only one of three doses of the same strain worked. One trial found a six-strain combination was worse than placebo for global relief of symptoms (Preidis 2020).
A Nine-Herb Combination Product
One widely studied liquid herbal product, coded STW 5 in the research literature, combines nine plant extracts: bitter candytuft (Iberis amara), lemon balm, chamomile, caraway, peppermint, licorice, angelica, milk thistle and greater celandine (Khayyal 2001). A research version called STW 5-II leaves out the last three.
- Irritable bowel syndrome. In a 4-week trial of 208 people with irritable bowel syndrome, both STW 5 and STW 5-II reduced abdominal pain and irritable bowel syndrome symptom scores more than placebo; a bitter candytuft extract alone did not differ significantly from placebo (Madisch 2004). A 2020 systematic review of Western herbal medicines in irritable bowel syndrome lists STW 5 and STW 5-II among preparations with positive results in rigorously designed trials, but notes that, apart from peppermint oil, aloe vera and asafoetida, none of the positive herbal trials has been replicated (Hawrelak 2020).
- Functional dyspepsia. A 2004 meta-analysis pooled three placebo-controlled dyspepsia trials (138 patients on the product, 135 on placebo) and found it more effective than placebo for the most bothersome symptom (Melzer 2004). In a 4-week trial in 186 patients, STW 5 and STW 5-II were non-inferior to the prokinetic drug cisapride (Rösch 2002).
- Liver safety. A 2016 case report describes severe liver injury linked to the product that led to liver transplantation (Sáez-González 2016). Separately, a 2017 review of greater celandine found liver-injury cases assessed as probably or highly probably connected to the herb and judged the risk-to-benefit ratio of greater-celandine products to be negative (Pantano 2017).
Triphala, Artichoke Leaf, Curcumin & Chinese Herbal Formulas
Triphala is an Ayurvedic preparation of the fruits of three plants: Phyllanthus emblica, Terminalia chebula and Terminalia bellirica. A 2021 review describes its traditional use for gastrointestinal disorders and reports clinical studies in constipation (Ahmed 2021). No controlled trial of triphala in irritable bowel syndrome is cited on this page.
Artichoke leaf extract (Cynara scolymus): the cited study is a post-hoc subset analysis of an open, uncontrolled, postal study in adults with dyspepsia. Among 208 who also had irritable bowel syndrome, the proportion meeting irritable bowel syndrome criteria fell by 26.4% after two months of the extract (Bundy 2004). Without a placebo group, the study cannot separate the extract's effect from other causes of improvement.
Curcumin, from turmeric: a 2018 meta-analysis of three randomized trials (326 patients) found an effect on irritable bowel syndrome symptoms that favoured curcumin but was not statistically significant, and described the evidence base as limited and heterogeneous (Ng 2018). A combination of curcumin and fennel essential oil is covered under fennel below. More on the spice is on the turmeric page.
Chinese herbal medicine: in a 16-week randomized trial of 116 patients, both individualised and standard Chinese herbal formulas improved bowel symptom scores more than placebo (Bensoussan 1998). A 2021 meta-analysis of 10 trials with 2,501 participants found Chinese herbal medicine more effective than placebo for adequate relief of global irritable bowel syndrome symptoms, with more adverse events than placebo (relative risk 1.51) (Zheng 2021). The formulas differ from trial to trial.
Slippery Elm, Marshmallow Root & the Mucilage Herbs
Slippery elm (Ulmus rubra), marshmallow root (Althaea officinalis) and deglycyrrhizinated licorice (DGL) are traditional remedies for gut irritation. No controlled irritable bowel syndrome trial of these herbs is cited on this page, so their effect in irritable bowel syndrome is not established by the evidence reviewed here.
Psyllium, Bran & PHGG: The Fibre Trials
The fibre trials separate clearly by fibre type.
- Psyllium (ispaghula husk). In the Ford 2008 meta-analysis, the benefit of fibre was limited to ispaghula (relative risk of persistent symptoms 0.78; number needed to treat 6), and bran had no significant effect. A 2014 update of 14 trials (906 patients) found benefit only for soluble fibre (number needed to treat 7) and none for bran (Moayyedi 2014). In a 12-week primary-care trial of 275 patients, 10 g of psyllium a day produced more responders than placebo in the first two months, and symptom severity fell by 90 points versus 49 with placebo (Bijkerk 2009). The 2021 ACG guideline gives soluble fibre a strong recommendation with moderate-quality evidence (Papale 2024).
- Wheat bran. Bran did not outperform placebo in either meta-analysis. The 2014 review found no evidence of harm from bran. In the 2009 trial, early dropout was most common in the bran group, mainly because irritable bowel syndrome symptoms worsened (Bijkerk 2009).
- Partially hydrolyzed guar gum (PHGG). In a trial of 121 randomized patients, 6 g a day for 12 weeks improved diary scores for bloating and for bloating with gas compared with placebo, but had no effect on other symptoms, overall severity scores or quality of life (Niv 2016).
Prebiotics: What the Meta-Analysis Found
Prebiotics are fibres that feed gut bacteria. A 2019 meta-analysis of 11 randomized trials (729 patients) found that prebiotics did not improve global response, abdominal pain, bloating, flatulence or quality of life compared with placebo, although they increased bifidobacteria. In subgroup analyses, inulin-type fructans (the group that includes inulin and fructo-oligosaccharides, FOS) worsened flatulence, while doses of 6 g a day or less and non-inulin-type prebiotics improved it (Wilson 2019). The overlap between irritable bowel syndrome and bacterial overgrowth is covered on the small intestinal bacterial overgrowth overlap page.
PHGG, the guar-gum fibre described above, improved bloating in its own trial (Niv 2016).
Ginger, Chamomile & Fennel
- Ginger. A traditional digestive herb; no controlled irritable bowel syndrome trial of ginger is cited on this page.
- Chamomile. A traditional digestive and calming herb; no controlled irritable bowel syndrome trial of chamomile is cited on this page.
- Fennel. In a 30-day randomized trial of 121 patients with mild-to-moderate irritable bowel syndrome, a combination of curcumin and fennel essential oil reduced symptom severity scores by 50.05% versus 26.12% with placebo, and more patients became symptom-free (25.9% versus 6.8%) (Portincasa 2016).
Supplement Quality and Regulation
In the United States, dietary supplements are not approved by the U.S. Food and Drug Administration (FDA) before sale. The firms that make and distribute them are responsible for evaluating safety and labelling before marketing, and the U.S. Food and Drug Administration can act against adulterated or misbranded products after they reach the market (U.S. Food and Drug Administration).
Several trials above show why the exact preparation matters: one strain worked at one dose but not at two others (Whorwell 2006), and two peppermint oil capsules with different release sites gave different results (Weerts 2020). The AGA technical review also noted that probiotic studies varied in strain, dose and method (Preidis 2020).
Pregnancy: What Is Known
The trials summarised on this page do not report results in pregnancy, so they say nothing about the safety of these products for a pregnant woman or her baby. The liver-injury findings for greater celandine (Pantano 2017) and the drug-interaction findings for peppermint oil (Dresser 2002) described above are not specific to pregnancy. Decisions about medicines and supplements in pregnancy belong with a clinician.
When Symptoms Point Beyond Irritable Bowel Syndrome
The herbal and probiotic trials enrolled people already diagnosed with irritable bowel syndrome. Some findings point to the need for further evaluation rather than irritable bowel syndrome treatment:
- Alarm features. A 2024 review of irritable bowel syndrome management lists alarm symptoms such as rectal bleeding, unintentional weight loss and a family history of colon cancer; without them, irritable bowel syndrome is diagnosed with limited testing based on history and the Rome IV criteria (Papale 2024).
- Testing for other conditions. The 2021 ACG guideline suggests serologic testing for celiac disease and a fecal calprotectin test to rule out inflammatory bowel disease in people with suspected irritable bowel syndrome and diarrhoea symptoms. Peppermint oil and probiotics are not treatments for Crohn's disease or ulcerative colitis.
- Prescription options for irritable bowel syndrome with diarrhoea. The 2022 AGA guideline makes conditional recommendations for eluxadoline, rifaximin, alosetron, loperamide, tricyclic antidepressants and antispasmodics in diarrhea-predominant irritable bowel syndrome, and the ACG guideline recommends rifaximin for global diarrhea-predominant irritable bowel syndrome symptoms. These are covered in the medications guide.
- Gut-brain therapies. The ACG guideline suggests gut-directed psychotherapy for global irritable bowel syndrome symptoms; see gut-directed hypnotherapy and cognitive behavioral therapy (CBT).
Related pages cover the medication guide, small intestinal bacterial overgrowth overlap and post-infectious irritable bowel syndrome.
Key Research Papers
- Khanna R, MacDonald JK, Levesque BG. Peppermint oil for the treatment of irritable bowel syndrome: a systematic review and meta-analysis. J Clin Gastroenterol. 2014;48(6):505-12. — doi:10.1097/mcg.0b013e3182a88357
- O'Mahony L, et al. Lactobacillus and Bifidobacterium in irritable bowel syndrome: symptom responses and relationship to cytokine profiles. Gastroenterology. 2005. — doi:10.1053/j.gastro.2004.11.050
- Whorwell PJ, et al. Efficacy of an encapsulated probiotic Bifidobacterium infantis 35624 in women with irritable bowel syndrome. Am J Gastroenterol. 2006. — doi:10.1111/j.1572-0241.2006.00734.x
- Rösch W, Vinson B, Sassin I. A randomised clinical trial comparing the efficacy of a herbal preparation STW 5 with the prokinetic drug cisapride in patients with dysmotility type of functional dyspepsia. Z Gastroenterol. 2002;40(6):401-8. — PubMed PMID: 12055663 (Corrected 2026-10-14: this entry previously described a 1995 placebo-controlled trial in the same journal, for which no record was found in PubMed or Crossref.)
- Ford AC, Talley NJ, Spiegel BM, et al. Effect of fibre, antispasmodics, and peppermint oil in the treatment of irritable bowel syndrome: systematic review and meta-analysis. BMJ. 2008;337:a2313. — PubMed PMID: 19008265
- Ingrosso MR, Ianiro G, Nee J, et al. Systematic review and meta-analysis: efficacy of peppermint oil in irritable bowel syndrome. Aliment Pharmacol Ther. 2022;56(6):932-941. — PubMed PMID: 35942669
- Weerts ZZRM, Masclee AAM, Witteman BJM, et al. Efficacy and Safety of Peppermint Oil in a Randomized, Double-Blind Trial of Patients With Irritable Bowel Syndrome. Gastroenterology. 2020;158(1):123-136. — PubMed PMID: 31470006
- Nee J, Ballou S, Kelley JM, et al. Peppermint Oil Treatment for Irritable Bowel Syndrome: A Randomized Placebo-Controlled Trial. Am J Gastroenterol. 2021;116(11):2279-2285. — PubMed PMID: 34319275
- Cash BD, Epstein MS, Shah SM. A Novel Delivery System of Peppermint Oil Is an Effective Therapy for Irritable Bowel Syndrome Symptoms. Dig Dis Sci. 2016;61(2):560-71. — PubMed PMID: 26319955
- Lacy BE, Pimentel M, Brenner DM, et al. ACG Clinical Guideline: Management of Irritable Bowel Syndrome. Am J Gastroenterol. 2021;116(1):17-44. — PubMed PMID: 33315591
- Lembo A, Sultan S, Chang L, et al. AGA Clinical Practice Guideline on the Pharmacological Management of Irritable Bowel Syndrome With Diarrhea. Gastroenterology. 2022;163(1):137-151. — PubMed PMID: 35738725
- Chang L, Sultan S, Lembo A, et al. AGA Clinical Practice Guideline on the Pharmacological Management of Irritable Bowel Syndrome With Constipation. Gastroenterology. 2022;163(1):118-136. — PubMed PMID: 35738724
- Su GL, Ko CW, Bercik P, et al. AGA Clinical Practice Guidelines on the Role of Probiotics in the Management of Gastrointestinal Disorders. Gastroenterology. 2020;159(2):697-705. — PubMed PMID: 32531291
- Preidis GA, Weizman AV, Kashyap PC, et al. AGA Technical Review on the Role of Probiotics in the Management of Gastrointestinal Disorders. Gastroenterology. 2020;159(2):708-738.e4. — PubMed PMID: 32531292
- Papale AJ, Flattau R, Vithlani N, et al. A Review of Pharmacologic and Non-Pharmacologic Therapies in the Management of Irritable Bowel Syndrome: Current Recommendations and Evidence. J Clin Med. 2024;13(22):6948. — PubMed PMID: 39598092
- Marlicz W, Skonieczna-Żydecka K, Krynicka P, et al. Probiotics in irritable bowel syndrome – is the quest for the right strain over? Rapid review of existing guidelines and recommendations. Prz Gastroenterol. 2021;16(4):369-382. — PubMed PMID: 34976247
- Tetali B, Suresh S. Management of irritable bowel syndrome: a narrative review. Transl Gastroenterol Hepatol. 2024;9:26. — PubMed PMID: 38716216
- Hawthorn M, Ferrante J, Luchowski E, et al. The actions of peppermint oil and menthol on calcium channel dependent processes in intestinal, neuronal and cardiac preparations. Aliment Pharmacol Ther. 1988;2(2):101-18. — PubMed PMID: 2856502
- Dresser GK, Wacher V, Wong S, et al. Evaluation of peppermint oil and ascorbyl palmitate as inhibitors of cytochrome P4503A4 activity in vitro and in vivo. Clin Pharmacol Ther. 2002;72(3):247-55. — PubMed PMID: 12235445
- Wacher VJ, Wong S, Wong HT. Peppermint oil enhances cyclosporine oral bioavailability in rats: comparison with D-alpha-tocopheryl poly(ethylene glycol 1000) succinate (TPGS) and ketoconazole. J Pharm Sci. 2002;91(1):77-90. — PubMed PMID: 11782899
- Hurrell RF, Reddy M, Cook JD. Inhibition of non-haem iron absorption in man by polyphenolic-containing beverages. Br J Nutr. 1999;81(4):289-95. — PubMed PMID: 10999016
- Niedzielin K, Kordecki H, Birkenfeld B. A controlled, double-blind, randomized study on the efficacy of Lactobacillus plantarum 299V in patients with irritable bowel syndrome. Eur J Gastroenterol Hepatol. 2001;13(10):1143-7. — PubMed PMID: 11711768
- Ducrotté P, Sawant P, Jayanthi V. Clinical trial: Lactobacillus plantarum 299v (DSM 9843) improves symptoms of irritable bowel syndrome. World J Gastroenterol. 2012;18(30):4012-8. — PubMed PMID: 22912552
- Sisson G, Ayis S, Sherwood RA, Bjarnason I. Randomised clinical trial: A liquid multi-strain probiotic vs. placebo in the irritable bowel syndrome – a 12 week double-blind study. Aliment Pharmacol Ther. 2014;40(1):51-62. — PubMed PMID: 24815298
- Kim HJ, Camilleri M, McKinzie S, et al. A randomized controlled trial of a probiotic, [product name omitted], on gut transit and symptoms in diarrhoea-predominant irritable bowel syndrome. Aliment Pharmacol Ther. 2003;17(7):895-904. — PubMed PMID: 12656692
- Kim HJ, Vazquez Roque MI, Camilleri M, et al. A randomized controlled trial of a probiotic combination [product name omitted] and placebo in irritable bowel syndrome with bloating. Neurogastroenterol Motil. 2005;17(5):687-96. — PubMed PMID: 16185307
- McFarlin BK, Henning AL, Bowman EM, et al. Oral spore-based probiotic supplementation was associated with reduced incidence of post-prandial dietary endotoxin, triglycerides, and disease risk biomarkers. World J Gastrointest Pathophysiol. 2017;8(3):117-126. — PubMed PMID: 28868181
- Madisch A, Holtmann G, Plein K, Hotz J. Treatment of irritable bowel syndrome with herbal preparations: results of a double-blind, randomized, placebo-controlled, multi-centre trial. Aliment Pharmacol Ther. 2004;19(3):271-9. — PubMed PMID: 14984373
- Melzer J, Rösch W, Reichling J, et al. Meta-analysis: phytotherapy of functional dyspepsia with the herbal drug preparation STW 5 [product name omitted]. Aliment Pharmacol Ther. 2004;20(11-12):1279-87. — PubMed PMID: 15606389
- Khayyal MT, el-Ghazaly MA, Kenawy SA, et al. Antiulcerogenic effect of some gastrointestinally acting plant extracts and their combination. Arzneimittelforschung. 2001;51(7):545-53. (Rat study; cited for the product's composition.) — PubMed PMID: 11505785
- Sáez-González E, Conde I, Díaz-Jaime FC, et al. [Product name omitted]-induced severe hepatotoxicity leading to liver transplantation. Am J Gastroenterol. 2016;111(9):1364-5. — PubMed PMID: 27580789
- Pantano F, Mannocchi G, Marinelli E, et al. Hepatotoxicity induced by greater celandine (Chelidonium majus L.): a review of the literature. Eur Rev Med Pharmacol Sci. 2017;21(1 Suppl):46-52. — PubMed PMID: 28379595
- Hawrelak JA, Wohlmuth H, Pattinson M, et al. Western herbal medicines in the treatment of irritable bowel syndrome: A systematic review and meta-analysis. Complement Ther Med. 2020;48:102233. — PubMed PMID: 31987249
- Ahmed S, Ding X, Sharma A. Exploring scientific validation of Triphala Rasayana in ayurveda as a source of rejuvenation for contemporary healthcare: An update. J Ethnopharmacol. 2021;273:113829. — PubMed PMID: 33465446
- Bundy R, Walker AF, Middleton RW, et al. Artichoke leaf extract reduces symptoms of irritable bowel syndrome and improves quality of life in otherwise healthy volunteers suffering from concomitant dyspepsia: a subset analysis. J Altern Complement Med. 2004;10(4):667-9. — PubMed PMID: 15353023
- Ng QX, Soh AYS, Loke W, et al. A Meta-Analysis of the Clinical Use of Curcumin for Irritable Bowel Syndrome (IBS). J Clin Med. 2018;7(10):298. — PubMed PMID: 30248988
- Bensoussan A, Talley NJ, Hing M, et al. Treatment of irritable bowel syndrome with Chinese herbal medicine: a randomized controlled trial. JAMA. 1998;280(18):1585-9. — PubMed PMID: 9820260
- Zheng H, Jin S, Shen YL, et al. Chinese Herbal Medicine for Irritable Bowel Syndrome: A Meta-Analysis and Trial Sequential Analysis of Randomized Controlled Trials. Front Pharmacol. 2021;12:694741. — PubMed PMID: 34385918
- Moayyedi P, Quigley EM, Lacy BE, et al. The effect of fiber supplementation on irritable bowel syndrome: a systematic review and meta-analysis. Am J Gastroenterol. 2014;109(9):1367-74. — PubMed PMID: 25070054
- Bijkerk CJ, de Wit NJ, Muris JW, et al. Soluble or insoluble fibre in irritable bowel syndrome in primary care? Randomised placebo controlled trial. BMJ. 2009;339:b3154. — PubMed PMID: 19713235
- Niv E, Halak A, Tiommny E, et al. Randomized clinical study: Partially hydrolyzed guar gum (PHGG) versus placebo in the treatment of patients with irritable bowel syndrome. Nutr Metab (Lond). 2016;13:10. — PubMed PMID: 26855665
- Wilson B, Rossi M, Dimidi E, et al. Prebiotics in irritable bowel syndrome and other functional bowel disorders in adults: a systematic review and meta-analysis of randomized controlled trials. Am J Clin Nutr. 2019;109(4):1098-1111. — PubMed PMID: 30949662
- Portincasa P, Bonfrate L, Scribano ML, et al. Curcumin and Fennel Essential Oil Improve Symptoms and Quality of Life in Patients with Irritable Bowel Syndrome. J Gastrointestin Liver Dis. 2016;25(2):151-7. — PubMed PMID: 27308645
- U.S. Food and Drug Administration. Dietary Supplements. Accessed 2026-10-14. — fda.gov/food/dietary-supplements
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on herbal and probiotic therapy for irritable bowel syndrome:
- PubMed: Peppermint oil RCTs in IBS
- PubMed: Bifidobacterium infantis 35624 and IBS
- PubMed: Lactobacillus plantarum 299v and IBS
- PubMed: STW 5 functional GI trials
- PubMed: Psyllium in IBS
- PubMed: Partially hydrolyzed guar gum (PHGG) in IBS
- PubMed: Triphala and functional constipation
- PubMed: Saccharomyces boulardii in IBS and antibiotic-associated diarrhea
- PubMed: Soil-based Bacillus spore probiotics in IBS
- PubMed: Artichoke leaf extract in IBS and functional dyspepsia
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Irritable Bowel Syndrome
- Small Intestinal Bacterial Overgrowth
- Herbal Antimicrobials
- Peppermint
- Ginger
- Turmeric
- Fennel
- Chamomile
- Probiotics
- Post-Infectious Irritable Bowel Syndrome
- Irritable Bowel Syndrome and Small Intestinal Bacterial Overgrowth Overlap
- Irritable Bowel Syndrome Medications Guide
- Low-FODMAP Diet for Irritable Bowel Syndrome
- Visceral Hypersensitivity and Brain-Gut Axis
- Gut-Directed Hypnotherapy and Cognitive Behavioral Therapy
- Ulcerative Colitis
- Crohn's Disease
- Bloating