Gut-Directed Hypnotherapy and Cognitive Behavioral Therapy (CBT) for Irritable Bowel Syndrome (IBS)
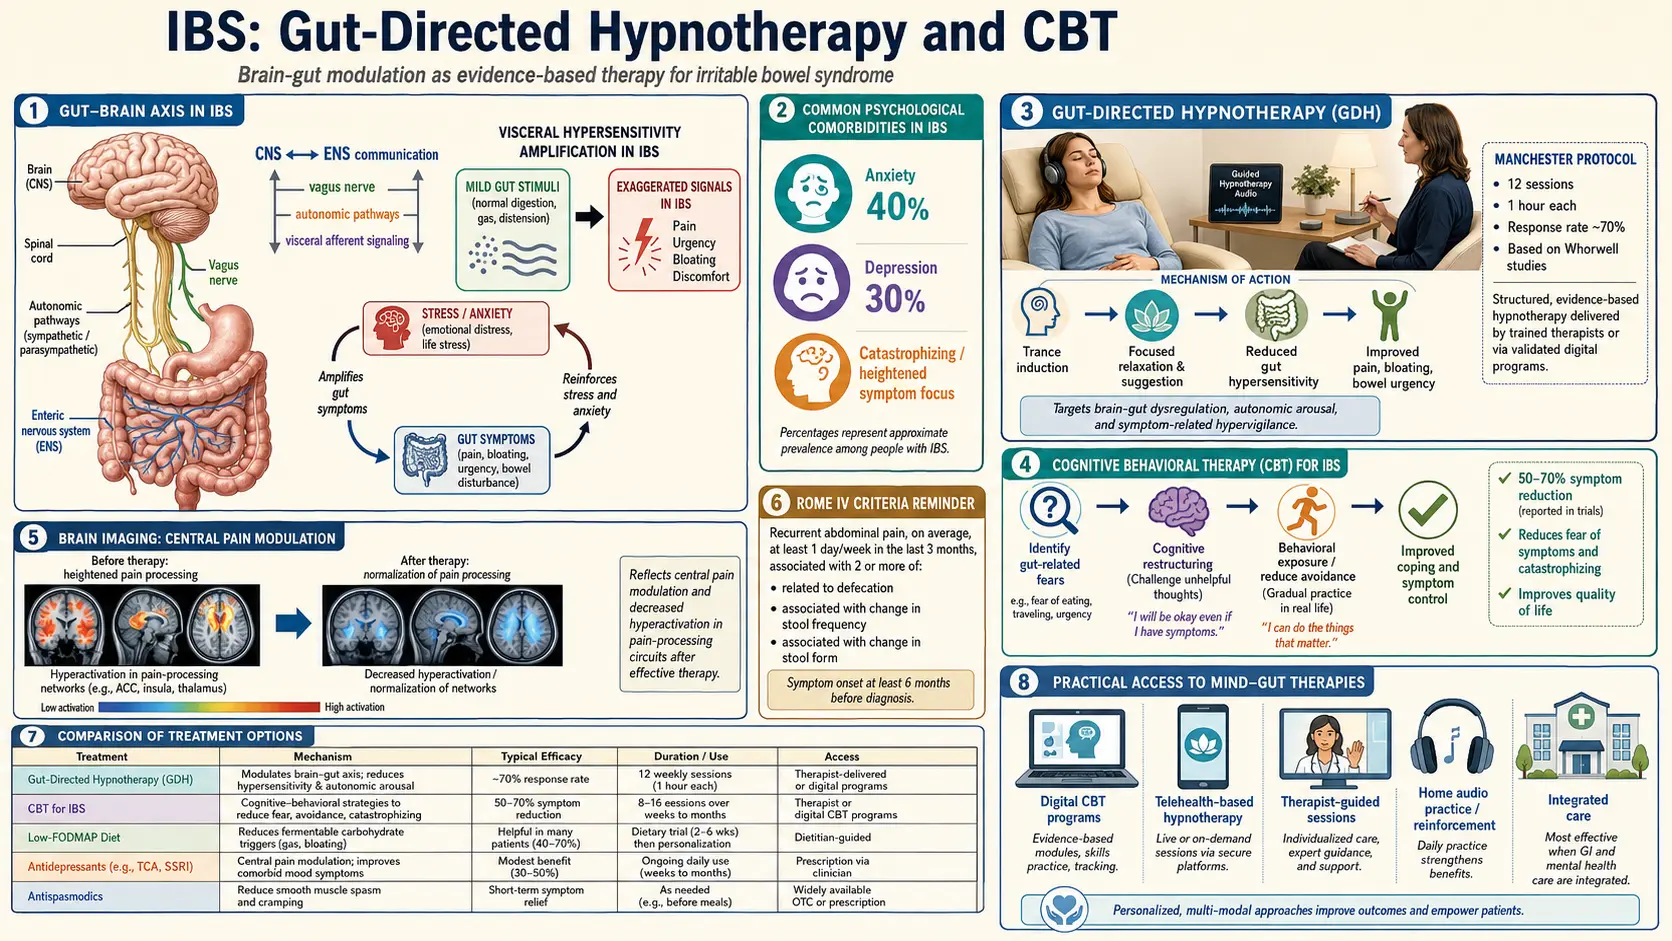
Table of Contents
- Why Mind-Body Therapies Actually Work for Irritable Bowel Syndrome
- The Manchester Protocol (Peter Whorwell)
- The North Carolina Protocol (Olafur Palsson)
- App-Based Delivery
- Finding an In-Person Provider
- Cognitive Behavioral Therapy for Irritable Bowel Syndrome — Not Generic Therapy
- Mindfulness-Based Stress Reduction and Yoga
- Low-Dose Tricyclic Antidepressants as Neuromodulators
- Insurance, HSA, and the Real Cost Picture
- Combining With Diet and Medication
- Realistic Expectations and Time Investment
- When It Doesn't Work — and Why
- Key Research Papers
- Connections
- Featured Videos
Why Mind-Body Therapies Actually Work for Irritable Bowel Syndrome
Hearing "it's stress" from a doctor is usually code for "I can't help you, now please leave." That is not what this article is about. Gut-directed hypnotherapy and cognitive behavioral therapy (CBT) are not generic relaxation. They are specific, evidence-based, outcome-measured treatments for the exact neurobiology that is broken in irritable bowel syndrome (IBS).
To understand why, start with the problem. In irritable bowel syndrome, the nerves lining the gut are turned up too loud. Normal amounts of gas, normal stretch from a meal, normal peristalsis — sensations a healthy person never notices — register as pain, cramping, bloating, or urgency. This is called visceral hypersensitivity, and it is the subject of a sibling article (Visceral Hypersensitivity and the Brain-Gut Axis) that pairs with this one. The volume knob lives partly in the gut wall and partly in the spinal cord and brainstem, where signals from the gut are interpreted, amplified, or dampened before they ever reach conscious awareness. This amplifier is called central sensitization, and it is the same mechanism driving fibromyalgia, migraine, and chronic pelvic pain.
Gut-directed hypnotherapy works on that amplifier directly. Functional magnetic resonance imaging (fMRI) studies show that hypnosis reduces activity in the anterior cingulate cortex and insula — the brain regions that convert gut signals into the conscious experience of pain. It increases vagal tone, the parasympathetic "rest and digest" signal that slows heart rate, relaxes gut smooth muscle, and down-regulates inflammatory cytokines. It shifts the autonomic nervous system out of the sympathetic "fight or flight" state that amplifies gut sensation and speeds or spasms motility. In measurable, repeatable, imaging-confirmed ways, it rewires the volume knob.
Cognitive behavioral therapy works on a parallel axis. It does not claim the symptoms are imaginary. It targets the secondary layer of the disease — the fear of symptoms, the avoidance behaviors (skipping meals, canceling plans, mapping every bathroom), the catastrophic thoughts ("this pain means cancer, I need to leave") — that feed back into the nervous system and keep it sensitized. Calming those loops reliably reduces the primary symptoms too, because the gut and brain really are one circuit.
The Manchester Protocol (Peter Whorwell)
The entire modern field of gut-directed hypnotherapy traces back to one gastroenterologist: Peter Whorwell, who started treating irritable bowel syndrome patients with hypnosis at the University of Manchester in the early 1980s because he was running out of options for the severely ill people on his ward. His 1984 paper in The Lancet was the first randomized controlled trial of hypnosis for any gastrointestinal condition. In that trial of 30 patients with severe, treatment-resistant irritable bowel syndrome, the comparison group given psychotherapy and placebo improved slightly in abdominal pain, abdominal swelling and general well-being but not in bowel habit, while the hypnotherapy group improved dramatically in all features.
The Manchester protocol is tight and reproducible:
- Seven sessions, each about 30 minutes, spaced one to two weeks apart over roughly three months.
- Each session begins with a progressive relaxation induction, then moves into gut-specific imagery. The most famous image is a gentle river flowing smoothly through the gut, warming, soothing, and normalizing its movement. Other sessions use hand-warmth imagery transferred to the abdomen, or the metaphor of a protective shield around hypersensitive nerves.
- Patients receive an audio recording of each session and practice daily self-hypnosis at home for 15 to 20 minutes between appointments. The home practice is where most of the work happens.
Manchester's published response rates run 70 to 80 percent for meaningful symptom improvement — at least a 50 percent reduction in pain, bloating, and bowel dysfunction. Manchester’s long-term follow-up of 204 patients (Gonsalkorale and colleagues, 2003) found that 71 percent responded at first and 81 percent of those responders kept their improvement, with benefits that appeared to last at least five years. A Swedish study by Lindfors and colleagues (2012), looking back at 208 patients treated outside specialist centres, found that 49 percent responded immediately and 73 percent of those responders had improved further at follow-up 2 to 7 years later (mean 4 years); 73 percent of the responders were still using hypnotherapy regularly. No irritable bowel syndrome medication on the market can claim that durability.
The North Carolina Protocol (Olafur Palsson)
The Manchester approach was hard to export because it required training under Whorwell's team. In the early 2000s, Icelandic psychologist Olafur Palsson, working at the University of North Carolina, built a scripted, manualized version designed to be delivered by any trained clinician while preserving the same clinical results.
The North Carolina protocol is also seven sessions, also 30 to 40 minutes each, but it runs off written scripts. Any licensed mental health professional or certified hypnotherapist can follow the manual. This mattered enormously for access: suddenly a therapy that required flying to Manchester was available in clinics, hospitals, and eventually homes across the U.S. Trials of the Palsson scripts have replicated the Manchester-style response rates of around 70 percent, with benefits durable at one to three years.
The North Carolina protocol is also the backbone of every app-based hypnotherapy program on the market. When people use one of these apps, they are hearing, in effect, a voice-acted and updated version of Palsson's scripts — lightly rewritten, professionally produced, and delivered on a phone instead of a clinician's couch.
App-Based Delivery
Many people cannot find a trained gut-directed hypnotherapist within 200 miles of home, and apps have closed part of that gap. The programs fall into three kinds:
Self-guided gut-directed hypnotherapy apps
One such app was developed in Australia with researchers at Monash University (the team that created the Low-FODMAP diet): daily hypnosis sessions, education modules, and a simple symptom tracker, sold without a prescription on iOS and Android. A 2023 retrospective evaluation by Peters and colleagues in Neurogastroenterology & Motility followed people with self-reported irritable bowel syndrome who started it: of 2,843 who began the free first sessions, 253 (9 percent) completed all 42 sessions, and 64 percent of the 190 completers with outcome data responded (a fall of more than 30 percent in abdominal pain). The authors described adherence as low and called for a controlled trial comparing app and face-to-face delivery.
Prescription digital therapeutics (FDA-cleared)
Two prescription-only programs for adults 22 and older with irritable bowel syndrome are regulated by the U.S. Food and Drug Administration (FDA) as medical devices, both intended to be used together with other IBS treatments. A doctor writes the prescription.
- A cognitive behavioral therapy program, not hypnotherapy, authorized through the FDA De Novo route in 2020: a three-month structured course built around cognitive restructuring, behavioral experiments, and symptom-exposure work.
- A gut-directed hypnotherapy app, not cognitive behavioral therapy, cleared through the FDA 510(k) route in 2021 as a three-month treatment for abdominal pain due to IBS: seven sessions of about 30 minutes, built on the Palsson North Carolina scripts and delivered through a voice-guided mobile interface.
Cash prices without insurance run to hundreds of dollars; a growing but still limited set of commercial insurers cover them.
Self-guided cognitive behavioral therapy apps
Other cognitive behavioral therapy-based apps are sold direct-to-consumer without a prescription, with a broader stress-and-IBS curriculum and a lower price point; their evidence base is lighter than that of the prescription programs.
On cost, the self-guided apps are the cheapest of these routes. The prescription programs need a prescription, and whether they are covered depends on the insurer.
Finding an In-Person Provider
Some people prefer a human therapist. These directories list them:
- American College of Gastroenterology (ACG) patient resources — a provider finder for gastrointestinal (GI) behavioral health clinicians, most of whom are Ph.D. psychologists trained in both cognitive behavioral therapy-for-IBS and gut-directed hypnotherapy.
- A patient organisation’s registry — a patient-run list of clinicians across the U.S., U.K., and Australia with specific gut-directed hypnotherapy training.
- The American Society of Clinical Hypnosis (ASCH) member directory lists certified hypnotherapists, but most are not gut-specialized. Two questions that sort them are whether they use the Palsson North Carolina irritable bowel syndrome protocol and roughly how many irritable bowel syndrome patients they have treated; a gut-specialized practitioner has usually treated hundreds.
Session costs run in the range of $150 to $250 per visit for a Ph.D. psychologist in a major U.S. city, less in smaller markets. The full seven-session course runs roughly $1,000 to $1,800 out of pocket — comparable to one month of rifaximin without insurance and with durability measured in years rather than weeks.
Cognitive Behavioral Therapy for Irritable Bowel Syndrome — Not Generic Therapy
"I tried therapy and it didn't help my gut" is a common complaint. Often what the person tried was generic supportive talk therapy, which is a fine thing but is not the same intervention as cognitive behavioral therapy for irritable bowel syndrome. The protocols differ in three specific ways.
Cognitive restructuring around symptom catastrophizing. Irritable bowel syndrome patients often run automatic thoughts like "this cramp means I'm about to have an accident in public" or "if I eat at the restaurant I will be sick for three days." cognitive behavioral therapy-for-IBS identifies these thoughts, tests them against actual evidence from the patient's own symptom diary, and teaches more accurate replacements. Over weeks, the catastrophic framing fades, and the autonomic arousal that was feeding the symptoms fades with it.
Behavioral experiments to test feared outcomes. A patient who has been avoiding restaurants for eight years believes, deep down, that restaurants cause flares. The therapist designs a graded test — first a coffee at a cafe, then a small snack, then a planned meal with a safe menu item — and the patient collects data. Most of the predicted disasters do not happen. The brain learns this, slowly, through lived experience. Reassurance alone does not accomplish this; the data collection does.
Gradual exposure to avoided foods and situations. Many irritable bowel syndrome patients develop progressively restrictive diets and shrinking social lives that they recognize are disproportionate but cannot override alone. Exposure work reintroduces tolerable items one at a time, in a planned, paced way, while the hypersensitivity and anxiety are being treated in parallel. This layer is critical in the subset of patients whose irritable bowel syndrome has blurred into avoidant/restrictive food intake disorder (ARFID).
Laird and colleagues published a 2016 meta-analysis in Clinical Gastroenterology and Hepatology pooling 41 trials of psychological therapies for irritable bowel syndrome, cognitive behavioral therapy among them (2,290 people), and found a medium effect on gut symptom severity immediately after treatment (d = 0.69) that stayed medium at 1 to 6 months (0.76) and at 6 to 12 months (0.73).
Mindfulness-Based Stress Reduction and Yoga
Mindfulness-Based Stress Reduction (MBSR), the eight-week program developed by Jon Kabat-Zinn, has modest but real evidence in irritable bowel syndrome. Trials generally show roughly 30 to 40 percent improvement in symptom severity scores — smaller than gut-directed hypnotherapy, but meaningful, and MBSR courses are widely available through hospital wellness programs, often for $200 to $400 or sometimes free through insurance wellness benefits. It is a mind-body option for people who cannot reach the specialized irritable bowel syndrome protocols.
Yoga has a surprisingly respectable irritable bowel syndrome evidence base. Kavuri and colleagues (2015) wrote a narrative review that proposes a yoga module for irritable bowel syndrome built on traditional yoga concepts; among the studies it describes, a trial of Iyengar yoga in 51 adolescents and young adults (six weeks of two 90-minute classes a week) reported improvements in symptoms, sleep, fatigue and psychological distress compared with usual care. The mechanism is presumed to overlap with MBSR — vagal-tone elevation, parasympathetic shift, interoceptive awareness. Two to three sessions per week for eight to twelve weeks is the dosing used in most trials.
Neither MBSR nor yoga replace gut-directed hypnotherapy as the evidence leader, but both are cheap, side-effect-free, and stack well with everything else.
Low-Dose Tricyclic Antidepressants as Neuromodulators
Low-dose tricyclic antidepressants (TCAs) — amitriptyline, nortriptyline, desipramine at doses of 10 to 50 mg at bedtime — are among the most effective pharmacologic treatments for irritable bowel syndrome, and they operate on the same central-sensitization target as hypnotherapy and cognitive behavioral therapy. The dose used is well below the antidepressant range; the mechanism here is pure neuromodulation of visceral pain signaling in the spinal cord and brainstem.
Clinically, tricyclic antidepressants pair well with behavioral therapy rather than competing with it. One sequence described for painful diarrhea-predominant irritable bowel syndrome (IBS-D) starts low-dose nortriptyline or amitriptyline for faster symptom relief (within two to four weeks), begins gut-directed hypnotherapy at the same time (it takes 8 to 12 weeks to show full effect), and tapers the TCA slowly once the hypnotherapy gains consolidate. Full dosing details and side-effect trade-offs are covered in the sibling article irritable bowel syndrome Medications Guide.
Insurance, HSA, and the Real Cost Picture
The infuriating truth: insurance coverage for gut-directed hypnotherapy and cognitive behavioral therapy-for-IBS is spotty and varies wildly by plan. Commercial insurance sometimes covers sessions with a Ph.D. psychologist if coded under a mental health diagnosis (common codes: F45.8 other somatoform disorders, F41.1 generalized anxiety disorder). Medicare covers psychotherapy but not always hypnotherapy specifically. The two prescription digital therapeutics are increasingly reimbursed since they carry U.S. Food and Drug Administration device clearance, but still denied by many plans.
Two workarounds that consistently help:
- HSA and FSA accounts. App-based programs, self-guided or prescribed, are reliably HSA/FSA-eligible. You can pay with pre-tax dollars even if your insurer is refusing. For a $150 app subscription at a 30 percent marginal tax rate, the effective cost drops to about $105.
- Superbilling. Many gastrointestinal psychologists do not take insurance directly but will provide a detailed receipt (superbill) that you submit to your plan for out-of-network reimbursement. A patient with 40 percent out-of-network coverage can often recover several hundred dollars of a seven-session course.
For comparison, a year of rifaximin rescue courses, hyoscyamine, probiotics, missed workdays, and peppermint capsules can easily exceed the cost of a full in-person hypnotherapy course that durably reduces symptoms for five-plus years.
Combining With Diet and Medication
The best-studied combination is low-FODMAP diet plus gut-directed hypnotherapy. Peters and colleagues ran a randomized trial of 74 patients directly comparing hypnotherapy, the diet and the two combined: each produced about a 70 percent response rate at six weeks (72, 71 and 72 percent), with no difference between the groups and similar quality-of-life improvement; six months after treatment the improvement held in 74, 82 and 54 percent. The authors concluded that no additive effects were observed; hypnotherapy improved anxiety and depression scores more than the diet. See the sibling article Low-FODMAP Diet for irritable bowel syndrome for the full protocol.
Medication is also combined with these therapies. Linaclotide, lubiprostone, or low-dose tricyclic antidepressants paired with hypnotherapy or cognitive behavioral therapy often allow medication doses to drop over time, and some patients ultimately taper off the drug entirely once the behavioral gains consolidate. Peppermint oil capsules (see Peppermint, Probiotics, and Herbals) layer in without any known interaction.
Realistic Expectations and Time Investment
Selling these therapies honestly means being clear about what they do and do not deliver.
- Meaningful improvement, not cure. Roughly 60 to 70 percent of patients who complete a full course experience at least 50 percent symptom reduction. A smaller fraction (maybe 20 to 30 percent) experience near-complete remission. A stubborn minority get little or no benefit.
- Time investment is real. Durable change typically takes 6 to 12 weeks to appear, with daily practice of 15 to 30 minutes during that window. Unlike a pill, you cannot shortcut the dosing.
- Durability is the single biggest advantage. In follow-ups of up to five years, most hypnotherapy responders kept their gains. Most drugs fade within weeks of stopping.
- The placebo response in irritable bowel syndrome is high (around 30 to 40 percent), but hypnotherapy trials consistently beat that baseline by a wide margin. Skepticism is healthy; the evidence is strong enough to overrule it.
When It Doesn't Work — and Why
A subset of patients go through the full protocol and get little benefit. In almost every case, one of four specific situations is in play:
- Severe untreated small intestinal bacterial overgrowth (SIBO). Small intestinal bacterial overgrowth generates real, ongoing gas, bloating, and motility dysfunction that no amount of nervous-system calming will fix until the bacterial load is reduced. Where bloating is the dominant symptom, small intestinal bacterial overgrowth is usually checked for first (see irritable bowel syndrome and small intestinal bacterial overgrowth Overlap).
- Missed inflammatory bowel disease (IBD). Crohn's and ulcerative colitis can masquerade as irritable bowel syndrome for years. Blood in the stool, diarrhea at night, unexplained weight loss, iron-deficiency anemia, or a raised fecal calprotectin are warning signs that point away from irritable bowel syndrome, and the behavioral therapies do not treat inflammatory bowel disease; colonoscopy is the test that looks for it.
- Untreated pelvic floor dysfunction. A tight, uncoordinated pelvic floor produces constipation, incomplete evacuation, and a sensation of obstruction that hypnotherapy does not treat. Anorectal manometry and pelvic-floor physical therapy come before mind-body work for this subgroup.
- Severe untreated anxiety, depression, or trauma. Irritable bowel syndrome-specific cognitive behavioral therapy is not a substitute for primary mental health treatment when a patient is in a major depressive episode, has active post-traumatic stress disorder (PTSD), or has untreated panic disorder. The usual sequence is treatment of the primary psychiatric condition first (medication, trauma-focused therapy, psychiatric care), then the gut-directed layer once the baseline is stabilized. See Anxiety and Depression.
If none of these apply and the therapy still does not work, that is a small but real group — roughly 20 to 30 percent of irritable bowel syndrome patients — for whom medication and diet remain the mainstays. That is not a failure of the patient; it is biological variability in a disease that is still not fully understood.
Key Research Papers
- Whorwell PJ, Prior A, Faragher EB. Controlled trial of hypnotherapy in the treatment of severe refractory irritable-bowel syndrome. Lancet. 1984;2(8414):1232-1234. — doi:10.1016/s0140-6736(84)92793-4
- Lindfors P, Unge P, Nyhlin H, Ljótsson B, Björnsson ES, Abrahamsson H, Simrén M. Long-term effects of hypnotherapy in patients with refractory irritable bowel syndrome. Scand J Gastroenterol. 2012;47(4):414-420. — doi:10.3109/00365521.2012.658858
- Peters SL, Yao CK, Philpott H, Yelland GW, Muir JG, Gibson PR. Randomised clinical trial: the efficacy of gut-directed hypnotherapy is similar to that of the low FODMAP diet for the treatment of irritable bowel syndrome. Aliment Pharmacol Ther. 2016;44(5):447-459. — doi:10.1111/apt.13706
- Laird KT, Tanner-Smith EE, Russell AC, Hollon SD, Walker LS. Short-term and long-term efficacy of psychological therapies for irritable bowel syndrome: a systematic review and meta-analysis. Clin Gastroenterol Hepatol. 2016;14(7):937-947.e4. — doi:10.1016/j.cgh.2015.11.020
- Gonsalkorale WM, Miller V, Afzal A, Whorwell PJ. Long term benefits of hypnotherapy for irritable bowel syndrome. Gut. 2003;52(11):1623-1629. — PubMed PMID: 14570733
- Peters SL, Gibson PR, Halmos EP. Smartphone app-delivered gut-directed hypnotherapy improves symptoms of self-reported irritable bowel syndrome: A retrospective evaluation. Neurogastroenterol Motil. 2023;35(4):e14533. — PubMed PMID: 36661117
- Kavuri V, Raghuram N, Malamud A, Selvan SR. Irritable Bowel Syndrome: Yoga as Remedial Therapy. Evid Based Complement Alternat Med. 2015;2015:398156. — PubMed PMID: 26064164
PubMed Topic Searches
For further reading, the following PubMed topic searches return current peer-reviewed work on gut-directed behavioral therapies for irritable bowel syndrome:
- PubMed: Gut-directed hypnotherapy for IBS
- PubMed: Manchester protocol and the Whorwell trials
- PubMed: Palsson North Carolina hypnotherapy scripts
- PubMed: Cognitive behavioral therapy for IBS
- PubMed: App-delivered hypnotherapy for IBS
- PubMed: Mindfulness-Based Stress Reduction and IBS
- PubMed: Yoga for IBS
- PubMed: Central sensitization and visceral pain in IBS
- PubMed: Vagal tone and the brain-gut axis
- PubMed: Low-dose tricyclic antidepressants in IBS
Connections
- Gastroenterology
- The Gut Barrier & Your Microbiome — interactive animation
- Irritable Bowel Syndrome
- Irritable Bowel Syndrome and Small Intestinal Bacterial Overgrowth Overlap
- Irritable Bowel Syndrome Medications Guide
- Low-FODMAP Diet for Irritable Bowel Syndrome
- Visceral Hypersensitivity and Brain-Gut Axis
- Peppermint, Probiotics, and Herbals
- Post-Infectious Irritable Bowel Syndrome
- Rome IV Subtypes
- Bile Acid Malabsorption
- Anxiety
- Depression
- Fibromyalgia
- Central Sensitization
- Chronic Pain
- Stress Management
- Gut-Brain Axis
- Small Intestinal Bacterial Overgrowth
- Bloating