Diabetes Disease
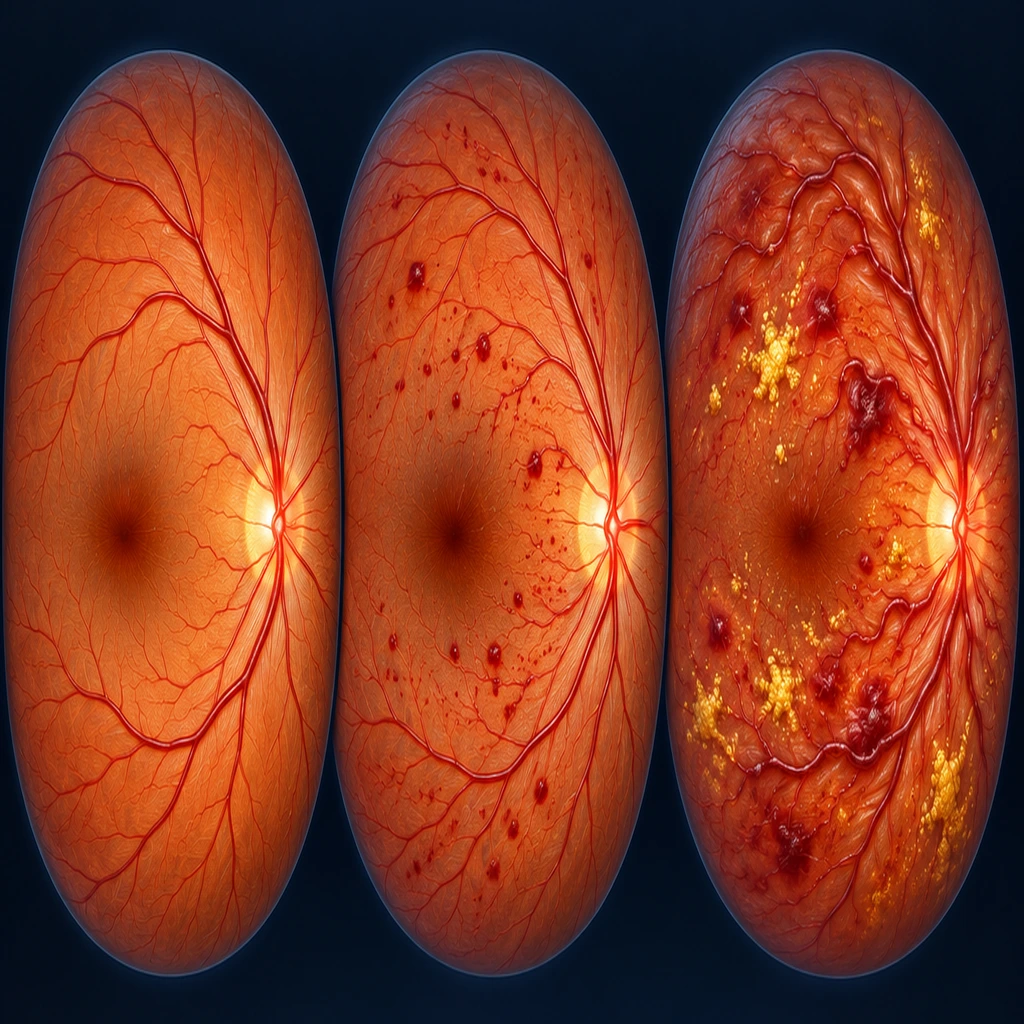
How Diabetes Affects the Body
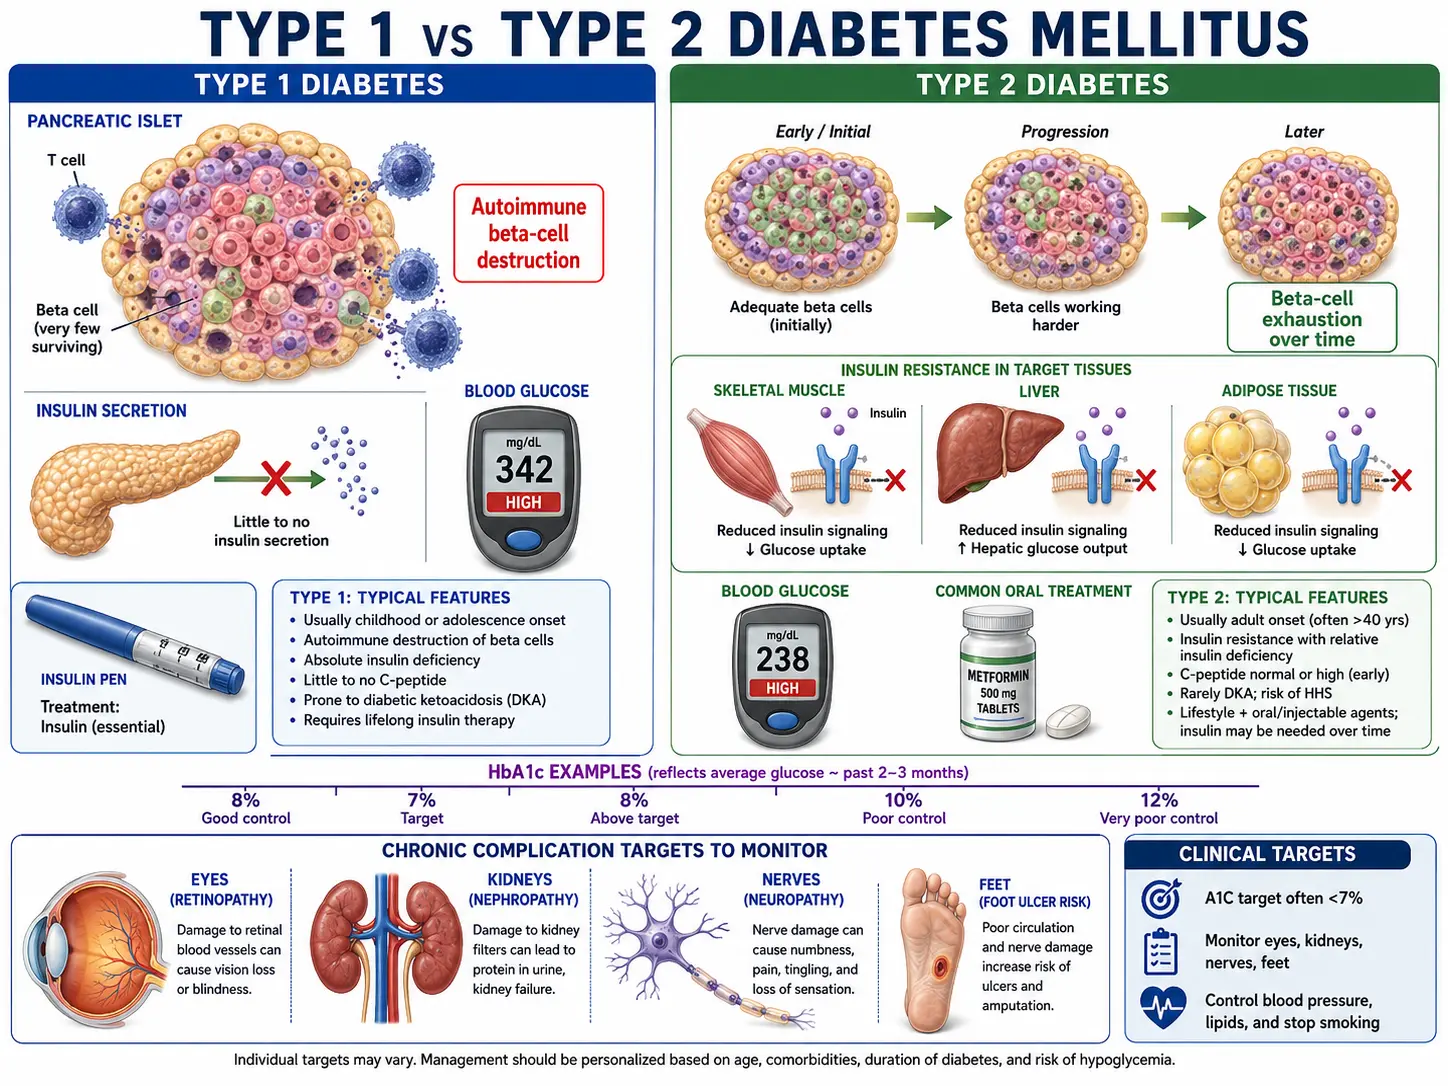
Diabetes is a chronic health condition that affects how your body turns food into energy. It occurs when your blood glucose (blood sugar) is too high.
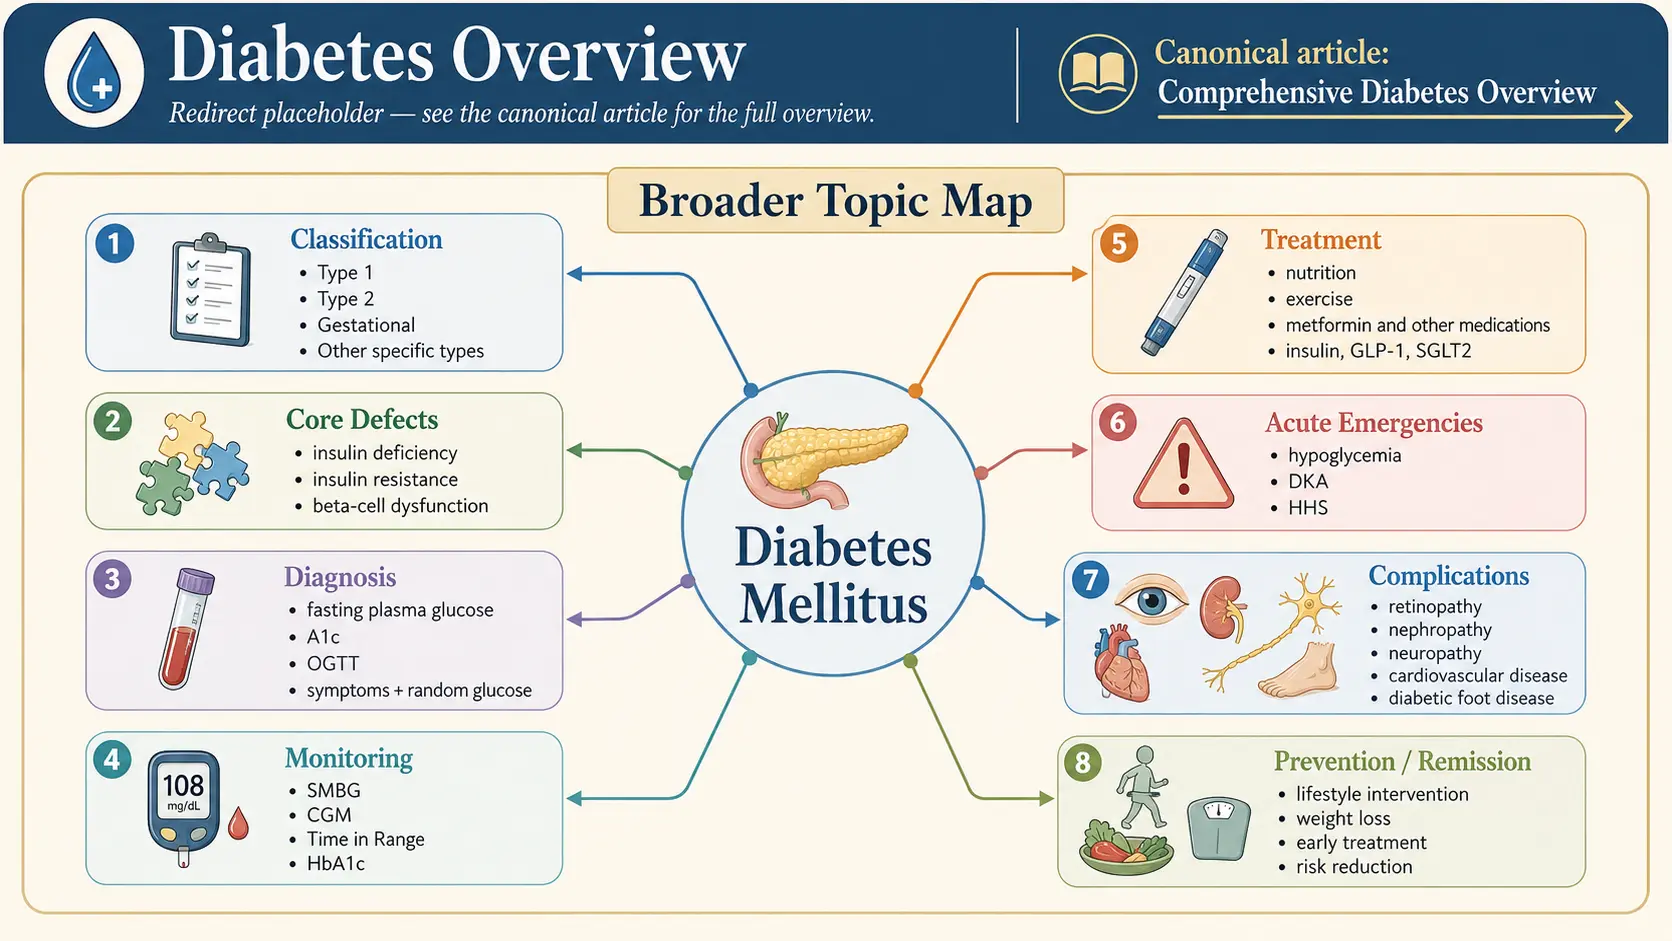
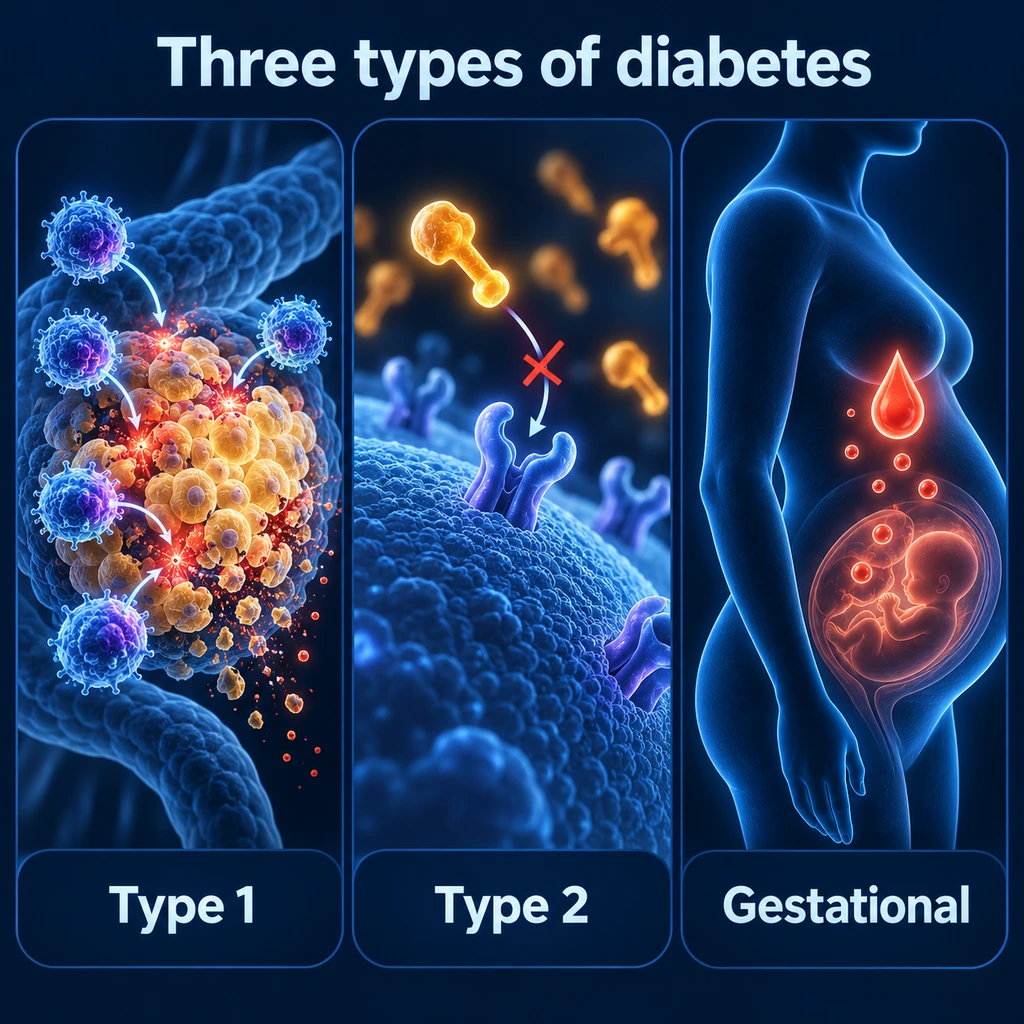
Types of Diabetes
1. Type 1 Diabetes
- Autoimmune condition: The immune system attacks and destroys insulin-producing cells in the pancreas.
- Insulin-dependent: Patients need to take insulin regularly.
- Commonly diagnosed in children and young adults.
2. Type 2 Diabetes
- Most common type: Represents the majority of diabetes cases.
- Insulin resistance: The body does not use insulin properly.
- Risk factors: Obesity, sedentary lifestyle, genetics, and age.
3. Gestational Diabetes
- Occurs during pregnancy: Can develop in women who did not previously have diabetes.
- Usually temporary: Typically resolves after childbirth, but increases the risk of developing type 2 diabetes later.
Symptoms of Diabetes
- Frequent urination
- Increased thirst
- Unexplained weight loss
- Fatigue
- Blurred vision
- Slow-healing sores
Diagnosis Numbers and Emergency Warning Signs
The American Diabetes Association’s Standards of Care (2025) diagnose diabetes outside pregnancy with any one of these results: a fasting blood sugar (fasting plasma glucose, after at least 8 hours without food) of 126 mg/dL (7.0 mmol/L) or higher; a hemoglobin A1c of 6.5% or higher; a blood sugar of 200 mg/dL (11.1 mmol/L) or higher two hours into a 75-gram glucose drink test (oral glucose tolerance test); or, in someone with the classic symptoms above or a high-blood-sugar crisis, a blood sugar of 200 mg/dL or higher at any time of day. Without clearly high blood sugar, the ADA requires two abnormal results to confirm the diagnosis.
Diabetic ketoacidosis (DKA) happens when insulin is so low that the body breaks down fat too fast and acids called ketones build up in the blood. The U.S. National Library of Medicine’s MedlinePlus describes it as a life-threatening medical emergency. Its signs include deep, rapid breathing; fruity-smelling breath; nausea and vomiting; stomach pain; thirst or frequent urination lasting a day or more; a flushed face; dry skin and mouth; headache; and decreased alertness. MedlinePlus lists decreased consciousness, fruity breath, nausea and vomiting, and trouble breathing as reasons to go to an emergency room.
Low blood sugar (hypoglycemia) is the most common side effect of insulin. The U.S. label for insulin glargine states that severe low blood sugar can cause seizures and may be life-threatening, and lists these signs: dizziness or light-headedness, sweating, confusion, headache, blurred vision, slurred speech, shakiness, fast heartbeat, anxiety, irritability or mood change, and hunger.
Causes and Risk Factors
- Genetics: Family history increases the likelihood.
- Lifestyle factors: Diet, physical inactivity, and obesity contribute to type 2 diabetes.
- Autoimmune response: Causes type 1 diabetes when the immune system mistakenly attacks insulin-producing cells.
Management and Treatment
Type 1 Diabetes
- Insulin therapy: Essential for survival.
- Blood sugar monitoring: Regular checks to manage levels.
- Healthy diet and exercise: Supports overall health.
Type 2 Diabetes
- Lifestyle changes: Diet, exercise, and weight management.
- Medications: Oral drugs or insulin may be needed.
- Monitoring blood glucose: Helps in adjusting treatment.
Gestational Diabetes
- Special meal plans and regular physical activity.
- Monitoring blood sugar to prevent complications.
Complications of Diabetes
- Cardiovascular disease: Increased risk of heart attack and stroke.
- Nerve damage (neuropathy): Can cause pain and numbness.
- Kidney damage (nephropathy): Potential kidney failure.
- Eye damage: Risk of blindness due to retinopathy.
- Foot damage: Poor blood flow and neuropathy can lead to amputations.
Key Research Papers
Historical Background
Diabetes has been known since antiquity — the term "diabetes" was coined by the Greek physician Aretaeus of Cappadocia in the 2nd century AD. The distinction between type 1 and type 2 diabetes was established by Harold Himsworth in 1936. The discovery of insulin by Frederick Banting, working with Charles Best, in 1921 at the University of Toronto remains one of the most transformative breakthroughs in medical history. The 1923 Nobel Prize went to Banting and John Macleod, in whose laboratory the work was done; Banting shared his prize money with Best, and Macleod shared his with James Collip, who purified the extract (Rydén 2021).
- The Diabetes Control and Complications Trial Research Group. The effect of intensive treatment of diabetes on the development and progression of long-term complications in insulin-dependent diabetes mellitus. N Engl J Med. 1993;329(14):977-986. — doi:10.1056/NEJM199309303291401
- UK Prospective Diabetes Study (UKPDS) Group. Intensive blood-glucose control with sulphonylureas or insulin compared with conventional treatment and risk of complications in patients with type 2 diabetes (UKPDS 33). Lancet. 1998;352(9131):837-853. — doi:10.1016/S0140-6736(98)07019-6
- ADVANCE Collaborative Group, Patel A, MacMahon S, Chalmers J, et al. Intensive blood glucose control and vascular outcomes in patients with type 2 diabetes. N Engl J Med. 2008;358(24):2560–72. — PubMed PMID: 18539916
- Zinman B, Wanner C, Lachin JM, et al. Empagliflozin, cardiovascular outcomes, and mortality in type 2 diabetes (EMPA-REG OUTCOME). N Engl J Med. 2015;373(22):2117-2128. — doi:10.1056/NEJMoa1504720
- Marso SP, Daniels GH, Brown-Frandsen K, et al. Liraglutide and Cardiovascular Outcomes in Type 2 Diabetes (LEADER). N Engl J Med. 2016;375(4):311–22. — PubMed PMID: 27295427
- Knowler WC, Barrett-Connor E, Fowler SE, et al. Reduction in the incidence of type 2 diabetes with lifestyle intervention or metformin (Diabetes Prevention Program). N Engl J Med. 2002;346(6):393-403. — doi:10.1056/NEJMoa012512
- American Diabetes Association Professional Practice Committee. 2. Diagnosis and Classification of Diabetes: Standards of Care in Diabetes-2025. Diabetes Care. 2025;48(1 Suppl 1):S27–S49. — PubMed PMID: 39651986
- Neal B, Perkovic V, Mahaffey KW, et al. Canagliflozin and cardiovascular and renal events in type 2 diabetes (CANVAS Program). N Engl J Med. 2017;377(7):644-657. — doi:10.1056/nejmoa1611925
- Tuomilehto J, Lindstrom J, Eriksson JG, et al. Prevention of type 2 diabetes mellitus by changes in lifestyle among subjects with impaired glucose tolerance (Finnish Diabetes Prevention Study). N Engl J Med. 2001;344(18):1343-1350. — doi:10.1056/NEJM200105033441801
- Inzucchi SE, Bergenstal RM, Buse JB, et al. Management of hyperglycemia in type 2 diabetes, 2015: a patient-centered approach: update to a position statement of the American Diabetes Association and the European Association for the Study of Diabetes. Diabetes Care. 2015;38(1):140–9. — PubMed PMID: 25538310
- NCD Risk Factor Collaboration (NCD-RisC). Worldwide trends in diabetes since 1980: a pooled analysis of 751 population-based studies with 4.4 million participants. Lancet. 2016;387(10027):1513–1530. — PubMed PMID: 27061677
- Gerstein HC, Colhoun HM, Dagenais GR, et al. Dulaglutide and cardiovascular outcomes in type 2 diabetes (REWIND). Lancet. 2019;394(10193):121-130. — PubMed PMID: 31189511
- Rydén L, Lindsten J. The history of the Nobel prize for the discovery of insulin. Diabetes Res Clin Pract. 2021;175:108819. — PubMed PMID: 33865917
PubMed Topic Searches
The following PubMed topic searches aggregate the current peer-reviewed literature. Each link opens a live PubMed query — results update as new studies are indexed.
- PubMed: Diabetes mellitus type 2
- PubMed: Type 1 diabetes
- PubMed: HbA1c glycemic control
- PubMed: Metformin type 2 diabetes
- PubMed: GLP-1 receptor agonist
- PubMed: SGLT2 inhibitor
- PubMed: Diabetic retinopathy
- PubMed: Diabetic nephropathy
- PubMed: Diabetic neuropathy
- PubMed: Insulin therapy diabetes
- PubMed: Continuous glucose monitoring
- PubMed: Diabetes lifestyle intervention
Deep-Dive Articles
Type 1 vs Type 2 vs LADA & MODY
Autoimmune T1D, insulin-resistant T2D, slowly-progressing LADA, and monogenic MODY — how to tell them apart and why misdiagnosis is common in adults.
Read the deep dive →Hemoglobin A1c, Fructosamine & Glycation
What hemoglobin A1c (HbA1c) actually measures, when it lies (anemia, pregnancy, hemoglobinopathies), fructosamine as a 2-3 week alternative, and the glycation-marker landscape.
Read the deep dive →CGM & Time-in-Range
Time-in-range (70-180) as the modern gold standard, GMI vs hemoglobin A1c, ambulatory glucose profile interpretation, and the main device types (continuous glucose monitors and automated insulin-delivery pumps).
Read the deep dive →Insulin Types & Dosing
Basal, bolus, pre-mixed, ultra-rapid; basal-bolus vs pump therapy; carb counting, correction factors, insulin-to-carb ratios, and the closed-loop pump systems.
Read the deep dive →Cardio-Renal Protection: SGLT2s & Glucagon-Like Peptide-1 Receptor Agonists
EMPA-REG, DAPA-HF, CREDENCE, FLOW, LEADER, SELECT — why these drugs' benefits extend beyond glucose and have reshaped diabetes guidelines.
Read the deep dive →Remission & Reversal
DiRECT trial, a commercial low-carbohydrate program’s 2-year ketogenic-diet data, bariatric-surgery remission, early-intensive-insulin, time-restricted eating. When remission is realistic and how to hold it.
Read the deep dive →Complications: Eye, Kidney, Nerve
Annual dilated eye exam, UACR and estimated glomerular filtration rate (eGFR), monofilament and vibration testing, autonomic neuropathy. Screening cadence, prevention, and the drugs that slow progression.
Read the deep dive →Hypoglycemia & Awareness
Recognizing lows, hypoglycemia unawareness, the rule of 15, glucagon (nasal glucagon, glucagon injection), nocturnal lows, dead-in-bed syndrome, and awareness restoration.
Read the deep dive →Diabetic Foot Care & Ulcer Prevention
Monofilament testing, ABI screening, offloading, and when to refer to wound care.
Read the deep dive →Table of Contents
Connections
- Endocrinology
- Retinal Imaging — the ADA Standards of Care call for a first eye exam at diagnosis of type 2 diabetes (within 5 years of onset in type 1), generally yearly exams after that, and accept retinal-photography screening programs
- Frederick Banting — the Nobel laureate who co-discovered insulin in 1921-22
- Glycation & Hemoglobin A1c: What That Number Actually Measures — interactive animation
- How the Liver Keeps Your Blood Sugar Steady — interactive animation
- Sodium-Glucose Cotransporter-2: Why Diabetes Drugs Make You Pee Sugar — interactive animation
- Blood pH: The Acid–Base Balancing Act — interactive animation
- Blood Sugar & Insulin — interactive animation
- Type 2 Diabetes
- Diabetic Kidney Disease
- Lactulose & Blood Sugar — Emerging Research (In-Depth)
- Beans for Blood Sugar & Diabetes
- Hemoglobin A1c, Fructosamine, and Glycation Markers
- CGM and Time-in-Range
- Cardio-Renal Protection: Sodium-Glucose Cotransporter-2 and Glucagon-Like Peptide-1
- Complications: Retinopathy, Nephropathy, Neuropathy
- Diabetic Foot Care and Ulcer Prevention
- Hypoglycemia Awareness and Prevention
- Insulin Types and Dosing Strategies
- Remission and Reversal Strategies
- Type 1 vs Type 2 vs LADA and MODY
- Insulin Resistance
- Obesity
- Metabolic Syndrome
- Hashimoto's Thyroiditis
- Chromium
- Magnesium
- Vitamin D3
- Gestational Diabetes
- Diabetes Insipidus
- Pancreatic Cancer
- Gum Disease
- Diabetic Retinopathy
- Frozen Shoulder
- Yeast Infections
- Salt in Socks — a popular foot remedy that violates standard diabetic foot-care guidance
- Herbs covered on this site that discuss this condition: Bitter Melon (Momordica charantia) · Gymnema (Gymnema sylvestre) · Berberine (Berberis & Coptis spp.) · Cinnamon (Cinnamomum verum) · Chanca Piedra (Phyllanthus niruri) · Cumin (Cuminum cyminum)
- Hemoglobin A1C
- Glucagon-Like Peptide-1 Agonists
- Holy Basil
- Black Seed
- Anti-Inflammatory Diet
Featured Videos