Yeast Infections
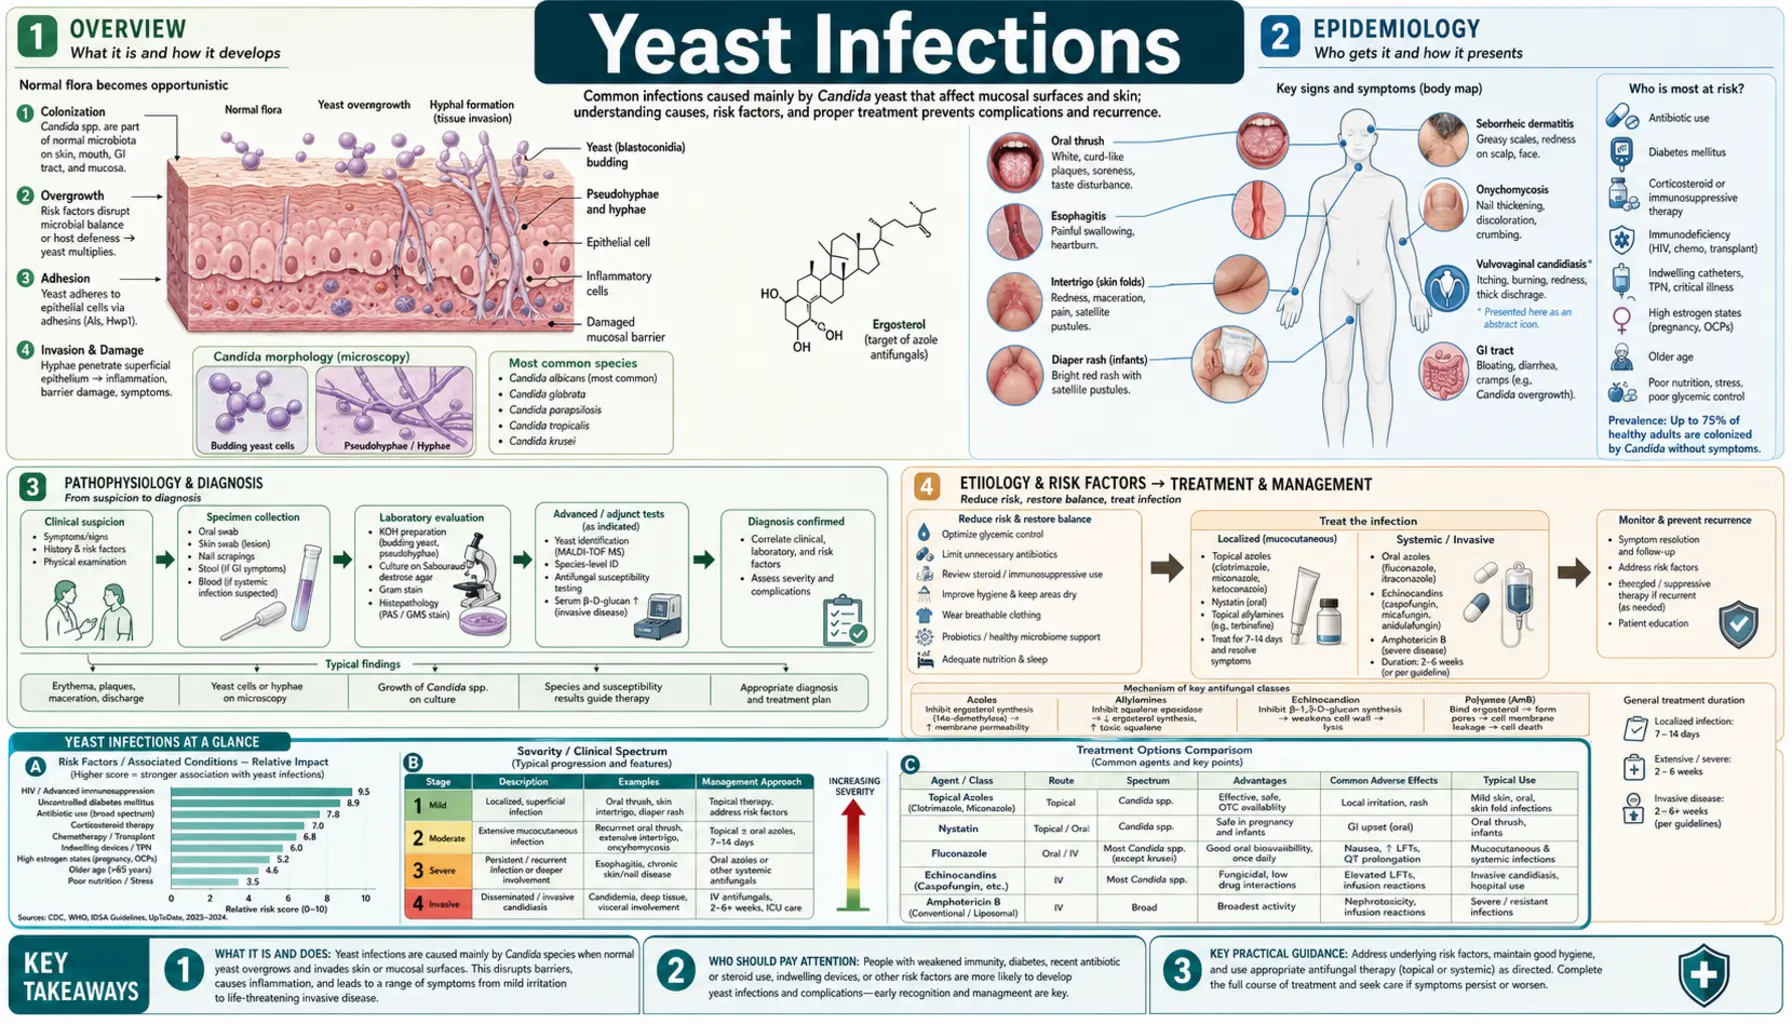
Table of Contents
1. Overview
A vaginal yeast infection — the medical term is vulvovaginal candidiasis (VVC) — is one of the most common reasons women see a clinician for vaginal symptoms. It is an overgrowth of a yeast, almost always Candida albicans, that produces the familiar trio of intense itching, burning, and a thick white discharge. It is so common that an estimated three out of four women will have at least one yeast infection in their lifetime, and many will have more than one.
Two facts are worth stating up front, because they push back on a lot of shame and misinformation. First, a yeast infection is not a sexually transmitted infection (STI). You do not "catch" it from a partner the way you catch chlamydia or gonorrhea. Second, it is not a sign that you are dirty or that you have poor hygiene — if anything, over-washing and scented products make things worse. Candida is a normal resident of the vagina, gut, and skin in many healthy people. A yeast infection happens when the local ecosystem shifts and that normally quiet yeast multiplies past the point your body tolerates it. You did not do anything wrong to cause it.
The good news is that yeast infections are generally easy to treat and respond well to short courses of antifungal medication. The trickier part — and a major theme of this page — is making sure that itching and discharge are actually caused by yeast and not by something else, because several other conditions produce overlapping symptoms and need entirely different treatment.
2. Epidemiology
Vulvovaginal candidiasis is extraordinarily common. Roughly 70–75% of women experience at least one episode during their reproductive years, and about 40–50% have a second episode. A smaller but important group — estimated at around 5–8% of women of reproductive age — develop recurrent vulvovaginal candidiasis (RVVC), defined as four or more culture-confirmed episodes in a year. A 2018 systematic review and global modeling study estimated that recurrent VVC affects approximately 138 million women worldwide each year, with annual losses in productivity that run into the billions of dollars.
Candidiasis is overwhelmingly a condition of the reproductive years. It is uncommon before puberty and becomes less frequent after menopause, because Candida thrives in the estrogen-rich, glycogen-rich vaginal environment of women who are menstruating. It becomes common again in postmenopausal women who take estrogen therapy. The single most consistent demographic finding is simply that exposure to estrogen, antibiotics, and uncontrolled blood sugar — not personal hygiene — drives the numbers.
3. Pathophysiology
To understand a yeast infection, picture the vagina as a tiny, balanced ecosystem. In health it is dominated by beneficial bacteria called Lactobacillus, which produce lactic acid and keep the vaginal pH acidic (usually below 4.5). This acidity, along with other defenses, holds Candida in check. Candida can live there quietly as a commensal — a harmless tenant — in 20% or more of healthy women without causing any symptoms at all.
Trouble starts when Candida shifts from its rounded, budding yeast form to an invasive, thread-like hyphal (filamentous) form. These hyphae burrow between and into the surface cells of the vaginal lining. Importantly, the misery of a yeast infection — the itching, swelling, and redness — is driven less by the yeast itself than by the immune system's inflammatory response to it. White blood cells flood the area and release signaling molecules, producing the heat, swelling, and intense itch. This is why two women with the same amount of yeast can have very different symptoms: it is the immune reaction, not the raw fungal count, that you feel.
Unlike bacterial vaginosis, where Lactobacillus is lost and pH rises, in a classic yeast infection the Lactobacillus and the acidic pH are usually preserved. That single fact — normal pH — is one of the most useful clues for telling yeast apart from other causes of vaginitis.
4. Etiology and Risk Factors
About 85–90% of yeast infections are caused by Candida albicans. The remainder are caused by non-albicans species — most often Candida glabrata (now also called Nakaseomyces glabratus), and less often C. krusei, C. tropicalis, or C. parapsilosis. This distinction matters for treatment, because non-albicans species are often less responsive to the standard azole antifungals.
Several well-established factors tip the balance toward overgrowth:
- Recent antibiotics — the classic trigger. Broad-spectrum antibiotics kill off protective Lactobacillus along with the bacteria they were meant to treat, opening space for yeast. Many women recognize the pattern: a sinus or urinary infection, a course of antibiotics, then a yeast infection a week later.
- Uncontrolled diabetes — high blood sugar feeds yeast. Repeated or stubborn yeast infections, especially in someone not previously known to be diabetic, are a legitimate reason to have blood sugar checked. A recurrent yeast infection can occasionally be the first clue to undiagnosed or poorly controlled diabetes.
- Pregnancy — high estrogen and increased vaginal glycogen make pregnancy a high-risk state for VVC.
- Estrogen exposure — high-dose combined oral contraceptives, estrogen therapy, and the natural estrogen surge of the menstrual cycle all favor yeast.
- Immunosuppression — human immunodeficiency virus (HIV) infection, organ-transplant medications, chemotherapy, and high-dose corticosteroids all weaken the local immune defenses.
- Recent corticosteroid use, including inhaled or oral steroids for asthma or autoimmune disease.
Some factors that get blamed are not strongly supported by evidence — routine sexual activity, tight clothing, and tampon use are weak or inconsistent associations. And again: yeast infections are not classified as an STI. Treating a male partner does not prevent a woman's recurrences and is generally not recommended.
5. Clinical Presentation
The hallmark of a yeast infection is itching — often intense, sometimes maddening — of the vulva and vaginal opening. Other typical symptoms include:
- Burning, especially during urination (as urine passes over inflamed skin) or during sex.
- Thick, white, clumpy discharge classically described as resembling cottage cheese. Crucially, this discharge is odorless or nearly so.
- Redness and swelling of the vulva, sometimes with small cracks (fissures) or a scattered rash extending onto the surrounding skin.
- Soreness and pain with intercourse (dyspareunia) and discomfort with urination (external dysuria).
How yeast differs from bacterial vaginosis and STIs
This is where many women (and a fair number of clinicians) go wrong. The three big causes of vaginal symptoms — yeast, bacterial vaginosis (BV), and trichomoniasis (an STI) — overlap but have telling differences:
- Yeast: very itchy, thick white "cottage cheese" discharge, no fishy odor, normal (acidic) pH below 4.5.
- Bacterial vaginosis: thin, gray-white discharge with a distinct fishy odor (especially after sex), elevated pH above 4.5, and usually less itching. BV is an imbalance of bacteria, not a yeast.
- Trichomoniasis: a sexually transmitted parasite that can cause frothy yellow-green discharge, odor, and irritation, with elevated pH; it requires oral prescription treatment and partner treatment.
For a careful side-by-side comparison of yeast versus BV — including the "whiff test," pH paper, and what each discharge looks like — see our dedicated Bacterial Vaginosis page. The one-line summary: fishy odor and high pH point away from yeast; intense itch with normal pH and no odor points toward it.
The over-the-counter pitfall
Here is a practical, money-saving point that the box of antifungal cream will never tell you: most women who self-diagnose a yeast infection are wrong. In a landmark 2002 study, 95 women buying over-the-counter antifungals at the pharmacy were examined and tested — only about one-third (33.7%) actually had a yeast infection. The rest had bacterial vaginosis (18.9%), a mix of conditions (21.1%), no infection at all (13.7%), other conditions (10.5%), or trichomoniasis (2.1%). Women who had been diagnosed with a yeast infection by a clinician before were no more accurate, and neither were women who had read the package label. Repeatedly buying antifungal creams for symptoms that aren't yeast wastes money, doesn't fix the real problem, and can delay correct diagnosis for weeks.
Over-the-counter (OTC) antifungals are sold for women who have had a clinician-confirmed yeast infection before and recognize the identical symptoms returning, although in the 2002 study a past diagnosis did not make self-diagnosis more accurate. Clinicians test rather than rely on self-diagnosis when:
- It is the first-ever episode of these symptoms.
- Symptoms are severe, or include fever, pelvic pain, or foul-smelling discharge.
- The woman is pregnant.
- Symptoms are recurrent (this keeps happening).
- An over-the-counter antifungal has already been tried and didn't work.
6. Diagnosis
Proper diagnosis is quick, inexpensive, and worth it. A clinician typically does the following:
- Examination of the vulva and vagina, looking for redness, swelling, fissures, and the characteristic discharge.
- Vaginal pH testing with a strip of pH paper. A normal, acidic pH (below 4.5) is consistent with yeast and helps rule out BV and trichomoniasis, which raise the pH.
- Microscopy — a sample of discharge is examined under the microscope. Adding potassium hydroxide (KOH) to the slide dissolves cells and debris, making the budding yeast and branching hyphae (pseudohyphae) easier to see. Seeing hyphae confirms active infection.
- Fungal culture — reserved for cases that are recurrent, complicated, or not responding to treatment. Culture identifies the exact species (important for spotting C. glabrata and other azole-resistant non-albicans yeasts) and can guide which drug to use.
Newer molecular (PCR/NAAT) panels can detect Candida and distinguish it from BV and trichomoniasis from a single swab; they are sensitive and increasingly available, though microscopy and culture remain the workhorses. A key caveat: a positive culture or polymerase chain reaction (PCR) alone, in a woman with no symptoms, does not mean she needs treatment — Candida is a normal commensal, and treating colonization without symptoms is unnecessary.
7. Treatment
Uncomplicated yeast infections
For a typical, uncomplicated yeast infection caused by C. albicans, short-course azole antifungals work very well, with cure rates of roughly 80–90%. There are two equally effective routes, and the choice mostly comes down to personal preference:
- Topical azoles — over-the-counter miconazole or clotrimazole creams or suppositories, available as 1-day, 3-day, or 7-day regimens. Longer regimens are often gentler on already-inflamed tissue. These act locally and are safe in pregnancy.
- Oral fluconazole — a single 150 mg pill by prescription. Its efficacy is equivalent to topical treatment, and many women prefer the convenience of one tablet over several days of cream. Fluconazole is not used in pregnancy (see below).
For more severe inflammation, clinicians sometimes use two doses of fluconazole 150 mg three days apart, or a longer 7–14 day topical course.
Non-albicans species (C. glabrata)
If symptoms persist after standard treatment, a culture may reveal Candida glabrata or another non-albicans species. These yeasts are frequently less responsive to azoles. Options include a longer course of intravaginal therapy, intravaginal boric acid suppositories (600 mg nightly for about 2 weeks), or, in resistant cases, prescription nystatin or compounded flucytosine cream prescribed by a specialist.
Recurrent vulvovaginal candidiasis (≥4 per year)
Recurrent VVC is treated as a two-phase problem: first knock the infection down (induction), then keep it down (maintenance/suppression). A landmark 2004 trial published in the New England Journal of Medicine by Sobel and colleagues established the modern standard: after induction, weekly oral fluconazole (150 mg) for six months dramatically reduced recurrences while women stayed on it: among 387 women, 90.8% on weekly fluconazole were disease-free at 6 months, against 35.9% on placebo. The catch, honestly reported, is that recurrences often return after maintenance stops — at 9 and 12 months (3 and 6 months after the last dose), 73.2% and 42.9% were disease-free, against 27.8% and 21.9% with placebo, and the median time to a recurrence was 10.2 months versus 4.0 months. Suppression controls the disease but does not cure the underlying tendency. The widely used European "ReCiDiF" regimen uses a tapering, individualized fluconazole schedule built on the same induction-then-maintenance logic.
Two newer oral antifungals have been approved for recurrent VVC; one of them was later affected by a recall (below):
- Oteseconazole is a selective fungal CYP51 inhibitor. In the phase 3 program reported by Martens and colleagues in 2022, it reduced recurrences over a year compared with placebo: in that trial of 219 women and girls with recurrent VVC, 5.1% of those on oteseconazole had a culture-proven recurrence through 50 weeks, against 42.2% on placebo, and for the starting infection it worked as well as fluconazole (93.2% versus 95.8% resolved). Because it has a very long half-life and theoretical reproductive-toxicity signals in animals, it is approved only for women who cannot become pregnant.
- Ibrexafungerp is a first-in-class oral triterpenoid (a glucan synthase inhibitor) approved for treating acute VVC and for reducing recurrences. The VANISH trials reported by Sobel and colleagues showed it outperformed placebo for acute episodes: in VANISH 306, 63.3% of women on a one-day course were clinically cured at the test-of-cure visit, against 44.0% on placebo. In the CANDLE trial, women with recurrent VVC who took ibrexafungerp once a month for 6 months after fluconazole treatment more often stayed free of a mycologically proven recurrence through week 24 (70.8% versus 58.5% on placebo). In September 2023 the manufacturer voluntarily recalled two lots of ibrexafungerp tablets nationwide, down to the consumer level, because of possible cross-contamination with a non-antibacterial beta-lactam drug substance; the recall notice posted by the U.S. Food and Drug Administration (FDA) states that such contamination could cause allergic (hypersensitivity) reactions, including anaphylaxis, and that no adverse events had been established as due to it.
These are useful additions, especially for azole-resistant or refractory disease, but they are not magic bullets and are considerably more expensive than generic fluconazole.
Probiotics, diet, and the "candida cleanse" myth
It is fair to ask whether Lactobacillus probiotics or dietary changes can prevent or cure yeast infections. The honest answer is: the evidence is limited and mixed, and it is easy to oversell. A 2017 Cochrane systematic review found that probiotics, added on to conventional antifungals, might modestly improve short-term cure rates, but the studies were small and of low-to-moderate quality, so the result is far from conclusive. A randomized trial by Pirotta and colleagues (BMJ, 2004) testing oral and vaginal Lactobacillus to prevent post-antibiotic yeast infections found no benefit. Probiotics are generally safe and low-risk; the trials tested them alongside antifungal treatment, not instead of it, and none showed dramatic results.
A more important point concerns the popular online idea of "systemic candida overgrowth" — the claim that a body-wide yeast burden causes fatigue, brain fog, bloating, and dozens of other vague symptoms, curable by a restrictive "candida cleanse" or "candida diet." This concept is not supported by medical evidence. Localized infections (vaginal, oral thrush, skin folds) are real and treatable; true invasive, bloodstream candidiasis is a serious hospital illness in profoundly immunocompromised people, not something an otherwise-healthy person treats with a juice cleanse. The danger of the "candida cleanse" framing is that it sends people on expensive, restrictive diets and supplement regimens while their actual cause of symptoms — which may be something entirely different — goes undiagnosed. Your symptoms are real; the "systemic candida" explanation usually is not.
Boric acid suppositories
Intravaginal boric acid (typically 600 mg in a gelatin capsule, inserted nightly) has the best evidence as a second-line option for recurrent or non-albicans infections that don't respond to azoles. A 2011 review by Iavazzo and colleagues found mycologic cure rates of roughly 40–100% across studies, supporting its use when standard treatment fails. Two safety facts stand out: boric acid is for vaginal use only — it is toxic if swallowed, including by children who find the capsules — and it is not used in pregnancy.
Pregnancy
Yeast infections are common in pregnancy and are treated, but the approach changes: the 2021 U.S. Centers for Disease Control and Prevention (CDC) guideline states that only topical azole therapies, applied for 7 days (such as clotrimazole or miconazole), are recommended in pregnancy, not oral fluconazole. High-dose oral fluconazole in early pregnancy has been associated with possible birth defects, and even low doses carry uncertainty, which is why the guideline lists topical therapy only. Boric acid is likewise avoided in pregnancy.
When the itching isn't yeast at all
When antifungals keep failing, the likely explanation is that persistent vulvar itching is often not yeast. Several skin conditions mimic it and need very different care:
- Lichen sclerosus — a chronic inflammatory skin condition causing itching, whitening, and thinning of vulvar skin; it is treated with prescription steroid ointment and ongoing follow-up, not with antifungals.
- Eczema and contact/irritant dermatitis — often triggered by scented soaps, wipes, pads, or the antifungal creams themselves. See Eczema.
- Atrophic vaginitis in postmenopausal women, from low estrogen.
After two or three rounds of "yeast" treatment without lasting relief, an examination is how the real cause is found — ideally during symptoms, when a clinician can test rather than guess.
8. Complications
For most women, an uncomplicated yeast infection is uncomfortable but not dangerous and causes no lasting harm. The most common "complications" are really consequences of mistreatment: recurrent symptoms, repeated wasted spending on over-the-counter products, irritation from over-treatment, and the emotional toll of an undiagnosed problem. Severe inflammation can cause painful fissures and broken skin, which occasionally allow a secondary bacterial infection.
In profoundly immunocompromised people — advanced human immunodeficiency virus/acquired immunodeficiency syndrome (AIDS), transplant recipients, those on chemotherapy — candidiasis can be more severe, more frequent, and harder to clear, and a small minority can develop invasive disease. This is the exception, not the rule, and does not apply to otherwise-healthy women with ordinary yeast infections. Recurrent or stubborn infections also warrant a check for undiagnosed diabetes — see Diabetes and Insulin Resistance.
9. Prognosis
The outlook for yeast infections is excellent. Uncomplicated episodes clear with a single short course of antifungal medication in the large majority of women, with relief often beginning within a day or two. The chief challenge is not the individual infection but the minority of women with recurrent disease, for whom maintenance therapy controls symptoms well during treatment but recurrences may return when it stops. Even so, recurrent VVC is a manageable, long-term condition, not a progressive or life-threatening one. With accurate diagnosis (testing rather than guessing), most women achieve good, durable control.
10. Prevention
Some risk factors are modifiable; many are not, and it's worth being honest about the limits of control. Factors with evidence behind them include:
- Fewer unnecessary antibiotics. The single most actionable factor. Antibiotics do nothing for viral colds, and a yeast infection can follow even a course of antibiotics that is genuinely needed.
- Blood sugar control in diabetes. Good glycemic control reduces yeast overgrowth and recurrences.
- No douching or scented products. Douches, scented soaps, "feminine washes," sprays, and scented pads disrupt the protective Lactobacillus balance and irritate the skin. Plain water is enough for the vulva; the vagina cleans itself.
- Breathable underwear. Cotton underwear and changing out of wet swimsuits or sweaty workout clothes are commonly recommended — the evidence is modest, but they are harmless and may help some women.
Neither self-blame nor elaborate "anti-candida" diets and cleanses change these drivers. For most women, yeast infections are an occasional, treatable nuisance driven by hormones, antibiotics, and blood sugar — factors that are often only partly within a woman's control. A recurrence is not a personal failing.
11. Recent Research and Advances
Several active research directions are reshaping how recurrent and resistant yeast infections are managed. The two recently approved oral antifungals — oteseconazole (a long-acting, fungus-selective CYP51 inhibitor) and ibrexafungerp (a first-in-class oral glucan synthase inhibitor) — give clinicians genuinely new mechanisms for recurrent and azole-resistant disease, an area where treatment had stagnated for two decades. Their real-world value, cost-effectiveness, and durability beyond the trial period are still being worked out.
A second major theme is antifungal resistance, particularly among non-albicans species such as C. glabrata, which has driven renewed interest in older agents (boric acid, flucytosine) and in stewardship to avoid overusing azoles. A third is the role of the vaginal microbiome and the host immune response: research increasingly frames symptomatic VVC as an immune-driven condition (an exaggerated inflammatory response to a normal commensal) rather than simply "too much yeast," which may eventually lead to immune-modulating or microbiome-based therapies. For now, the practical advances that benefit patients most are unglamorous: accurate testing instead of self-diagnosis, recognizing non-albicans species, and not mistaking skin conditions or the "candida cleanse" myth for a yeast infection.
Key Research Papers
- Sobel JD. Vulvovaginal candidosis. The Lancet, 2007;369(9577):1961–1971. — doi:10.1016/S0140-6736(07)60917-9
- Sobel JD, Wiesenfeld HC, Martens M, et al. Maintenance Fluconazole Therapy for Recurrent Vulvovaginal Candidiasis. New England Journal of Medicine, 2004;351(9):876–883. — doi:10.1056/NEJMoa033114
- Sobel JD. Recurrent Vulvovaginal Candidiasis: A Prospective Study of the Efficacy of Maintenance Ketoconazole Therapy. New England Journal of Medicine, 1986;315(23):1455–1458. — doi:10.1056/NEJM198612043152305
- Martens MG, Maximos B, Degenhardt T, et al. Phase 3 study evaluating the safety and efficacy of oteseconazole in the treatment of recurrent vulvovaginal candidiasis and acute vulvovaginal candidiasis infections. American Journal of Obstetrics and Gynecology, 2022;227(6):880.e1–880.e11. — doi:10.1016/j.ajog.2022.07.023
- Sobel R, Nyirjesy P, Ghannoum MA, et al. Efficacy and safety of oral ibrexafungerp for the treatment of acute vulvovaginal candidiasis: a global phase 3, randomised, placebo-controlled superiority study (VANISH 306). BJOG, 2022;129(3):412–420. — doi:10.1111/1471-0528.16972
- Goje O, Azie NE, Angulo DA, et al. A phase 3, multicenter, randomized, placebo-controlled trial of monthly oral ibrexafungerp to reduce the incidence of recurrent vulvovaginal candidiasis. American Journal of Obstetrics and Gynecology, 2025;233(6):617.e1–617.e18. — doi:10.1016/j.ajog.2025.07.040
- Pirotta M, Gunn J, Chondros P, et al. Effect of lactobacillus in preventing post-antibiotic vulvovaginal candidiasis: a randomised controlled trial. BMJ, 2004;329(7465):548. — doi:10.1136/bmj.38210.494977.DE
- Xie HY, Feng D, Wei DM, et al. Probiotics for vulvovaginal candidiasis in non-pregnant women. Cochrane Database of Systematic Reviews, 2017;(11):CD010496. — doi:10.1002/14651858.CD010496.pub2
- Iavazzo C, Gkegkes ID, Zarkada IM, Falagas ME. Boric Acid for Recurrent Vulvovaginal Candidiasis: The Clinical Evidence. Journal of Women's Health, 2011;20(8):1245–1255. — doi:10.1089/jwh.2010.2708
- Ferris DG, Nyirjesy P, Sobel JD, et al. Over-the-Counter Antifungal Drug Misuse Associated With Patient-Diagnosed Vulvovaginal Candidiasis. Obstetrics & Gynecology, 2002;99(3):419–425. — doi:10.1016/s0029-7844(01)01759-8
- Workowski KA, Bachmann LH, Chan PA, et al. Sexually Transmitted Infections Treatment Guidelines, 2021. MMWR Recommendations and Reports, 2021;70(4):1–187. — doi:10.15585/mmwr.rr7004a1
- Gonçalves B, Ferreira C, Alves CT, et al. Vulvovaginal candidiasis: Epidemiology, microbiology and risk factors. Critical Reviews in Microbiology, 2016;42(6):905–927. — doi:10.3109/1040841X.2015.1091805
- Blostein F, Levin-Sparenberg E, Wagner J, Foxman B. Recurrent vulvovaginal candidiasis. Annals of Epidemiology, 2017;27(9):575–582.e3. — doi:10.1016/j.annepidem.2017.08.010
- Denning DW, Kneale M, Sobel JD, Rautemaa-Richardson R. Global burden of recurrent vulvovaginal candidiasis: a systematic review. The Lancet Infectious Diseases, 2018;18(11):e339–e347. — doi:10.1016/S1473-3099(18)30103-8
Historical Background
Vaginal candidiasis has been recognized for well over a century, but effective oral therapy is relatively recent. The systematic study of recurrent disease began in the 1980s, when Sobel's prospective work in the New England Journal of Medicine (1986) defined recurrent vulvovaginal candidiasis as a distinct clinical entity. The introduction of the azole antifungals, and especially the single-dose oral fluconazole regimen, transformed treatment in the 1990s by offering a convenience equivalent in efficacy to topical creams. The pivotal 2004 NEJM maintenance-fluconazole trial then established the modern induction-plus-suppression strategy for recurrent disease. Most recently, the 2021 U.S. Centers for Disease Control and Prevention (CDC) guidelines and the approval of oteseconazole and ibrexafungerp (2021–2022) opened the first new mechanistic options for recurrent and resistant infections in a generation.
PubMed Topic Searches
Explore current, peer-reviewed literature on vulvovaginal candidiasis and yeast infections through these live PubMed topic searches. Each link opens the latest indexed studies in a new tab.
- PubMed: Vulvovaginal candidiasis
- PubMed: Recurrent vulvovaginal candidiasis
- PubMed: Candida albicans vaginitis
- PubMed: Candida glabrata vaginitis treatment
- PubMed: Fluconazole vulvovaginal candidiasis
- PubMed: Boric acid vaginal candidiasis
- PubMed: Oteseconazole
- PubMed: Ibrexafungerp vulvovaginal candidiasis
- PubMed: Probiotics and vulvovaginal candidiasis
- PubMed: Diabetes and vulvovaginal candidiasis
- PubMed: Vaginal microbiome and Candida
- PubMed: Azole resistance in Candida vaginitis
Connections
- Reproductive Medicine
- Bacterial Vaginosis — the most common look-alike; side-by-side comparison of yeast vs. BV.
- Infertility — related reproductive-health topic and vaginal-health context.
- Urinary Tract Infections — another common cause of burning and discomfort, often confused with yeast.
- Diabetes — high blood sugar feeds yeast; recurrent infections can be a clue to check it.
- Insulin Resistance — the metabolic precursor to diabetes and elevated glucose.
- Fungal Infections — the broader family of Candida and other fungal infections.
- Eczema — irritant/contact dermatitis that can mimic persistent vulvar itching.
- Human Immunodeficiency Virus / Acquired Immunodeficiency Syndrome — immunosuppression that makes candidiasis more frequent and severe.
- Small Intestinal Bacterial Overgrowth — another condition wrongly blamed on "systemic yeast" in popular health claims.
- Probiotics — the honest evidence on Lactobacillus for vaginal health.
- Yogurt — a dietary source of Lactobacillus often suggested for vaginal balance.
- Garlic — a folk antifungal remedy; useful context on what the evidence does and doesn't support.
- All Conditions — the full health-conditions index.