Insulin Resistance: The Silent Upstream Driver of Chronic Disease
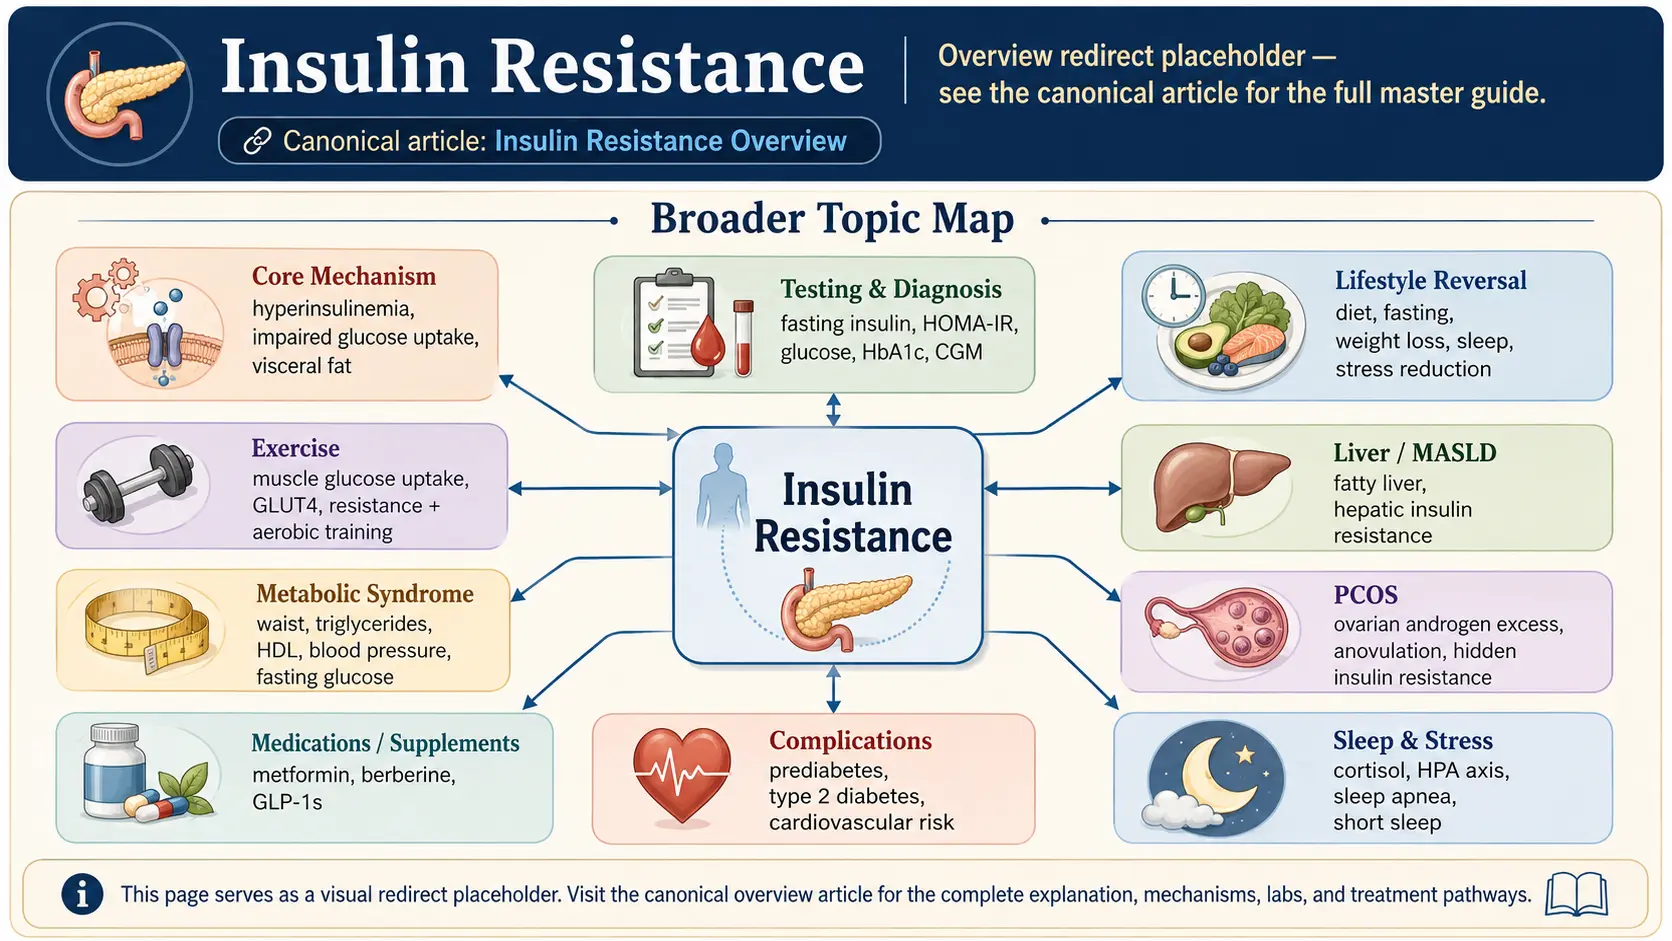
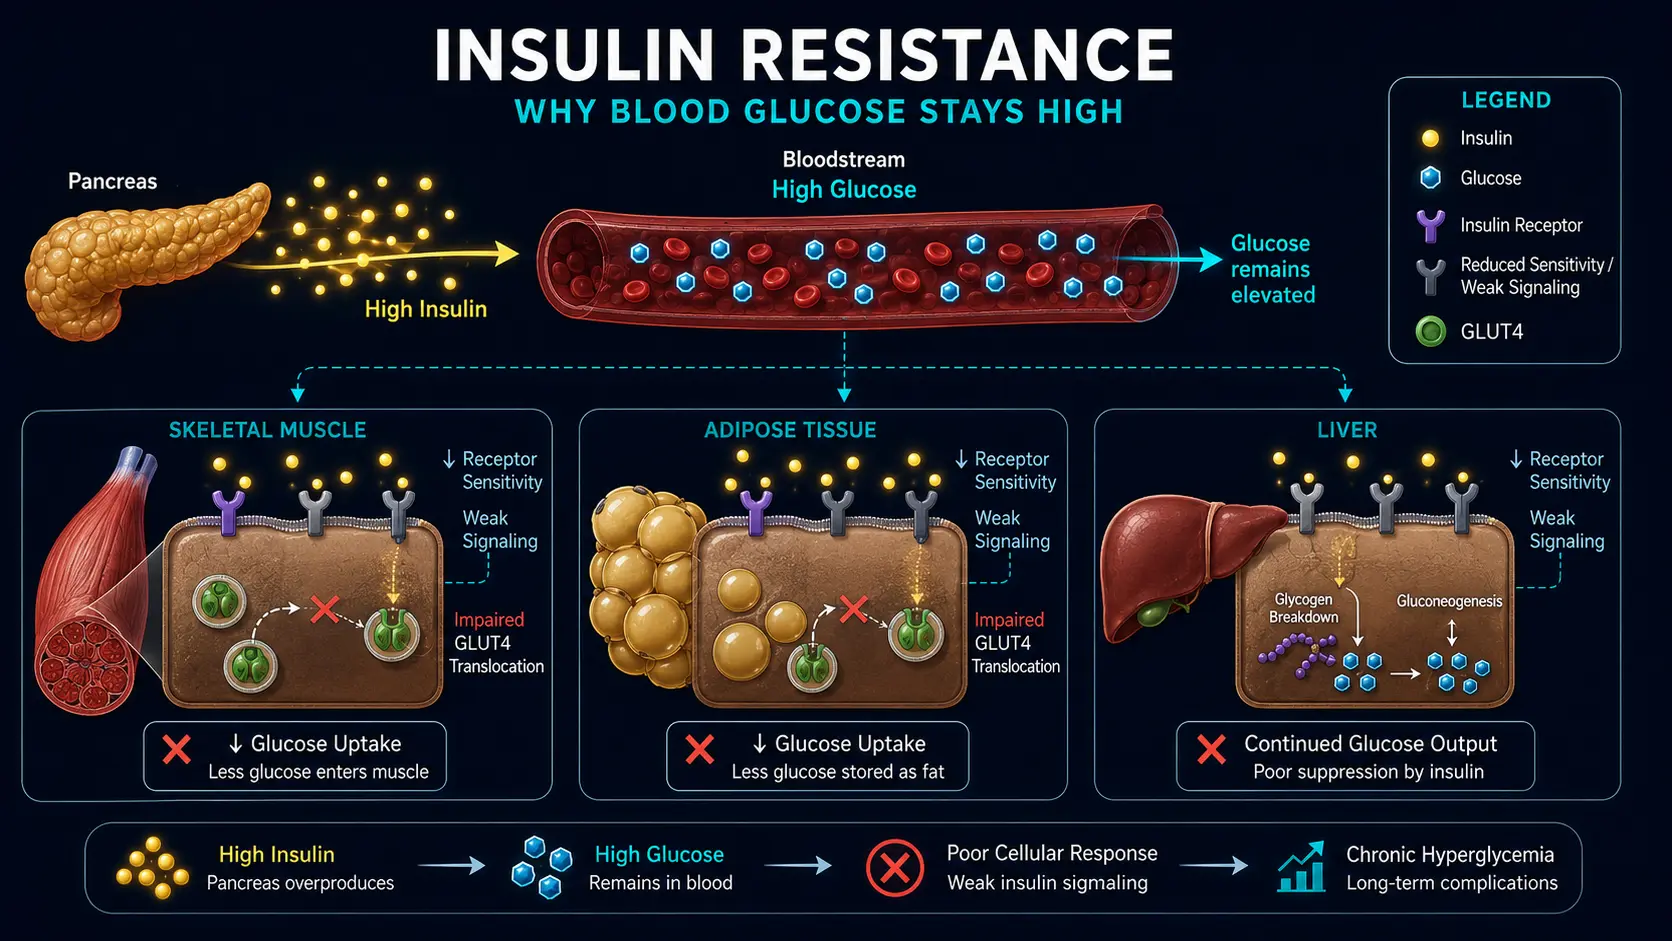
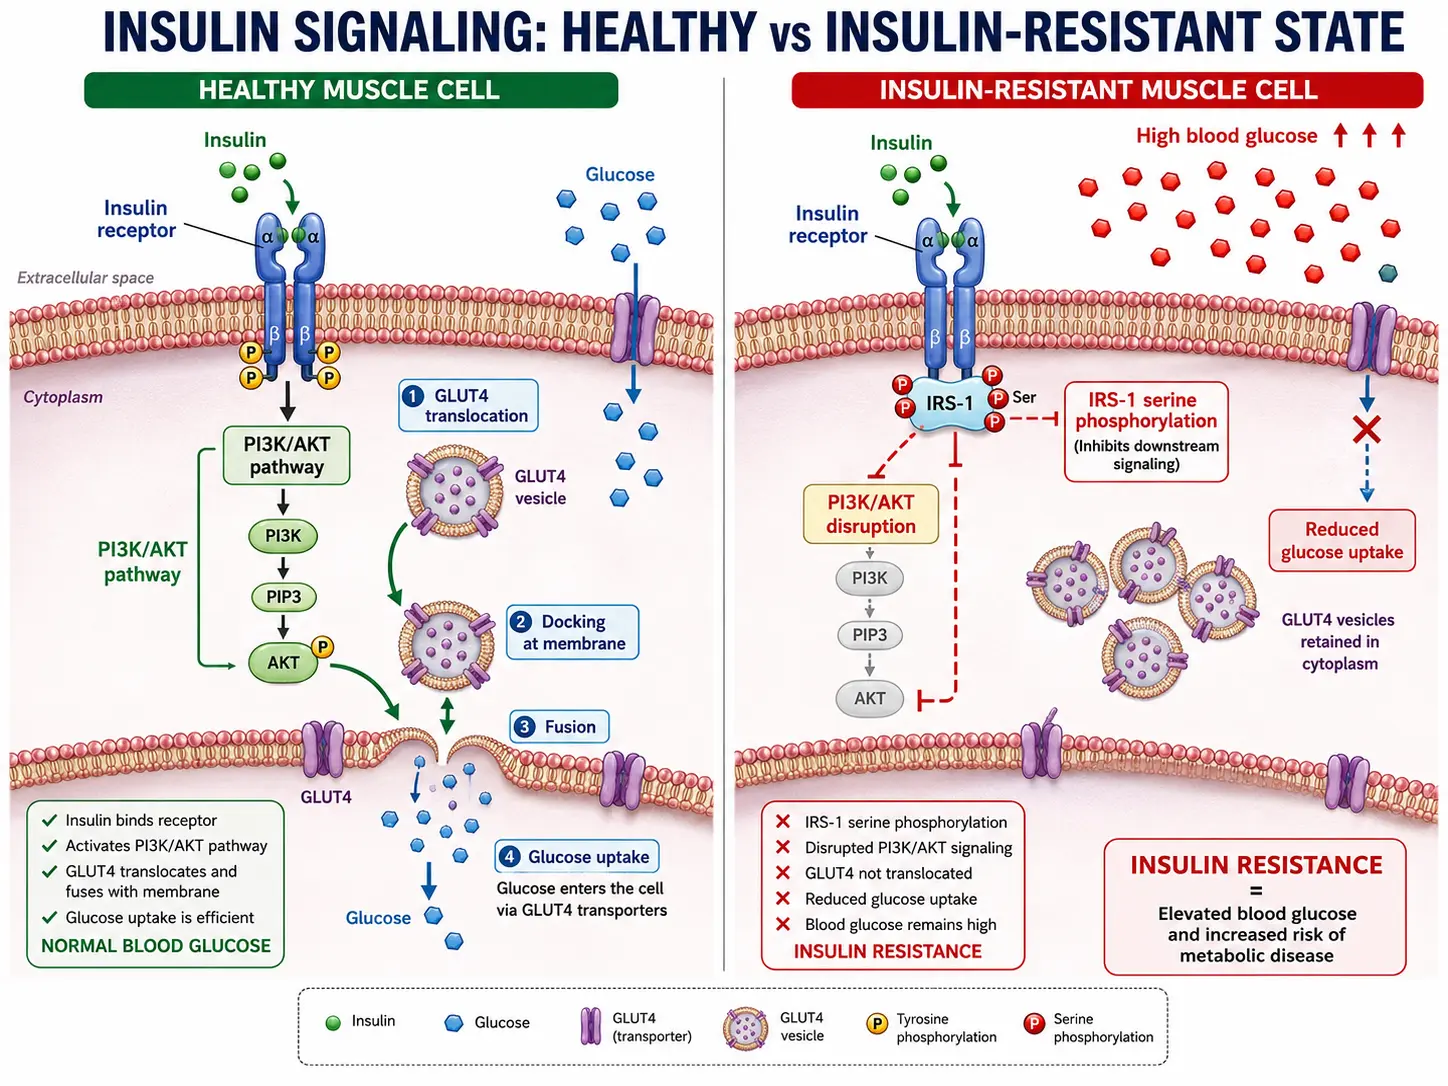
Insulin resistance is a state in which the body’s cells — particularly muscle, liver, and adipose tissue — respond less effectively to insulin, so the pancreas must release more insulin to achieve the same blood-glucose control. It is the central metabolic defect that precedes and drives type 2 diabetes, fatty liver disease, polycystic ovary syndrome, metabolic syndrome, much of cardiovascular disease, and a substantial fraction of Alzheimer’s disease (now called by some researchers “type 3 diabetes”). Perhaps most important, insulin resistance is usually present for 10 to 15 years before blood sugar rises into prediabetic or diabetic ranges, a long window in which it is reversible — but almost never measured in routine medical care.
Deep-Dive Articles
Fasting Insulin & Homeostatic Model Assessment of Insulin Resistance
Why fasting insulin catches problems 10+ years before fasting glucose moves. Homeostatic model assessment of insulin resistance (HOMA-IR) formula, target ranges, OGTT with insulin, and what labs to ask for.
Read the deep dive →CGM for Non-Diabetics
Dexcom G7, Freestyle Libre, Levels/Nutrisense/Signos — what to actually learn from a 2-week CGM trial without pathologizing every spike.
Read the deep dive →Reversal: Diet & Fasting
The evidence for low-carb/ketogenic, Mediterranean, and protein-forward diets; time-restricted eating; DiRECT-trial 5%-weight-loss threshold; protein sparing modified fasts.
Read the deep dive →IR & Polycystic Ovary Syndrome
Polycystic ovary syndrome (PCOS) is insulin resistance in an ovary costume. Rotterdam criteria, androgen excess, metformin + inositol, glucagon-like peptide-1 (GLP-1) receptor agonists (GLP-1s), fertility impact.
Read the deep dive →Metabolic Syndrome & CV Risk
ATP-III criteria, waist circumference as the best single marker, triglyceride-to-HDL ratio, apoB, Lp(a), and why statins alone don't fix the metabolic engine.
Read the deep dive →Non-Alcoholic Fatty Liver Disease / Metabolic Dysfunction-Associated Steatotic Liver Disease Connection
Fatty liver (now renamed metabolic dysfunction-associated steatotic liver disease, MASLD) as the hepatic arm of insulin resistance. FIB-4, FibroScan, why alanine aminotransferase (ALT) "within normal range" still matters, and reversal.
Read the deep dive →Exercise & Muscle Sensitivity
Why resistance training + brisk walking beat cardio alone for insulin sensitivity. GLUT4 translocation, Zone 2, HIIT tradeoffs, muscle as the largest glucose sink.
Read the deep dive →Metformin, Berberine & Glucagon-Like Peptide-1 Receptor Agonists
Metformin 500-2000 mg, berberine as the natural-medicine analog, glucagon-like peptide-1 receptor agonists (semaglutide, tirzepatide), and when each makes sense off-label for IR.
Read the deep dive →Sleep, Stress & Cortisol
Why sleep restriction, OSA, and chronic stress drive insulin resistance.
Read the deep dive →Table of Contents
What Insulin Resistance Is
Insulin is the anabolic hormone released by pancreatic beta cells in response to rising blood glucose and certain amino acids. It moves glucose from blood into cells via GLUT4 transporters in muscle and fat, suppresses hepatic glucose production, and promotes storage of glucose as glycogen and fat. In insulin-resistant tissue, the signaling cascade downstream of the insulin receptor is impaired. The pancreas compensates by secreting more insulin, maintaining glucose control at the cost of chronic hyperinsulinemia — which is itself a problem. Eventually, pancreatic beta cells fatigue and can no longer keep up, at which point fasting glucose rises and type 2 diabetes is diagnosed. By then the horse has been out of the barn for a decade.
Why It Matters — Downstream Consequences
- Type 2 diabetes
- Non-alcoholic fatty liver disease (MASLD/MASH)
- Polycystic ovary syndrome
- Metabolic syndrome — central adiposity, hypertension, dyslipidemia, hyperglycemia
- Cardiovascular disease — accelerated atherosclerosis, endothelial dysfunction
- Gout (hyperinsulinemia raises uric acid)
- Alzheimer’s disease (brain insulin resistance)
- Some cancers (breast, colon, endometrium, pancreatic)
- Acanthosis nigricans, skin tags, hirsutism in women
- Infertility and erectile dysfunction
How to Test For It
- Fasting insulin. Optimal <7 µinternational units (IU)/mL. 10–15 suggests insulin resistance even with normal fasting glucose. >15 is clearly abnormal.
- Homeostatic model assessment of insulin resistance. Calculated: (fasting insulin × fasting glucose) / 405. Values >2 suggest resistance; >2.5 strongly suggest it.
- Fasting triglyceride-to-HDL ratio. >2 (mg/dL) or >0.9 (mmol/L) suggests resistance in non-Black populations.
- Oral glucose tolerance test with insulin. The Kraft test — 2- or 3-hour paired glucose and insulin at 30-min intervals — is the most sensitive but less commonly available.
- Continuous glucose monitor. A 2-week CGM often reveals post-meal glucose excursions that are the earliest measurable clinical sign.
- Hemoglobin A1c rises late and catches only the tail end of the insulin-resistance trajectory.
- Waist-to-height ratio. >0.5 strongly suggests central adiposity driven by insulin resistance.
Clinical Signs
- Central adiposity — “apple” shape.
- Skin tags, particularly at neck and axilla.
- Acanthosis nigricans — dark velvety skin at neck, axilla, groin.
- Reactive hypoglycemia 2–4 hours after meals.
- Post-meal energy crashes and irresistible carb cravings.
- Hirsutism, irregular periods, acne in women.
Primary Drivers
- Diet dominated by ultra-processed foods, refined carbohydrates, and liquid calories.
- Chronic caloric surplus and excess adipose tissue, particularly visceral.
- Sedentary lifestyle.
- Chronic sleep restriction or fragmentation.
- Chronic stress and elevated cortisol.
- Genetics (modest individual contribution).
- Certain medications (glucocorticoids, atypical antipsychotics, some antivirals).
- Endocrine disruptors and persistent organic pollutants.
The Reversal Framework
- Reduce refined carbohydrate. Sugar, soft drinks, juice, ultra-processed snacks, and refined starch are the biggest levers.
- Increase protein and fiber. Both slow glucose absorption and improve satiety.
- Time-restricted eating. 10-, 12-, or 14-hour eating windows improve insulin sensitivity for many.
- Resistance training. Skeletal muscle mass is the largest glucose sink; building it is the single most effective sensitizer.
- Post-meal walking. 10–15 minutes after each meal cuts glucose excursion substantially.
- Sleep 7–9 hours. One night of 4-hour sleep impairs insulin sensitivity measurably.
- Stress management. Cortisol is a glucocorticoid — the name is literal.
- Weight loss of 5–10% body weight produces large improvements in insulin sensitivity and can reverse early type 2 diabetes.
Pharmacologic Aids
- Metformin — first-line for insulin-resistant states including prediabetes and polycystic ovary syndrome.
- Glucagon-like peptide-1 receptor agonists — powerful improvement in insulin sensitivity alongside weight loss. See glucagon-like peptide-1 Receptor Agonists.
- Sodium-glucose cotransporter-2 (SGLT2) inhibitors — additional cardiovascular and renal benefits.
- Pioglitazone — insulin sensitizer with weight-gain trade-off.
Evidence-Based Supplements
- Berberine — 500 mg three times daily; comparable to metformin in some trials.
- Magnesium — deficiency impairs insulin action.
- Chromium picolinate — modest improvements.
- Alpha-lipoic acid, cinnamon, and fenugreek have supportive evidence.
- Omega-3 fatty acids — improve membrane fluidity and insulin signaling.
Connections
- Endocrinology
- How the Liver Keeps Your Blood Sugar Steady — interactive animation
- How Insulin Opens the Cell: The GLUT4 Switch — interactive animation
- Inside the Beta Cell: How Insulin Is Released — interactive animation
- Fat Burning & Ketosis — interactive animation
- Hunger, Leptin & Why Diets Fight Back — interactive animation
- Blood Sugar & Insulin — interactive animation
- Berberine
- Glucagon-Like Peptide-1 Receptor Agonists
- Non-Alcoholic Fatty Liver Disease & Metabolic Dysfunction-Associated Steatotic Liver Disease Connection
- Reversal Protocol: Diet and Fasting
- CGM for Non-Diabetics
- Fasting Insulin and Homeostatic Model Assessment of Insulin Resistance Testing
- Insulin Resistance and Polycystic Ovary Syndrome
- Exercise and Muscle Insulin Sensitivity
- Metformin, Berberine and Glucagon-Like Peptide-1 Receptor Agonists
- Metabolic Syndrome Cardiovascular Risk
- Sleep, Stress and Cortisol
- Diabetes
- Metabolic Syndrome
- Polycystic Ovary Syndrome
- Fasting Insulin
- Magnesium
- Fasting
- Chromium
- Breast Cancer
- Pancreatic Cancer
- Diabetic Retinopathy
- Blood Sugar Deep Dive: Insulin Resistance — the blood-sugar-side companion, covering the Taylor personal fat threshold, fructose and hepatic resistance, and the DiRECT/Virta/Counterpoint remission trials.
- Herbs covered on this site that discuss this condition: Bitter Melon (Momordica charantia) · Gymnema (Gymnema sylvestre) · Berberine (Berberis & Coptis spp.) · Black Seed (Nigella sativa) · Stevia (Stevia rebaudiana) · Butterfly Pea (Clitoria ternatea)
- Blood Sugar Remedies — the full index of herbs, nutrients, foods and practices that act on blood glucose
- Apple Cider Vinegar
- Obesity
- Hemoglobin A1C
- Continuous Glucose Monitor
Key Research Papers
- Petersen MC, Shulman GI (2018). Mechanisms of Insulin Action and Insulin Resistance. Physiological Reviews — PubMed PMID: 30067154
- Matthews DR, Hosker JP, Rudenski AS, et al. (1985). Homeostasis model assessment: insulin resistance and beta-cell function from fasting plasma glucose and insulin concentrations in man. Diabetologia — PubMed PMID: 3899825
- Knowler WC, Barrett-Connor E, Fowler SE, et al. (2002). Reduction in the incidence of type 2 diabetes with lifestyle intervention or metformin. The New England Journal of Medicine — PubMed PMID: 11832527
- Lean ME, Leslie WS, Barnes AC, et al. (2018). Primary care-led weight management for remission of type 2 diabetes (DiRECT): an open-label, cluster-randomised trial. Lancet (London, England) — PubMed PMID: 29221645
- Donga E, van Dijk M, van Dijk JG, et al. (2010). A single night of partial sleep deprivation induces insulin resistance in multiple metabolic pathways in healthy subjects. The Journal of Clinical Endocrinology and Metabolism — PubMed PMID: 20371664
- Sutton EF, Beyl R, Early KS, et al. (2018). Early Time-Restricted Feeding Improves Insulin Sensitivity, Blood Pressure, and Oxidative Stress Even without Weight Loss in Men with Prediabetes. Cell Metabolism — PubMed PMID: 29754952
- Yin J, Xing H, Ye J (2008). Efficacy of berberine in patients with type 2 diabetes mellitus. Metabolism: Clinical and Experimental — PubMed PMID: 18442638
- Simental-Mendía LE, Sahebkar A, Rodríguez-Morán M, et al. (2016). A systematic review and meta-analysis of randomized controlled trials on the effects of magnesium supplementation on insulin sensitivity and glucose control. Pharmacological Research — PubMed PMID: 27329332
PubMed Topic Searches
The following PubMed topic searches aggregate the current peer-reviewed literature. Each link opens a live PubMed query — results update as new studies are indexed.
- PubMed: Insulin resistance
- PubMed: HOMA-IR
- PubMed: Metabolic syndrome insulin resistance
- PubMed: Visceral adiposity
- PubMed: Low carbohydrate diet insulin resistance
- PubMed: Time restricted eating insulin
- PubMed: Exercise insulin sensitivity
- PubMed: Metformin prediabetes
- PubMed: Berberine insulin resistance
- PubMed: Inositol PCOS insulin
- PubMed: Hepatic insulin resistance NAFLD
- PubMed: Magnesium insulin sensitivity