Frozen Shoulder
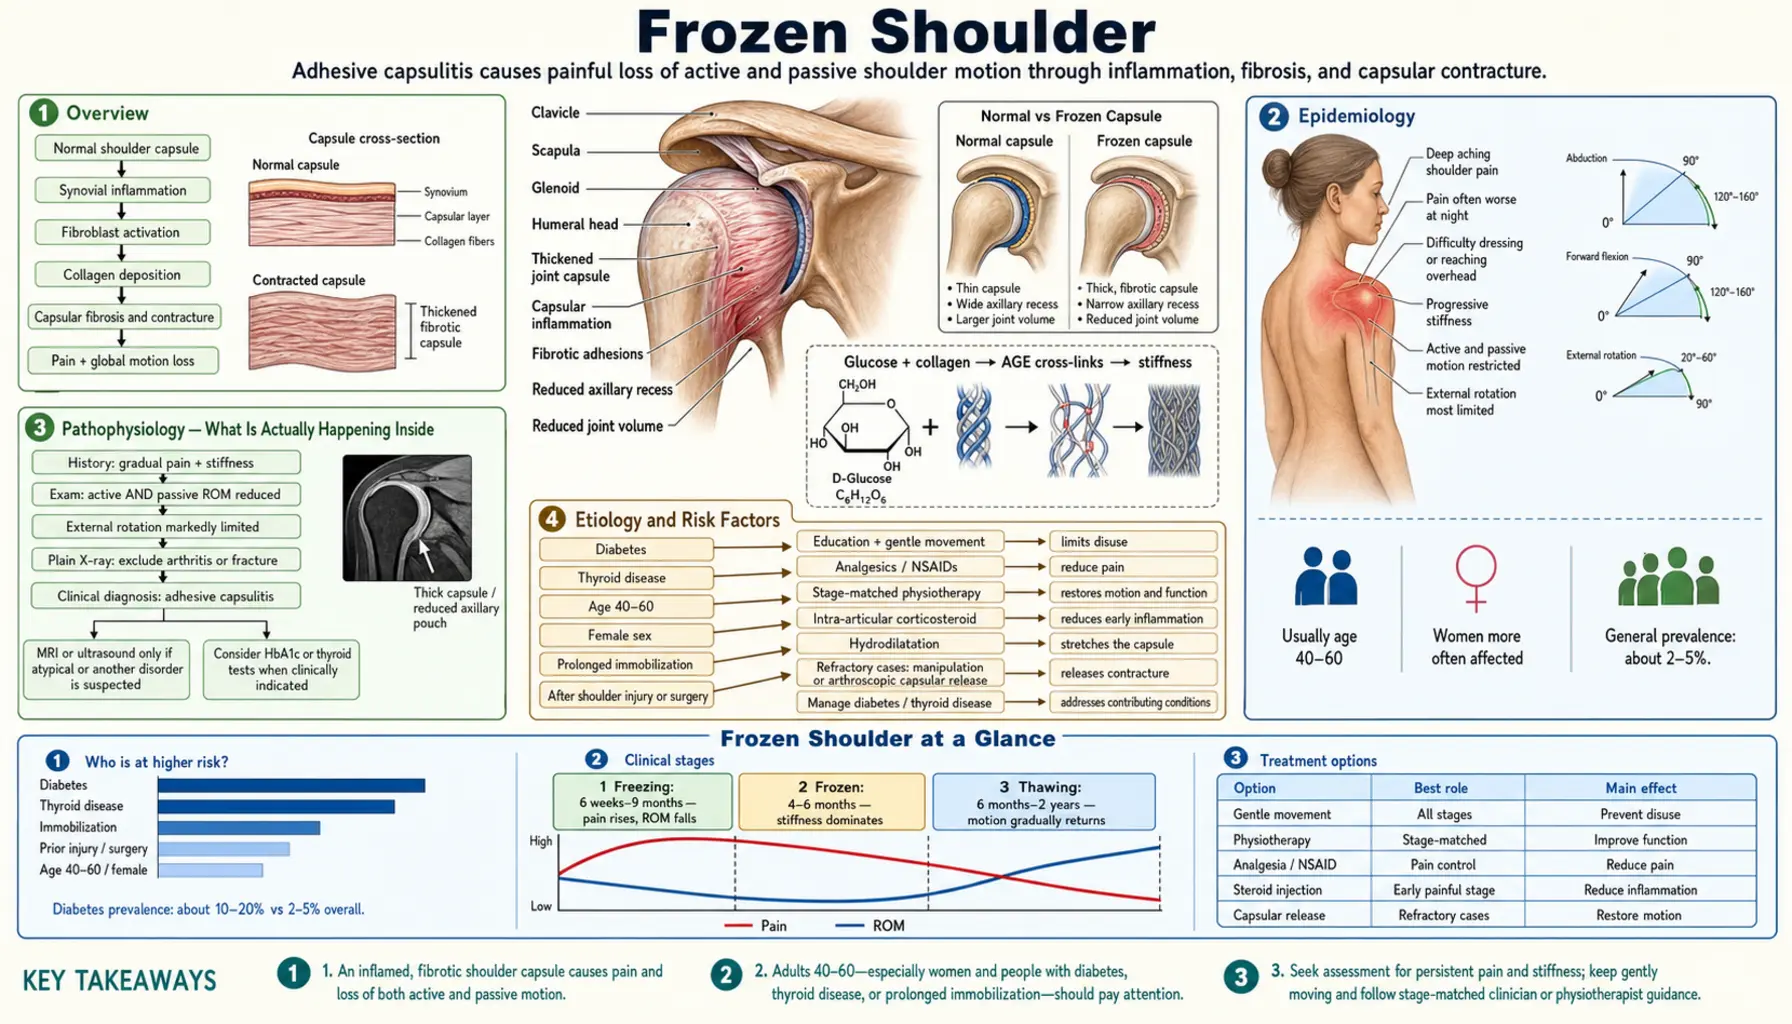
Table of Contents
1. Overview
Frozen shoulder — known in medicine as adhesive capsulitis — is a painful, stiff shoulder that slowly loses its range of motion over months. The thin sleeve of tissue that wraps around the shoulder ball-and-socket joint, called the joint capsule, becomes inflamed, thickens, and tightens. As it contracts, it grips the joint like a shrunken garment, and the shoulder simply stops moving the way it should. The name is apt: the joint really does feel as if it has been frozen in place.
If you have frozen shoulder, the most important thing to understand up front is this: it is slow and frustrating, but it is almost always temporary. The condition runs a natural course over one to three years in most people, and the great majority recover good — often near-normal — function whether or not they have aggressive treatment. That is the honest, double-edged truth. It usually gets better on its own. It also takes a long, exhausting time to do so, and nothing we currently have reliably speeds the whole process up. Knowing what is happening, what to expect, and what genuinely helps can make the long road far easier to walk.
One feature sets frozen shoulder apart from almost every other shoulder problem and is the key to diagnosing it. In frozen shoulder, the shoulder is restricted in both active and passive motion — meaning you cannot lift the arm yourself, and someone else cannot move it for you either, no matter how relaxed you are. In a rotator cuff tear or tendinitis, by contrast, a clinician can usually move your arm through a near-full range even if you cannot move it yourself, because the problem is muscle and tendon, not the capsule. When passive motion is genuinely lost — especially the ability to rotate the arm outward — that points strongly to a frozen, contracted capsule.
2. Epidemiology
Frozen shoulder affects roughly 2–5% of the general population over a lifetime. It is most common in middle age, with a clear peak between 40 and 60 years old, and it is uncommon before 40. Women are affected somewhat more often than men.
In a long-term follow-up of 223 people with primary frozen shoulder (Hand and colleagues, 2008), about one in five (20%) reported symptoms in both shoulders, though rarely at the same time. Once a particular shoulder has fully recovered, it is unusual for the same shoulder to freeze again — true recurrence in the previously affected joint is rare.
The single most striking statistic in frozen shoulder is its link with diabetes. While only a few percent of the general population is affected, prevalence among people with diabetes is far higher. A 2016 meta-analysis of prevalence (18 studies) found that people with diabetes were five times more likely than people without it to have frozen shoulder, with an overall prevalence of about 13% (roughly one in eight); it also estimated that about 30% of people with frozen shoulder have diabetes. People with diabetes also tend to have more severe, more stubborn, and more often bilateral disease. The meta-analysis authors wrote that screening for diabetes should be considered in people who present with frozen shoulder.
3. Pathophysiology — What Is Actually Happening Inside
The shoulder is a ball-and-socket joint with an unusually loose, roomy capsule — that slack is exactly what lets you scratch your back, reach overhead, and throw. In frozen shoulder, that healthy looseness is lost. The process unfolds in two overlapping biological stages:
Inflammation first. Early on, the capsule and its lining (the synovium) become inflammed and engorged with new blood vessels and nerve fibres. This is the painful phase, and the new nerve growth helps explain why early frozen shoulder hurts so much, including at rest and at night.
Fibrosis (scarring) second. Inflammation gives way to a process that looks biologically like an over-active wound-healing response. Cells called fibroblasts multiply and lay down dense, disorganised collagen, and some transform into contractile myofibroblasts — the same cell type responsible for the tightening seen in conditions like Dupuytren's contracture of the hand (which often coexists with frozen shoulder). The capsule, especially the front-lower part and a structure called the rotator interval and coracohumeral ligament, thickens and physically contracts. The joint space shrinks. This is the mechanical reason the shoulder gets stiff: the bag holding the joint has literally tightened and shortened.
Crucially, this is not a problem of "adhesions" or scar tissue gluing surfaces together, despite the old name "adhesive capsulitis." It is a contracture of living, thickened capsule. That distinction matters, because it explains why the stiffness eventually softens and reverses as the abnormal tissue remodels — something true scar adhesions would not do.
4. Etiology and Risk Factors
Frozen shoulder is divided into two broad types, and the difference has a very practical lesson built into it.
Primary (idiopathic) frozen shoulder arises out of the blue, with no clear trigger. "Idiopathic" simply means we do not know the cause. This is the classic form, strongly linked to the metabolic and hormonal risk factors below.
Secondary frozen shoulder follows an identifiable event — a shoulder injury, a fracture or surgery, a rotator cuff problem, or most importantly a period of immobilization (an arm in a sling, a stroke that weakens an arm, recovery from a heart procedure). The pattern is plain: a shoulder that is kept still is a shoulder at risk of freezing. For this reason, care after an injury or operation usually keeps the joint gently moving, within the limits the surgeon sets.
The main risk factors are:
- Diabetes — by far the strongest medical association; both type 1 and type 2, and risk rises with longer disease duration.
- Thyroid disease — both an under-active thyroid (hypothyroidism) and an over-active thyroid are linked to frozen shoulder. When a shoulder freezes for no obvious reason, thyroid function and blood sugar are commonly checked.
- Age 40–60 and female sex.
- Immobilization after injury, surgery, or stroke.
- Other associations including Dupuytren's contracture, Parkinson's disease, and some cardiovascular conditions.
5. Clinical Presentation — The Three Phases
Frozen shoulder is famous for moving through three classic phases. Real people blur the lines between them, and the timelines below are wide on purpose — your course may be faster or slower. But knowing the map helps you understand where you are and what comes next.
Phase 1 — Freezing (painful phase): roughly 6 weeks to 9 months. Pain comes first and dominates. It is a deep, aching pain, often worse than the stiffness at this stage. The hallmark is night pain that disrupts sleep — you cannot lie on that side, and the ache wakes you. As the months pass, motion quietly drains away. This is the most miserable phase, and unfortunately the longest-feeling.
Phase 2 — Frozen (stiff phase): roughly 4 to 12 months. The good news is the sharp pain usually eases. The bad news is the shoulder is now genuinely stuck. Everyday movements become impossible or awkward: reaching behind your back (fastening a bra, tucking in a shirt, reaching a back pocket or wallet), reaching overhead (a high shelf, washing or styling your hair), and reaching out and around (the seatbelt, the back seat of a car). Pain may now mostly appear only at the extremes of movement.
Phase 3 — Thawing (recovery phase): roughly 6 months to 2 years. Slowly, motion returns. It is gradual and uneven, but it is real. Most people regain the lion's share of their function during this phase.
Add it up and you can see why frozen shoulder demands patience: the whole journey commonly takes one to three years. That is the hard truth nobody likes to hear. But the destination, for most people, is a working shoulder.
6. Diagnosis
Frozen shoulder is, above all, a clinical diagnosis — it is made from your history and a physical examination, not from a scan. A skilled clinician can usually recognise it across the room and confirm it in a few minutes.
The defining finding is global restriction of both active and passive movement, with loss of external rotation (rotating the arm outward with the elbow tucked at your side) being especially characteristic. If your clinician asks you to fully relax and then tries to rotate your arm outward and it simply will not go — and it hurts at the end-point — that is the classic frozen-shoulder sign. Because the capsule is what limits external rotation, and the capsule is the problem, this movement is restricted early and reliably. A rotator cuff tear does not do this: with a cuff tear, passive external rotation is usually preserved.
Imaging is used mainly to rule out other things, not to make the diagnosis. Plain X-rays are typically normal in frozen shoulder, and their value is in excluding arthritis, a missed dislocation, a bone problem, or a tumour. Magnetic resonance imaging (MRI) or ultrasound may show a thickened capsule or coracohumeral ligament, but they are usually reserved for confusing cases or to exclude a significant rotator cuff tear when the picture is unclear. When the history and examination fit, an expensive scan adds little to what is already clear.
7. Treatment — The Honest Version
Here is the part where honesty serves you best. The evidence on frozen-shoulder treatment is humbling: no treatment we have reliably and dramatically shortens the natural course of the disease. Most options are aimed at controlling pain and preserving what motion you have while the condition runs through its phases. That is not a counsel of despair — there is genuinely useful help available — but it is the truth, and it lets you make calm decisions instead of chasing a cure that does not exist.
Pain control and patience. Simple analgesia (paracetamol/acetaminophen, anti-inflammatories where safe for you) takes the edge off, especially the night pain. Heat before gentle movement helps many people. Knowing the condition is self-limiting is, in itself, part of the treatment.
Gentle range-of-motion physical therapy — but match it to the phase. This is where people most often go wrong. In the painful freezing phase, aggressive, forceful stretching can backfire, ramping up inflammation and pain and slowing you down. Early on, the goal is gentle movement within your comfort zone — pendulum swings, easy supported reaches — to keep the joint from seizing further. As pain settles in the frozen and thawing phases, more committed stretching becomes both tolerable and worthwhile. The guiding principle is "keep it moving," not "force it open."
Corticosteroid injection — the option with real evidence. A steroid injected into the joint is the intervention with the best supporting trial data, and it can meaningfully reduce pain and speed recovery in the early phases. In a landmark placebo-controlled trial (Carette and colleagues, 2003), intra-articular steroid combined with physiotherapy outperformed physiotherapy alone for early pain and function. The benefit is most pronounced early and tends to be greatest when combined with exercise. It does not cure the disease, but for the right person at the right time it can make the painful phase far more bearable.
A 2020 review that gathered 65 randomised studies (4,097 people) came to a similar conclusion (Challoumas and colleagues). Of all the treatments compared, only a steroid injection into the joint gave a clear short-term benefit for pain and function over no treatment, placebo or physiotherapy — about 1 point less pain on a 10-point scale. Adding a simple home exercise programme of stretches, with or without physiotherapy, to the injection was linked to extra benefit in the medium term (3 to 12 months). The authors found that early injection, in shoulders frozen for less than a year, was linked to better outcomes.
Hydrodilatation (joint distension). Here the joint is injected — usually under imaging guidance — with a larger volume of fluid (saline, often with steroid and local anaesthetic) to gently stretch and expand the tightened capsule. Trials such as Buchbinder's distension studies show short-term improvements in pain and movement. It is a low-risk option, often used when a plain steroid injection has not been enough. A 2023 review of hydrodilatation trials (Poku and colleagues) found that it gives at least a short-lived larger improvement in shoulder disability and in outward rotation of the arm than a steroid injection alone, and the authors described it as possibly preferable to manipulation under anaesthesia because of its lower cost and greater convenience; how much the short-term gain matters in daily life is still unclear.
For stubborn, refractory cases — manipulation or surgery. When the shoulder stays frozen and disabling despite months of conservative care, two more aggressive options exist:
- Manipulation under anaesthesia (MUA) — with you fully asleep and your muscles relaxed, the surgeon forces the shoulder through its range, deliberately tearing the contracted capsule to release it.
- Arthroscopic capsular release — keyhole surgery to precisely cut the thickened capsule and free the joint.
Importantly, the large UK FROST trial (503 adults at 35 UK hospitals, published 2020) compared early structured physiotherapy plus a steroid injection with manipulation under anaesthesia and with arthroscopic capsular release for primary frozen shoulder. At 12 months the average Oxford Shoulder Score (0–48, higher is better) was 40.3 after capsular release, 38.3 after manipulation and 37.2 after physiotherapy plus injection; every difference was smaller than the gap the researchers had set in advance as meaningful, so none of the three was clinically superior. Capsular release carried more risk: 8 serious adverse events, against 2 with manipulation. Structured physiotherapy was the least costly option, but the trial and its 2021 economic analysis (Corbacho and colleagues) found manipulation under anaesthesia the most cost-effective, and capsular release not cost-effective. Surgery has a role for the genuinely refractory minority, but it is not a first move, and it is not a magic shortcut.
The bottom line on treatment: the options studied aim to control the pain and keep the joint gently moving; a steroid injection (especially early) and hydrodilatation have the most trial support among non-surgical options, manipulation or surgery are generally used for the stubborn cases — and most people recover good function. No single treatment compresses the natural timeline dramatically; the value of treatment is in making the long course more comfortable and protecting your range while you heal.
8. Complications
Frozen shoulder is rarely dangerous, but its complications are real and mostly about quality of life:
- Sleep deprivation from relentless night pain in the freezing phase — often the single most wearing part of the condition.
- Persistent stiffness in a minority. Although most people recover well, a subset — disproportionately those with diabetes — are left with some lasting loss of motion, particularly at the extremes (full overhead reach, reaching far behind the back).
- Bilateral disease, with the second shoulder freezing during or after the first.
- Procedure-related risks from the more aggressive treatments: manipulation under anaesthesia carries a small risk of fracture, dislocation, or rotator cuff injury from the force applied, and surgery carries the usual risks of an operation.
- Mood and function — months of pain, broken sleep, and being unable to do simple daily tasks understandably take a toll on mood and work.
9. Prognosis
The prognosis is the most encouraging part of this story, and it is worth repeating clearly: frozen shoulder is usually self-limiting, and most people recover good — often near-complete — function. Long-term follow-up studies (Hand and colleagues, 2008) found that the majority of patients had mild or no symptoms years later, with only a minority left with significant ongoing limitation.
What the prognosis does not promise is speed. Recovery is measured in months to years, not weeks, and the timeline cannot be reliably compressed. A realistic expectation — one to three years from first symptom to substantial recovery — protects you from the despair of feeling that something is "wrong" because you are not better in a month.
Some honest nuances: people with diabetes tend to have a more severe and more prolonged course and a higher chance of some residual stiffness. And while the previously affected shoulder rarely re-freezes, the opposite shoulder may go through the same process later. Even so, for the typical person, the destination is a usable, comfortable shoulder.
10. Prevention
Primary (idiopathic) frozen shoulder largely cannot be prevented — it arrives without warning. But several factors are linked with lower risk or milder disease, especially for the secondary, immobilization-related form:
- Movement after injury or surgery. Within the limits a surgeon or therapist sets, early gentle mobilization after a shoulder injury, fracture, operation, or stroke is the single most protective habit. A shoulder left immobile in a sling is a shoulder at risk of freezing.
- Diabetes and thyroid control. Good blood-sugar control and properly treated thyroid disease may reduce risk and severity, and both are commonly checked when a shoulder freezes without an obvious cause.
- Early stiffness. A shoulder that is starting to lose range — especially the ability to rotate outward or reach behind the back — is in the early phase, before it tightens further. The 2020 review of 65 trials linked an early steroid injection, in shoulders frozen for less than a year, with better outcomes.
11. Recent Research and Advances
Research over the last two decades has steadily reframed frozen shoulder from a mysterious "adhesion" problem into a fibrotic, inflammatory disorder of the capsule — biologically closer to a localized scarring disease. This shift, championed by surgeons such as Tony Bunker, even prompted a serious proposal to rename the condition "contracture of the shoulder" to reflect what is really happening.
Several threads stand out in current work:
- The fibrosis-and-inflammation mechanism. Studies of the diseased capsule have identified active fibroblasts, contractile myofibroblasts, new blood-vessel and nerve growth, and inflammatory cytokines — the same biology seen in other fibrotic contractures. This has opened the door to thinking about anti-fibrotic and anti-inflammatory strategies.
- Comparative-effectiveness trials. The large UK FROST randomized trial and its cost-effectiveness analyses brought hard data to the comparison of treatments: none of the three approaches was clinically superior at 12 months, capsular release carried more serious adverse events, structured physiotherapy plus injection was the least costly, and manipulation under anaesthesia was the most cost-effective.
- Refining injections. Work comparing steroid injection, hydrodilatation, and image-guided techniques continues to clarify who benefits most and when, including head-to-head studies in diabetic versus idiopathic frozen shoulder, which consistently show diabetic shoulders respond but tend to do somewhat less well.
- The natural-history debate. Long-term follow-up studies keep testing the old assumption that frozen shoulder always fully resolves. The emerging, more honest picture is that most people recover very well, but a real minority — again, often those with diabetes — retain some measurable, usually mild, restriction.
Key Research Papers
- Zuckerman JD, Rokito A. Frozen shoulder: a consensus definition. Journal of Shoulder and Elbow Surgery. 2011;20(2):322–325. — doi:10.1016/j.jse.2010.07.008
- Dias R, Cutts S, Massoud S. Frozen shoulder. BMJ. 2005;331(7530):1453–1456. — doi:10.1136/bmj.331.7530.1453
- Lewis J. Frozen shoulder contracture syndrome – aetiology, diagnosis and management. Manual Therapy. 2015;20(1):2–9. — doi:10.1016/j.math.2014.07.006
- Bunker T. Time for a new name for frozen shoulder—contracture of the shoulder. Shoulder & Elbow. 2009;1(1):4–9. — doi:10.1111/j.1758-5740.2009.00007.x
- Carette S, Moffet H, Tardif J, et al. Intraarticular corticosteroids, supervised physiotherapy, or a combination of the two in the treatment of adhesive capsulitis of the shoulder: a placebo-controlled trial. Arthritis & Rheumatism. 2003;48(3):829–838. — doi:10.1002/art.10954
- Buchbinder R, Green S. Effect of arthrographic shoulder joint distension with saline and corticosteroid for adhesive capsulitis. British Journal of Sports Medicine. 2004;38(4):384–385. — doi:10.1136/bjsm.2004.013532
- Page MJ, Green S, Kramer S, et al. Manual therapy and exercise for adhesive capsulitis (frozen shoulder). Cochrane Database of Systematic Reviews. 2014;(8). — doi:10.1002/14651858.cd011275
- Hand C, Clipsham K, Rees JL, Carr AJ. Long-term outcome of frozen shoulder. Journal of Shoulder and Elbow Surgery. 2008;17(2):231–236. — doi:10.1016/j.jse.2007.05.009
- Neviaser AS, Neviaser RJ. Adhesive capsulitis of the shoulder. Journal of the American Academy of Orthopaedic Surgeons. 2011;19(9):536–542. — doi:10.5435/00124635-201109000-00004
- Zreik NH, Malik RA, Charalambous CP. Adhesive capsulitis of the shoulder and diabetes: a meta-analysis of prevalence. Muscles, Ligaments and Tendons Journal. 2016;6(1):26–34. — doi:10.11138/mltj/2016.6.1.026
- Corbacho B, Brealey S, Keding A, et al. Cost-effectiveness of surgical treatments compared with early structured physiotherapy in secondary care for adults with primary frozen shoulder (UK FROST). Bone & Joint Open. 2021;2(8):685–695. — doi:10.1302/2633-1462.28.bjo-2021-0075.r1
- Hwang JT. Arthroscopic capsular release versus manipulation under anesthesia for primary frozen shoulder. Clinics in Shoulder and Elbow. 2020;23(4):167–168. — doi:10.5397/cise.2020.00311
- Neviaser A, Stupay K. Management of adhesive capsulitis. Orthopedic Research and Reviews. 2015;7:83–91. — doi:10.2147/orr.s56317
- Cho CH, Jin HJ, Kim DH. Comparison of clinical outcomes between idiopathic frozen shoulder and diabetic frozen shoulder after a single ultrasound-guided intra-articular corticosteroid injection. Diagnostics. 2020;10(6):370. — doi:10.3390/diagnostics10060370
- Rangan A, Brealey SD, Keding A, et al. Management of adults with primary frozen shoulder in secondary care (UK FROST): a multicentre, pragmatic, three-arm, superiority randomised clinical trial. Lancet. 2020;396(10256):977–989. — PubMed PMID: 33010843
- Challoumas D, Biddle M, McLean M, Millar NL. Comparison of Treatments for Frozen Shoulder: A Systematic Review and Meta-analysis. JAMA Network Open. 2020;3(12):e2029581. — PubMed PMID: 33326025
- Poku D, Hassan R, Migliorini F, Maffulli N. Efficacy of hydrodilatation in frozen shoulder: a systematic review and meta-analysis. British Medical Bulletin. 2023;147(1):121–147. — PubMed PMID: 37496207
Historical Background
The vivid term "frozen shoulder" was popularized by the Boston surgeon Ernest Amory Codman in his 1934 book The Shoulder, where he described a painful, stiff shoulder of slow onset, normal X-rays, and eventual recovery — and candidly admitted it was "difficult to define, difficult to treat, and difficult to explain." Eleven years later, Julius Neviaser coined the more clinical name "adhesive capsulitis" in 1945 after observing thickened, contracted capsule at surgery and arthrography, though we now know "adhesive" is something of a misnomer — the capsule is contracted and fibrotic, not glued by adhesions. The condition's natural history — whether it truly always resolves completely — has been debated ever since, and remains the subject of long-term follow-up studies to this day.
PubMed Topic Searches
Frozen shoulder is an active area of orthopedic, rheumatologic, and rehabilitation research. The PubMed searches below open live, continually updated lists of peer-reviewed studies on adhesive capsulitis — its mechanisms, its strong link with diabetes, and the evidence behind each treatment. Use them to dig deeper or to bring current literature to a conversation with your clinician.
- PubMed: Frozen shoulder / adhesive capsulitis
- PubMed: Adhesive capsulitis and diabetes mellitus
- PubMed: Corticosteroid injection randomized trials
- PubMed: Hydrodilatation and joint distension
- PubMed: Manipulation under anaesthesia
- PubMed: Arthroscopic capsular release
- PubMed: Physical therapy and exercise
- PubMed: Pathophysiology and capsular fibrosis
- PubMed: Natural history and long-term outcome
- PubMed: Adhesive capsulitis and thyroid disease
- PubMed: External rotation loss and diagnosis
- PubMed: UK FROST comparative-effectiveness trial
Connections
- Orthopedics
- Rheumatoid Arthritis in the Shoulder — an inflammatory cause of shoulder pain and stiffness to distinguish from adhesive capsulitis
- Tendinitis
- Carpal Tunnel Syndrome
- Herniated Disc
- Sciatica
- Osteoarthritis
- Rheumatoid Arthritis
- Fibromyalgia
- Diabetes
- Hypothyroidism
- Insulin Resistance
- Chronic Pain