⚠ Evidence warning: Clinical trials or other evidence do not support the claims that chromium picolinate is generally safe at recommended dosages and that trivalent chromium supplements are generally well tolerated up to 1,000 micrograms a day. This page keeps it as a report of what people, websites or other media say.
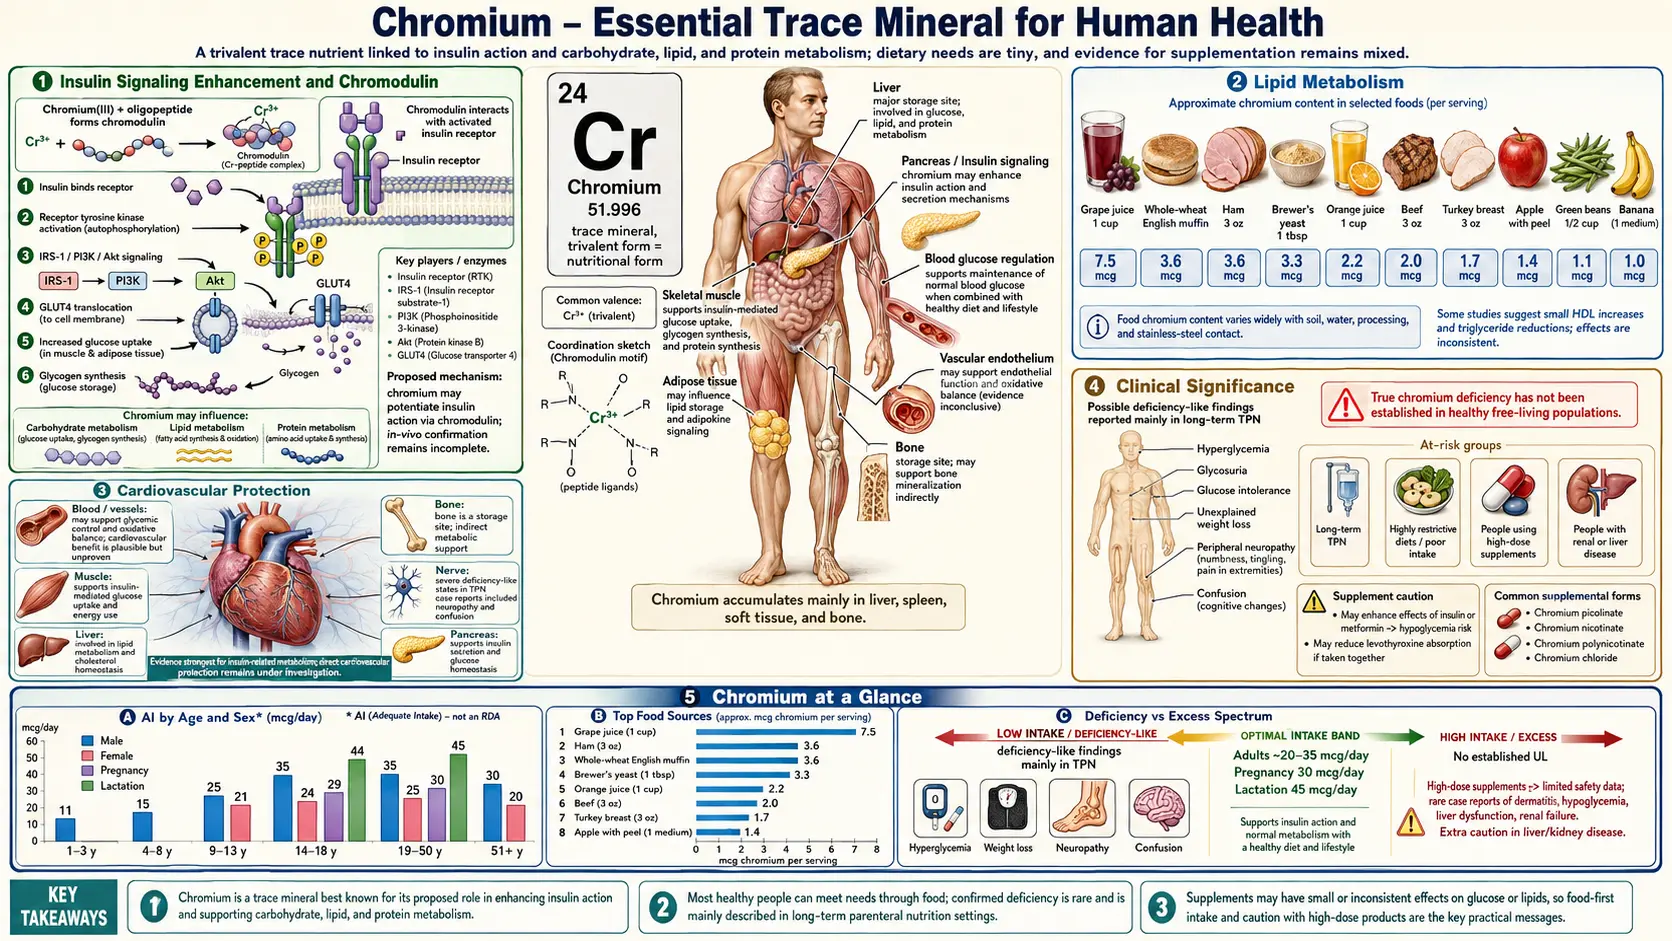
Chromium – Essential Trace Mineral for Human Health
Interactive Visualization Blood Sugar & Insulin — eat a meal and watch glucose move Watch insulin escort glucose into cells and the liver bank glycogen, then switch on insulin resistance and see the curve change. Launch → Interactive Visualization Inside the Beta Cell — release insulin yourself Zoom inside a beta cell and watch glucose close the K-ATP channel, calcium flood in, and insulin granules pop out — then force it with a sulfonylurea or silence it with diazoxide. Launch →
Table of Contents
- Insulin Signaling Enhancement and Chromodulin
- Glucose Metabolism
- Lipid Metabolism
- Macronutrient Metabolism
- Body Composition
- Cardiovascular Protection
- Forms of Supplemental Chromium
- Clinical Significance
- Deficiency and Excess
- Connections
- Featured Videos
Chromium is an essential trace mineral that plays a central role in the regulation of insulin signaling, glucose metabolism, and lipid homeostasis. Although required only in microgram quantities, chromium is indispensable for normal metabolic function. The biologically active trivalent form (Cr3+) is the form relevant to human nutrition, whereas hexavalent chromium (Cr6+) is an industrial toxicant with no nutritional role. The adequate intake (AI) for chromium ranges from 20 to 35 micrograms per day for adults, depending on age and sex.
Insulin Signaling Enhancement and Chromodulin
The most well-characterized biological function of chromium involves its role in potentiating the action of insulin at the cellular level. Chromium does not replace insulin, nor does it independently stimulate glucose uptake. Rather, it amplifies the signal that insulin initiates upon binding to its receptor on target cells such as muscle, liver, and adipose tissue.
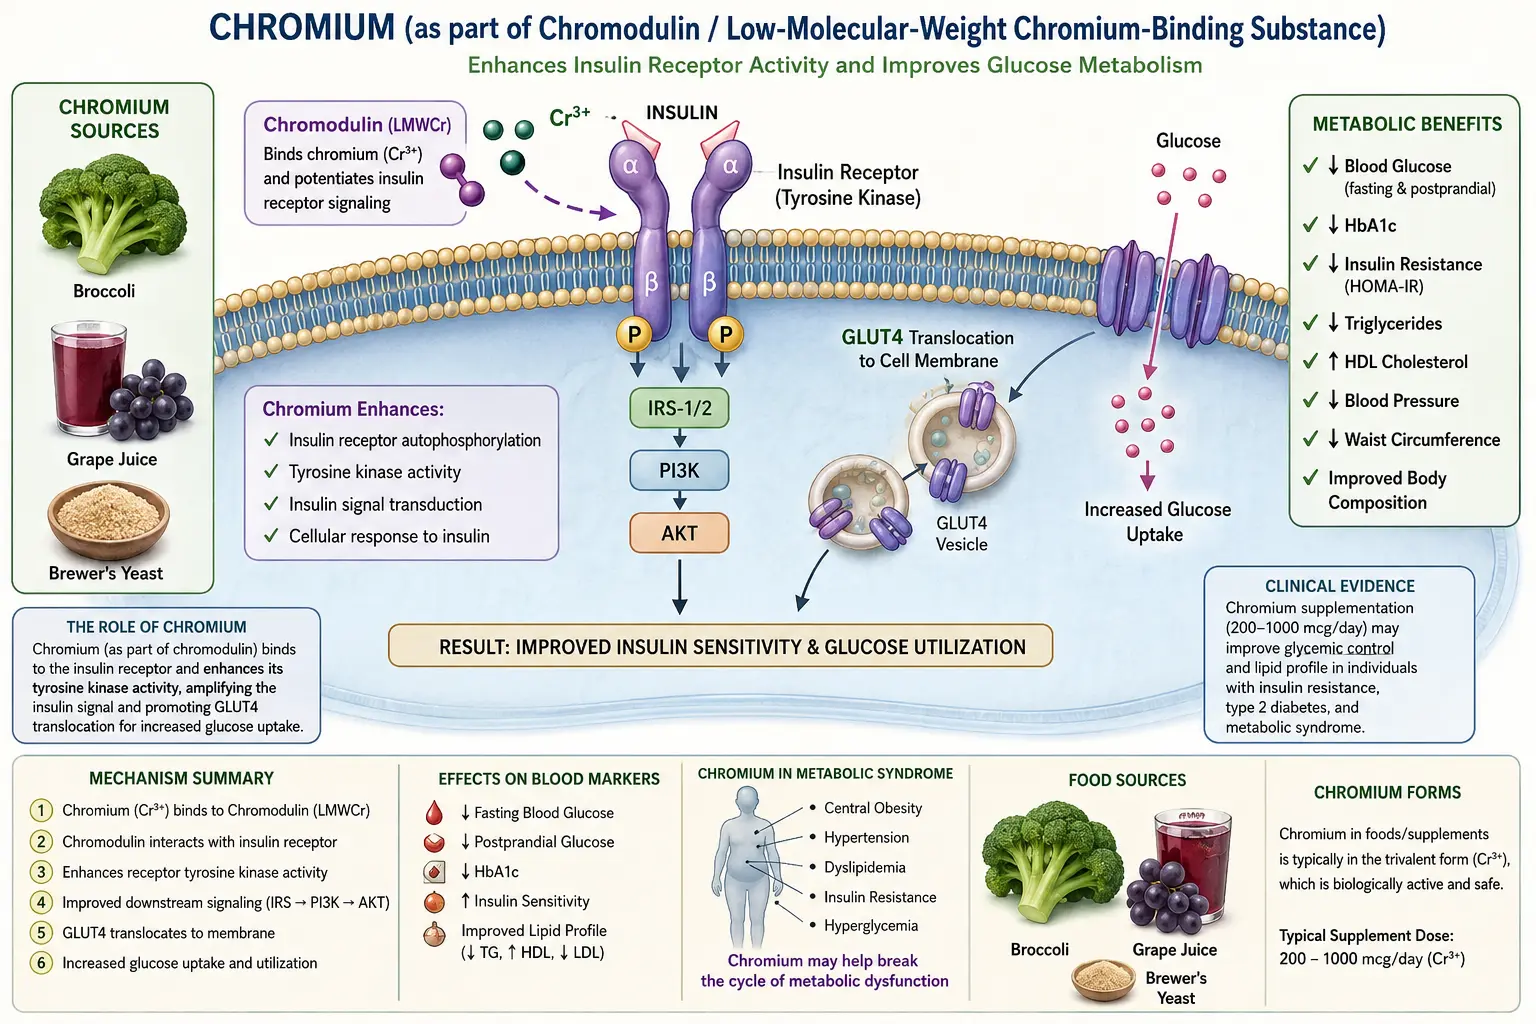
- Chromodulin (low-molecular-weight chromium-binding substance): Chromodulin is a small oligopeptide composed of glycine, cysteine, aspartate, and glutamate residues that binds four chromic ions. When insulin binds to the alpha subunit of the insulin receptor, the receptor undergoes autophosphorylation. Chromodulin is then recruited to the intracellular beta subunit of the activated receptor, where it sustains and amplifies the tyrosine kinase activity of the receptor. This amplification enhances downstream signaling cascades, including the PI3K/Akt pathway, which governs glucose transporter (GLUT4) translocation to the cell membrane.
- Insulin receptor potentiation: In the presence of adequate chromium, the insulin receptor exhibits increased sensitivity to circulating insulin. This means that a given concentration of insulin produces a greater biological effect, improving the efficiency of glucose clearance from the bloodstream. In chromium-deficient states, insulin resistance may develop because the receptor signaling cascade operates at diminished capacity.
- Transferrin-mediated chromium transport: Chromium circulates in the blood bound to transferrin, the same iron-transport protein. When insulin levels rise after a meal, chromium is mobilized from transferrin and delivered to insulin-sensitive tissues, where it is incorporated into chromodulin. This insulin-dependent mobilization ensures that chromium is available precisely when it is needed to enhance post-prandial glucose disposal.
Glucose Metabolism
Chromium exerts its most significant metabolic effects on the regulation of blood glucose. Through its amplification of insulin signaling, chromium influences multiple steps in glucose homeostasis.
- GLUT4 translocation: By enhancing insulin receptor kinase activity, chromium promotes the movement of GLUT4 glucose transporters from intracellular vesicles to the plasma membrane of skeletal muscle and adipose cells. This increases the rate of insulin-stimulated glucose uptake into these tissues, lowering circulating blood glucose levels after meals.
- Glycogen synthesis: Chromium supports insulin-mediated activation of glycogen synthase, the enzyme responsible for converting glucose into glycogen for storage in the liver and skeletal muscle. Adequate glycogen stores are essential for maintaining blood glucose levels between meals and during physical activity.
- Hepatic glucose output: Insulin normally suppresses hepatic gluconeogenesis and glycogenolysis. By enhancing insulin's effectiveness at the liver, chromium contributes to the appropriate suppression of endogenous glucose production in the fed state, preventing excessive glucose release into the circulation.
- Fasting glucose regulation: Clinical studies have demonstrated that chromium supplementation can modestly reduce fasting blood glucose levels in individuals with impaired glucose tolerance or type 2 diabetes. The effect is more pronounced in individuals who are chromium-deficient or who exhibit significant insulin resistance.
Lipid Metabolism
Chromium influences lipid metabolism through both insulin-dependent and insulin-independent pathways. Dyslipidemia frequently accompanies insulin resistance, and by improving insulin sensitivity, chromium can positively affect the lipid profile.
- Total cholesterol reduction: Several clinical trials have shown that chromium supplementation can reduce total cholesterol levels, particularly in individuals with elevated baseline values. The mechanism involves improved insulin-mediated regulation of hepatic cholesterol synthesis via HMG-CoA reductase activity.
- Low-density lipoprotein (LDL) cholesterol: Chromium may reduce low-density lipoprotein (LDL) cholesterol by enhancing low-density lipoprotein receptor expression on hepatocytes, increasing the clearance of low-density lipoprotein particles from the circulation. This effect contributes to reduced atherogenic risk.
- High-density lipoprotein (HDL) cholesterol elevation: Some studies report modest increases in high-density lipoprotein (HDL) cholesterol with chromium supplementation, which is associated with improved reverse cholesterol transport and cardiovascular protection.
- Triglyceride reduction: Chromium supplementation has been associated with reductions in serum triglyceride levels. Improved insulin sensitivity enhances the activity of lipoprotein lipase in peripheral tissues, accelerating the clearance of triglyceride-rich lipoproteins from the blood.
Macronutrient Metabolism
Beyond its prominent role in glucose and lipid metabolism, chromium influences the broader metabolic handling of macronutrients.
- Protein metabolism: Insulin is an anabolic hormone that promotes amino acid uptake into skeletal muscle and stimulates protein synthesis. By amplifying insulin signaling, chromium indirectly supports the incorporation of amino acids into structural and functional proteins. This has implications for muscle maintenance, recovery from exercise, and wound healing.
- Carbohydrate utilization: Chromium enhances the efficiency of carbohydrate oxidation for energy production by improving the cellular uptake and intracellular processing of glucose. This is particularly relevant during periods of increased energy demand such as physical exercise.
- Fat oxidation and storage: Through its effects on insulin sensitivity, chromium modulates the balance between fat storage and fat oxidation. Improved insulin signaling in adipose tissue regulates lipolysis and lipogenesis, helping to maintain appropriate energy balance.
Body Composition
The influence of chromium on body composition has been a subject of considerable research interest, particularly in the context of weight management and athletic performance.
- Lean body mass: Some studies have reported that chromium supplementation, particularly as chromium picolinate, may promote modest increases in lean body mass when combined with resistance training. The proposed mechanism involves enhanced insulin-mediated amino acid uptake and protein synthesis in skeletal muscle.
- Fat mass reduction: Certain clinical trials have demonstrated small but statistically significant reductions in body fat percentage with chromium supplementation. Improved insulin sensitivity may reduce the tendency toward lipogenesis and promote more efficient fat oxidation.
- Appetite regulation: Preliminary research suggests that chromium may influence appetite and food cravings, particularly for carbohydrates and sweets. This effect may be mediated through improved glucose regulation in the brain and modulation of serotonin and norepinephrine signaling pathways involved in satiety.
Cardiovascular Protection
Chromium contributes to cardiovascular health through multiple interconnected pathways related to its metabolic functions.
- Endothelial function: Insulin resistance is associated with endothelial dysfunction, which is an early step in the development of atherosclerosis. By improving insulin sensitivity, chromium may help preserve the ability of the endothelium to produce nitric oxide, a vasodilator that protects against vascular inflammation and plaque formation.
- Anti-inflammatory effects: Chromium supplementation has been associated with reductions in markers of systemic inflammation, including C-reactive protein (CRP) and pro-inflammatory cytokines such as tumor necrosis factor-alpha. Chronic low-grade inflammation is a recognized driver of cardiovascular disease.
- Blood pressure: While the evidence is less consistent, some studies suggest that chromium supplementation may contribute to modest reductions in blood pressure, likely mediated through improved insulin sensitivity and endothelial function.
- Oxidative stress reduction: Chromium may reduce oxidative stress by decreasing the formation of advanced glycation end products (AGEs), which are generated when blood glucose levels remain chronically elevated. AGEs contribute to vascular damage and accelerated atherosclerosis.
Forms of Supplemental Chromium
Chromium supplements are available in several forms, which differ in their bioavailability, absorption, and clinical evidence base.
- Chromium picolinate: This is the most widely studied form of supplemental chromium, in which trivalent chromium is chelated with picolinic acid. The picolinic acid moiety enhances intestinal absorption and cellular uptake. Chromium picolinate has been used in the majority of clinical trials examining chromium's effects on glucose metabolism, lipid profiles, and body composition. It is generally considered safe at recommended dosages. There is no officially recommended supplement dose: the Institute of Medicine (IOM) set only an Adequate Intake (35 micrograms per day for young men and 25 for young women) and set no Tolerable Upper Intake Level; case reports of kidney and liver injury with high-dose chromium picolinate are described under Safety considerations below.
- Chromium polynicotinate (niacin-bound chromium): In this form, chromium is complexed with niacin (vitamin B3), mimicking the structure of glucose tolerance factor (GTF), a naturally occurring chromium complex identified in brewer's yeast. Chromium polynicotinate is well-absorbed and has demonstrated efficacy in studies examining insulin sensitivity and lipid metabolism.
- Chromium chloride: This inorganic salt form of chromium has lower bioavailability compared to the organic chelated forms. It was used in early chromium research but has largely been superseded by picolinate and polynicotinate forms in modern supplementation.
- Chromium histidinate: A newer chelated form in which chromium is bound to the amino acid histidine. Early research suggests favorable absorption characteristics and potential benefits for glucose metabolism, though the clinical evidence base is less extensive than for picolinate.
Clinical Significance
Chromium deficiency, while relatively uncommon in the general population, can produce clinically significant metabolic disturbances. Populations at increased risk of inadequate chromium status include individuals with type 2 diabetes, older adults, people consuming highly refined diets low in whole grains and vegetables, and patients receiving long-term parenteral nutrition without chromium supplementation.
- Signs of deficiency: Chromium deficiency manifests as impaired glucose tolerance, elevated fasting insulin levels, increased total and low-density lipoprotein cholesterol, decreased high-density lipoprotein cholesterol, and peripheral neuropathy. In severe cases documented in patients on chromium-free parenteral nutrition, frank hyperglycemia unresponsive to insulin was observed and resolved upon chromium repletion.
- Type 2 diabetes: Numerous clinical trials have evaluated chromium supplementation in patients with type 2 diabetes. The reviews of these trials disagree. A 2014 meta-analysis of 25 randomized trials (Suksomboon and colleagues, PubMed PMID: 24635480) found that chromium lowered hemoglobin A1c (HbA1c) by 0.55 percentage points and fasting plasma glucose by 1.15 mmol/L on average, including in people whose blood sugar was poorly controlled at the start. A 2016 review of 20 randomized trials by scientists at the National Institutes of Health Office of Dietary Supplements (Costello and colleagues, PubMed PMID: 27261273) found that only a few trials reached clinically meaningful treatment goals (fasting glucose in 5 of 20, HbA1c in 3 of 14) and concluded that chromium supplements have limited effectiveness. In its 2005 qualified health claim for chromium picolinate, the U.S. Food and Drug Administration (FDA) allowed the statement that one small study suggests it may reduce the risk of insulin resistance and possibly type 2 diabetes, while concluding that the existence of such a relationship is “highly uncertain.” However, chromium supplementation is not a substitute for standard diabetes management including diet, exercise, and prescribed medications.
- Metabolic syndrome: Given chromium's effects on insulin sensitivity, glucose metabolism, and lipid profiles, supplementation has been investigated as an adjunctive therapy for metabolic syndrome. Improvements in multiple components of the syndrome, including waist circumference, triglycerides, and fasting glucose, have been reported in some trials.
- Dietary sources: Chromium is found in a variety of foods including brewer's yeast, broccoli, grape juice, whole grains, nuts, green beans, potatoes, and certain meats. Food processing and refining significantly reduce chromium content, which is one reason why modern diets may provide suboptimal amounts of this mineral.
- Safety considerations: Trivalent chromium supplements are generally well tolerated at doses up to 1,000 micrograms per day. The Institute of Medicine's 2001 review set no Tolerable Upper Intake Level (UL) for trivalent chromium, because few serious adverse effects have been linked to chromium from food, but it lists reports of harm at high intakes: chronic kidney damage (interstitial nephritis) attributed to chromium picolinate in two case reports, reports of liver injury in humans, and muscle breakdown (rhabdomyolysis) in reports that did not rule out other causes. The same review notes that people with existing kidney or liver disease may be particularly susceptible to excess chromium. In one of those case reports (Cerulli and colleagues 1998, PubMed PMID: 9562138), a 33-year-old woman who had taken 1,200–2,400 micrograms of chromium picolinate a day for 4–5 months to lose weight developed anemia, liver injury (liver enzymes 15–20 times normal) and kidney failure that needed dialysis; a year later her laboratory values were back to normal. Because chromium's effect on blood sugar could add to that of insulin or oral diabetes medicines, the combination could increase the risk of low blood sugar (hypoglycemia); shakiness, sweating, a fast heartbeat, hunger and confusion are the warning signs of low blood sugar.
Deficiency and Excess
Too little or too much chromium can both cause problems. True nutritional (trivalent) chromium deficiency is uncommon and mainly affects people on long-term chromium-free parenteral nutrition, where it impairs glucose tolerance; meanwhile, the toxic concern is not dietary chromium but industrial hexavalent chromium (Cr6+) exposure. For a full, patient-friendly guide to the symptoms, causes, and treatment, see Chromium Deficiency: What the Evidence Shows and Chromium Toxicity: Symptoms, Causes, and Risks.
Connections
- All Minerals
- Inside the Beta Cell: How Insulin Is Released — interactive animation
- Blood Sugar & Insulin — interactive animation
- Chromium Deficiency: What the Evidence Shows
- Chromium Toxicity: Symptoms, Causes, and Risks
- Hexavalent Chromium (Chromium-6)
- Chromium Benefits Deep Dive
- Chromium for Blood Sugar
- Chromium for Insulin Sensitivity
- Chromium for Lipid Profile
- Chromium for Weight Management
- Insulin Resistance
- Diabetes
- Metabolic Syndrome
- Polycystic Ovary Syndrome
- Blood Sugar
- Fasting
- Hemoglobin A1C
- Fasting Insulin
- Atherosclerosis
- Obesity
- Iron
- Vitamin B3
- Cinnamon
- Cardiovascular Disease
- Peripheral Neuropathy
- Gestational Diabetes
- Berberine
- Conditions on this site that reference this page: Prediabetes · Type 2 Diabetes · Endocrinology
- Blood Sugar Remedies — the full index of herbs, nutrients, foods and practices that act on blood glucose