Cardio-Renal Protection: Sodium-Glucose Cotransporter-2 Inhibitors and Glucagon-Like Peptide-1 Agonists
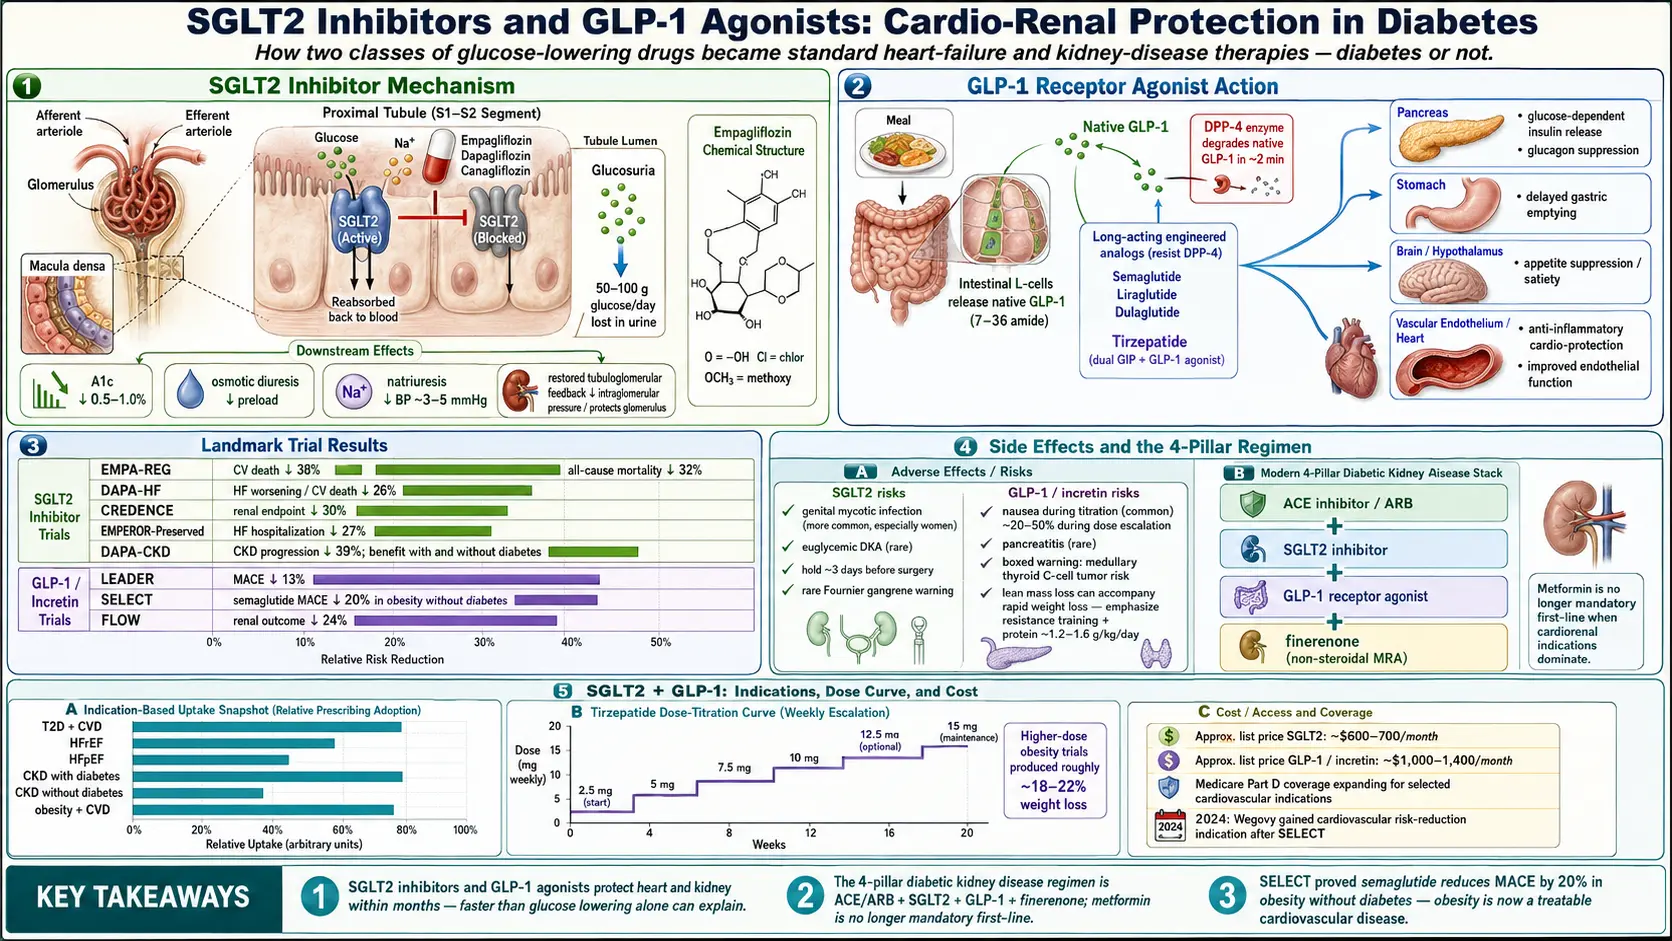
Table of Contents
- The Paradigm Shift — From Safety Trials to Lifesaving Drugs
- Sodium-Glucose Cotransporter-2 Inhibitors — How They Work
- The Sodium-Glucose Cotransporter-2 Drug List
- Landmark Cardiovascular Trials
- Heart Failure Trials — DAPA-HF, EMPEROR, DELIVER
- Renal Trials — CREDENCE, DAPA-CKD, EMPA-KIDNEY
- Sodium-Glucose Cotransporter-2 Side Effects & Safety
- Glucagon-Like Peptide-1 Receptor Agonists — How They Work
- The Glucagon-Like Peptide-1 Drug List
- Glucagon-Like Peptide-1 Cardiovascular & Renal Trials
- Weight Loss, SELECT, and Obesity as a Disease
- Glucagon-Like Peptide-1 Side Effects & Safety
- Combining Sodium-Glucose Cotransporter-2 + Glucagon-Like Peptide-1 — The Emerging Standard
- Finerenone — The Third Pillar for Diabetic Kidney Disease
- Residual Risk — Icosapent Ethyl and REDUCE-IT
- Cost, Insurance, and Access
- Non-Diabetic Uses
- Who the Outcome Trials Studied
- Key Research Papers
- Connections
- Featured Videos
The Paradigm Shift — From Safety Trials to Lifesaving Drugs
In 2008, after the rosiglitazone controversy suggested a diabetes drug could lower blood sugar while raising heart attack risk, the U.S. Food and Drug Administration (FDA) issued a new mandate: every new glucose-lowering drug for type 2 diabetes had to prove cardiovascular safety in a large outcome trial before approval. The goal was modest — show the drug does not kill people. The result was one of the most important accidents in modern medicine.
Starting with EMPA-REG OUTCOME in 2015, these mandatory safety trials began showing the opposite of what regulators expected. The new drugs did not just fail to harm the heart — they prevented heart attacks, hospitalizations for heart failure, kidney failure, and death. Benefits appeared within months, too fast to be explained by glucose lowering alone. The trials forced cardiologists and nephrologists to rewrite guidelines that had stood for decades, and forced pharmaceutical companies to re-run the same trials in patients without diabetes — where the drugs worked just as well.
Today, two drug classes dominate this revolution: sodium-glucose cotransporter-2 (SGLT2) inhibitors (the “-flozins”) and glucagon-like peptide-1 (GLP-1) receptor agonists (GLP-1s) (the “-tides” plus tirzepatide). Their outcome trials in people with type 2 diabetes and heart or kidney disease are described below.
Sodium-Glucose Cotransporter-2 Inhibitors — How They Work
Every day your kidneys filter about 180 grams of glucose out of the blood — and then, under normal circumstances, reabsorb essentially all of it before it reaches the urine. The reabsorption is done mostly by a protein called sodium-glucose cotransporter 2, sitting in the early part of the proximal tubule. Sodium-glucose cotransporter-2 pulls glucose back into the bloodstream and drags a sodium ion along with it.
Sodium-glucose cotransporter-2 inhibitors block that protein. The result is that roughly 50–100 grams of glucose spill into the urine every day, along with the sodium that would have been reabsorbed with it. This triggers four simultaneous effects, all therapeutic:
- Glucose lowering — hemoglobin A1c drops by about 0.5 to 1.0 percentage points, without causing hypoglycemia (the drug stops working as blood sugar approaches normal).
- Osmotic diuresis — the spilled glucose drags water with it, gently reducing fluid overload. This is why the heart-failure benefit kicks in within weeks.
- Natriuresis — sodium loss lowers blood pressure by roughly 3–5 mmHg systolic, adding to cardiovascular benefit.
- Tubuloglomerular feedback restoration — the sodium reaching the distal tubule signals the glomerulus to relax its overworked filtration pressure, protecting the kidney long term. This is the mechanism behind the renal outcomes.
Beyond the kidney, sodium-glucose cotransporter-2 inhibitors modestly shift fuel metabolism toward ketones, reduce cardiac preload, lower uric acid, and improve erythropoiesis (hematocrit rises 2–3% on therapy). The whole package adds up to something that behaves less like a glucose drug and more like a gentle diuretic, antihypertensive, and cardiac protectant rolled into one.
The Sodium-Glucose Cotransporter-2 Drug List
- Empagliflozin — The most thoroughly studied. Approved for type 2 diabetes, heart failure with reduced ejection fraction (HFrEF), heart failure with preserved ejection fraction (HFpEF), and chronic kidney disease. Dose: 10 mg once daily, optional increase to 25 mg.
- Dapagliflozin — Approved for type 2 diabetes, HFrEF, HFpEF, and chronic kidney disease (CKD). Dose: 10 mg once daily.
- Canagliflozin — The first to show renal benefit (CREDENCE). Dose: 100–300 mg once daily. Carries a slightly higher amputation signal in CANVAS, which has not been reproduced consistently.
- Ertugliflozin — Approved for type 2 diabetes only; its outcome trial (VERTIS CV) was neutral on major adverse cardiovascular events (MACE: cardiovascular death, heart attack and stroke), so it sits below the other three for cardio-renal indications.
- Bexagliflozin — the newest entrant, approved 2023. Works the same way as the others but has no completed outcomes trial yet, so it is usually chosen for cost rather than evidence.
Landmark Cardiovascular Trials
EMPA-REG OUTCOME (Zinman and colleagues, NEJM 2015). 7,020 patients with type 2 diabetes and established cardiovascular disease were randomized to empagliflozin or placebo on top of standard care. After a median 3.1 years, empagliflozin reduced cardiovascular death by 38%, all-cause mortality by 32%, and heart failure hospitalizations by 35%. The mortality curves separated within three months — far too fast for glucose lowering to explain. Cardiology was forced to pay attention.
CANVAS (canagliflozin, 2017) confirmed the composite MACE benefit in a broader population including primary-prevention diabetics. DECLARE-TIMI 58 (dapagliflozin, 2019) extended the evidence to lower-risk patients; it did not lower MACE (hazard ratio 0.93, 95% confidence interval 0.84–1.03) but lowered the combined rate of cardiovascular death or heart-failure hospitalization (hazard ratio 0.83), reflecting fewer heart-failure hospitalizations. Together, these three trials established sodium-glucose cotransporter-2 inhibition as a disease-modifying therapy in type 2 diabetes with cardiovascular risk.
Heart Failure Trials — DAPA-HF, EMPEROR, DELIVER
The next wave of trials asked a question nobody had taken seriously: do these drugs work in people without diabetes?
DAPA-HF (McMurray and colleagues, NEJM 2019) randomized 4,744 patients with heart failure and reduced ejection fraction (HFrEF) to dapagliflozin or placebo, regardless of diabetes status. Dapagliflozin cut the composite of heart-failure death or hospitalization by 26%, with nearly identical benefit in diabetics and non-diabetics. EMPEROR-Reduced (2020) confirmed the effect with empagliflozin. HFrEF guidelines rewrote themselves in under a year.
EMPEROR-Preserved (2021) tackled the much harder condition of heart failure with preserved ejection fraction (HFpEF) — a disease with no effective drugs until that point. Empagliflozin lowered the combined risk of cardiovascular death or heart-failure hospitalization (13.8% vs 17.1%; hazard ratio 0.79), mainly through fewer heart-failure hospitalizations (total heart-failure hospitalizations 27% lower); the trial did not show a mortality benefit. DELIVER (2022) replicated the finding with dapagliflozin. For millions of patients with “diastolic dysfunction” who had been told there was nothing to do, these trials showed a drug class that reduced heart-failure hospitalizations.
Renal Trials — CREDENCE, DAPA-CKD, EMPA-KIDNEY
CREDENCE (Perkovic and colleagues, NEJM 2019) randomized 4,401 patients with type 2 diabetes and overt diabetic nephropathy to canagliflozin or placebo. The trial was stopped early for benefit: canagliflozin reduced the composite renal endpoint (end-stage kidney disease, doubling of creatinine, or death from kidney or cardiovascular causes) by 30%. Dialysis rates fell. It was the first dedicated renal-outcome trial in diabetes to show a kidney-protective drug effect in a generation.
DAPA-CKD (2020) extended the benefit to patients without diabetes. EMPA-KIDNEY (2023) broadened the evidence to an even wider chronic kidney disease population, including many with proteinuria below the diabetic-nephropathy threshold. Today sodium-glucose cotransporter-2 inhibitors are U.S. Food and Drug Administration-approved for chronic kidney disease whether the patient has diabetes or not.
Sodium-Glucose Cotransporter-2 Side Effects & Safety
- Genital mycotic infections — the most common side effect. Sugar in the urine feeds yeast. Incidence is roughly 5–10% in women, 2–5% in men (uncircumcised men higher). Most episodes respond to a single dose of oral fluconazole or topical antifungal. Good local hygiene prevents recurrence.
- Euglycemic diabetic ketoacidosis (DKA) — a rare but dangerous ketoacidosis that can occur at near-normal blood glucose, so the diagnosis is often missed. Triggered by fasting, surgery, severe illness, low-carb diets, or sudden insulin reduction. The drug labels say to withhold these drugs at least 3 days, if possible, before surgery or procedures with prolonged fasting, and, if possible, during temporary situations that could predispose to ketoacidosis, until the person is stable and eating again.
- Volume depletion — the diuretic effect can cause dizziness, especially in older adults or those on loop diuretics. Loop-diuretic doses are often reduced when a sodium-glucose cotransporter-2 inhibitor is started.
- Fournier’s gangrene — a necrotizing infection of the perineum. Extraordinarily rare; the drug labels list it under Warnings and Precautions (it is not a boxed warning) and describe it as life-threatening and requiring urgent surgery. Pain or tenderness, redness, or swelling in the genital or perianal area, with fever or feeling unwell, are the warning signs; hospitals treat it as an emergency.
- Small rise in low-density lipoprotein (LDL) cholesterol (roughly 3–5 mg/dL) — clinically minor and outweighed by the cardiovascular benefit.
- Transient estimated glomerular filtration rate (eGFR) dip in the first 2–4 weeks (3–5 mL/min), followed by long-term preservation of kidney function. This is the drug working, not harming.
Glucagon-Like Peptide-1 Receptor Agonists — How They Work
Glucagon-like peptide-1 is a hormone released by the gut within minutes of a meal. It tells the pancreas to release insulin (but only when blood sugar is elevated — so it does not cause hypoglycemia on its own), tells the pancreas to stop releasing glucagon, tells the stomach to empty more slowly (so a meal lasts longer as a drip-feed instead of a flood), and acts on brain centers in the hypothalamus and brainstem to reduce appetite.
Native glucagon-like peptide-1 is destroyed within two minutes by the enzyme dipeptidyl peptidase-4 (DPP-4). Glucagon-like peptide-1 receptor agonists are engineered versions of the hormone — or entirely synthetic molecules that bind the same receptor — modified to resist breakdown. Half-lives range from hours (exenatide twice daily) to a week or more (semaglutide, dulaglutide). In addition to the metabolic effects, glucagon-like peptide-1 receptors sit on vascular endothelium, cardiomyocytes, and inflammatory cells, which is where the cardiovascular benefit is thought to originate.
The Glucagon-Like Peptide-1 Drug List
- Semaglutide — one molecule sold under separate brand names for diabetes and for weight loss: a weekly injection for type 2 diabetes, a daily tablet for type 2 diabetes (the first oral glucagon-like peptide-1), and a higher-dose weekly injection for obesity.
- Tirzepatide — A dual glucose-dependent insulinotropic polypeptide (GIP) + glucagon-like peptide-1 agonist, not a pure glucagon-like peptide-1. Adds a second incretin receptor and produces the strongest weight loss of any drug ever approved (15–22% in trials). Sold under separate brand names for type 2 diabetes and for obesity.
- Liraglutide — Once-daily injection, sold under separate brand names for type 2 diabetes and for obesity. The first glucagon-like peptide-1 to show a cardiovascular mortality benefit.
- Dulaglutide — Weekly injection; simple auto-injector. Best cardiovascular data in primary prevention (REWIND).
- Exenatide — The original glucagon-like peptide-1. Weekly extended-release or twice-daily forms. Rarely first-line now.
Glucagon-Like Peptide-1 Cardiovascular & Renal Trials
LEADER (Marso and colleagues, NEJM 2016) randomized 9,340 patients with type 2 diabetes at high cardiovascular risk to liraglutide or placebo. Liraglutide reduced the composite MACE endpoint (cardiovascular death, non-fatal myocardial infarction (MI), non-fatal stroke) by 13%, with a particularly clear cardiovascular mortality benefit. It was the first glucagon-like peptide-1 outcomes trial to turn positive.
SUSTAIN-6 (semaglutide injectable, 2016) extended the benefit. PIONEER 6 (oral semaglutide, 2019) was a safety trial: oral semaglutide was not inferior to placebo for MACE (hazard ratio 0.79, 95% confidence interval 0.57–1.11), which is not a statistically significant reduction. REWIND (dulaglutide, 2019) was important because most of its enrolled patients had no prior cardiovascular event — it demonstrated benefit in primary prevention, broadening the treatable population substantially.
On the renal side, the FLOW trial (semaglutide, 2024) was stopped early for overwhelming benefit: semaglutide slowed the progression of chronic kidney disease in type 2 diabetes by 24%, meaning glucagon-like peptide-1 agonists now join sodium-glucose cotransporter-2 inhibitors as nephroprotective drugs rather than just metabolic ones.
Weight Loss, SELECT, and Obesity as a Disease
Weight loss on these drugs is not a side effect — it is now a primary reason for prescription. The STEP trials (semaglutide 2.4 mg weekly) produced average weight losses of 12–15% in people with obesity without diabetes. The SURMOUNT trials (tirzepatide 10–15 mg weekly) produced 18–22%, approaching bariatric-surgery territory.
The SELECT trial (semaglutide 2.4 mg, published 2023) was the first cardiovascular outcomes trial in people with obesity who did not have diabetes. It enrolled 17,604 adults with a body mass index (BMI) of 27 or higher and pre-existing cardiovascular disease. Semaglutide reduced the three-point MACE composite by 20%, independent of how much weight each person lost. That result reframed obesity itself as a treatable cardiovascular disease, not merely a risk factor, and accelerated Medicare and insurance coverage for glucagon-like peptide-1 use in obesity with established heart disease.
Glucagon-Like Peptide-1 Side Effects & Safety
- Nausea, vomiting, constipation, diarrhea — the headline side effects, affecting 20–50% of users at dose escalations. Usually managed with slow dose titration (months, not weeks), small frequent meals, and temporary dose reduction. Most people adapt within 1–3 months.
- Pancreatitis — a rare association (incidence under 1%). The labels say to discontinue the drug if pancreatitis is suspected; persistent severe abdominal pain radiating to the back is the classic warning sign.
- Gallbladder disease — increased rates of gallstones and cholecystitis, especially with rapid weight loss. Any rapid weight loss does this; glucagon-like peptide-1 receptor agonists do not cause it uniquely, but they magnify it.
- Medullary thyroid cancer — a boxed warning based on rodent studies. Contraindicated in anyone with a personal or family history of medullary thyroid carcinoma or multiple endocrine neoplasia type 2 (MEN-2). No human signal has been confirmed in two decades of use, but the warning stands.
- Diabetic retinopathy worsening — a paradoxical signal in SUSTAIN-6 attributed to rapid hemoglobin A1c improvement. The semaglutide label states that patients with a history of diabetic retinopathy should be monitored.
- Muscle loss — roughly 25–40% of weight lost on glucagon-like peptide-1 receptor agonists is lean mass. This is not unique to these drugs (all weight loss does this), but it matters for long-term function. Resistance training 2–3 times weekly and protein intake of 1.2–1.6 g/kg ideal body weight are the measures commonly described for preserving strength while on a glucagon-like peptide-1.
- Injection-site reactions and, rarely, hair shedding during rapid weight loss (telogen effluvium, reversible).
Combining Sodium-Glucose Cotransporter-2 + Glucagon-Like Peptide-1 — The Emerging Standard
The two drug classes work through completely separate mechanisms. Sodium-glucose cotransporter-2 inhibitors pull glucose out through the kidney and protect the heart and kidneys mechanically and metabolically. Glucagon-like peptide-1 agonists reduce appetite, improve insulin secretion, and protect the heart through vascular and inflammatory pathways. The cardio-renal benefits in trials are additive, not overlapping.
The American Diabetes Association (ADA) reviews these outcome trials in its yearly Standards of Care (the 2026 edition was published in December 2025). Metformin remains a widely used, low-cost glucose-lowering drug. See Metformin, Berberine, and glucagon-like peptide-1 receptor agonists for the full comparison of glucose-lowering agents.
Finerenone — The Third Pillar for Diabetic Kidney Disease
Finerenone is a non-steroidal mineralocorticoid receptor antagonist — a cousin of spironolactone, but designed to block the aldosterone receptor selectively without the sex-hormone side effects that make spironolactone intolerable for many men (gynecomastia) and women (menstrual irregularity).
The FIDELIO-DKD and FIGARO-DKD trials showed that finerenone added to standard care (including an angiotensin-converting enzyme inhibitor (ACE inhibitor) or angiotensin receptor blocker (ARB)) reduces kidney-failure progression and cardiovascular events in type 2 diabetic kidney disease. The benefit stacks on top of a sodium-glucose cotransporter-2 inhibitor — the two drugs target different pieces of the same problem. For a patient with type 2 diabetes, albuminuric chronic kidney disease, and an estimated glomerular filtration rate above 25, the current “four-pillar” package is: an angiotensin-converting enzyme inhibitor or angiotensin receptor blocker, a sodium-glucose cotransporter-2 inhibitor, a glucagon-like peptide-1 agonist, and finerenone. Finerenone raises blood potassium modestly, so potassium is checked during treatment.
Residual Risk — Icosapent Ethyl and REDUCE-IT
Even on maximum statin therapy, a sodium-glucose cotransporter-2 inhibitor, and a glucagon-like peptide-1 agonist, some patients keep having cardiovascular events. In the REDUCE-IT trial, patients with elevated triglycerides (135–499 mg/dL) and either established cardiovascular disease or diabetes-plus-risk-factors were randomized to icosapent ethyl (4 grams daily of purified eicosapentaenoic acid, EPA) or mineral oil placebo. Icosapent ethyl reduced MACE by 25%. The mechanism is not fully understood — it is not just triglyceride lowering — but for patients with persistent hypertriglyceridemia on statins, it is used as a fourth layer on top of the cardio-renal regimen.
Cost, Insurance, and Access
These drugs are expensive. U.S. list prices for brand-name sodium-glucose cotransporter-2 inhibitors run around $600–$700 per month; glucagon-like peptide-1 agonists are $1,000–$1,400 per month; tirzepatide is similar. Commercial insurance and Medicare Part D cover both classes for type 2 diabetes, usually with prior authorization. For obesity without diabetes, Medicare has traditionally excluded anti-obesity drugs, but in 2024 the Centers for Medicare & Medicaid Services (CMS) allowed Part D coverage of semaglutide specifically for patients with established cardiovascular disease — the first crack in a decades-old exclusion, driven entirely by the SELECT results.
Manufacturer copay cards often bring commercial out-of-pocket cost to $25 per month but are typically barred for Medicare and Medicaid enrollees. When glucagon-like peptide-1 agonists went into U.S. Food and Drug Administration-declared shortage in 2022–2024, compounding pharmacies legally produced semaglutide and tirzepatide at a fraction of the cost. The U.S. Food and Drug Administration removed both drugs from the shortage list in 2024–2025, which in turn restricted most compounded versions. Counterfeit injectables sold online, outside licensed pharmacies, have caused overdoses.
Non-Diabetic Uses
- Heart failure (HFrEF and HFpEF) — sodium-glucose cotransporter-2 inhibitors are standard, diabetes or not. See Heart Failure.
- Chronic kidney disease — sodium-glucose cotransporter-2 inhibitors reduce progression with or without diabetes. See Kidney Disease.
- Obesity with cardiovascular disease — semaglutide 2.4 mg is U.S. Food and Drug Administration-approved for MACE reduction. See Obesity.
- Metabolic dysfunction-associated steatotic liver disease (MASLD, formerly non-alcoholic fatty liver disease) — glucagon-like peptide-1 agonists and sodium-glucose cotransporter-2 inhibitors both reduce liver fat and inflammation; tirzepatide and semaglutide have the strongest data in metabolic dysfunction-associated steatohepatitis (MASH), the inflamed form.
- Polycystic ovary syndrome — glucagon-like peptide-1 agonists improve insulin resistance, weight, and menstrual regularity.
Who the Outcome Trials Studied
The outcome trials on this page enrolled people with type 2 diabetes (and, in the heart-failure and kidney trials, people without diabetes) who had one or more of the following:
- Established cardiovascular disease (prior heart attack, stroke, stent, bypass, or symptomatic peripheral artery disease).
- Heart failure of either type — reduced or preserved ejection fraction.
- Chronic kidney disease (estimated glomerular filtration rate under 60 or albumin-to-creatinine ratio over 30 mg/g).
- High cardiovascular risk without a prior event (multiple risk factors).
These are the groups in which the heart and kidney benefits described above were measured; the trials offer less direct evidence for people with none of these conditions.
Key Research Papers
The cardiovascular and renal outcome trials that turned sodium-glucose cotransporter-2 inhibitors and glucagon-like peptide-1 receptor agonists from glucose-lowering drugs into disease-modifying therapies for the heart and kidney.
- The Diabetes Control and Complications Trial Research Group. The Effect of Intensive Treatment of Diabetes on the Development and Progression of Long-Term Complications in Insulin-Dependent Diabetes Mellitus (DCCT). New England Journal of Medicine. 1993;329(14):977-986. — doi:10.1056/NEJM199309303291401
- UK Prospective Diabetes Study (UKPDS) Group. Intensive Blood-Glucose Control with Sulphonylureas or Insulin Compared with Conventional Treatment and Risk of Complications in Patients with Type 2 Diabetes (UKPDS 33). Lancet. 1998;352(9131):837-853. — doi:10.1016/S0140-6736(98)07019-6
- American Diabetes Association Professional Practice Committee for Diabetes. Introduction and Methodology: Standards of Care in Diabetes—2026. Diabetes Care. 2026;49(Suppl 1):S1-S5. — PubMed PMID: 41358883
- Zinman B, Wanner C, Lachin JM, et al. Empagliflozin, Cardiovascular Outcomes, and Mortality in Type 2 Diabetes (EMPA-REG OUTCOME). New England Journal of Medicine. 2015;373(22):2117-2128. — doi:10.1056/NEJMoa1504720
- Neal B, Perkovic V, Mahaffey KW, et al. Canagliflozin and Cardiovascular and Renal Events in Type 2 Diabetes (CANVAS). New England Journal of Medicine. 2017;377(7):644-657. — doi:10.1056/NEJMoa1611925
- Wiviott SD, Raz I, Bonaca MP, et al. Dapagliflozin and Cardiovascular Outcomes in Type 2 Diabetes (DECLARE-TIMI 58). New England Journal of Medicine. 2019;380(4):347-357. — doi:10.1056/NEJMoa1812389
- Perkovic V, Jardine MJ, Neal B, et al. Canagliflozin and Renal Outcomes in Type 2 Diabetes and Nephropathy (CREDENCE). New England Journal of Medicine. 2019;380(24):2295-2306. — doi:10.1056/NEJMoa1811744
- Heerspink HJL, Stefansson BV, Correa-Rotter R, et al. Dapagliflozin in Patients with Chronic Kidney Disease (DAPA-CKD). New England Journal of Medicine. 2020;383(15):1436-1446. — doi:10.1056/NEJMoa2024816
- Bakris GL, Agarwal R, Anker SD, et al. Effect of Finerenone on Chronic Kidney Disease Outcomes in Type 2 Diabetes (FIDELIO-DKD). New England Journal of Medicine. 2020;383(23):2219-2229. — doi:10.1056/NEJMoa2025845
- Marso SP, Daniels GH, Brown-Frandsen K, et al. Liraglutide and Cardiovascular Outcomes in Type 2 Diabetes (LEADER). New England Journal of Medicine. 2016;375(4):311-322. — doi:10.1056/NEJMoa1603827
- Marso SP, Bain SC, Consoli A, et al. Semaglutide and Cardiovascular Outcomes in Patients with Type 2 Diabetes (SUSTAIN-6). New England Journal of Medicine. 2016;375(19):1834-1844. — doi:10.1056/NEJMoa1607141
- Gerstein HC, Colhoun HM, Dagenais GR, et al. Dulaglutide and Cardiovascular Outcomes in Type 2 Diabetes (REWIND). Lancet. 2019;394(10193):121-130. — doi:10.1016/S0140-6736(19)31149-3
- Frias JP, Davies MJ, Rosenstock J, et al. Tirzepatide versus Semaglutide Once Weekly in Patients with Type 2 Diabetes (SURPASS-2). New England Journal of Medicine. 2021;385(6):503-515. — doi:10.1056/NEJMoa2107519
- McMurray JJV, Solomon SD, Inzucchi SE, et al. Dapagliflozin in Patients with Heart Failure and Reduced Ejection Fraction (DAPA-HF). New England Journal of Medicine. 2019;381(21):1995-2008. — doi:10.1056/NEJMoa1911303
- Anker SD, Butler J, Filippatos G, et al. Empagliflozin in Heart Failure with a Preserved Ejection Fraction (EMPEROR-Preserved). New England Journal of Medicine. 2021;385(16):1451-1461. — doi:10.1056/NEJMoa2107038
PubMed Topic Searches
Live PubMed queries that update as new papers are indexed.
- PubMed: SGLT2 inhibitors and cardiovascular outcomes
- PubMed: Empagliflozin and HFpEF
- PubMed: Dapagliflozin and chronic kidney disease
- PubMed: GLP-1 receptor agonists and cardiovascular outcomes
- PubMed: Semaglutide, SELECT trial, and obesity cardiovascular risk
- PubMed: Tirzepatide and the SURMOUNT weight-loss trials
- PubMed: Finerenone, FIDELIO, and FIGARO in diabetic kidney disease
- PubMed: Icosapent ethyl and REDUCE-IT residual triglyceride risk
- PubMed: Euglycemic DKA and SGLT2 inhibitors
- PubMed: GLP-1 weight loss and muscle preservation
Connections
- Endocrinology
- Blood Sugar & Insulin — interactive animation
- Diabetes Overview
- Type 1 vs Type 2 vs LADA and MODY
- Insulin Types and Dosing Strategies
- Hypoglycemia Awareness and Prevention
- Remission and Reversal Strategies
- CGM and Time-in-Range
- Hemoglobin A1c, Fructosamine, and Glycation Markers
- Complications: Retinopathy, Nephropathy, Neuropathy
- Diabetic Foot Care and Ulcer Prevention
- Insulin Resistance
- Obesity
- Metabolic Syndrome
- Kidney Disease
- Hypertension
- Heart Failure
- Estimated Glomerular Filtration Rate
- Glucagon-Like Peptide-1 Receptor Agonists
- Cardiovascular Disease
- Type 2 Diabetes — the underlying condition these two drug classes were developed for, and where the cardio-renal indications now apply regardless of hemoglobin A1c.
- Cardiology