Curcumin: The Master Polyphenol Antioxidant
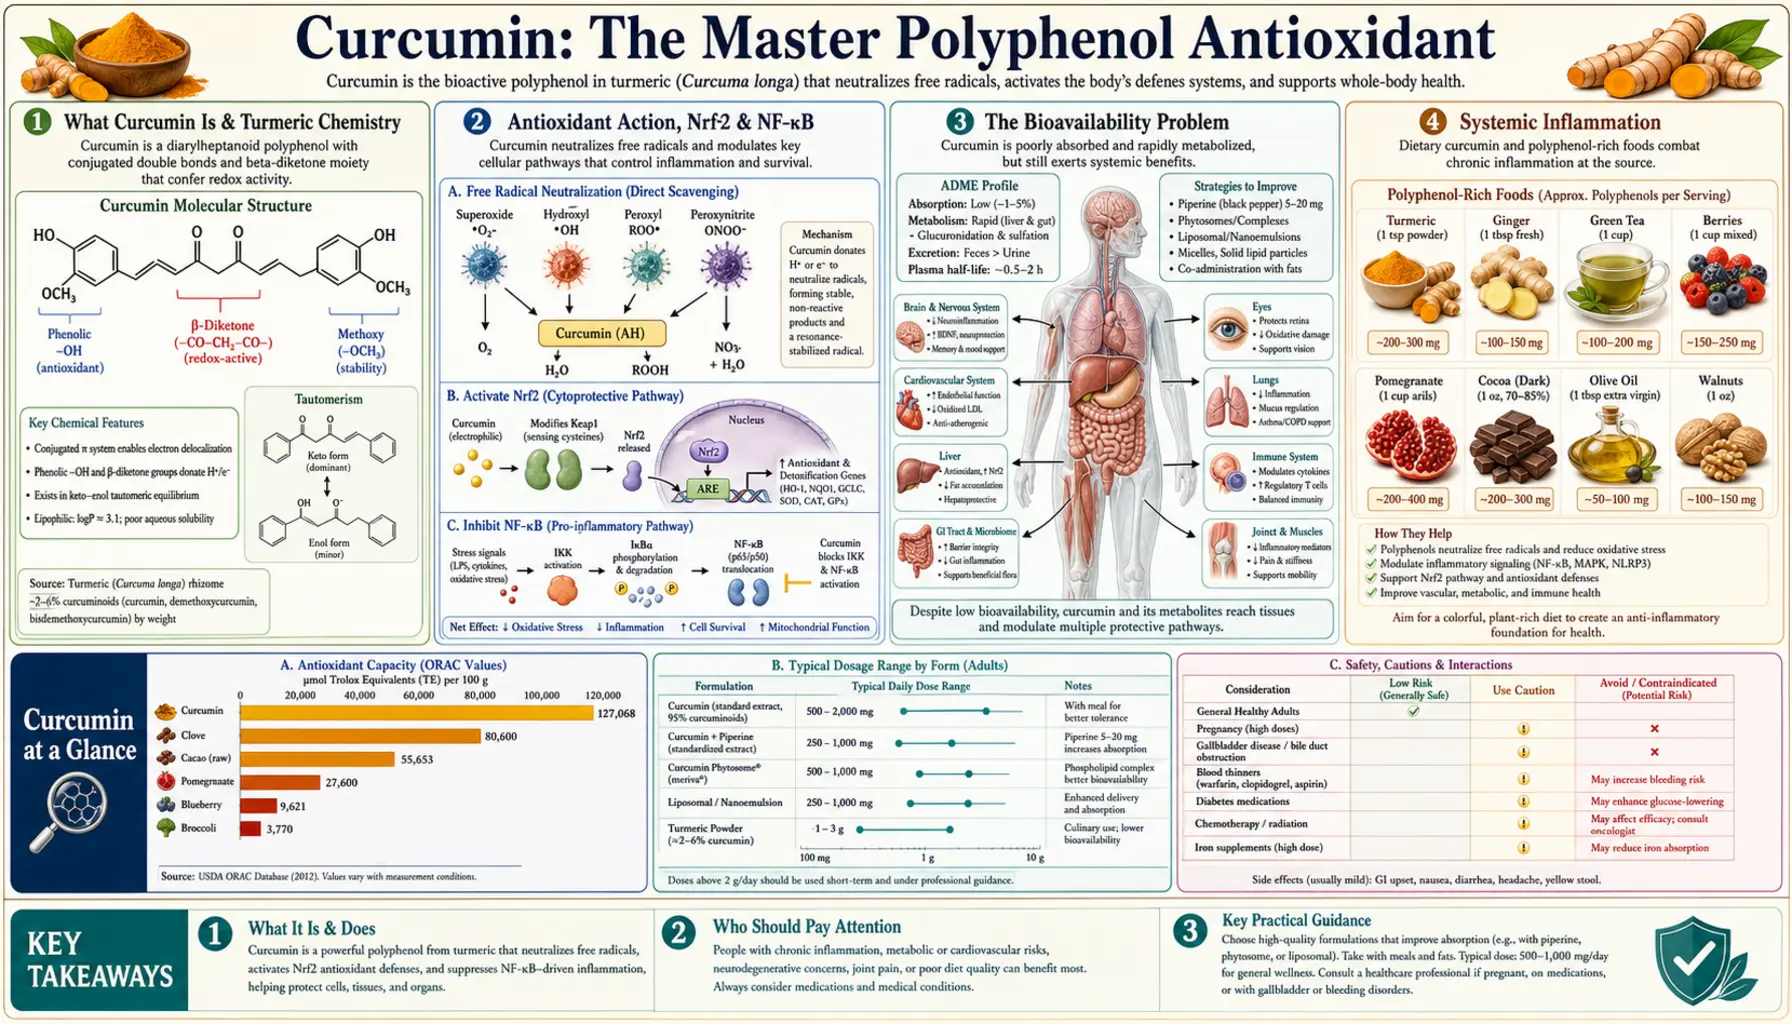
Curcumin is the principal bioactive polyphenol of turmeric (Curcuma longa) — the bright yellow-orange diarylheptanoid responsible for the spice's color and most of its medicinal activity. It is a pleiotropic molecule that acts simultaneously as a direct free-radical scavenger, an activator of the Nrf2 antioxidant-response pathway, and a potent inhibitor of the master inflammatory switch NF-κB. The central practical problem with curcumin is its poor oral bioavailability — it is poorly absorbed, rapidly metabolized, and quickly eliminated — which is why piperine, phospholipid, and nanoparticle formulations matter so much. The strongest clinical evidence is in osteoarthritis and joint pain, systemic inflammation, depression, and metabolic and liver health.
Interactive Visualization Inflammation — fire the cascade and watch it resolve Follow injury through prostaglandins and leukotrienes to swelling — then watch omega-3-derived resolvins actively switch it off, and see what a nonsteroidal anti-inflammatory drug really trades away. Launch →
Table of Contents
What Curcumin Is & Turmeric Chemistry
Curcumin is a low-molecular-weight polyphenol (chemical name 1,7-bis(4-hydroxy-3-methoxyphenyl)-1,6-heptadiene-3,5-dione) belonging to the diarylheptanoid family. Structurally it consists of two methoxylated phenol rings joined by a seven-carbon chain containing two enone groups and a central β-diketone. In solution the β-diketone exists in equilibrium between a keto form and an enol form, and it is the enol tautomer — with its conjugated, planar, electron-rich structure — that gives curcumin both its intense yellow color and much of its redox and metal-chelating activity.
Curcumin is not found in isolation in nature. It is one of three closely related pigments — collectively the curcuminoids — extracted from the dried rhizome of turmeric:
- Curcumin (diferuloylmethane) — roughly 70-80% of the curcuminoid fraction; the most studied and most active
- Demethoxycurcumin — about 15-20%; lacks one methoxy group
- Bisdemethoxycurcumin — about 3-5%; lacks both methoxy groups, more chemically stable
Whole turmeric rhizome contains only about 2-5% curcuminoids by weight, so culinary turmeric — while a healthful spice — delivers very little curcumin relative to the doses used in clinical trials. A standardized "curcumin extract" used in supplements is typically concentrated to 95% total curcuminoids. Turmeric also contains turmerone-rich essential oils (ar-turmerone, α- and β-turmerone) that have their own bioactivity and, interestingly, can enhance curcumin absorption — one reason some products use whole-turmeric matrix extracts rather than isolated curcuminoids.
Turmeric has been a cornerstone of Ayurvedic and traditional Chinese medicine for over two thousand years, used for wound healing, digestive complaints, joint pain, and inflammatory skin conditions. Modern pharmacology has spent four decades cataloguing the molecular targets that explain these traditional uses, and curcumin is now one of the most heavily researched natural products in the scientific literature.
Antioxidant Action, Nrf2 & NF-κB
Curcumin's antioxidant activity operates on three distinct levels — direct scavenging, induction of the cell's own antioxidant machinery, and suppression of the inflammatory signaling that generates oxidative stress in the first place.
Direct radical scavenging
The phenolic hydroxyl groups on curcumin's aromatic rings, together with the reactive central methylene/β-diketone, donate hydrogen atoms and electrons to neutralize reactive oxygen and nitrogen species — superoxide, hydroxyl radical, peroxyl radicals, singlet oxygen, nitric oxide, and peroxynitrite. Curcumin also chelates redox-active transition metals such as iron and copper, preventing them from catalyzing Fenton-type hydroxyl-radical generation. This direct scavenging is real but, given curcumin's low circulating concentrations, is probably less important clinically than its indirect effects.
Nrf2 activation (turning antioxidant defenses ON)
The more powerful antioxidant effect is indirect. Curcumin modifies cysteine residues on Keap1, the cytoplasmic protein that normally tethers and degrades the transcription factor Nrf2 (nuclear factor erythroid 2-related factor 2). When Keap1 is modified, Nrf2 is released, translocates to the nucleus, and binds the antioxidant response element (ARE) in the promoters of dozens of cytoprotective genes. This upregulates the cell's endogenous antioxidant enzymes — glutathione synthesis enzymes, glutathione peroxidase, glutathione-S-transferases, NAD(P)H quinone oxidoreductase 1 (NQO1), superoxide dismutase, catalase, and heme oxygenase-1. In effect, curcumin trains the cell to defend itself, which is far more durable than scavenging individual radicals. This Nrf2 mechanism is shared with sulforaphane and is the basis for raising intracellular glutathione.
NF-κB inhibition (turning inflammation OFF)
Nuclear factor kappa-B (NF-κB) is the master transcriptional switch for inflammation. When activated — by oxidative stress, cytokines, or microbial products — it drives expression of tumor necrosis factor-α, interleukin-1β, interleukin-6, cyclooxygenase-2 (COX-2), iNOS, and a host of adhesion molecules. Curcumin blocks the activation of IκB kinase (IKK), preventing the degradation of the inhibitor IκBα that normally holds NF-κB in the cytoplasm. The result is broad suppression of the pro-inflammatory cytokine cascade. Because inflammation and oxidative stress reinforce each other in a vicious loop, shutting down NF-κB indirectly lowers oxidative burden as well.
Curcumin additionally modulates many other targets — it inhibits cyclooxygenase-2 and 5-LOX in the eicosanoid pathway, downregulates the NLRP3 inflammasome, modulates PPAR-γ, and influences numerous kinases and growth-factor pathways. This pleiotropy — acting on dozens of targets at once rather than a single receptor — is the defining feature of curcumin pharmacology and explains both its broad therapeutic interest and the difficulty of pinning down a single mechanism of action.
The Bioavailability Problem
The single biggest obstacle to using curcumin is that plain curcumin is barely absorbed. Three forces work against it:
- Poor solubility and absorption — curcumin is highly lipophilic and practically insoluble in water at gastric pH, so very little crosses the intestinal wall
- Rapid metabolism — whatever is absorbed is quickly glucuronidated and sulfated in the intestinal wall and liver, converting active curcumin into largely inactive conjugates
- Fast elimination — the conjugates are rapidly cleared, so plasma levels of free curcumin stay extremely low and short-lived
Studies giving large oral doses of unformulated curcumin (even multiple grams) have measured nearly undetectable free-curcumin plasma concentrations. This is why simply swallowing turmeric capsules is often disappointing, and why formulation technology is central to the field. The major strategies:
- Black-pepper extract (piperine) — piperine, the pungent alkaloid of black pepper, inhibits the glucuronidation and intestinal/hepatic clearance of curcumin. The classic Shoba (1998) study found that co-administration of just 20 mg piperine with 2 g curcumin increased curcumin bioavailability by approximately 2,000% (a 20-fold increase) in humans. This is the cheapest and most common enhancement and the reason most turmeric supplements list "black pepper extract."
- Phospholipid complexes (phospholipid-bound curcumin) — curcumin bound to phosphatidylcholine forms a lipid-soluble complex that is far better absorbed; one phospholipid-bound product has shown roughly 29-fold higher absorption of total curcuminoids than standard curcumin in human pharmacokinetic studies, and most osteoarthritis trials use this form.
- Nano / micellar / solid-dispersion forms — reducing curcumin to nanoparticles or dispersing it in micelles dramatically increases the dissolved surface area and absorption; published bioavailability multipliers range from about 10-fold to as much as 185-fold depending on the formulation and reference standard.
Practical takeaway: the dose printed on the label means little without knowing the formulation. A few hundred milligrams of a well-absorbed phospholipid or nano form can deliver more active curcumin to the bloodstream than several grams of unformulated powder. When comparing products and trials, the delivery technology tells more than the milligram count.
Systemic Inflammation
Curcumin's best-characterized clinical effect is the lowering of circulating inflammatory markers. Because it suppresses NF-κB and the downstream cytokine cascade, supplementation reliably reduces measurable inflammation across a range of populations.
A 2019 meta-analysis by Tabrizi and colleagues, pooling 15 randomized controlled trials, found that curcumin-containing supplements significantly reduced interleukin-6 (IL-6), high-sensitivity C-reactive protein (CRP) and malondialdehyde (a marker of oxidative damage), but had no significant effect on tumor necrosis factor-alpha (TNF-α). The effect on C-reactive protein is the most consistent and is most pronounced in people who start with elevated baseline inflammation — those with metabolic syndrome, obesity, arthritis, or chronic disease — rather than in already-healthy subjects.
An earlier 2014 meta-analysis by Sahebkar, pooling 6 trials (172 people on curcuminoids and 170 on placebo), found a significant reduction in circulating C-reactive protein, about 6.4 mg/L on average; the effect held in trials that used bioavailability-improved preparations and lasted at least 4 weeks, but not in trials without these features. The magnitude of C-reactive protein reduction in inflamed populations is clinically meaningful and comparable in some studies to that produced by conventional anti-inflammatory interventions, without the gastrointestinal toxicity of nonsteroidal anti-inflammatory drugs (NSAIDs).
This anti-inflammatory action is the common thread linking curcumin's benefits in joints, mood, metabolism, and the gut, since chronic low-grade inflammation underlies all of these conditions. It also makes curcumin a frequently used adjunct in inflammatory bowel disease, where several trials of add-on curcumin in ulcerative colitis have shown improved remission rates.
Joints & Osteoarthritis
Joint pain is the indication with the most robust and clinically actionable evidence for curcumin. Osteoarthritis is driven in large part by interleukin-1 beta (IL-1β) and tumor necrosis factor-α-mediated cartilage breakdown and synovial inflammation — exactly the pathways curcumin suppresses.
- Kuptniratsaikul et al. (2014) — a large randomized trial in knee osteoarthritis patients compared 1,500 mg/day of turmeric extract (in divided doses) against ibuprofen 1,200 mg/day over 4 weeks. Curcumin was non-inferior to ibuprofen for pain and function on the WOMAC scale, with fewer gastrointestinal adverse events — a strong real-world result given the bleeding and ulcer risk of chronic nonsteroidal anti-inflammatory drug (NSAID) use.
- Belcaro et al. (2010) — in a 3-month registry study of 50 people with osteoarthritis taking phospholipid-bound curcumin (200 mg curcumin a day), the global WOMAC score fell by 58%, treadmill walking distance rose from 76 m to 332 m, and treatment costs, including the use of anti-inflammatory drugs, fell significantly compared with a control group. A follow-up 8-month study by the same group in 100 osteoarthritis patients reported significant improvements in WOMAC scores, walking performance and inflammatory markers compared with controls.
- Daily et al. (2016) — a systematic review and meta-analysis of randomized trials concluded that curcumin/turmeric extracts (typically ~1,000 mg/day curcumin) produced significant reductions in arthritis pain and improvements in function, while cautioning that more large, high-quality trials are needed.
The practical appeal is that curcumin offers nonsteroidal anti-inflammatory drug-comparable symptom relief for many osteoarthritis patients without the cardiovascular, renal, and gastrointestinal hazards that limit long-term nonsteroidal anti-inflammatory drug use. It is widely used as a stand-alone or nonsteroidal anti-inflammatory drug-sparing agent for knee and hand osteoarthritis, often combined with other antioxidants and omega-3 fatty acids in joint-support regimens. Benefit in inflammatory rheumatologic conditions such as rheumatoid arthritis has also been reported in smaller trials.
Mood & Depression
Curcumin has emerging, surprisingly consistent evidence as an adjunct in depression. The rationale is mechanistic: depression is increasingly understood to involve neuroinflammation, elevated pro-inflammatory cytokines, oxidative stress, hypothalamic-pituitary-adrenal-axis dysregulation, and reduced brain-derived neurotrophic factor (BDNF) — and curcumin favorably affects all of these. It also modulates monoamine levels (serotonin and dopamine) in preclinical models.
- Sanmukhani et al. (2014) — a randomized controlled trial in patients with major depressive disorder compared curcumin, fluoxetine, and their combination. Curcumin was comparable to fluoxetine in reducing depression scores, and the combination tended to perform best — a notable signal that curcumin can stand alongside a standard selective serotonin reuptake inhibitor (SSRI).
- Lopresti et al. (2014) — an 8-week placebo-controlled trial in 56 people with major depressive disorder (500 mg curcumin twice daily) found curcumin significantly better than placebo on depression-symptom and mood scores from weeks 4 to 8, with only a non-significant trend for anxiety; the effect was greater in a subgroup with atypical depression, and the authors described the result as “partial support.”
- Ng et al. (2017) — a meta-analysis of 6 clinical trials (377 patients) found curcumin significantly better than placebo for depression symptoms. Anxiety was not pooled, though 3 of the trials reported significant anti-anxiety effects, and no adverse events were reported in any of the trials.
Curcumin is best framed as a low-risk adjunct rather than a replacement for established antidepressant therapy, and it pairs logically with other anti-inflammatory and mitochondrial-support approaches to mood. Typical trial doses were 500-1,000 mg/day of a bioavailability-enhanced curcumin.
Metabolic & Liver Health
Curcumin has been studied extensively in metabolic syndrome, type 2 diabetes, and fatty liver disease — conditions in which chronic inflammation, insulin resistance, and oxidative stress converge.
Glycemic control and prediabetes
A landmark 9-month randomized, double-blind, placebo-controlled trial by Chuengsamarn and colleagues (2012) enrolled adults with prediabetes. Strikingly, none of the 116 patients in the curcumin group progressed to type 2 diabetes, versus 16.4% in the placebo group. The curcumin group also showed improved beta-cell function (HOMA-β), lower insulin resistance, and reduced inflammatory markers. This is one of the most impressive prevention signals in the curcumin literature.
Lipids and metabolic syndrome
Multiple trials and meta-analyses report that curcumin supplementation modestly improves the lipid profile — lowering triglycerides and low-density lipoprotein (LDL) cholesterol and, in some studies, raising high-density lipoprotein (HDL) — and reduces fasting glucose and hemoglobin A1c (HbA1c) in people with metabolic syndrome or type 2 diabetes. The effects are most evident when a bioavailability-enhanced formulation is used and baseline values are abnormal.
Non-alcoholic fatty liver disease (NAFLD/Metabolic Dysfunction-Associated Steatotic Liver Disease)
Several randomized trials, including work by Rahmani and colleagues (2016), have shown that curcumin reduces hepatic fat content on ultrasound and lowers serum alanine aminotransferase (ALT) and aspartate aminotransferase (AST) in patients with non-alcoholic fatty liver disease. The proposed mechanisms are reduced hepatic inflammation (NF-κB suppression), improved insulin sensitivity, and Nrf2-driven antioxidant protection of hepatocytes. This makes curcumin a popular component of liver-support and metabolic-recovery protocols.
Cognition & Brain Aging
Interest in curcumin for the aging brain was sparked partly by epidemiology: populations in India with high dietary turmeric intake have historically reported lower rates of Alzheimer's disease, though such observations are heavily confounded. Mechanistically, curcumin crosses the blood-brain barrier, binds and helps disaggregate amyloid-beta plaques in preclinical models, reduces neuroinflammation, and supports brain-derived neurotrophic factor — all plausible routes to neuroprotection.
The most cited human trial is Small and colleagues (2018) at UCLA: an 18-month randomized, double-blind, placebo-controlled study in non-demented older adults using a highly bioavailable nanoparticle curcumin (90 mg twice daily). The curcumin group showed significant improvements in memory and attention scores compared with placebo, and positron emission tomography (PET) imaging suggested reduced amyloid and tau accumulation in brain regions associated with memory and mood.
The evidence here is more preliminary than for joints or inflammation — several earlier trials of poorly absorbed curcumin in established Alzheimer's disease were negative, very likely because too little reached the brain. The lesson reinforces the bioavailability theme: cognitive benefit appears to require a genuinely well-absorbed formulation taken for many months. Curcumin is reasonably positioned as one component of a broader brain-aging and antioxidant strategy rather than a stand-alone treatment for dementia.
Forms & Dosing
Because absorption depends overwhelmingly on the formulation, the form you choose matters more than the raw milligram number.
- Standardized curcumin extract (95% curcuminoids) + piperine — the most common and economical option. Typical dosing is 500-1,000 mg curcuminoids two to three times daily, with 5-20 mg piperine (black pepper extract) to enhance absorption. Usually taken with a fat-containing meal.
- Phospholipid-bound curcumin — the best-studied form for osteoarthritis; roughly 29× better absorbed than plain curcumin. Common dosing is 500-1,000 mg of the complex once or twice daily.
- Nanoparticle / micellar / solid-dispersion forms — the highest-absorption forms; effective doses are correspondingly lower (e.g. 90-180 mg/day of a nanoparticle form in the cognition trials). More expensive per gram but more reliable delivery of active curcumin.
- Whole-turmeric matrix (turmeric oils + curcuminoids) — retains turmerones that contribute their own activity and modestly aid absorption.
- Culinary turmeric — a healthful spice but a poor source of therapeutic curcumin; pairing it with black pepper and fat (the traditional "golden milk" combination) improves absorption but cannot match a standardized extract.
What the studies and users describe: for everyday antioxidant and anti-inflammatory support, a curcumin extract with piperine taken with food is the common, inexpensive option. The trials for specific targets — osteoarthritis, depression, fatty liver, or cognition — each used a particular enhanced formulation at a set dose, and practitioners describe giving it 8-12 weeks (longer for cognition) before judging response. Absorption rises substantially when curcumin is taken with a fatty meal.
Safety & Interactions
Curcumin has an excellent safety record. It is classified Generally Recognized As Safe (GRAS) as a food additive, and human trials have used doses up to 8-12 g/day with good tolerability. The JECFA acceptable daily intake for curcumin is 0-3 mg/kg body weight as a food additive (a conservative food-additive figure, well below typical supplement-trial doses). Key considerations:
- Gastrointestinal effects — the most common side effects are mild: nausea, diarrhea, bloating, or reflux, generally at higher doses. Usually resolved by lowering the dose, dividing it, or taking with food.
- Anticoagulant / antiplatelet interaction — curcumin has mild antiplatelet activity and may add to the effect of warfarin, direct oral anticoagulants, aspirin, clopidogrel, or other blood thinners, theoretically increasing bleeding risk. For that reason practitioners commonly describe stopping curcumin 1-2 weeks before elective surgery.
- Gallbladder disease and bile-duct obstruction — curcumin stimulates gallbladder contraction and bile flow. This is beneficial for healthy people but can provoke pain in those with gallstones or bile-duct obstruction. The European Medicines Agency (EMA) turmeric monograph lists it as not recommended with bile-duct obstruction, inflammation of the bile ducts (cholangitis), liver disease, gallstones or any other biliary disease, because it may stimulate bile secretion.
- Iron absorption — curcumin chelates iron and, at high doses over time, may reduce iron absorption. Relevant for people with iron-deficiency anemia; less relevant (potentially even helpful) in iron overload.
- Drug-metabolism interactions — the same enzyme inhibition that makes piperine-boosted curcumin more bioavailable can also raise blood levels of other drugs metabolized by CYP and UGT enzymes (and P-glycoprotein). This matters most with narrow-therapeutic-index medications, where a small rise in blood level can cause harm.
- Diabetes medications — curcumin's glucose-lowering effect can add to insulin or oral hypoglycemics, raising the chance of low blood sugar.
- Liver injury (uncommon, but documented) — LiverTox, the U.S. National Institutes of Health liver-injury database, records “several dozen instances of clinically apparent acute liver injury” linked to some turmeric products. In Italy, 28 spontaneous reports of acute hepatitis, mostly with cholestasis (blocked bile flow), linked to turmeric supplements reached the national phytovigilance system in the first six months of 2019, and Italian regulators took action; in the seven Tuscan cases, every product was a high-bioavailability, high-dose curcumin formulation. The EMA monograph lists turmeric as not recommended with liver disease. The U.S. National Center for Complementary and Integrative Health (NCCIH) lists fatigue, nausea, poor appetite, dark urine and jaundice (yellow skin or eyes) as liver-damage symptoms; dark urine and jaundice are signs of liver injury that hospitals treat as urgent.
- Pregnancy, breastfeeding and children — culinary amounts of turmeric are an ordinary food. For turmeric medicines, the EMA monograph states that safety during pregnancy and breastfeeding has not been established and, in the absence of sufficient data, use during pregnancy and breastfeeding is not recommended; NCCIH says turmeric supplements in pregnancy “may be unsafe.” The EMA monograph also says use under 18 has not been established and is not recommended.
- Supplement quality — turmeric products have historically been a target for adulteration (including lead chromate added to boost color). Third-party testing is how a product shows it has been checked for lead and other contaminants.
Key Research Papers
The following peer-reviewed papers underpin the clinical and mechanistic claims on this page. Author names, titles, and journals are given as plain text; the linked year/volume/pages resolve to the article via DOI or PubMed.
- Hewlings SJ, Kalman DS. Curcumin: A Review of Its Effects on Human Health. Foods. 2017;6(10):92. — doi:10.3390/foods6100092
- Shoba G, Joy D, Joseph T, et al. Influence of piperine on the pharmacokinetics of curcumin in animals and human volunteers. Planta Medica. 1998;64(4):353-356. — doi:10.1055/s-2006-957450
- Anand P, Kunnumakkara AB, Newman RA, Aggarwal BB. Bioavailability of curcumin: problems and promises. Molecular Pharmaceutics. 2007;4(6):807-818. — doi:10.1021/mp700113r
- Tabrizi R, Vakili S, Akbari M, et al. The effects of curcumin-containing supplements on biomarkers of inflammation and oxidative stress: A systematic review and meta-analysis of randomized controlled trials. Phytotherapy Research. 2019;33(2):253-262. — doi:10.1002/ptr.6226
- Sahebkar A. Are curcuminoids effective C-reactive protein-lowering agents in clinical practice? Evidence from a meta-analysis. Phytotherapy Research. 2014;28(5):633-642. — doi:10.1002/ptr.5045
- Kuptniratsaikul V, Dajpratham P, Taechaarpornkul W, et al. Efficacy and safety of Curcuma domestica extracts compared with ibuprofen in patients with knee osteoarthritis. Clinical Interventions in Aging. 2014;9:451-458. — doi:10.2147/CIA.S58535
- Belcaro G, Cesarone MR, Dugall M, et al. Product-evaluation registry of Meriva, a curcumin-phosphatidylcholine complex, for the complementary management of osteoarthritis. Panminerva Medica. 2010;52(2 Suppl 1):55-62. — PubMed PMID: 20657536
- Belcaro G, Cesarone MR, Dugall M, et al. Efficacy and safety of Meriva®, a curcumin-phosphatidylcholine complex, during extended administration in osteoarthritis patients. Alternative Medicine Review. 2010;15(4):337-344. — PubMed PMID: 21194249
- Daily JW, Yang M, Park S. Efficacy of turmeric extracts and curcumin for alleviating the symptoms of joint arthritis: A systematic review and meta-analysis of randomized clinical trials. Journal of Medicinal Food. 2016;19(8):717-729. — doi:10.1089/jmf.2016.3705
- Sanmukhani J, Satodia V, Trivedi J, et al. Efficacy and safety of curcumin in major depressive disorder: A randomized controlled trial. Phytotherapy Research. 2014;28(4):579-585. — doi:10.1002/ptr.5025
- Lopresti AL, Maes M, Maker GL, et al. Curcumin for the treatment of major depression: A randomised, double-blind, placebo-controlled study. Journal of Affective Disorders. 2014;167:368-375. — doi:10.1016/j.jad.2014.06.001
- Ng QX, Koh SSH, Chan HW, Ho CYX. Clinical use of curcumin in depression: A meta-analysis. Journal of the American Medical Directors Association. 2017;18(6):503-508. — doi:10.1016/j.jamda.2016.12.071
- Chuengsamarn S, Rattanamongkolgul S, Luechapudiporn R, et al. Curcumin extract for prevention of type 2 diabetes. Diabetes Care. 2012;35(11):2121-2127. — doi:10.2337/dc12-0116
- Rahmani S, Asgary S, Askari G, et al. Treatment of non-alcoholic fatty liver disease with curcumin: A randomized placebo-controlled trial. Phytotherapy Research. 2016;30(9):1540-1548. — doi:10.1002/ptr.5659
- Small GW, Siddarth P, Li Z, et al. Memory and brain amyloid and tau effects of a bioavailable form of curcumin in non-demented adults: A double-blind, placebo-controlled 18-month trial. American Journal of Geriatric Psychiatry. 2018;26(3):266-277. — doi:10.1016/j.jagp.2017.10.010
PubMed Topic Searches
- PubMed: Curcumin antioxidant Nrf2
- PubMed: Curcumin NF-κB inflammation
- PubMed: Curcumin bioavailability piperine
- PubMed: Curcumin osteoarthritis knee pain
- PubMed: Curcumin depression randomized trial
- PubMed: Curcumin type 2 diabetes metabolic syndrome
- PubMed: Curcumin non-alcoholic fatty liver disease
- PubMed: Curcumin cognition memory Alzheimer
External Authoritative Resources
Connections
- Inflammation & How It Resolves — interactive animation
- All Antioxidants
- Turmeric (Source Herb)
- Quercetin
- Glutathione
- N-Acetylcysteine (Glutathione Precursor)
- Sulforaphane (Nrf2 Activator)
- Resveratrol
- Coenzyme Q10
- Alpha Lipoic Acid
- Oxidative Stress
- Rheumatology & Arthritis
- Gastroenterology & Inflammatory Bowel Disease
- Hepatology & Fatty Liver
- Endocrinology & Diabetes
- Psychiatry & Depression
- Neurology
- Vitamin D
- Vitamin C
- Vitamin E
- Zinc
- Magnesium
- Ginger
- Boswellia
- Black Pepper (Piperine)
- Omega-3 Fatty Acids
- C-Reactive Protein (CRP)
- Hemoglobin A1c
- Liver Function Tests
- Lipid Panel