Oxidative Stress: Free Radicals, Antioxidants, and How to Test
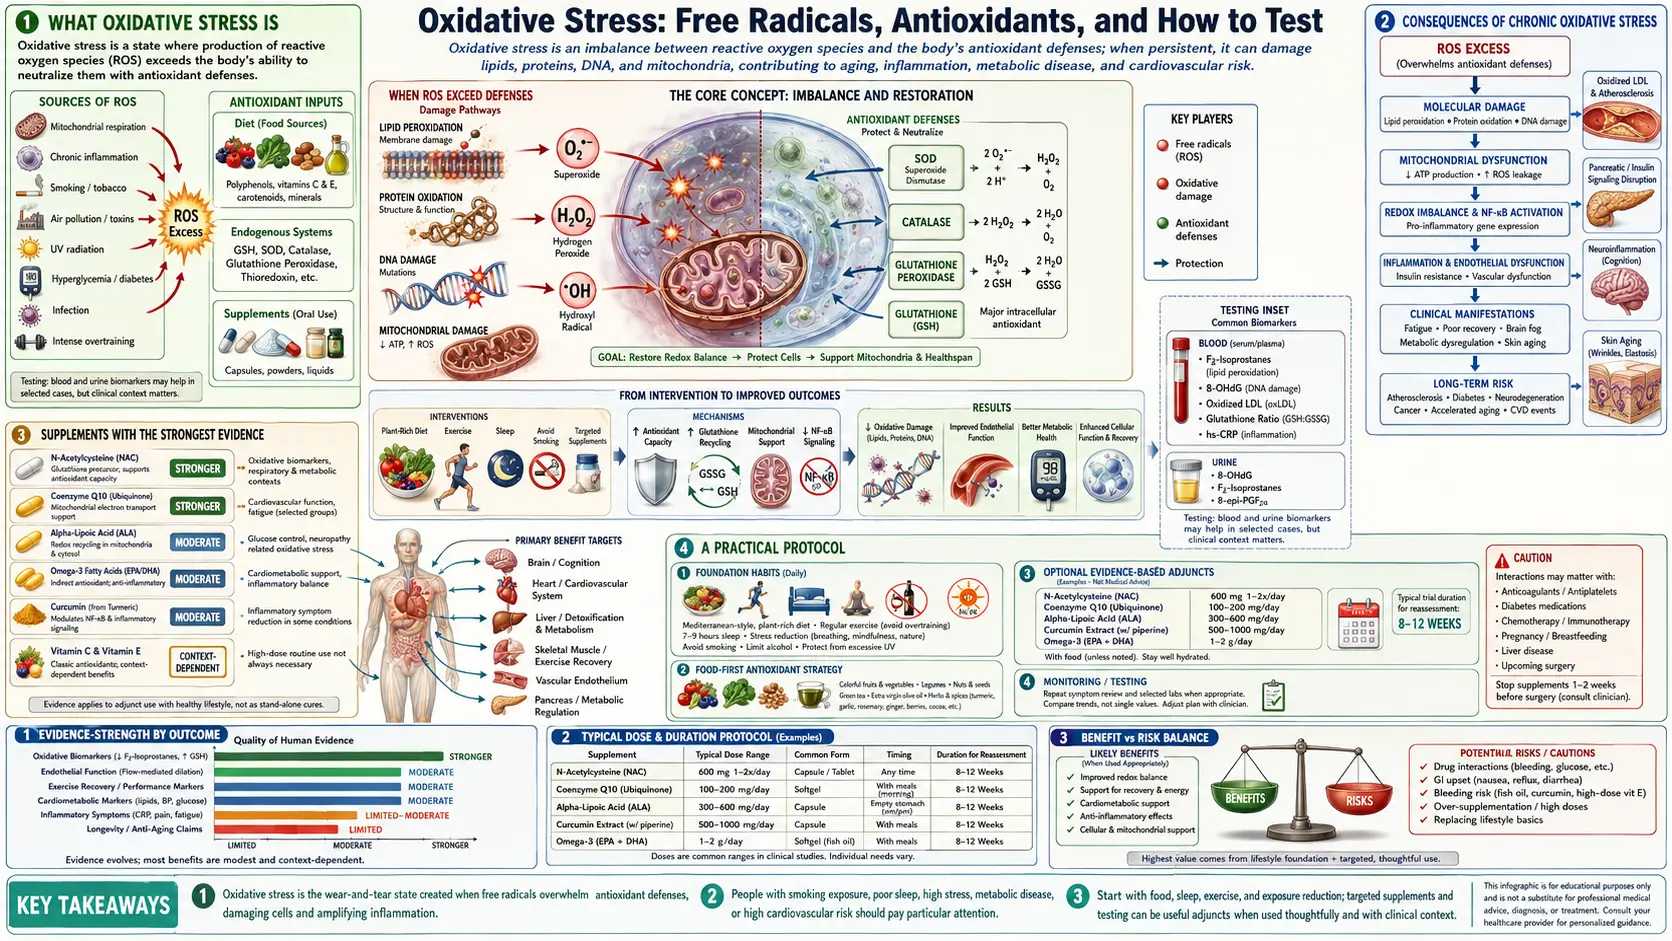
Oxidative stress is the imbalance between the production of reactive oxygen species (ROS) and the body's capacity to neutralize them with antioxidant defenses. A small amount of ROS production is normal and necessary — cells use peroxide bursts for signaling, immune killing, and metabolic regulation. The trouble starts when ROS production chronically exceeds the antioxidant systems that contain them, damaging lipids, proteins, and DNA. Decades of research have linked sustained oxidative stress to cardiovascular disease, neurodegeneration, cancer initiation, accelerated aging, infertility, and chronic inflammation.
This page covers what oxidative stress actually is at the molecular level, the antioxidant systems that defend against it, the lifestyle and dietary inputs that change the balance, what supplement trials have found (including harms), and the lab tests used to measure the damage.
Table of Contents
- What Oxidative Stress Is
- Sources of Reactive Oxygen Species
- The Body's Antioxidant Systems
- Consequences of Chronic Oxidative Stress
- Lifestyle Drivers and Reducers
- Dietary Antioxidants
- Supplements: What Has Evidence, and Where It Turns Harmful
- Testing Oxidative Stress in the Lab
- The Antioxidant Paradox
- Summary of the Research
- Key Research Papers
- Connections
- Featured Videos
What Oxidative Stress Is
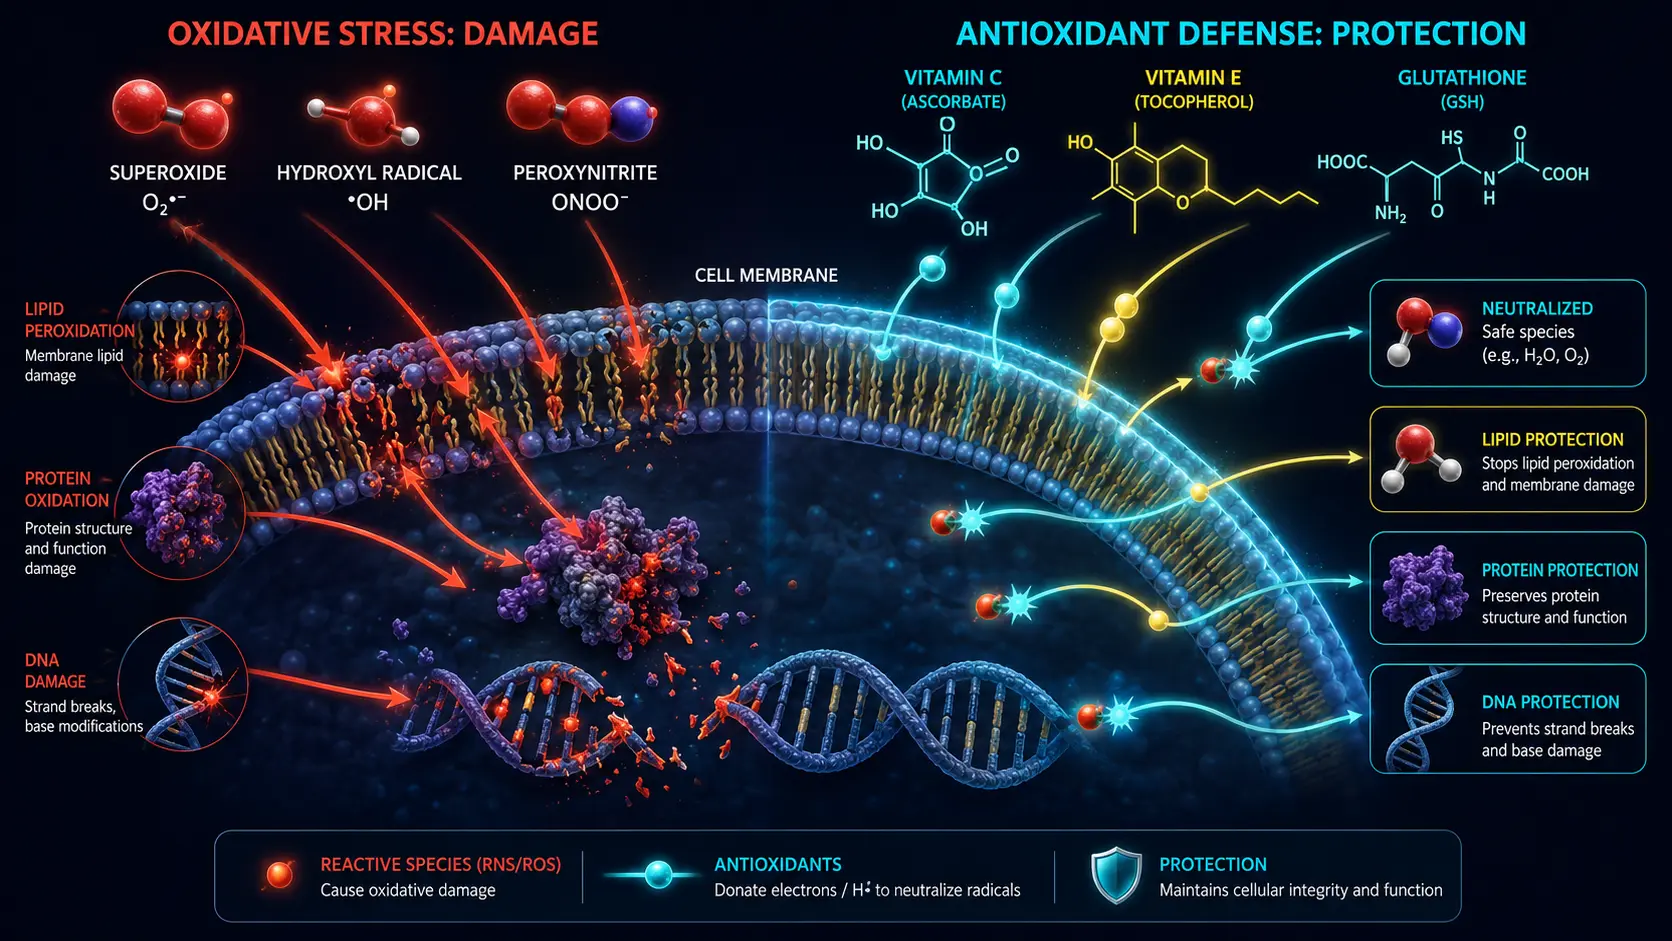
Reactive oxygen species are oxygen-containing molecules with an unpaired electron, making them chemically aggressive. The major species:
- Superoxide (O₂·⁻) — produced primarily as a byproduct of mitochondrial electron transport. Figures such as 1–2% of consumed oxygen are widely quoted, but they come from isolated mitochondria; a 2009 review states that superoxide production in living tissue cannot be estimated from isolated-mitochondria rates and that such extrapolations are misleading (Murphy 2009)
- Hydrogen peroxide (H₂O₂) — less reactive but highly diffusible; functions as a signaling molecule at low levels
- Hydroxyl radical (•OH) — the most reactive; formed when H₂O₂ reacts with iron or copper (Fenton reaction)
- Peroxynitrite (ONOO⁻) — from superoxide and nitric oxide; particularly damaging to mitochondria and proteins
- Singlet oxygen (¹O₂) — formed in skin from UV exposure and from neutrophil activity
Reactive nitrogen species (RNS), reactive sulfur species, and lipid peroxidation products (4-HNE, malondialdehyde) operate alongside ROS and are sometimes lumped under the broader term "reactive species" or "redox stress." A balanced cell handles all of these continuously through a layered set of antioxidant defenses.
The idea that this damage drives aging traces to Denham Harman's 1956 free radical theory of aging (Harman 1956). Later work has challenged it: a 2009 review from one laboratory reported that only one of 18 genetic manipulations of antioxidant enzymes in mice changed lifespan, which the authors said "calls into serious question" a role for oxidative damage in mouse longevity (Pérez 2009).
Sources of Reactive Oxygen Species
Endogenous (internal)
- Mitochondrial respiration — a major source; a 2009 review describes complex I as the predominant site of superoxide production in isolated mitochondria (Murphy 2009)
- NADPH oxidase (NOX) — in neutrophils, macrophages, and vascular cells; deliberate ROS production for signaling and antimicrobial defense
- Xanthine oxidase — the enzyme that converts purines to uric acid; a recognized source after ischemia and reperfusion
- Cytochrome P450 enzymes — drug and xenobiotic metabolism (especially alcohol and acetaminophen)
- Peroxisomal β-oxidation — processing very-long-chain fatty acids
- Inflammation — activated immune cells generate large ROS bursts to kill pathogens; chronic inflammation means chronic ROS
Exogenous (external)
- Smoking — tobacco smoke carries a heavy load of oxidants
- Air pollution — PM2.5, ozone, nitrogen oxides
- UV and ionizing radiation — sunlight, medical imaging, cosmic rays
- Heavy metals — lead, mercury, cadmium, arsenic. A 2005 review describes iron and copper as redox-cycling metals that drive Fenton chemistry, whereas the main route of toxicity for mercury and cadmium is depletion of glutathione and binding to protein sulfhydryl groups, and arsenic is thought to bind critical thiols (Valko 2005)
- Pesticides and industrial solvents
- Heat-treated and processed foods — advanced glycation end-products (AGEs), oxidized lipids, acrylamide
- Excessive iron — high serum ferritin, hemochromatosis, and excess iron supplementation
- Excessive alcohol — CYP2E1 induction and acetaldehyde
The Body's Antioxidant Systems
The body has three layered antioxidant defenses:
Enzymatic antioxidants (the first responders)
- Superoxide dismutase (SOD) — converts superoxide to hydrogen peroxide; copper/zinc-dependent (cytoplasm) and manganese-dependent (mitochondria)
- Catalase — converts hydrogen peroxide to water and oxygen; iron-dependent
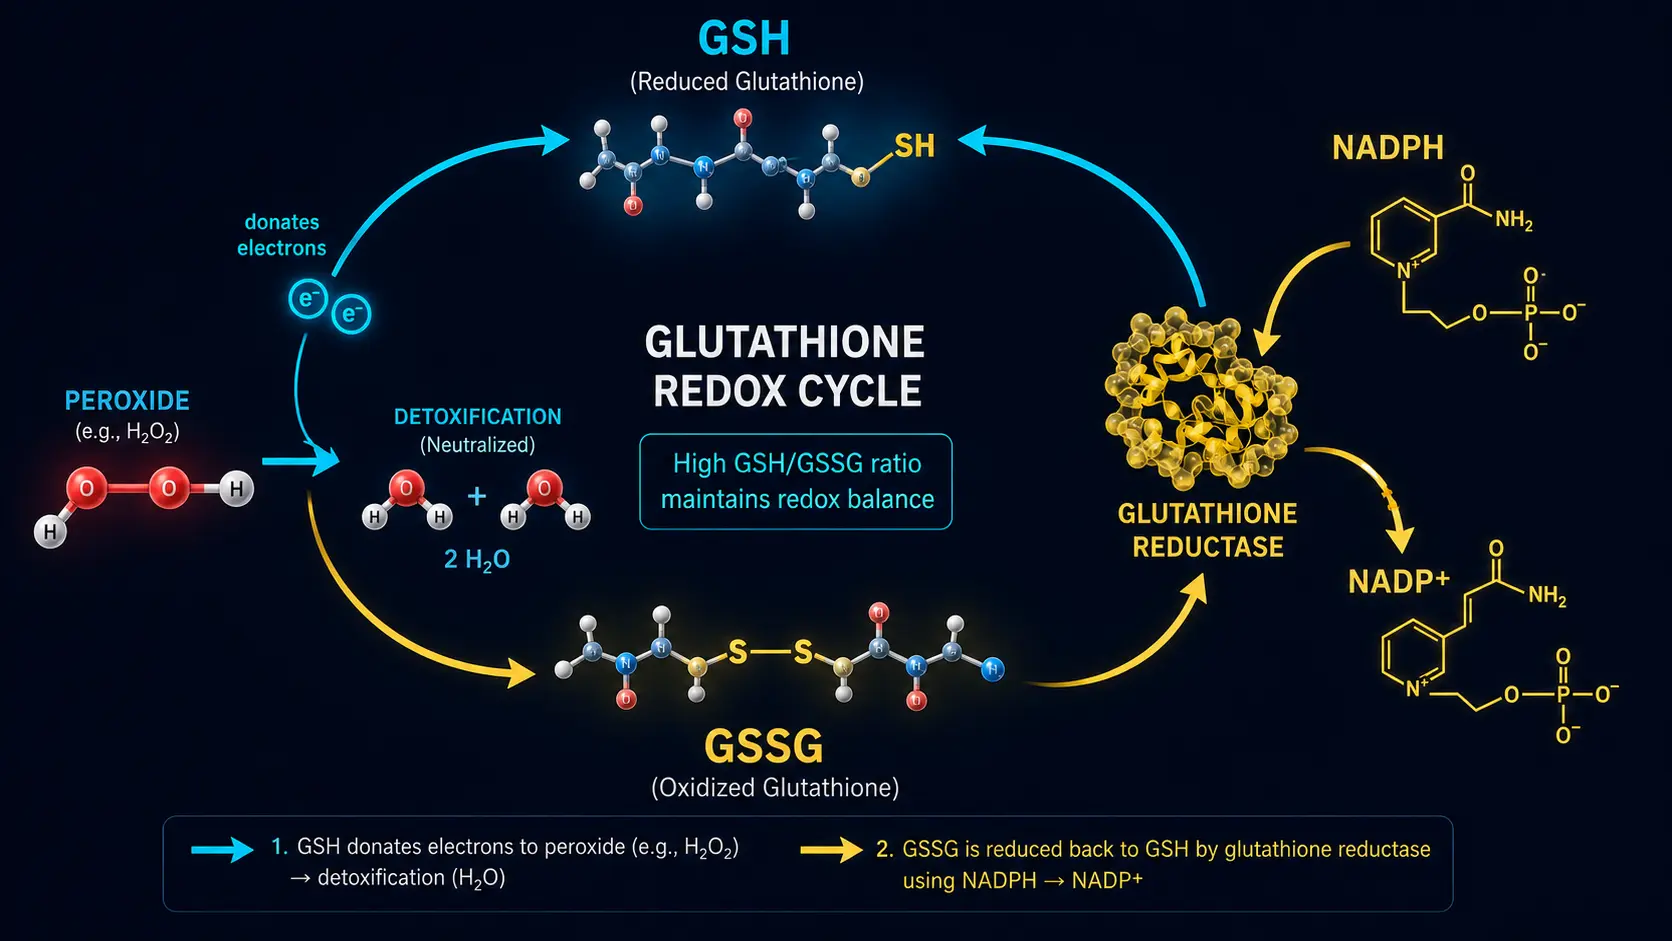
- Glutathione peroxidase — converts hydrogen peroxide to water using glutathione; selenium-dependent
- Glutathione reductase — recycles oxidized glutathione (GSSG) back to reduced glutathione (GSH) using NADPH
- Thioredoxin reductase — another major redox-cycling enzyme
Small-molecule antioxidants (the heavy lifters)
- Glutathione (GSH) — the most abundant non-protein thiol in cells and a central intracellular antioxidant; a tripeptide of glutamate, cysteine and glycine
- Vitamin C (ascorbate) — water-soluble; primary antioxidant in plasma and cytoplasm
- Vitamin E (alpha-tocopherol) — lipid-soluble; primary antioxidant in cell membranes
- Coenzyme Q10 (ubiquinol) — mitochondrial electron transport and lipid antioxidant
- Uric acid — a major contributor to plasma antioxidant capacity
- Bilirubin — a lipid-phase antioxidant
- Alpha-lipoic acid — both water- and lipid-soluble; described as regenerating other antioxidants
Mineral cofactors
Selenium, zinc, copper, manganese, and iron are all required cofactors for the antioxidant enzymes above. Deficiency in any of them impairs the system.
Master regulators
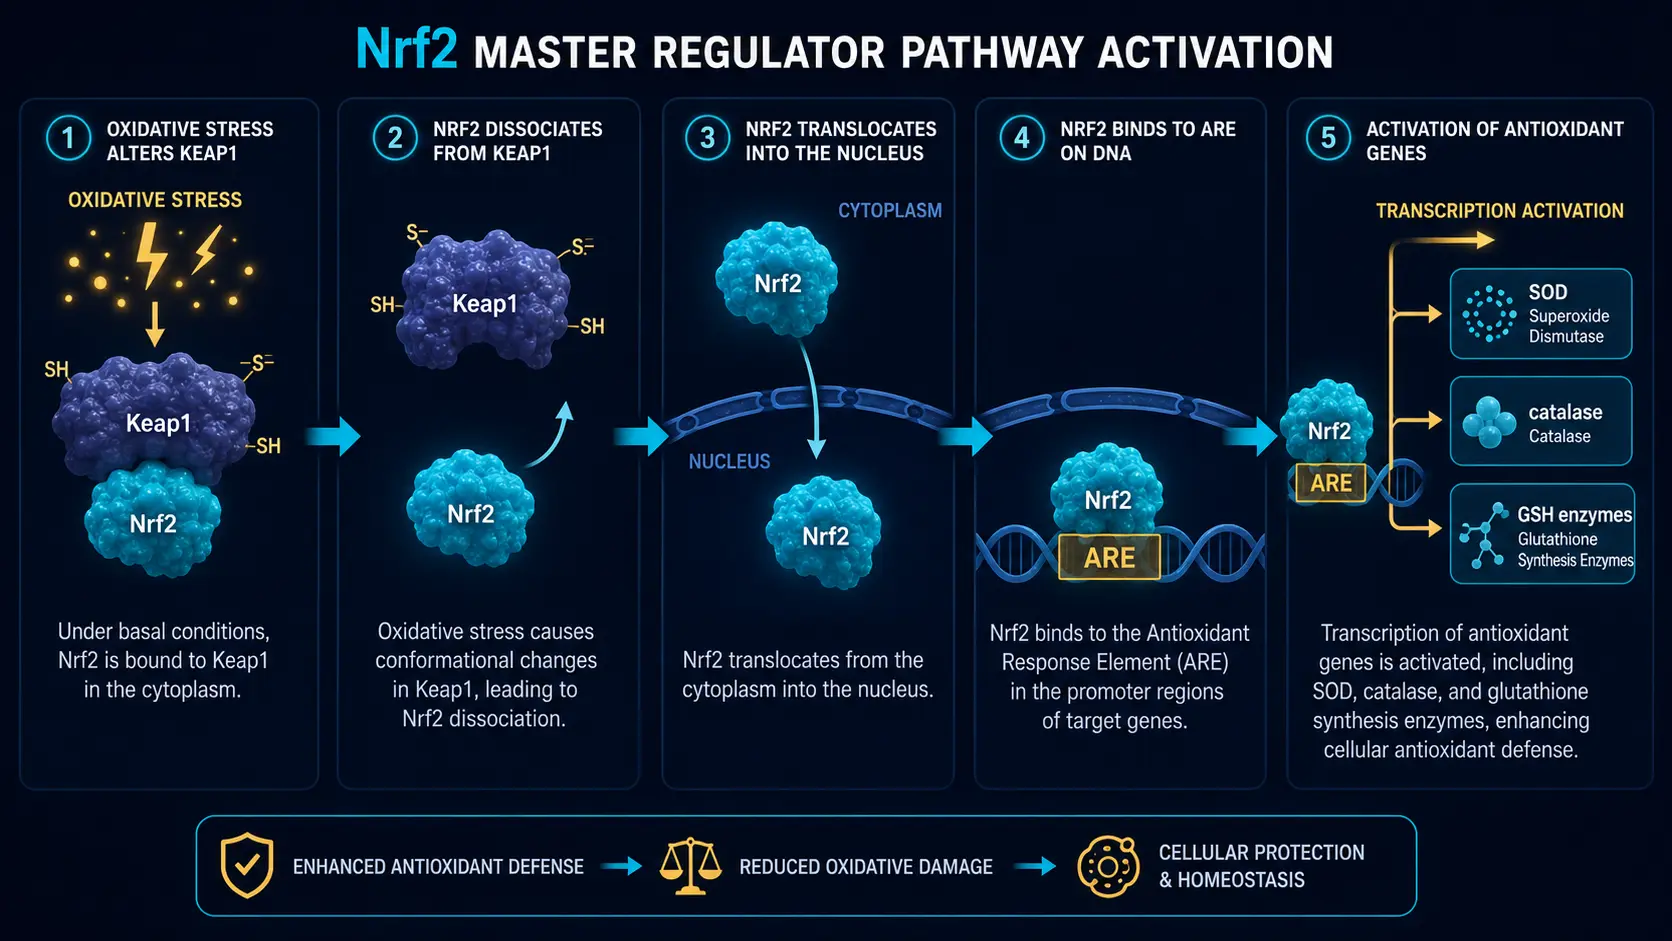
The Nrf2 transcription factor is the central conductor: when oxidative stress rises, Nrf2 enters the nucleus and switches on the genes for SOD, catalase, glutathione peroxidase, glutathione synthesis enzymes, and a large set of other antioxidant and detoxification genes. Nrf2 activation is one of the main mechanisms proposed for the effects of dietary compounds such as sulforaphane in broccoli, curcumin, EGCG in green tea and resveratrol.
Consequences of Chronic Oxidative Stress
- Lipid peroxidation — oxidation of cell membrane lipids; produces 4-HNE and malondialdehyde (MDA); oxidized LDL is implicated in atherosclerotic plaque formation
- Protein damage — oxidation of cysteine, methionine, tyrosine residues; protein carbonylation; aggregates implicated in Alzheimer's and Parkinson's
- DNA damage — 8-oxo-deoxyguanosine (8-OHdG) is one of the most widely measured oxidative DNA lesions; misrepair drives mutation and cancer
- Mitochondrial dysfunction — ROS damages the mitochondria that produce them, creating a self-amplifying loop
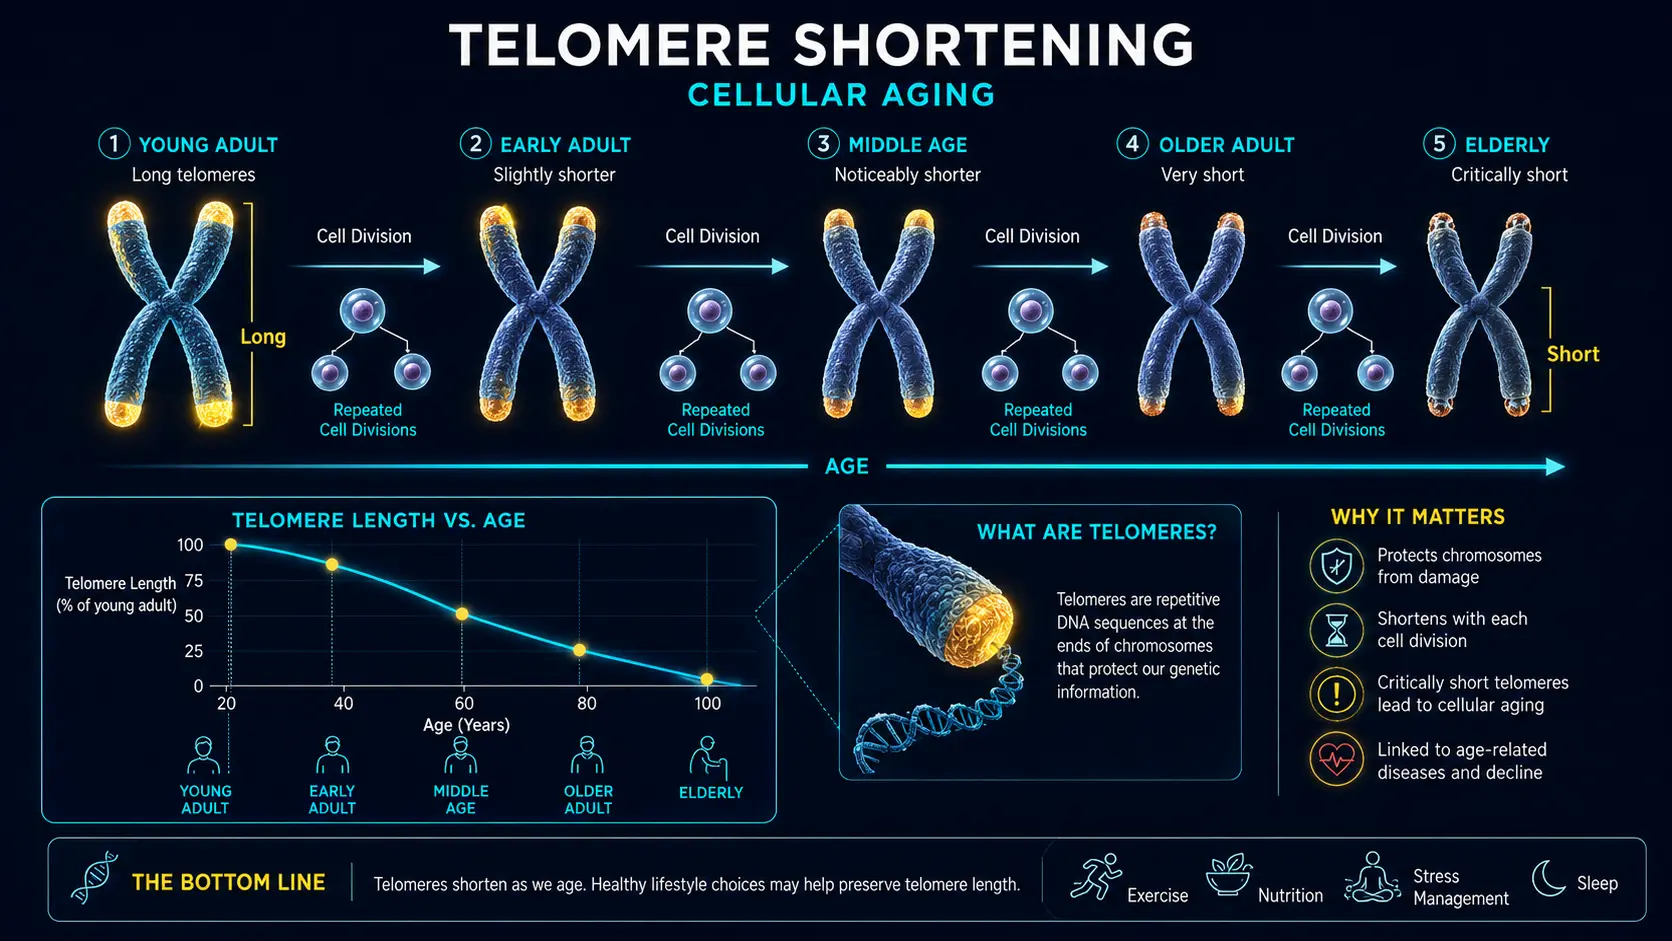
- Telomere shortening — linked to cellular aging
- Inflammation — oxidative stress activates NF-κB, the master inflammatory transcription factor; inflammation creates more ROS — the inflammation-oxidation loop
Conditions where oxidative stress is a documented contributor: cardiovascular disease, type 2 diabetes, non-alcoholic fatty liver disease, COPD, age-related macular degeneration, infertility (sperm DNA damage), Alzheimer's, Parkinson's, ALS, multiple sclerosis, and many cancers.
Lifestyle Drivers and Reducers
Things that increase oxidative stress
- Smoking and second-hand smoke
- Heavy alcohol use
- Chronic short sleep
- Sedentary lifestyle
- Visceral obesity
- Chronic psychological stress (cortisol & catecholamine effects)
- Excessive endurance training without adequate recovery
- High-glycemic, ultra-processed Western diet
- Industrial seed oils oxidized at high heat
- Air pollution and indoor PM2.5 (e.g., gas stoves without ventilation)
Things that reduce oxidative stress
- Regular exercise — in a 4-week training study, exercise induced the muscle's own antioxidant enzymes (superoxide dismutases 1 and 2, glutathione peroxidase) (Ristow 2009)
- Adequate sleep
- Caloric restriction — in the CALERIE 2 trial, 218 healthy non-obese adults were randomized to 25% caloric restriction or their usual diet; after 2 years the restriction group had lower urinary F2-isoprostanes (Il'yasova 2018)
- A diet rich in colorful plants, polyphenols, and cruciferous vegetables
- Heat exposure (sauna) and cold exposure — mild stressors proposed to upregulate antioxidant defenses (hormesis)
- Smoking cessation
- Air filtration, especially in urban or wildfire environments
Dietary Antioxidants
Large trials of isolated antioxidant supplements have mostly not shown benefit (see The Antioxidant Paradox). In prospective studies, higher fruit and vegetable intake is associated with lower cardiovascular disease, cancer and all-cause mortality (summary relative risk for all-cause mortality 0.90 per 200 g/day; Aune 2017) — an association, which does not show that antioxidants are the cause. Food categories studied for their antioxidant compounds:
- Cruciferous vegetables — broccoli, kale, cabbage, cauliflower, Brussels sprouts; activate Nrf2 via sulforaphane
- Berries — blueberries, raspberries, blackberries, strawberries; anthocyanins, ellagic acid
- Dark leafy greens — spinach, kale; carotenoids, chlorophyll, polyphenols
- Tomatoes — lycopene
- Tea, especially green — EGCG; Green Tea
- Coffee — chlorogenic acid and other polyphenols; in a French cohort of 4,942 adults, nonalcoholic beverages and fruit were the largest contributors to polyphenol intake (Pérez-Jiménez 2011)
- Dark chocolate (≥ 70%) — flavanols
- Spices — turmeric (curcumin), cinnamon, oregano, cumin (in a 2010 ranking of the 100 richest dietary sources of polyphenols, spices and dried herbs ranked highest, led by cloves at 15,000 mg per 100 g; Pérez-Jiménez 2010)
- Olive oil, extra-virgin — oleocanthal and oleuropein
- Nuts & seeds — walnuts, almonds; vitamin E, polyphenols
- Fatty fish — salmon, sardines; omega-3 fatty acids, studied for effects on inflammation
Supplements: What Has Evidence, and Where It Turns Harmful
The trial results in The Antioxidant Paradox below bear directly on this list. Two of the entries — vitamin E and selenium — are ones large randomized trials found to increase prostate cancer (vitamin E) and type 2 diabetes (selenium), and a meta-analysis linked high-dose vitamin E to higher all-cause mortality, at doses commonly sold. The list reports what trials used and found; it is not a set of recommendations.
- N-Acetylcysteine (NAC) — a cysteine prodrug that replenishes glutathione; best known as the antidote for acetaminophen (paracetamol) poisoning. A 2007 review noted that over two-thirds of 46 placebo-controlled trials of oral NAC reported beneficial effects, in conditions including HIV infection and COPD (Atkuri 2007). Its oral bioavailability as intact NAC is low: in 10 healthy volunteers given single 600 mg doses, oral availability ranged from 6 to 10% depending on the formulation (Borgström 1986).
- Glutathione (oral or liposomal) — oral glutathione was long considered poorly absorbed. In a 6-month randomized, double-blind, placebo-controlled trial in 54 non-smoking adults, oral glutathione at 250 or 1,000 mg/day raised glutathione levels in blood; at 6 months the high-dose group had 30–35% higher glutathione in erythrocytes, plasma and lymphocytes and 260% higher levels in buccal cells, and levels returned to baseline after a 1-month washout (Richie 2015). A 1-month pilot study of liposomal glutathione in 12 healthy adults reported rises in blood glutathione and falls in oxidative-stress markers (Sinha 2018); the study was funded by, and used a product supplied by, a supplement company.
- Alpha-lipoic acid — described as regenerating vitamins C and E. In the SYDNEY 2 trial (181 patients with diabetic polyneuropathy, 5 weeks), oral doses of 600, 1,200 and 1,800 mg once daily all reduced neuropathic symptoms more than placebo, with dose-dependent nausea, vomiting and vertigo; the authors judged 600 mg once daily to give the best risk-to-benefit ratio (Ziegler 2006)
- Vitamin C — in the Physicians' Health Study II (14,641 male physicians, mean follow-up 8 years), 500 mg/day of vitamin C did not reduce major cardiovascular events (hazard ratio 0.99, 95% CI 0.89 to 1.11) or total mortality (Sesso 2008). The US tolerable upper intake level for adults is 2,000 mg/day, set to prevent diarrhea and gastrointestinal disturbances.
- Vitamin E — the evidence points the other way. The SELECT trial gave healthy men 400 IU/day of alpha-tocopherol and found increased prostate cancer: hazard ratio 1.17 (99% CI 1.004 to 1.36, P = 0.008), an absolute excess of 1.6 cases per 1,000 person-years. A meta-analysis of 19 trials found a dose-response relationship with all-cause mortality, with increased risk above 150 IU/day; its authors concluded that high-dosage (400 IU/day or more) supplements "may increase all-cause mortality and should be avoided" (Miller 2005). In the Physicians' Health Study II, 400 IU every other day did not reduce major cardiovascular events and was associated with more hemorrhagic stroke (hazard ratio 1.74, 95% CI 1.04 to 2.91) (Sesso 2008). Food sources — nuts, seeds, olive oil, avocado — carry the wider family of tocopherols and tocotrienols; the trials above tested supplements, not foods.
- Selenium — harm reported in people already replete. Selenium is genuinely required for glutathione peroxidase, and deficiency is real in low-selenium soils. Trials have not found extra selenium benign: in a randomized trial in low-selenium areas of the eastern United States, 200 mcg/day for an average of 7.7 years increased type 2 diabetes incidence (hazard ratio 1.55, 95% CI 1.03 to 2.33), with the risk concentrated in those whose baseline plasma selenium was already in the highest third (hazard ratio 2.70, 95% CI 1.30 to 5.61) (Stranges 2007). In SELECT, 200 mcg/day did not reduce prostate cancer (hazard ratio 1.09, 99% CI 0.93 to 1.27) (Klein 2011). The selenium content of Brazil nuts depends on the soil: the Linus Pauling Institute reports that nuts from selenium-rich soil may provide more than 100 mcg in one nut and those from selenium-poor soil an amount 10 times lower. The US tolerable upper intake level for adults is 400 mcg/day from food and supplements combined.
- CoQ10 (ubiquinol) — carries electrons in the mitochondrial electron transport chain; its reduced form acts as a lipid-soluble antioxidant. Meta-analyses of CoQ10 for statin-associated muscle symptoms disagree: a 2015 analysis of 6 trials found no significant benefit (Banach 2015), while a 2018 analysis of 12 trials (575 patients) reported less muscle pain, weakness, cramps and tiredness but no change in creatine kinase (Qu 2018).
- Quercetin — a flavonoid with antioxidant properties, described in laboratory research as a mast-cell stabilizer
- Curcumin — curcumin alone is poorly absorbed; in human volunteers, 20 mg of piperine taken with 2 g of curcumin increased curcumin bioavailability by 2000% (Shoba 1998)
- Milk Thistle (silymarin) — for hepatic oxidative stress
Testing Oxidative Stress in the Lab
No single oxidative-stress lab test is universally accepted. Markers in use:
- 8-OHdG (urine or serum) — oxidized DNA marker; in a multilaboratory validation study in rats, urinary 8-OHdG was named a potential general biomarker of oxidative stress (Kadiiska 2005)
- F2-isoprostanes (urine) — lipid peroxidation; in the same rat validation study, plasma and urinary isoprostanes rose consistently with oxidative injury (Kadiiska 2005), and urinary F2-isoprostanes were the primary oxidative-stress measure in the CALERIE 2 trial (Il'yasova 2018)
- Malondialdehyde (MDA) — older lipid peroxidation marker; less specific
- 4-HNE (4-hydroxynonenal) — lipid peroxidation; research-grade
- GSH/GSSG ratio — the ratio of reduced to oxidized glutathione; a falling ratio indicates rising oxidative stress
- Total antioxidant capacity (TAC) — reasonable screening but non-specific
- Oxidized LDL — a marker of vascular oxidative stress
- Inflammatory markers — hs-CRP and others — not direct oxidative-stress markers but tightly linked downstream
- Homocysteine — indicates methylation and B-vitamin status; elevated levels are associated with oxidative stress
Routine clinical tests sometimes discussed alongside oxidative stress include hs-CRP, homocysteine, GGT, serum ferritin and oxidized LDL; none is a direct measure of oxidative damage. Direct oxidative markers (8-OHdG, F2-isoprostanes) are used mainly in research.
The Antioxidant Paradox
This is not a minor caveat. Isolated high-dose antioxidant supplements have been tested in very large randomized trials, and the results have been consistently disappointing — CARET was stopped early not for benefit but for harm.
- CARET gave beta-carotene plus vitamin A to 18,314 smokers and asbestos-exposed workers. Lung cancer rose (relative risk 1.28, 95% CI 1.04 to 1.57), death from lung cancer rose (1.46, 1.07 to 2.00), and death from any cause rose (1.17, 1.03 to 1.33). The trial was stopped 21 months early. The conclusion was that supplementation "had no benefit and may have had an adverse effect" (Omenn 1996).
- ATBC gave 20 mg/day of beta-carotene and/or 50 mg/day of vitamin E to 29,133 male smokers in Finland. Lung cancer incidence was 18% higher with beta-carotene (95% CI 3 to 36%) and total mortality 8% higher (1 to 16%); vitamin E did not reduce lung cancer, and more deaths from hemorrhagic stroke were seen with it (ATBC Study Group 1994).
- SELECT randomized 35,533 men; 400 IU/day of vitamin E increased prostate cancer (hazard ratio 1.17, 99% CI 1.004 to 1.36) (Klein 2011).
- A meta-analysis of 19 vitamin E trials found a dose-response relationship with all-cause mortality, with increased risk above 150 IU/day and a pooled excess of 39 deaths per 10,000 people in trials of 400 IU/day or more (95% CI 3 to 74) (Miller 2005).
- A 2012 Cochrane review of 78 randomized trials (296,707 participants) found no evidence to support antioxidant supplements for primary or secondary prevention. In trials at low risk of bias, beta-carotene (relative risk 1.05, 95% CI 1.01 to 1.09) and vitamin E (1.03, 1.00 to 1.05) increased mortality; vitamin A (1.07, 0.97 to 1.18), vitamin C and selenium did not significantly affect mortality, although higher doses of vitamin A were associated with higher mortality in meta-regression (Bjelakovic 2012).
- Selenium at 200 mcg/day for 7.7 years increased type 2 diabetes (hazard ratio 1.55, 95% CI 1.03 to 2.33), most in people whose baseline selenium was already high (Stranges 2007).
In the selenium trial the risk concentrated in people whose selenium was already highest at baseline, and in the vitamin E meta-analysis the risk rose with dose. Results like these run against the idea of "more antioxidants, less oxidative stress."
One explanation researchers have proposed: reactive oxygen species are not purely "bad." Cells use them for signaling, immune defense, exercise adaptation, and tumor surveillance, and mega-dose antioxidants may disrupt these signals. In a 2009 study in 39 healthy young men, 4 weeks of exercise improved insulin sensitivity and induced the muscle's own antioxidant enzymes only in men not taking vitamin C (1,000 mg/day) plus vitamin E (400 IU/day); the authors described this as mitohormesis (Ristow 2009). A 12-week endurance-training study in 21 men found that vitamins C and E did not alter training adaptations such as maximal oxygen uptake (Yfanti 2010). Approaches studied for upregulating the body's own antioxidant systems, rather than adding exogenous antioxidants, include:
- Polyphenol-rich whole foods (Nrf2 activators)
- Regular moderate exercise (mitochondrial biogenesis)
- Heat and cold exposure (hormetic stress)
- Adequate sleep
- Smoking cessation, alcohol moderation
- Supplementation for a documented deficiency, or for specific clinical uses tested in trials (for example alpha-lipoic acid in diabetic neuropathy)
Summary of the Research
The findings above, gathered in one place:
- The largest modifiable sources — smoking, heavy alcohol use and ultra-processed diets are among the external drivers of oxidative stress listed above.
- Exercise — regular exercise induced the muscle's own antioxidant enzymes in a training study (Ristow 2009).
- Plant foods — higher fruit and vegetable intake is associated with lower cardiovascular disease, cancer and all-cause mortality (Aune 2017); spices, dried herbs, cocoa products and dark berries are among the richest polyphenol sources (Pérez-Jiménez 2010).
- Caloric restriction — 2 years of 25% restriction lowered urinary F2-isoprostanes in healthy adults (Il'yasova 2018).
- Isolated high-dose antioxidants — beta-carotene and vitamin E supplements were linked to more cancer or higher mortality in large trials and reviews (CARET, ATBC, SELECT, Bjelakovic 2012).
- Testing — direct markers (8-OHdG, F2-isoprostanes) are mainly research tools; routine clinical tests are indirect.
- Decisions about supplements and testing belong with a clinician.
Key Research Papers
Key Research Papers
The trials, reviews and studies cited above, each linked by numeric PubMed ID so the figures can be checked.
- Omenn GS, Goodman GE, Thornquist MD, et al. Effects of a combination of beta carotene and vitamin A on lung cancer and cardiovascular disease (CARET). New England Journal of Medicine. 1996;334(18):1150-1155. Stopped 21 months early for harm. — PubMed PMID: 8602180
- Klein EA, Thompson IM Jr, Tangen CM, et al. Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA. 2011;306(14):1549-1556. — PubMed PMID: 21990298
- Miller ER 3rd, Pastor-Barriuso R, Dalal D, Riemersma RA, Appel LJ, Guallar E. Meta-analysis: high-dosage vitamin E supplementation may increase all-cause mortality. Annals of Internal Medicine. 2005;142(1):37-46. — PubMed PMID: 15537682
- Stranges S, Marshall JR, Natarajan R, et al. Effects of long-term selenium supplementation on the incidence of type 2 diabetes: a randomized trial. Annals of Internal Medicine. 2007;147(4):217-223. — PubMed PMID: 17620655
- Alpha-Tocopherol, Beta Carotene Cancer Prevention Study Group. The effect of vitamin E and beta carotene on the incidence of lung cancer and other cancers in male smokers. New England Journal of Medicine. 1994;330(15):1029-1035. — PubMed PMID: 8127329
- Bjelakovic G, Nikolova D, Gluud LL, Simonetti RG, Gluud C. Antioxidant supplements for prevention of mortality in healthy participants and patients with various diseases. Cochrane Database of Systematic Reviews. 2012;(3):CD007176. — PubMed PMID: 22419320
- Harman D. Aging: a theory based on free radical and radiation chemistry. Journal of Gerontology. 1956;11(3):298-300. — PubMed PMID: 13332224
- Pérez VI, Bokov A, Van Remmen H, et al. Is the oxidative stress theory of aging dead? Biochimica et Biophysica Acta. 2009;1790(10):1005-1014. — PubMed PMID: 19524016
- Ristow M, Zarse K, Oberbach A, et al. Antioxidants prevent health-promoting effects of physical exercise in humans. Proceedings of the National Academy of Sciences of the USA. 2009;106(21):8665-8670. — PubMed PMID: 19433800
- Yfanti C, Akerström T, Nielsen S, et al. Antioxidant supplementation does not alter endurance training adaptation. Medicine and Science in Sports and Exercise. 2010;42(7):1388-1395. — PubMed PMID: 20019626
- Murphy MP. How mitochondria produce reactive oxygen species. Biochemical Journal. 2009;417(1):1-13. — PubMed PMID: 19061483
- Valko M, Morris H, Cronin MT. Metals, toxicity and oxidative stress. Current Medicinal Chemistry. 2005;12(10):1161-1208. — PubMed PMID: 15892631
- Kadiiska MB, Gladen BC, Baird DD, et al. Biomarkers of oxidative stress study II: are oxidation products of lipids, proteins, and DNA markers of CCl4 poisoning? Free Radical Biology and Medicine. 2005;38(6):698-710. — PubMed PMID: 15721980
- Il'yasova D, Fontana L, Bhapkar M, et al. Effects of 2 years of caloric restriction on oxidative status assessed by urinary F2-isoprostanes: the CALERIE 2 randomized clinical trial. Aging Cell. 2018;17(2):e12719. — PubMed PMID: 29424490
- Aune D, Giovannucci E, Boffetta P, et al. Fruit and vegetable intake and the risk of cardiovascular disease, total cancer and all-cause mortality: a systematic review and dose-response meta-analysis of prospective studies. International Journal of Epidemiology. 2017;46(3):1029-1056. — PubMed PMID: 28338764
- Pérez-Jiménez J, Neveu V, Vos F, Scalbert A. Identification of the 100 richest dietary sources of polyphenols: an application of the Phenol-Explorer database. European Journal of Clinical Nutrition. 2010;64(Suppl 3):S112-S120. — PubMed PMID: 21045839
- Pérez-Jiménez J, Fezeu L, Touvier M, et al. Dietary intake of 337 polyphenols in French adults. American Journal of Clinical Nutrition. 2011;93(6):1220-1228. — PubMed PMID: 21490142
- Atkuri KR, Mantovani JJ, Herzenberg LA, Herzenberg LA. N-Acetylcysteine — a safe antidote for cysteine/glutathione deficiency. Current Opinion in Pharmacology. 2007;7(4):355-359. — PubMed PMID: 17602868
- Borgström L, Kågedal B, Paulsen O. Pharmacokinetics of N-acetylcysteine in man. European Journal of Clinical Pharmacology. 1986;31(2):217-222. — PubMed PMID: 3803419
- Richie JP Jr, Nichenametla S, Neidig W, et al. Randomized controlled trial of oral glutathione supplementation on body stores of glutathione. European Journal of Nutrition. 2015;54(2):251-263. — PubMed PMID: 24791752
- Sinha R, Sinha I, Calcagnotto A, et al. Oral supplementation with liposomal glutathione elevates body stores of glutathione and markers of immune function. European Journal of Clinical Nutrition. 2018;72(1):105-111. — PubMed PMID: 28853742
- Ziegler D, Ametov A, Barinov A, et al. Oral treatment with alpha-lipoic acid improves symptomatic diabetic polyneuropathy: the SYDNEY 2 trial. Diabetes Care. 2006;29(11):2365-2370. — PubMed PMID: 17065669
- Sesso HD, Buring JE, Christen WG, et al. Vitamins E and C in the prevention of cardiovascular disease in men: the Physicians' Health Study II randomized controlled trial. JAMA. 2008;300(18):2123-2133. — PubMed PMID: 18997197
- Banach M, Serban C, Sahebkar A, et al. Effects of coenzyme Q10 on statin-induced myopathy: a meta-analysis of randomized controlled trials. Mayo Clinic Proceedings. 2015;90(1):24-34. — PubMed PMID: 25440725
- Qu H, Guo M, Chai H, et al. Effects of coenzyme Q10 on statin-induced myopathy: an updated meta-analysis of randomized controlled trials. Journal of the American Heart Association. 2018;7(19):e009835. — PubMed PMID: 30371340
- Shoba G, Joy D, Joseph T, et al. Influence of piperine on the pharmacokinetics of curcumin in animals and human volunteers. Planta Medica. 1998;64(4):353-356. — PubMed PMID: 9619120
PubMed Topic Searches
- PubMed: Oxidative stress and ROS
- PubMed: Nrf2 master regulator
- PubMed: Glutathione redox marker
- PubMed: F2-isoprostanes
- PubMed: 8-OHdG DNA oxidation
- PubMed: NAC and glutathione trials
- PubMed: Antioxidant supplements and mortality
- PubMed: Antioxidants and exercise adaptation
- PubMed: Exercise hormesis
- PubMed: Sulforaphane and Nrf2
- PubMed: Oxidized LDL and atherosclerosis
- PubMed: The ATBC prevention trial
External Authoritative Resources
Connections
- All Remedies
- All Antioxidants
- Alpha Lipoic Acid
- NAC
- Vitamin C
- Vitamin E
- Selenium
- Zinc
- Turmeric
- Milk Thistle
- Quercetin
- Inflammatory Markers
- Homocysteine
- GGT
- Glutathione
- Copper
- Manganese
- Anti-Inflammatory Diet
- Longevity Protocols
- Mercury
- Lead
- Conditions on this site that reference this page: Bacillus subtilis · Aortic Aneurysm · Vitiligo · Amyotrophic Lateral Sclerosis (ALS) · Friedreich's Ataxia · Huntington's Disease · Cataracts · Glaucoma
Featured Videos