Selenium and Cancer Prevention: Selenoproteins, the NPC and SELECT Trials, and the U-Shaped Dose-Response Curve
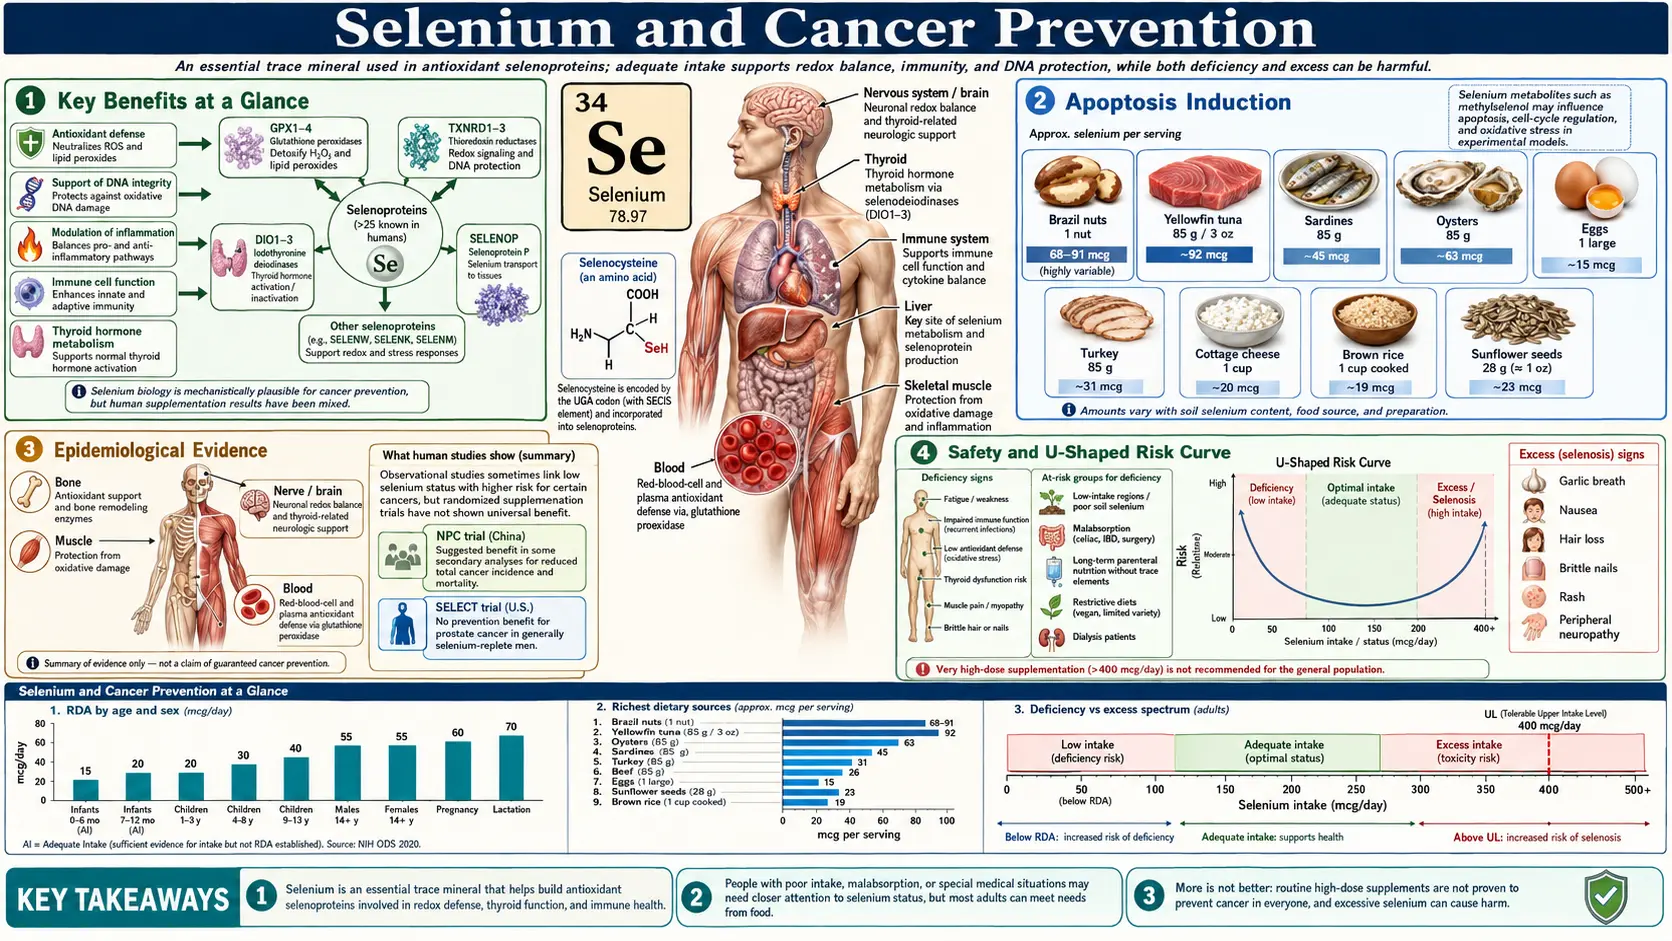
Few nutrients have generated as much excitement — or as much subsequent disappointment — in cancer chemoprevention research as selenium. The story arc runs from a landmark 1996 trial that appeared to slash prostate, colorectal, and lung cancer incidence at 200 µg/day, through a much larger 2009 trial that failed to reproduce any benefit, to a current understanding that selenium's anticancer effects depend critically on baseline selenium status, the chemical form supplied, the specific cancer type, and host genetics. This page maps the biology of selenoproteins as cancer modulators, walks through the NPC and SELECT trials and what they actually taught us, and finishes with what the trials mean for who might benefit from selenium — and in whom the research raises concerns.
Table of Contents
- Overview: Selenium as a Cancer-Modulating Trace Element
- Selenoprotein Biology and Glutathione Peroxidase
- The Nutritional Prevention of Cancer (NPC) Trial, 1996
- The SELECT Trial, 2009 — A Null Result and What It Taught Us
- Prostate Cancer Evidence
- Colorectal, Lung, Liver, and Thyroid Cancer Signals
- The U-Shaped Dose-Response Curve and Diabetes Signal
- Food Forms vs Supplement Forms — Brazil Nut Variability
- Selenium Status Testing and the Optimal Range
- What the Trials Mean for Supplement Use
- Key Research Papers
- Connections
- Featured Videos
Overview: Selenium as a Cancer-Modulating Trace Element
Selenium is an essential trace element required in microgram quantities for the synthesis of selenoproteins — a family of approximately 25 enzymes in humans that incorporate the 21st amino acid, selenocysteine, at their catalytic sites. Several of these selenoproteins sit at the intersection of pathways that matter for cancer: oxidative stress regulation, DNA damage repair, programmed cell death, immune surveillance, and inflammation. For most of the late 20th century, ecological data linking selenium-poor soils to higher cancer mortality, plus mechanistic work showing selenium-induced apoptosis in tumor cells, generated a confident narrative that more selenium should mean less cancer.
The reality turned out to be more complicated. Selenium operates with a narrow therapeutic window. At deficient baseline, raising selenium status improves selenoprotein expression and may meaningfully reduce cancer risk — this is what the NPC trial captured in selenium-replete-to-low American adults in the 1980s and 1990s. At adequate baseline, additional selenium does not reliably reduce risk and may, depending on form and population, produce small adverse signals including increased risk of type 2 diabetes and possibly an increase in aggressive prostate cancer — this is what the SELECT trial captured. The shape of the dose-response curve matters more than the headline question of whether selenium "prevents cancer."
The practical synthesis: selenium is necessary for normal selenoprotein function and that function is anti-carcinogenic; supplementing already-adequate adults with high-dose selenium is not a cancer-prevention strategy and carries small but real risks.
Selenoprotein Biology and Glutathione Peroxidase
Selenium's anticancer effects route almost entirely through selenoproteins. Free selenocysteine and other low-molecular-weight selenium metabolites have direct cytotoxic effects on tumor cells in culture, but in vivo it is the selenoprotein machinery that drives the population-level signals.
- Glutathione peroxidases (GPx1, GPx2, GPx3, GPx4) — reduce hydrogen peroxide and lipid hydroperoxides to harmless alcohols using glutathione as the electron donor. GPx1 (cytosolic, ubiquitous) lowers steady-state H2O2 and limits oxidative DNA damage. GPx2 protects the gastrointestinal epithelium — relevant to colorectal cancer. GPx4 reduces phospholipid hydroperoxides in membranes and is now recognized as the master regulator of ferroptosis, an iron-dependent form of lipid-peroxidation-driven cell death that some tumor types are exquisitely sensitive to.
- Thioredoxin reductases (TrxR1, TrxR2, TrxR3) — maintain the thioredoxin system in its reduced state. TrxR1 supports DNA synthesis (ribonucleotide reductase needs reduced thioredoxin), modulates apoptosis through ASK1 regulation, and influences transcription factors such as p53, NF-kB, and AP-1. TrxR1 is paradoxically overexpressed in many tumors, where it supports proliferation — one reason that the "more selenium = less cancer" story is not as clean as early researchers hoped.
- Selenoprotein P (SELENOP) — the dominant plasma selenium transport protein, carrying up to 10 selenocysteine residues. SELENOP delivers selenium to peripheral tissues via the ApoER2 and megalin receptors and also has intrinsic antioxidant activity. Plasma SELENOP is the most informative biomarker of functional selenium status — it plateaus once selenoprotein synthesis is saturated, which happens around a plasma selenium of 125 ng/mL.
- Selenoprotein F, H, K, M, S, T, V, W — smaller and less-characterized selenoproteins variously involved in endoplasmic reticulum quality control, redox signaling, calcium handling, and inflammation. Several have been implicated in carcinogenesis through mechanisms that are still being mapped.
- Iodothyronine deiodinases (DIO1, DIO2, DIO3) — activate and inactivate thyroid hormones. Indirectly relevant to cancer through thyroid-driven metabolic effects.
How selenoproteins suppress carcinogenesis, in summary: they reduce oxidative DNA damage (lower 8-oxoguanine and double-strand-break frequency); they protect DNA-repair machinery from oxidative inactivation; they regulate apoptosis pathways so that damaged cells are eliminated rather than allowed to clonally expand; they support immune surveillance through effects on natural killer (NK) cells, T cells, and macrophage polarization; and they modulate inflammation, attenuating the chronic low-grade inflammatory tone that drives several cancers.
Importantly, selenoprotein synthesis saturates. Once the body has enough selenium to fully express the selenoprotein hierarchy — somewhere around 125 ng/mL plasma selenium — additional selenium intake does not raise selenoprotein levels further. It instead feeds into the metabolic pool of low-molecular-weight selenium metabolites such as selenomethionine (incorporated nonspecifically into body proteins), methylselenocysteine, and methylselenol. Those metabolites have their own pharmacology, some beneficial and some not, but they no longer leverage the selenoprotein system.
The Nutritional Prevention of Cancer (NPC) Trial, 1996
The Nutritional Prevention of Cancer trial, led by Larry Clark and published in JAMA in 1996, is the single piece of evidence most responsible for the optimism about selenium chemoprevention. NPC randomized 1,312 American adults with a history of basal-cell or squamous-cell skin cancer to either 200 µg/day of high-selenium yeast (Se-yeast, a mixed organic form dominated by selenomethionine) or placebo. The primary endpoint was incidence of new skin cancers. Participants were treated for a mean of 4.5 years; total follow-up averaged 6.4 years.
Selenium did not reduce non-melanoma skin cancer incidence — the primary endpoint was negative. The striking findings were in the secondary cancer endpoints:
- Total cancer incidence — reduced by approximately 37% (relative risk 0.63, 95% confidence interval (CI) 0.47–0.85)
- Total cancer mortality — reduced by approximately 50% (relative risk (RR) 0.50, 95% confidence interval 0.31–0.80)
- Prostate cancer incidence — reduced by approximately 63% (relative risk 0.37)
- Colorectal cancer incidence — reduced by approximately 58%
- Lung cancer incidence — reduced by approximately 46%
These were extraordinary effect sizes for a single nutrient intervention. The trial's Data and Safety Monitoring Committee terminated the blinded portion of the trial early in 1996 specifically because of the secondary cancer benefit signals, which were considered too large to keep withholding from the control arm.
Several features of NPC matter for interpreting it. The study population had a mean baseline plasma selenium of approximately 113 ng/mL — in the lower end of the modern adequate range, and below the saturation level for selenoprotein P expression. The selenium form was Se-yeast, which delivers a mix of selenomethionine, selenocysteine, methylselenocysteine, and inorganic selenium — importantly, it includes the methylated metabolites that have the strongest preclinical anticancer signals. The dose was 200 µg/day on top of typical American dietary intake of 100–130 µg/day. Clark LC et al., JAMA 1996;276(24):1957–63. PMID 8971064. doi:10.1001/jama.1996.03540240035027 The trial's 2002 summary report found the reduction in total cancer incidence confined to participants in the lowest two tertiles of baseline plasma selenium (below 121.6 ng/mL); participants in the highest tertile showed no benefit and a non-significantly elevated incidence (hazard ratio 1.20, 95% CI 0.77–1.86). Duffield-Lillico AJ et al., Cancer Epidemiol Biomarkers Prev 2002;11(7):630–9. PMID 12101110
Analyses to the end of blinded treatment (1996) found the prostate cancer reduction persisted (relative risk 0.51, 95% CI 0.29–0.87), confined to men with lower baseline plasma selenium and PSA, Duffield-Lillico AJ et al., BJU Int 2003;91(7):608–12. PMID 12699469. doi:10.1046/j.1464-410X.2003.04167.x while the lung (hazard ratio 0.74, 95% CI 0.44–1.24) and colorectal (hazard ratio 0.46, 95% CI 0.21–1.02) reductions were no longer statistically significant. Duffield-Lillico AJ et al., Cancer Epidemiol Biomarkers Prev 2002;11(7):630–9. PMID 12101110
The SELECT Trial, 2009 — A Null Result and What It Taught Us
The Selenium and Vitamin E Cancer Prevention Trial (SELECT) was designed to definitively answer whether selenium, vitamin E, or both could prevent prostate cancer in healthy men. SELECT randomized 35,533 men aged 50+ (or 55+, depending on ethnicity) at 427 sites in the U.S., Canada, and Puerto Rico to four arms: selenium alone (200 µg/day as L-selenomethionine), vitamin E alone (400 international units (IU)/day as all-rac-alpha-tocopheryl acetate), both, or placebo.
SELECT was halted early in October 2008 by its Data and Safety Monitoring Committee for futility (no chance of demonstrating a benefit) and concerns about adverse signals. The 2009 primary analysis (median follow-up 5.5 years) reported:
- No reduction in prostate cancer incidence with selenium alone (hazard ratio 1.04, 99% confidence interval 0.87–1.24)
- No reduction with vitamin E alone (hazard ratio (HR) 1.13, 99% confidence interval 0.95–1.35; not statistically significant in primary analysis)
- No interaction between selenium and vitamin E
- Non-statistically-significant signals for increased type 2 diabetes (selenium arm) and increased prostate cancer (vitamin E arm)
A 2011 update with longer follow-up (median 7 years, plus several additional years of post-intervention observation) showed that the vitamin E arm had a statistically significant 17% increase in prostate cancer (hazard ratio 1.17, 99% confidence interval 1.004–1.36, P = 0.008) and that the combined selenium + vitamin E arm had no benefit either. Lippman SM et al., JAMA 2009;301(1):39–51. PMID 19066370. doi:10.1001/jama.2008.864 · Klein EA et al., JAMA 2011;306(14):1549–56. PMID 21990298. doi:10.1001/jama.2011.1437
Why did SELECT fail to reproduce NPC? Several reasons, none mutually exclusive:
- Higher baseline selenium status. SELECT enrolled men with a mean baseline plasma selenium of approximately 135 ng/mL — above the saturation level for plasma selenoprotein P expression. Additional selenium had no selenoprotein headroom to fill. NPC enrolled at a mean baseline of 113 ng/mL, where additional selenium meaningfully raised selenoprotein synthesis.
- Different chemical form. SELECT used pure L-selenomethionine. NPC used selenized yeast, which contains selenomethionine plus methylselenocysteine, selenocysteine, and several minor methylated species. Methylselenocysteine in particular is metabolized to methylselenol, which preclinical work suggests is the actual anticancer effector through pro-apoptotic and anti-angiogenic mechanisms. Selenomethionine, by contrast, is largely incorporated nonspecifically into body proteins as a methionine substitute — building a selenium pool that does not have the same pharmacology as methylated metabolites.
- Different study population. NPC enrolled high-risk men (history of non-melanoma skin cancer, predominantly older). SELECT enrolled a healthy, lower-baseline-risk population.
- Secondary endpoint overinterpretation in NPC. NPC's prostate cancer result was a secondary endpoint (the secondary endpoints were set in 1990, years after enrollment began in 1983) in a trial whose primary skin-cancer endpoint was negative. The whole trial recorded 196 cancers of all types by the 1996 report, so site-specific counts were small and the confidence intervals wide; secondary-endpoint signals from prematurely-stopped trials are notorious for shrinking on replication.
- Genetics. Subsequent analysis has shown selenoprotein and antioxidant-enzyme gene polymorphisms (in SEP15, SELENOP, GPX1 and the manganese superoxide dismutase gene SOD2) modify the response to selenium in ways that can flip the direction of effect for prostate cancer.
The post-SELECT consensus: selenomethionine supplementation does not prevent prostate cancer in already-replete men and, in men with higher baseline selenium status, was associated with more high-grade prostate cancer. Kristal AR et al., J Natl Cancer Inst 2014;106(3):djt456. PMID 24563519. doi:10.1093/jnci/djt456
Prostate Cancer Evidence
After the SELECT reversal, the prostate-cancer-and-selenium literature has been thoroughly reanalyzed.
The Kristal et al. 2014 case-cohort analysis of SELECT grouped men by baseline toenail selenium. Selenium supplementation had no effect among men with low selenium status (below the 60th percentile of toenail selenium) but increased the risk of high-grade (Gleason 7–10) prostate cancer by 91% among men with higher selenium status. Vitamin E alone increased prostate cancer risk among men with lower selenium status. The authors concluded that men should avoid selenium or vitamin E supplementation at doses that exceed recommended dietary intakes. This is the clearest direct trial evidence in humans that selenium's effect depends on baseline status.
Cohort studies have consistently shown that low selenium status — serum selenium below approximately 80 ng/mL, or toenail selenium in the lowest quintile — is associated with increased prostate cancer incidence and mortality. A 2012 meta-analysis of 12 studies found, in a non-linear dose-response analysis, that prostate cancer risk decreased with increasing plasma/serum selenium up to 170 ng/mL. — Hurst R et al., Am J Clin Nutr 2012;96(1):111–22. PMID 22648711 A 2018 meta-analysis pooling 38 studies of all designs (case-control, cohort and randomized trials; 36,419 cases) reported a pooled relative risk of 0.86 (95% CI 0.78–0.94) for the selenium–prostate cancer association. — Sayehmiri K et al., Asian Pac J Cancer Prev 2018;19(6):1431–7. PMID 29936712
A 2018 Cochrane review (83 studies, covering both observational studies and randomized controlled trials, RCTs) found that well-conducted RCTs showed no beneficial effect of selenium supplements in reducing cancer risk (high certainty of evidence); some RCTs reported more high-grade prostate cancer and type 2 diabetes with supplementation, and the NPC hypothesis that people with low blood selenium could reduce their cancer risk by increasing intake has not been confirmed, with no clear influence of baseline selenium status emerging. Observational studies showed an inverse association for some cancer types, but null and direct relations were also reported, no systematic dose-response pattern emerged, and those studies suffer from exposure misclassification and unmeasured confounding. The review concluded there is no evidence that increasing selenium intake through diet or supplementation prevents cancer in humans. — Vinceti M et al., Cochrane Database Syst Rev 2018;1:CD005195. PMID 29376219
Colorectal, Lung, Liver, and Thyroid Cancer Signals
Colorectal cancer. NPC's reported 58% reduction in colorectal cancer incidence has not been clearly reproduced in subsequent randomized controlled trials, but observational evidence is reasonably consistent that low selenium status is associated with higher colorectal cancer risk. A 2015 nested case-control study within the European Prospective Investigation into Cancer and Nutrition (EPIC; 966 cases, 966 matched controls) found higher serum selenium associated with a non-significant lower colorectal cancer risk overall (incidence rate ratio 0.92, 95% CI 0.82–1.03 per 25 µg/L increase), with a statistically significant association in women (0.83, 95% CI 0.70–0.97) but not in men. — Hughes DJ et al., Int J Cancer 2015;136(5):1149–61. PMID 25042282 The likely mechanism: GPx2 expression in colorectal mucosa, which is upregulated by adequate selenium and limits oxidative damage to colonocyte DNA.
Lung cancer. NPC's 46% reduction in lung cancer signal also faded over longer follow-up. Observational pooled analyses suggest a modest inverse association between serum selenium and lung cancer in non-smokers, but not in current smokers — possibly because the magnitude of carcinogen exposure in smokers overwhelms any selenium-derived antioxidant protection. The general signal aligns with a role for GPx1 and TrxR1 in pulmonary epithelial oxidative defense.
Hepatocellular carcinoma (liver). Some of the strongest selenium-cancer signals come from regions with both selenium deficiency and high hepatitis B prevalence. The Qidong, China selenium intervention study fortified table salt with sodium selenite in a hepatitis B virus-endemic region and reported substantial reductions in primary liver cancer incidence over several years of follow-up. Mechanistically, GPx1 and SELENOP attenuate hepatocyte oxidative damage and may slow hepatitis B virus-driven oncogenesis. The Qidong result is hard to generalize to selenium-replete populations.
Thyroid cancer. The thyroid concentrates more selenium per gram than any other organ and depends on selenoprotein-mediated peroxide handling during thyroid hormone synthesis. Observational studies link low serum selenium with higher differentiated thyroid cancer risk and with worse autoimmune thyroid status, but randomized controlled trial (RCT) evidence for selenium supplementation as thyroid cancer prevention is limited. Selenium supplementation does have an established role in autoimmune thyroiditis (reducing thyroid peroxidase (TPO) antibody titers in Hashimoto's), which is a separate clinical use from cancer prevention — see Selenium and Thyroid Function.
The U-Shaped Dose-Response Curve and Diabetes Signal
The biggest mental-model update from the NPC-to-SELECT arc is that selenium follows a U-shaped (or J-shaped) dose-response curve for several outcomes including total cancer mortality, prostate cancer aggressiveness, type 2 diabetes risk, and probably all-cause mortality.
At plasma selenium below approximately 80 ng/mL, selenoprotein synthesis is incomplete and several health outcomes are worse: higher cancer risk, weaker immune function, possibly higher cardiovascular mortality, and increased Keshan-disease vulnerability in regions with appropriate cofactors. Raising plasma selenium toward 120–150 ng/mL improves these outcomes.
At plasma selenium above 150 ng/mL, the benefits plateau and adverse signals begin to appear. Above approximately 160 ng/mL, large cohorts such as NHANES and EPIC have reported increasing risk of type 2 diabetes. In a secondary analysis of the NPC trial, type 2 diabetes developed in 58 selenium recipients and 39 placebo recipients over an average 7.7 years (hazard ratio 1.55, 95% CI 1.03–2.33), with the highest risk in the top tertile of baseline plasma selenium (hazard ratio 2.70). — Stranges S et al., Ann Intern Med 2007;147(4):217–23. PMID 17620655 The mechanism is believed to involve selenoprotein P interference with insulin signaling: SELENOP at high concentrations binds to the insulin receptor pathway and reduces glucose uptake, and excess selenoprotein expression interferes with the redox signaling required for normal insulin secretion. Above 200 ng/mL, the diabetes signal is statistically robust across multiple study designs.
For cancer, the SELECT-Kristal analysis suggests that the upward arm of the U-curve includes increased high-grade prostate cancer in men with higher baseline selenium status.
The toxicity threshold is much higher than the cancer-mortality threshold. Chronic intake above 400 µg/day produces selenosis: garlic breath, hair and nail loss, dermatitis, peripheral neuropathy. Much larger doses cause acute poisoning: in a 2008 United States outbreak traced to a liquid dietary supplement containing 200 times its labeled selenium concentration, 201 people in 10 states were affected after consuming a median estimated 41,749 µg/day; the most frequent symptoms were diarrhea, fatigue, hair loss, joint pain, nail discoloration or brittleness and nausea, and 1 person was hospitalized. MacFarquhar JK et al., Arch Intern Med 2010;170(3):256–61. PMID 20142570 Acute single ingestions above approximately 1,000–5,000 µg (typically from contaminated supplements — the 2008 supplement recall delivered 200× the labeled dose, causing widespread selenosis) cause severe gastrointestinal distress, cardiomyopathy, and occasionally death. The Tolerable Upper Intake Level set by the IOM is 400 µg/day for adults; in 2023 the European Food Safety Authority (EFSA) set a lower upper level of 255 µg/day for adults, based on the hair loss (alopecia) seen in SELECT. EFSA NDA Panel, EFSA J 2023;21(1):e07704. PMID 36698500
Food Forms vs Supplement Forms — Brazil Nut Variability
The chemical form of dietary selenium matters for pharmacology, and the variability is larger than most consumers realize.
- Brazil nuts (Bertholletia excelsa) — the single richest dietary source. Reported selenium content ranges from 8 µg per nut to over 90 µg per nut depending on the Amazonian soil where the tree grew. The amount on the bag almost never reflects the actual content. A "one Brazil nut per day" strategy can produce anything from sub-RDA intake to 200 µg over the upper limit if the nuts come from a high-selenium-soil region. Brazil nuts deliver selenium primarily as selenomethionine.
- Seafood — tuna, sardines, halibut, shrimp, oysters all deliver 30–90 µg per typical serving, predominantly as selenocysteine in animal proteins.
- Organ meats — liver, kidney deliver 25–50 µg per serving.
- Muscle meats, eggs, dairy — modest sources at 10–30 µg per serving, content varying with the selenium in animal feed.
- Whole grains and seeds — sunflower seeds, wheat bran, brown rice deliver 10–30 µg per serving, content tracking soil selenium very strongly.
For supplements:
- L-selenomethionine — the form used in SELECT. Highly bioavailable, incorporated nonspecifically into body proteins as a methionine substitute, builds a slow-turnover body selenium pool. Does not appear to deliver the anticancer effects researchers hoped for in already-replete people.
- Selenized yeast (high-selenium yeast) — the form used in NPC. A mixed organic preparation, predominantly selenomethionine (about 55–70%) plus methylselenocysteine, selenocysteine, gamma-glutamyl-methylselenocysteine, and minor selenosugars. Higher in methylated species than pure selenomethionine and more closely resembles food-form selenium. Some experts argue Se-yeast is the form most likely to reproduce a cancer-prevention signal if a future trial is done in genuinely low-selenium populations.
- Sodium selenite and sodium selenate — inorganic forms, less efficiently incorporated into selenoproteins than organic forms. Used in some hospital nutrition products and in the Qidong selenium-fortified-salt liver cancer trial. Cheaper but with poorer bioavailability and higher pro-oxidant toxicity at higher doses.
- Selenium-methylselenocysteine (Se-MSC, sometimes labeled methylselenocysteine) — the pure methylated form. Strongest preclinical anticancer signal of any selenium species through pro-apoptotic and anti-angiogenic methylselenol generation. Limited human trial data. Some integrative oncologists use it specifically because the SELECT-style selenomethionine evidence does not generalize to methylated forms.
Selenium Status Testing and the Optimal Range
Three lab tests usefully assess selenium status:
- Serum or plasma selenium — the most widely available test. Reflects intake over the prior several days to weeks. Reference range typically 70–150 ng/mL; population means vary by country (U.S. mean approximately 135 ng/mL, U.K. mean approximately 90 ng/mL, several European countries with selenium-poor soils below 80 ng/mL). The cancer-mortality minimum sits around 120–150 ng/mL.
- Plasma selenoprotein P (SELENOP) — the most informative functional biomarker. SELENOP synthesis saturates at plasma selenium near 125 ng/mL and a SELENOP concentration above approximately 4–5 mg/L. Below that, additional selenium will raise SELENOP further. Above it, selenoprotein synthesis is already maximal and further supplementation feeds only the metabolic selenium pool. Available through commercial laboratories, usually as a send-out test.
- Erythrocyte or platelet glutathione peroxidase activity — a functional assay reflecting longer-term selenium status. Useful in research; less available clinically.
- Toenail selenium — reflects integrated selenium intake over the prior 6–12 months. Used in epidemiology because of its longer integration window.
Optimal serum selenium range for cancer-related outcomes is approximately 120–150 ng/mL. Above 170–180 ng/mL the diabetes signal kicks in; above 400 ng/mL chronic toxicity becomes a real concern. Below 80 ng/mL most observational signals for cancer, cardiovascular disease, and immune function are unfavorable.
How these ranges line up with the trials: SELECT enrolled men with a mean baseline plasma selenium near 135 ng/mL and found no benefit from 200 µg/day, while NPC's benefit was confined to participants below about 121.6 ng/mL at baseline. A plasma selenium measurement is the only way to know where a person sits on this curve. The IOM upper limit for total intake is 400 µg/day and the EFSA upper limit 255 µg/day; the signs of too much selenium (selenosis) are garlic breath, hair and nail loss, skin rash (dermatitis) and nerve damage (peripheral neuropathy).
What the Trials Mean for Supplement Use
The cleanest synthesis the post-SELECT evidence supports:
- Baseline plasma selenium above approximately 130 ng/mL. SELECT's men (mean baseline about 135 ng/mL) gained no prostate cancer protection from 200 µg/day, and the diabetes and high-grade-prostate-cancer signals lean in the wrong direction. This range includes most American adults eating a typical Western diet that includes any seafood, meat, eggs, or wheat-based grains.
- Baseline plasma selenium 100–130 ng/mL. This range is close to NPC's mean baseline of about 113 ng/mL. A modest supplement (50–100 µg/day) or one Brazil nut every other day is the amount commonly described for reaching the 120–150 range; Se-yeast (the NPC form) and methylselenocysteine differ chemically from the pure selenomethionine used in SELECT.
- Baseline plasma selenium below 100 ng/mL, especially below 80. This is where selenoprotein synthesis has room to rise and where the observational signals for cancer, heart disease and immune function are unfavorable. Amounts commonly described are 100–200 µg/day for three months followed by a retest; low intake from food or from selenium-poor soils is the usual cause.
- Type 2 diabetes, pre-diabetes, or a strong family history of either. The diabetes-promoting signal from high-dose selenium (hazard ratio 1.55 in NPC, 2.70 in its highest baseline tertile) is most relevant to this population; the lower end of the optimal range (120–130 ng/mL, not 150) is the part of the curve furthest from that signal.
- A personal or strong family history of aggressive prostate cancer. The SELECT-Kristal finding — more high-grade prostate cancer with L-selenomethionine among men with higher baseline selenium status — is the research concern most relevant here. Dietary intake from seafood, Brazil nuts (one a week, not one a day) and whole grains is a different exposure from the 200 µg/day pharmacologic dose tested in SELECT.
- Hashimoto's thyroiditis. The selenium-for-thyroid evidence (200 µg/day Se-yeast or selenomethionine, 3–6 months) is a separate clinical use with its own risk-benefit calculus. Many Hashimoto's patients reach 150–180 ng/mL during treatment, above the range linked to the best cancer outcomes.
- Hemodialysis, total parenteral nutrition without selenium, or severe malabsorption carry a real risk of selenium deficiency, the setting where supplemental selenium has its clearest use.
- Upper limits. The IOM Tolerable Upper Intake Level is 400 µg/day of total intake (food + supplement) for adults, and EFSA's 2023 upper level is 255 µg/day. SELECT and NPC both gave 200 µg/day of supplemental selenium on top of dietary intake.
For healthy adults eating a varied diet that includes seafood or meat in a country with adequate soil selenium (most of North America, much of Asia and South America), the trials above found no cancer-prevention gain from supplements. Food sources such as seafood (30–90 µg per serving) and Brazil nuts supply selenium, and the wide nut-to-nut variability of Brazil nuts is why one or two a week, rather than one a day, is the amount often cited. The "more is better" intuition that motivated SELECT did not hold up; the evidence points to "enough, and not more."
Key Research Papers
- Clark LC, Combs GF Jr, Turnbull BW, et al. Effects of selenium supplementation for cancer prevention in patients with carcinoma of the skin: a randomized controlled trial (the NPC trial). JAMA. 1996;276(24):1957–63. PubMed PMID: 8971064. doi:10.1001/jama.1996.03540240035027. — PubMed PMID: 8971064
- Lippman SM, Klein EA, Goodman PJ, et al. Effect of selenium and vitamin E on risk of prostate cancer and other cancers: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA. 2009;301(1):39–51. PubMed PMID: 19066370. doi:10.1001/jama.2008.864. — PubMed PMID: 19066370
- Klein EA, Thompson IM Jr, Tangen CM, et al. Vitamin E and the risk of prostate cancer: the Selenium and Vitamin E Cancer Prevention Trial (SELECT). JAMA. 2011;306(14):1549–56. PubMed PMID: 21990298. doi:10.1001/jama.2011.1437. — PubMed PMID: 21990298
- Kristal AR, Darke AK, Morris JS, et al. Baseline selenium status and effects of selenium and vitamin E supplementation on prostate cancer risk. J Natl Cancer Inst. 2014;106(3):djt456. PubMed PMID: 24563519. doi:10.1093/jnci/djt456. — PubMed PMID: 24563519
- Vinceti M, Filippini T, Del Giovane C, et al. Selenium for preventing cancer. Cochrane Database Syst Rev. 2018;1(1):CD005195. — PubMed PMID: 29376219
- Stranges S, Marshall JR, Natarajan R, et al. Effects of long-term selenium supplementation on the incidence of type 2 diabetes: a randomized trial. Ann Intern Med. 2007;147(4):217–23. — PubMed PMID: 17620655
- Duffield-Lillico AJ, Dalkin BL, Reid ME, et al. Selenium supplementation, baseline plasma selenium status and incidence of prostate cancer: an analysis of the complete treatment period of the Nutritional Prevention of Cancer Trial. BJU Int. 2003;91(7):608–12. doi:10.1046/j.1464-410X.2003.04167.x. — PubMed PMID: 12699469
- Duffield-Lillico AJ, Reid ME, Turnbull BW, et al. Baseline characteristics and the effect of selenium supplementation on cancer incidence in a randomized clinical trial: a summary report of the Nutritional Prevention of Cancer Trial. Cancer Epidemiol Biomarkers Prev. 2002;11(7):630–9. — PubMed PMID: 12101110
- Hughes DJ, Fedirko V, Jenab M, et al. Selenium status is associated with colorectal cancer risk in the European prospective investigation of cancer and nutrition cohort. Int J Cancer. 2015;136(5):1149–61. — PubMed PMID: 25042282
- Sayehmiri K, Azami M, Mohammadi Y, et al. The association between selenium and prostate cancer: a systematic review and meta-analysis. Asian Pac J Cancer Prev. 2018;19(6):1431–7. — PubMed PMID: 29936712
- Hurst R, Hooper L, Norat T, et al. Selenium and prostate cancer: systematic review and meta-analysis. Am J Clin Nutr. 2012;96(1):111–22. — PubMed PMID: 22648711
- MacFarquhar JK, Broussard DL, Melstrom P, et al. Acute selenium toxicity associated with a dietary supplement. Arch Intern Med. 2010;170(3):256–61. — PubMed PMID: 20142570
- EFSA Panel on Nutrition, Novel Foods and Food Allergens (NDA), Turck D, Bohn T, et al. Scientific opinion on the tolerable upper intake level for selenium. EFSA J. 2023;21(1):e07704. — PubMed PMID: 36698500
- Search PubMed
- Search PubMed
- Search PubMed
Connections
- All Minerals
- Selenium Overview
- Selenium Benefits Deep Dive
- Selenium for Antioxidant Defense
- Selenium for Cancer Prevention (Benefits Hub)
- Selenium for Immune Function
- Selenium and Thyroid Function
- Cancer (Oncology)
- Cancer Overview
- Glutathione
- Oxidative Stress
- Zinc
- Iodine
- Vitamin E
- Vitamin C
- Vitamin D
- Methionine
- Cysteine
- Type 2 Diabetes
- Selenium Lab Test
- Prostate Cancer — the primary endpoint of the SELECT trial and the cancer where selenium's U-shaped dose-response is best documented.
- Conditions on this site that reference this page: Head and Neck Cancer · Nasopharyngeal Cancer · Prostate Conditions
- Glutathione