Prostate Cancer
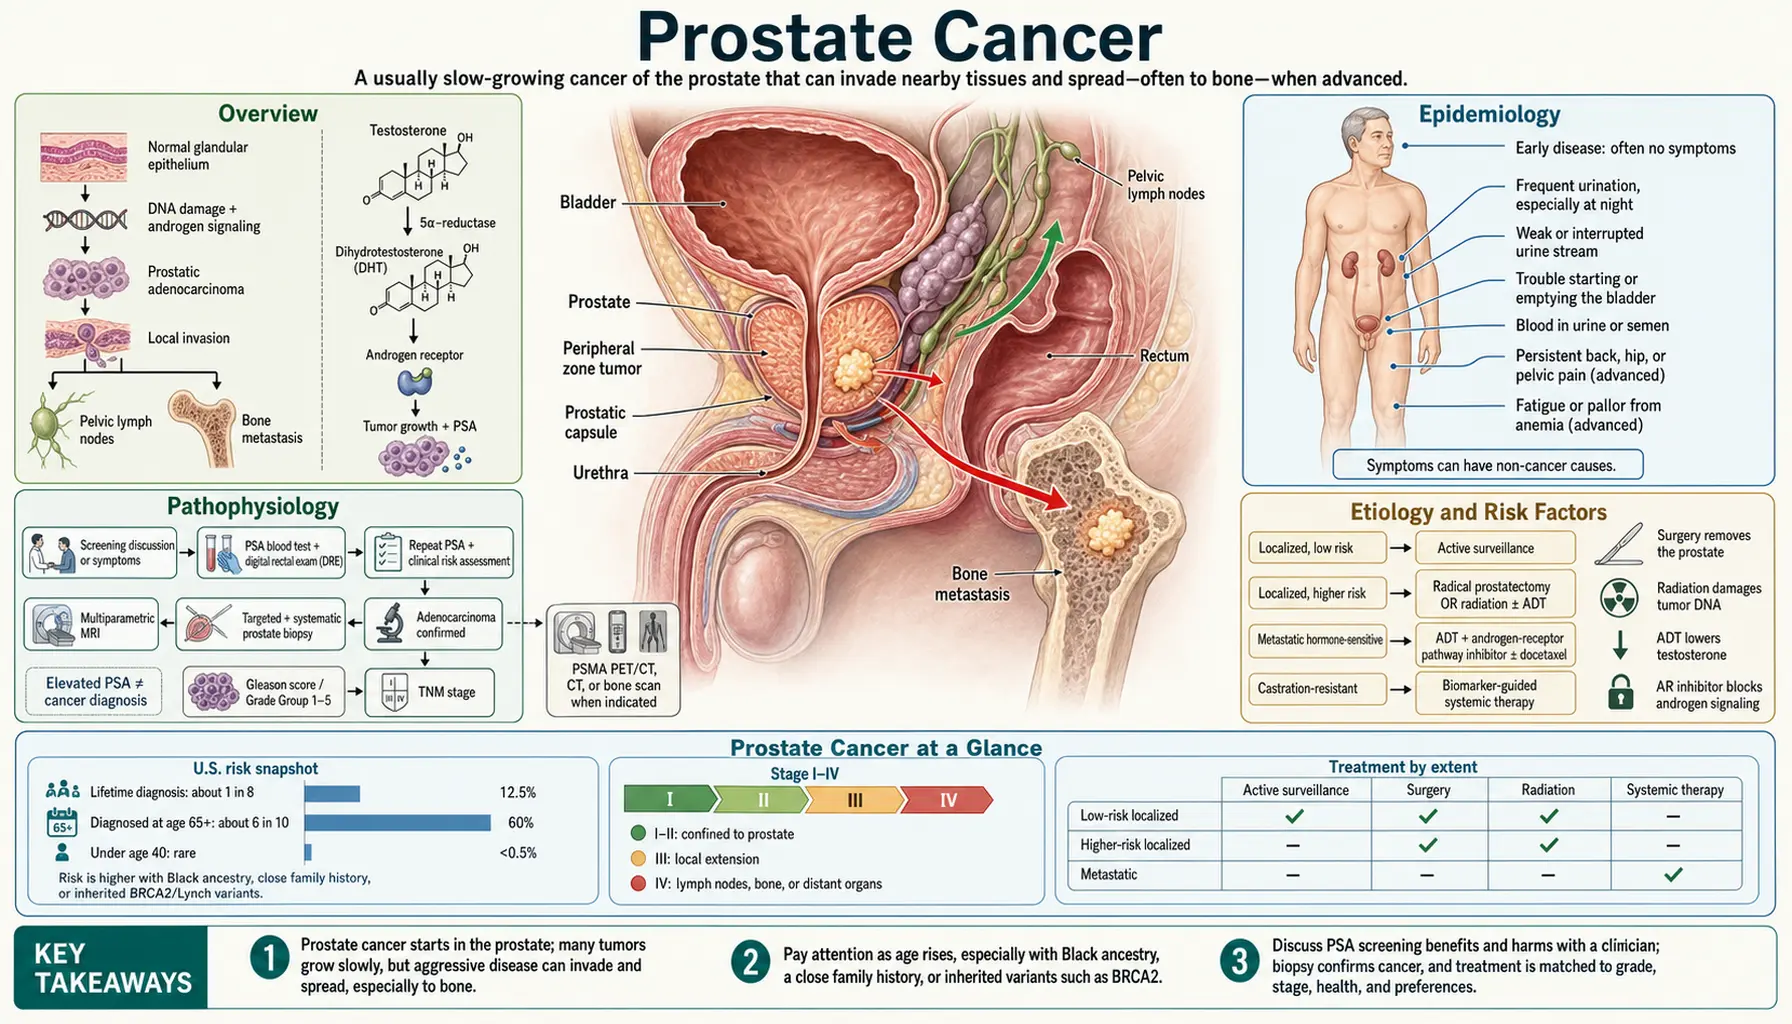
Table of Contents
1. Overview
Prostate cancer is a malignancy that arises in the prostate, a walnut-sized gland that sits just below the bladder and wraps around the urethra in men. The prostate makes part of the fluid that carries sperm. Most prostate cancers begin in the gland cells (these are called adenocarcinomas) and many of them grow remarkably slowly — so slowly that a great number of men who have prostate cancer will never feel sick from it and will ultimately die of something else entirely.
That last sentence is the single most important thing to understand about this disease, and it deserves to be said plainly: prostate cancer is the most commonly diagnosed cancer in American men, yet most men who have it die with it, not of it. A large share of tumors found through screening are small, low-grade, and biologically lazy. At the same time, a minority of prostate cancers are genuinely dangerous — aggressive, fast-spreading, and lethal. The entire modern approach to this disease is an effort to tell those two groups apart, so that men with harmless cancer are spared the side effects of treatment while men with dangerous cancer are caught and treated in time.
This page covers prostate cancer specifically. The closely related, non-cancerous conditions of the prostate — benign prostatic hyperplasia (BPH), prostatitis, and the broader prostate-specific antigen-screening debate at an overview level — are covered on our Prostate Conditions page. If you are here because of urinary symptoms (weak stream, frequency, getting up at night), it is worth knowing that those are far more often caused by benign enlargement than by cancer; that page covers them.
2. Epidemiology
In the United States, prostate cancer is the most frequently diagnosed solid tumor in men, with roughly 300,000 new cases each year and approximately 35,000 deaths. About 1 in 8 men will be diagnosed with prostate cancer at some point in life. It is overwhelmingly a disease of older age: the median age at diagnosis is in the late 60s, and it is uncommon before age 50. The American Cancer Society's 2025 prostate cancer report found that US incidence turned from falling 6.4% a year (2007–2014) to rising 3.0% a year (2014–2021); over the past decade of data, cancer that had already spread at diagnosis (distant-stage disease) rose 2.6% a year in men under 55, 6.0% a year at ages 55–69 and 6.2% a year at 70 and older.
The gap between how often the cancer is diagnosed and how often it kills tells the story. Autopsy studies of men who died of unrelated causes have repeatedly found microscopic prostate cancer in a striking fraction of older men — roughly a third of men in their 50s and the majority of men in their 80s harbor some cancer cells that never caused a problem. This reservoir of clinically silent disease is why screening can find so many cancers that would have been better left undiscovered, a phenomenon called overdiagnosis.
There are stark racial disparities. Black men in the United States are diagnosed about 1.7 times as often as white men and are roughly twice as likely to die from the disease (the 2025 report gives 67% higher incidence and double the death rate compared with White men). The reasons are not fully understood and almost certainly combine biology (some evidence for more aggressive tumor genetics and earlier onset) with unequal access to screening, timely diagnosis, and high-quality treatment. For Black men and men with a strong family history, most guidelines suggest starting the screening conversation earlier — around age 40–45 rather than 50–55.
3. Pathophysiology
Normal prostate tissue depends on androgens — male hormones, chiefly testosterone and its more potent product dihydrotestosterone (DHT) — to grow and function. Prostate cancer cells, especially early on, keep this dependence. They carry the androgen receptor and use androgen signaling as fuel. This single fact underlies the most important treatment in advanced disease: starve the cancer of androgens and it shrinks. It also explains why testosterone is so central to the whole story (see Low Testosterone & TRT).
Most prostate cancers begin in the peripheral (outer) zone of the gland — conveniently, the part a clinician's finger can reach on a digital rectal exam. Cancer cells make prostate-specific antigen (PSA), the protein measured in the blood test, and they tend to leak more of it into the circulation than healthy tissue does, which is why a rising prostate-specific antigen can signal a problem.
When prostate cancer does spread, it has a notable preference for bone, particularly the spine and pelvis. Bone metastases are the hallmark of advanced disease and the main source of its symptoms — pain, fractures, and sometimes spinal-cord compression. The next stop is typically the lymph nodes. Over time, in men treated with hormone therapy, the cancer can evolve to keep growing even when androgen levels are driven down to near zero — a state called castration-resistant prostate cancer (CRPC), discussed below.
4. Etiology and Risk Factors
The three risk factors that matter most are not lifestyle choices — they are things you cannot change:
- Age. Risk climbs steeply after 50. This is the dominant factor.
- Family history. Having a father or brother with prostate cancer roughly doubles your risk, and the risk rises further with multiple affected relatives or relatives diagnosed young. A family history of breast or ovarian cancer matters too, because of shared inherited mutations.
- Race/ancestry. Men of African ancestry carry the highest risk and the worst outcomes (see Epidemiology above).
Inherited gene mutations. A meaningful minority of aggressive prostate cancers trace to inherited DNA-repair mutations, most importantly BRCA2 (and to a lesser degree BRCA1). The same genes are famous for breast and ovarian cancer in women. A man who carries a BRCA2 mutation has a higher lifetime risk of prostate cancer and, crucially, a higher chance that his cancer will be aggressive and present at a younger age. This is no longer academic: BRCA2 status now changes screening advice and opens the door to specific drugs (PARP inhibitors) in advanced disease. Genetic counseling is the service that assesses this inherited risk for men with a strong family pattern of breast, ovarian, pancreatic, or prostate cancer.
Lifestyle and metabolic factors. The evidence here is softer. Obesity is consistently linked not so much to getting prostate cancer as to getting a more aggressive form and dying of it (see Obesity). Diets heavy in saturated animal fat and very high calcium intake have been associated with worse risk in some studies, though the data are mixed. One large chemoprevention trial (SELECT) tested two supplements — vitamin E and selenium — and neither prevented prostate cancer; the vitamin E arm raised the risk (see Prevention).
5. Clinical Presentation
Here is the uncomfortable truth: early, curable prostate cancer usually causes no symptoms at all. Because it starts in the outer part of the gland, away from the urethra, a small tumor does not block urine flow. This is exactly why screening exists — and exactly why screening is so fraught, since the cancers it finds are often the silent, slow ones.
The urinary symptoms that men worry about — a weak stream, hesitancy, frequency, dribbling, waking at night to urinate — are far more often caused by benign enlargement of the gland pressing on the urethra than by cancer. (See Benign Prostatic Hyperplasia.) Having these symptoms does not mean you have cancer; not having them does not mean you are in the clear.
When prostate cancer does cause symptoms, it usually means the disease is more advanced. Warning signs that warrant prompt evaluation include:
- Blood in the urine or semen (hematuria, hematospermia).
- New erectile dysfunction that is otherwise unexplained (see Erectile Dysfunction).
- Bone pain — especially persistent back, hip, or pelvic pain — which can signal metastatic spread to bone.
- Unintentional weight loss, fatigue, or leg swelling in advanced disease.
- Sudden leg weakness, numbness, or loss of bladder/bowel control — a medical emergency that can indicate spinal-cord compression from a spine metastasis.
6. Diagnosis
The PSA test and the screening debate
The prostate-specific antigen (PSA) blood test is the starting point. It is not a cancer test — it is a prostate test. Prostate-specific antigen rises with cancer but also with benign enlargement, infection, recent ejaculation, and even a vigorous bike ride. There is no single “normal” cutoff that cleanly separates cancer from no cancer; the higher the number, the higher the odds, but plenty of cancers occur at low prostate-specific antigen and plenty of high PSAs turn out to be benign. (For the test itself, see Prostate-Specific Antigen (PSA) Test.)
Two enormous trials defined the screening debate and reached famously different conclusions:
- The ERSPC (European Randomized Study of Screening for Prostate Cancer) found that prostate-specific antigen screening reduced prostate-cancer deaths. Its final report, after a median 23 years of follow-up of 162,236 men aged 55–69, found prostate-cancer deaths 13% lower in the screened group (rate ratio 0.87), an absolute reduction of 0.22%: one death was prevented for every 456 men invited to screening and for every 12 men diagnosed (628 and 18 at 16 years). The cost was substantial overdiagnosis: prostate cancer was diagnosed 30% more often in the screened group (rate ratio 1.30).
- The American PLCO trial found no mortality benefit from screening — though it was later recognized that the great majority of men in its “no-screening” comparison group had actually been getting prostate-specific antigen tests anyway, which muddied the result.
A 2026 Cochrane review of six randomized trials (789,086 men) drew mainly on ERSPC for its main estimates. It found that PSA screening likely lowers prostate-cancer deaths by about 2 per 1000 men (from 16 to 14 per 1000), may make little or no difference to deaths from all causes (rate ratio 0.99, low-certainty evidence), likely increases prostate cancer diagnoses by about 30%, and may reduce diagnoses of cancer that has already spread (metastatic disease, risk ratio 0.65, low-certainty evidence). The reviewers found too little evidence on harms such as biopsy and treatment complications.
The honest summary: prostate-specific antigen screening can prevent some prostate-cancer deaths, but it also leads many men to be diagnosed and treated for cancers that would never have harmed them — with real side effects. Because of this trade-off, modern guidelines (US Preventive Services Task Force and others) recommend shared decision-making for men roughly 55–69: the man and his clinician weigh the pros and cons and decide together, factoring in their own risk (age, race, family history, BRCA status) and how they personally weigh the risk of dying of prostate cancer against the risk of incontinence and erectile dysfunction from treatment. There is no universally right answer.
The modern MRI-first pathway
One of the biggest advances of the last decade has been putting multiparametric magnetic resonance imaging (MRI) of the prostate before the biopsy, rather than biopsying everyone with a high prostate-specific antigen blindly. A good-quality magnetic resonance imaging can show suspicious areas and, just as importantly, can be reassuring when it looks clean. The PROMIS study showed magnetic resonance imaging is far better than the old random biopsy at detecting clinically significant cancer, and the PRECISION trial showed that using magnetic resonance imaging to target the biopsy — and skipping biopsy in men with a normal magnetic resonance imaging — found more important cancers while detecting fewer of the trivial ones. When a biopsy is needed, the magnetic resonance imaging image is fused with live ultrasound so the needle goes precisely to the suspicious spot — a fusion biopsy.
Gleason score and Grade Groups, explained plainly
If a biopsy finds cancer, a pathologist grades how abnormal the cells look under the microscope — essentially, how much they have lost the orderly pattern of normal prostate tissue. The traditional Gleason score adds the two most common patterns in the sample (each scored 1–5), giving totals like 6, 7, 8, 9, or 10. Because a “6” sounds alarming but is actually the lowest grade now diagnosed, pathologists also report a simpler 1-to-5 Grade Group:
- Grade Group 1 (Gleason 6): low-grade, slow-growing — the kind most appropriate for monitoring.
- Grade Group 2 (Gleason 3+4=7): favorable intermediate.
- Grade Group 3 (Gleason 4+3=7): less favorable intermediate — the order matters; more “4” means more aggressive.
- Grade Group 4 (Gleason 8): high-grade.
- Grade Group 5 (Gleason 9–10): the most aggressive.
The grade, the prostate-specific antigen, and the clinical stage (how far the tumor has spread, by exam and imaging) are combined into a risk category — low, intermediate, or high risk — which drives every treatment decision below. For men with high-risk disease, modern PSMA-PET imaging (see Recent Research) has become the most accurate way to check for spread before committing to treatment.
7. Treatment
There is rarely one “correct” treatment for prostate cancer. There are options, each with a different balance of cancer control and side effects, and the right choice depends on the cancer's risk category, the man's age and other health problems, and his own priorities. The authors of the 15-year ProtecT report concluded that the choice of therapy involves weighing trade-offs between the benefits and harms of each treatment.
Active surveillance — choosing not to treat (yet)
For low-risk disease (Grade Group 1), a common option is active surveillance: no immediate treatment, but careful monitoring with periodic prostate-specific antigen tests, magnetic resonance imaging, and repeat biopsies, with the plan to treat only if the cancer shows signs of becoming more aggressive. This is not “doing nothing” it is actively watching, and it spares men the side effects of surgery and radiation for a cancer that may never threaten them.
The landmark ProtecT trial randomized 1,643 UK men with localized prostate cancer found by PSA testing to active monitoring, surgery, or radiotherapy and followed them for a median of 15 years (range 11 to 21). The result was striking: prostate-cancer deaths were very low (2.7% overall — 3.1% with monitoring, 2.2% after surgery, 2.9% after radiotherapy) and statistically the same in all three groups; deaths from any cause (21.7%) were also similar. Surgery and radiation did reduce the chance of the cancer spreading or progressing, but they did not save more lives over 15 years — while they did cause more incontinence and sexual side effects. In plain numbers: cancer spread to other organs (metastases) in 9.4% of the monitored men, against 4.7% after surgery and 5.0% after radiotherapy; long-term hormone therapy was started in 12.7%, 7.2% and 7.7%; and 24.4% of the monitored men were alive at the end without ever having had prostate cancer treatment. More than one third of the men in the trial had intermediate- or high-risk disease at diagnosis, and the trial found no difference in cancer deaths by PSA level, stage, grade or risk score. For many men with low- and favorable-intermediate-risk disease, monitoring is a safe, evidence-backed choice. The older PIVOT trial similarly found that surgery did not reduce overall or prostate-cancer mortality versus observation in men with mostly low-risk, screen-detected disease.
Surgery and radiation — the side-effect trade-offs, candidly
For men who need or choose treatment for localized cancer, the two main curative options are radical prostatectomy (surgical removal of the prostate, now usually robot-assisted) and radiation therapy (external-beam radiation or implanted seeds, called brachytherapy). Both can cure localized cancer at similar rates. They differ mainly in their side effects, and men deserve honest numbers:
- Urinary incontinence is more common and more immediate after surgery. Many men leak in the first months and improve over a year, but a meaningful minority have lasting leakage that needs pads.
- Erectile dysfunction is common after both, because the nerves that control erection run alongside the prostate. Surgery tends to cause an immediate drop in function (sometimes partly recovering over 1–2 years if nerves are spared); radiation tends to cause a more gradual decline over the following years.
- Bowel and rectal symptoms (urgency, irritation, occasional bleeding) are more associated with radiation.
The large PROST-QA quality-of-life study documented these patterns in detail and is the reason clinicians can now counsel men with real expectations rather than vague reassurance. The bottom line: there is no side-effect-free curative treatment, the trade-offs differ by modality, and matching the choice to what a man cares about most is the whole point.
Hormone therapy (ADT) and newer agents
Because prostate cancer feeds on androgens, lowering them is a cornerstone of treatment for high-risk, recurrent, and advanced disease. Androgen deprivation therapy (ADT) — usually injections that shut down testosterone production, sometimes combined with radiation — can dramatically shrink the cancer. The cost is a set of predictable side effects from low testosterone: hot flashes, loss of libido and erections, fatigue, muscle loss, weight gain, bone thinning, and metabolic changes.
For more advanced disease, ADT is now routinely combined with one of a class of powerful androgen-pathway drugs that block androgen signaling more completely than ADT alone:
- Abiraterone blocks androgen production not just in the testes but in the adrenal glands and the tumor itself; the COU-AA-302 trial showed it extends survival in metastatic disease.
- Enzalutamide directly blocks the androgen receptor; the PREVAIL trial showed it extends survival and delays progression.
- Adding chemotherapy (docetaxel) to ADT up front, as in the CHAARTED trial, also extends survival in men with metastatic hormone-sensitive disease.
Metastatic and castration-resistant disease
When prostate cancer keeps growing despite ADT driving testosterone down to castration levels, it is called metastatic castration-resistant prostate cancer (mCRPC). This is the hardest stage, but the toolkit has expanded substantially — the newer androgen-pathway drugs above, chemotherapy, bone-targeted agents, and two of the most important recent advances:
- PSMA-targeted radioligand therapy. Prostate cancer cells carry a surface protein called PSMA (prostate-specific membrane antigen). A radioactive drug, lutetium-177–PSMA-617, homes in on PSMA and delivers radiation directly to cancer cells wherever they are. The VISION trial showed it extends survival in men with mCRPC after other treatments — a genuinely new kind of therapy.
- PARP inhibitors for DNA-repair-deficient cancers. Men whose tumors carry mutations in BRCA2 and similar repair genes can benefit from drugs like olaparib; the PROfound trial showed it slows progression in these selected men — a clear example of why genetic testing now matters for treatment, not just for screening.
8. Complications
Complications come from two sources: the cancer itself and the treatments. It is worth being honest that, for many men, the treatment side effects are the dominant burden — which is exactly why the option to monitor low-risk disease matters so much.
- Treatment-related: urinary incontinence, erectile dysfunction, bowel/rectal irritation, and the wide-ranging effects of long-term ADT (bone loss and fractures, hot flashes, fatigue, muscle wasting, weight gain, and a higher risk of cardiovascular and metabolic problems).
- Disease-related (advanced cancer): bone pain and pathological fractures from bone metastases; spinal-cord compression (an emergency); urinary obstruction or kidney problems if the tumor blocks the urethra or ureters; anemia and weight loss; and lymphedema (leg swelling) from involved pelvic lymph nodes.
Many of these are manageable. Bone health during ADT can be protected with bone-density monitoring, exercise, and bone-strengthening drugs; erectile dysfunction has treatment options; incontinence often improves with pelvic-floor rehabilitation and, when needed, surgery.
9. Prognosis
For most men, the outlook for prostate cancer is excellent — better than for almost any other common cancer. But the average hides an enormous spread, and the honest numbers depend entirely on how far the cancer has spread at diagnosis:
- Localized or regional disease (confined to the prostate or nearby): 5-year relative survival is essentially ~100%. These men, as a group, do not die of prostate cancer over that horizon.
- Distant (metastatic) disease at diagnosis: 5-year relative survival drops to roughly 37%. For comparison, the American Cancer Society's Cancer statistics, 2026 reports that 5-year relative survival for all distant-stage (metastatic) cancers combined reached 35% for diagnoses in 2015–2021, up from 17% in the mid-1990s. This is the dangerous end of the disease and the reason early detection of the aggressive cancers matters.
So both things are true at once: prostate cancer is usually survivable, and prostate cancer still kills tens of thousands of American men a year. The challenge has never been treating the disease — it has been figuring out which cancers are the dangerous ones. Tools like grade group, PSMA-PET imaging, and genetic testing exist precisely to sharpen that distinction so that aggressive cancers are caught early and indolent ones are left alone.
10. Prevention
There is no proven way to prevent prostate cancer, and a few widely marketed strategies have been tested and failed. Honesty here matters more than hope.
What failed: The large SELECT trial — one trial with four groups (selenium, vitamin E, both, or placebo) in 35,533 men — tested vitamin E and selenium supplements to prevent prostate cancer. It did not work — and worse, longer follow-up found that vitamin E supplementation actually increased the risk of prostate cancer (620 cases with vitamin E against 529 with placebo; hazard ratio 1.17), while selenium's small rise (hazard ratio 1.09) was not statistically significant. This is a clear, well-documented example of a popular supplement doing harm, and it is the reason no reputable guideline recommends vitamin E or selenium pills to prevent prostate cancer.
What may help (with honest caveats):
- Diet. Diets rich in vegetables and fruit — including tomatoes and tomato products, which contain lycopene — are associated with lower risk in observational studies, though the evidence is suggestive rather than proven. Foods like pomegranate and green tea are popular for the same reason; the evidence for them is as part of the diet, not as medicine. Diets heavy in saturated animal fat are the pattern some studies link to higher risk, though the data are mixed (see Etiology above).
- Exercise and weight. Regular physical activity and avoiding obesity are linked to a lower risk of aggressive, lethal prostate cancer specifically — one of the more consistent findings. (See Obesity.)
- Vitamin D. Low vitamin D status has been associated with worse prostate-cancer outcomes in some studies, though supplements have not been proven to prevent the disease; vitamin D's wider roles are covered on the Vitamin D3 page (see Vitamin D3).
The most evidence-backed “prevention” for the men at highest risk is not a pill at all — it is informed early detection through shared decision-making about prostate-specific antigen screening, so that the dangerous cancers are caught while they are still curable.
11. Recent Research and Advances
Prostate-cancer care has changed faster in the last decade than in the prior thirty years. The most consequential advances:
- Magnetic resonance imaging-first diagnosis. Putting multiparametric magnetic resonance imaging before biopsy (PROMIS, PRECISION) finds more dangerous cancers, fewer trivial ones, and lets some men safely skip biopsy altogether — reducing overdiagnosis at the front door.
- PSMA-PET imaging. Scanning with a tracer that binds PSMA is far more accurate than conventional computed tomography (CT) and bone scans at finding where prostate cancer has spread. The proPSMA trial showed it changes management in a large share of high-risk men before they commit to surgery or radiation.
- Lutetium-177–PSMA radioligand therapy. The same PSMA target is now used to treat: a radioactive drug delivers radiation directly to cancer cells throughout the body (VISION trial), extending survival in advanced, treatment-resistant disease.
- Genomics-guided treatment. Testing tumors (and inherited DNA) for repair-gene mutations like BRCA2 now selects men for PARP inhibitors such as olaparib (PROfound), and mismatch-repair-deficient tumors may respond to immunotherapy. Prostate cancer has firmly entered the era of precision medicine.
- Treatment intensification up front. Combining ADT with abiraterone, enzalutamide, or docetaxel early in metastatic disease — rather than saving drugs for later — has meaningfully extended survival.
Key Research Papers
Historical Background
The modern understanding of prostate cancer rests on a single Nobel-winning insight. In 1941, Charles Huggins and Clarence Hodges at the University of Chicago showed that lowering androgens — by surgical castration or estrogen — caused advanced prostate cancer to regress, the first demonstration that a cancer could be controlled by manipulating hormones. Huggins received the Nobel Prize in 1966, and androgen deprivation remains a cornerstone of treatment today. The introduction of the prostate-specific antigen blood test in the late 1980s transformed the disease into one that could be screened for and detected years before symptoms — a double-edged advance that created the overdiagnosis problem we still grapple with. The robotic-surgery era of the 2000s, and the genomics and PSMA-imaging revolution of the 2010s, complete the arc from Huggins's hormonal insight to today's precision care.
- Hamdy FC, Donovan JL, Lane JA, et al. 10-Year Outcomes after Monitoring, Surgery, or Radiotherapy for Localized Prostate Cancer. New England Journal of Medicine. 2016;375(15):1415-1424. — doi:10.1056/NEJMoa1606220
- Hamdy FC, Donovan JL, Lane JA, et al. Fifteen-Year Outcomes after Monitoring, Surgery, or Radiotherapy for Prostate Cancer. New England Journal of Medicine. 2023;388(17):1547-1558. — doi:10.1056/NEJMoa2214122
- Wilt TJ, Brawer MK, Jones KM, et al. Radical Prostatectomy versus Observation for Localized Prostate Cancer. New England Journal of Medicine. 2012;367(3):203-213. — doi:10.1056/NEJMoa1113162
- Schröder FH, Hugosson J, Roobol MJ, et al. Screening and Prostate-Cancer Mortality in a Randomized European Study. New England Journal of Medicine. 2009;360(13):1320-1328. — doi:10.1056/NEJMoa0810084
- Andriole GL, Crawford ED, Grubb RL, et al. Mortality Results from a Randomized Prostate-Cancer Screening Trial. New England Journal of Medicine. 2009;360(13):1310-1319. — doi:10.1056/NEJMoa0810696
- Schröder FH, Hugosson J, Roobol MJ, et al. Prostate-Cancer Mortality at 11 Years of Follow-up. New England Journal of Medicine. 2012;366(11):981-990. — doi:10.1056/NEJMoa1113135
- Roobol MJ, de Vos II, Månsson M, et al. European Study of Prostate Cancer Screening — 23-Year Follow-up. New England Journal of Medicine. 2025;393(17):1669-1680. — doi:10.1056/NEJMoa2503223
- Franco JV, Hwang EC, Jung JH, Vaimberg O, Ilic D, Cleves A, Dahm P. Prostate-specific antigen (PSA) test for prostate cancer screening. Cochrane Database of Systematic Reviews. 2026;5(5):CD004720. — doi:10.1002/14651858.CD004720.pub4
- Ahmed HU, El-Shater Bosaily A, Brown LC, et al. Diagnostic accuracy of multi-parametric MRI and TRUS biopsy in prostate cancer (PROMIS): a paired validating confirmatory study. The Lancet. 2017;389(10071):815-822. — doi:10.1016/S0140-6736(16)32401-1
- Kasivisvanathan V, Rannikko AS, Borghi M, et al. MRI-Targeted or Standard Biopsy for Prostate-Cancer Diagnosis. New England Journal of Medicine. 2018;378(19):1767-1777. — doi:10.1056/NEJMoa1801993
- Hofman MS, Lawrentschuk N, Francis RJ, et al. Prostate-specific membrane antigen PET-CT in patients with high-risk prostate cancer before curative-intent surgery or radiotherapy (proPSMA). The Lancet. 2020;395(10231):1208-1216. — doi:10.1016/S0140-6736(20)30314-7
- Sartor O, de Bono J, Chi KN, et al. Lutetium-177–PSMA-617 for Metastatic Castration-Resistant Prostate Cancer. New England Journal of Medicine. 2021;385(12):1091-1103. — doi:10.1056/NEJMoa2107322
- Ryan CJ, Smith MR, de Bono JS, et al. Abiraterone in Metastatic Prostate Cancer without Previous Chemotherapy. New England Journal of Medicine. 2013;368(2):138-148. — doi:10.1056/NEJMoa1209096
- Beer TM, Armstrong AJ, Rathkopf DE, et al. Enzalutamide in Metastatic Prostate Cancer before Chemotherapy. New England Journal of Medicine. 2014;371(5):424-433. — doi:10.1056/NEJMoa1405095
- Sanda MG, Dunn RL, Michalski J, et al. Quality of Life and Satisfaction with Outcome among Prostate-Cancer Survivors. New England Journal of Medicine. 2008;358(12):1250-1261. — doi:10.1056/NEJMoa074311
- Lippman SM, Klein EA, Goodman PJ, et al. Effect of Selenium and Vitamin E on Risk of Prostate Cancer and Other Cancers (SELECT). JAMA. 2009;301(1):39-51. — doi:10.1001/jama.2008.864
- Klein EA, Thompson IM, Tangen CM, et al. Vitamin E and the Risk of Prostate Cancer (SELECT follow-up). JAMA. 2011;306(14):1549-1556. — doi:10.1001/jama.2011.1437
- Kratzer TB, Mazzitelli N, Star J, Dahut WL, Jemal A, Siegel RL. Prostate cancer statistics, 2025. CA: A Cancer Journal for Clinicians. 2025;75(6):485-497. — doi:10.3322/caac.70028
- Siegel RL, Kratzer TB, Wagle NS, Sung H, Jemal A. Cancer statistics, 2026. CA: A Cancer Journal for Clinicians. 2026;76(1):e70043. — doi:10.3322/caac.70043
PubMed Topic Searches
Prostate-cancer research moves quickly. The links below run live searches on PubMed, the U.S. National Library of Medicine's database of biomedical literature, so they always return the newest peer-reviewed studies on each topic. Open any link to see current results.
- PubMed: Prostate cancer: active surveillance
- PubMed: PSA screening and prostate-cancer mortality
- PubMed: Multiparametric MRI and prostate biopsy
- PubMed: Gleason score and Grade Groups
- PubMed: PSMA-PET imaging in prostate cancer
- PubMed: Lutetium-177–PSMA radioligand therapy
- PubMed: Castration-resistant prostate cancer treatment
- PubMed: BRCA2 mutations and PARP inhibitors
- PubMed: Androgen-deprivation therapy side effects
- PubMed: Prostatectomy: erectile dysfunction and incontinence
- PubMed: Racial disparities in prostate cancer
- PubMed: Diet, lycopene, and prostate-cancer prevention
Connections
- Oncology
- How Cancer Spreads (Metastasis) — interactive animation
- Cancer — Overview
- Metastatic Cancers
- Prostate Conditions (Benign Prostatic Hyperplasia, Prostatitis, Prostate-Specific Antigen)
- Benign Prostatic Hyperplasia
- Low Testosterone & TRT
- Erectile Dysfunction
- Urinary Tract Infections
- Bladder Cancer
- Obesity
- Prostate-Specific Antigen Test
- Vitamin D3
- Pomegranate
- Green Tea
- Prostate Conditions: History and Discovery
- Selenium and Cancer Prevention — why the NPC trial's 63% risk reduction did not survive SELECT, and when selenium raises high-grade risk.
- Benign Prostatic Hyperplasia: History and Discovery — how medicine learned to tell benign enlargement apart from prostate cancer.