⚠ Evidence warning: Clinical trials or other evidence do not support the claims that saw palmetto, selenium, green tea and vitamin D treat prostate enlargement or protect against prostate cancer. This page keeps it as a report of what people, websites or other media say.
Prostate Conditions
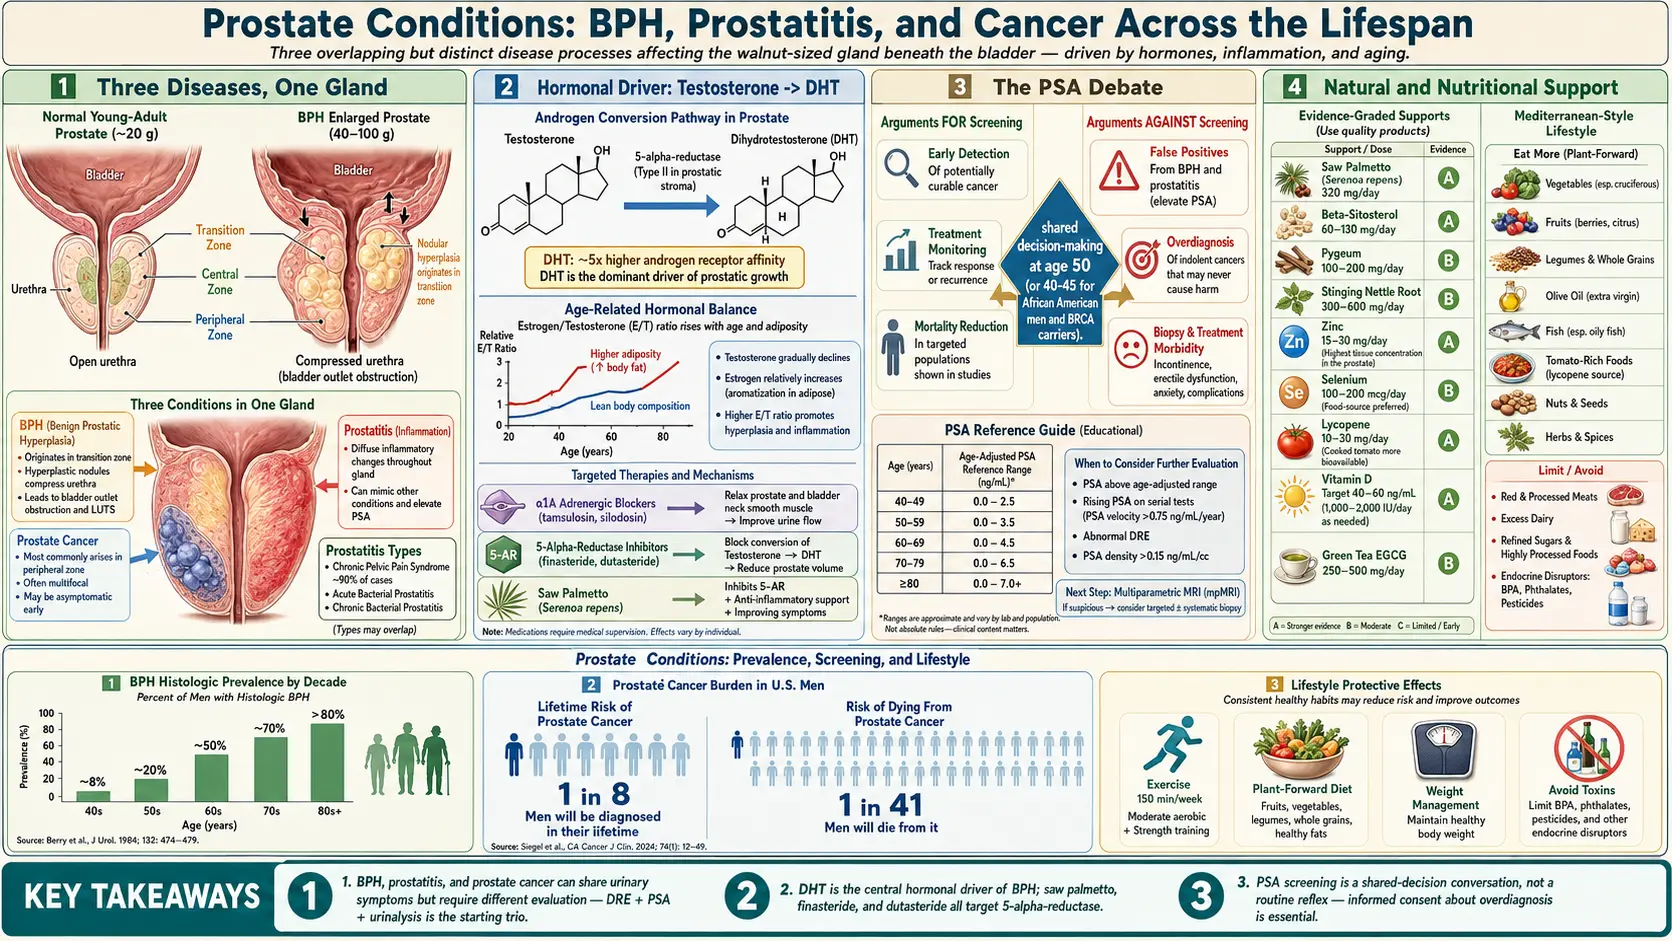
Table of Contents
- Overview of the Prostate
- Benign Prostatic Hyperplasia (BPH)
- Prostatitis
- Prostate Cancer Screening and the Prostate-Specific Antigen Debate
- Risk Factors
- Common Symptoms
- Conventional Treatments
- Natural Support for Prostate Health
- Diet and Lifestyle Modifications
- Pelvic Floor Health
- Cautions and Signs Hospitals Treat as Urgent
- Key Research Papers
- Connections
- Featured Videos
Overview of the Prostate
The prostate gland is a walnut-sized organ located below the bladder and surrounding the urethra in men. It produces seminal fluid that nourishes and transports sperm. As men age, the prostate is susceptible to several conditions that can significantly impact urinary function and quality of life. From a naturopathic perspective, prostate health is deeply connected to hormonal balance, nutritional status, and overall metabolic wellness.
Benign Prostatic Hyperplasia (BPH)
Benign prostatic hyperplasia is a non-cancerous enlargement of the prostate gland that affects the majority of men as they age. By age 60, roughly half of all men have some degree of benign prostatic hyperplasia, and by age 85, approximately 90% are affected.
How Benign Prostatic Hyperplasia Develops
Benign prostatic hyperplasia is driven primarily by the conversion of testosterone to dihydrotestosterone (DHT) by the enzyme 5-alpha reductase. DHT stimulates prostate cell growth. Estrogen levels also rise relative to testosterone with aging, which may further promote prostate tissue proliferation. Chronic low-grade inflammation is increasingly recognized as a contributing factor.
Symptoms of Benign Prostatic Hyperplasia
- Frequent urination, especially at night (nocturia)
- Weak or interrupted urine stream
- Difficulty initiating urination (hesitancy)
- Sensation of incomplete bladder emptying
- Urgency and occasional urge incontinence
- Dribbling at the end of urination
Prostatitis
Prostatitis refers to inflammation of the prostate gland and is the most common urological diagnosis in men under 50. It can be acute or chronic, bacterial or non-bacterial.
Types of Prostatitis
- Acute bacterial prostatitis: Sudden onset with fever, chills, painful urination, and pelvic pain. Requires prompt antibiotic treatment.
- Chronic bacterial prostatitis: Recurring bacterial infections with milder but persistent symptoms.
- Chronic pelvic pain syndrome (CPPS): The most common form, accounting for roughly 90% of cases. No identifiable bacterial cause but involves chronic pelvic pain, urinary symptoms, and sometimes sexual dysfunction.
- Asymptomatic inflammatory prostatitis: Inflammation found incidentally during evaluation for other conditions.
Naturopathic practitioners often address CPPS through a combination of anti-inflammatory nutrition, stress management, pelvic floor rehabilitation, and targeted supplementation.
Prostate Cancer Screening and the Prostate-Specific Antigen Debate
The prostate-specific antigen (PSA) test has been a cornerstone of prostate cancer screening since the late 1980s, but it remains one of the most debated topics in men's health.
Arguments for Prostate-Specific Antigen Screening
- Can detect prostate cancer at an early, potentially curable stage
- Useful for monitoring men already diagnosed with prostate cancer
- May reduce prostate cancer mortality when used in targeted populations
Arguments Against Routine Prostate-Specific Antigen Screening
- High false-positive rate: prostate-specific antigen can be elevated due to benign prostatic hyperplasia, prostatitis, recent ejaculation, or cycling
- Overdiagnosis: Many prostate cancers are slow-growing and may never cause symptoms or death
- Overtreatment risks: Unnecessary biopsies, surgeries, and radiation carry significant side effects including incontinence and erectile dysfunction
The 2023 American Urological Association and Society of Urologic Oncology guideline recommends prostate-specific antigen screening combined with shared decision-making, in which the benefits are weighed against the false positives, overdiagnosis and overtreatment listed above. It states that clinicians “may begin prostate cancer screening and offer a baseline PSA test to people between ages 45 to 50 years”, that screening beginning at age 40 to 45 is offered to people at increased risk (“Black ancestry, germline mutations, strong family history of prostate cancer”), and that regular screening every 2 to 4 years is offered to people aged 50 to 69.
What the Long-Term Trials Report
- European screening trial, 23-year results (2025): among 162,236 men aged 55 to 69, prostate cancer deaths were 13% lower in the group offered repeated prostate-specific antigen tests. One death was prevented for every 456 men invited and for every 12 men diagnosed; diagnoses rose by 30%.
- Single invitation in England and Wales, 15-year results (2024): of 415,357 eligible men, 0.69% of invited men and 0.78% of the others died of prostate cancer, which the authors call a small absolute reduction. Invitation increased detection of low-grade and localized cancers but not of intermediate-grade, high-grade or advanced tumors.
- ProtecT trial, 15-year results (2023): among 1,643 men with localized prostate cancer, death from prostate cancer was low whichever path was assigned: 3.1% with active monitoring, 2.2% with surgery, 2.9% with radiotherapy. Metastases were more common with monitoring (9.4% against 4.7% and 5.0%).
Risk Factors
- Age: The single greatest risk factor for all prostate conditions
- Family history: Having a first-degree relative with prostate cancer doubles the risk
- Ethnicity: African American men have higher rates of prostate cancer and benign prostatic hyperplasia
- Hormonal imbalances: Elevated DHT and estrogen-to-testosterone ratio
- Obesity: Associated with more aggressive prostate disease and higher estrogen levels
- Sedentary lifestyle: Contributes to pelvic congestion and metabolic dysfunction
- Chronic inflammation: Poor diet, environmental toxins, and chronic stress all promote systemic inflammation
- Exposure to endocrine disruptors: BPA, phthalates, and pesticides may affect prostate health
Common Symptoms
While specific symptoms vary by condition, the following are general warning signs that warrant evaluation:
- Changes in urinary frequency or urgency
- Pain or burning during urination
- Blood in urine or semen
- Pelvic, lower back, or perineal pain
- Painful ejaculation
- Erectile dysfunction
- Unexplained weight loss (potential cancer sign)
Conventional Treatments
For Benign Prostatic Hyperplasia
- Alpha-blockers (tamsulosin, alfuzosin): Relax smooth muscle in the prostate and bladder neck
- 5-alpha reductase inhibitors (finasteride, dutasteride): Block DHT production to shrink the prostate
- Combination therapy: Alpha-blocker plus 5-alpha reductase inhibitor for moderate to severe benign prostatic hyperplasia
- Minimally invasive procedures: prostatic urethral lift, water vapor thermal therapy, transurethral microwave thermotherapy
- Surgery: Transurethral resection of the prostate (TURP) for severe cases
For Prostatitis
- Antibiotics: For bacterial forms (fluoroquinolones, trimethoprim-sulfamethoxazole)
- Alpha-blockers: To relieve urinary symptoms
- Anti-inflammatories: nonsteroidal anti-inflammatory drugs (NSAIDs) for pain management
- Physical therapy: Pelvic floor myofascial release for CPPS
Natural Support for Prostate Health
From a naturopathic perspective, several evidence-based natural therapies can support prostate health, either as primary approaches for mild conditions or as complementary support alongside conventional care.
Saw Palmetto (Serenoa repens)
Saw palmetto is the most well-researched herbal remedy for benign prostatic hyperplasia. It works as a mild 5-alpha reductase inhibitor, reducing DHT levels in prostate tissue. It also has anti-inflammatory and anti-estrogenic properties. Naturopathic practitioners report that it can improve urinary symptoms and flow rates in men with mild to moderate benign prostatic hyperplasia. The usual dose described is 320 mg daily of a standardized liposterolic extract, the standard dose named in the trials.
The 2023 Cochrane review (27 trials, 4,656 men) found that saw palmetto “results in little to no difference in urologic symptoms” at 3 to 6 months (0.90 points lower on the 0-to-35 symptom score than placebo) and at 12 to 17 months (0.07 points higher), rated high-certainty evidence. The CAMUS trial (369 men, 72 weeks, doses rising to 3 times the standard dose) found it was no more effective than placebo on symptoms or on any secondary measure, including peak urine flow. What is not known: the Cochrane authors state there is more uncertainty about saw palmetto combined with other herbs, and they found no data on long-term adverse events.
Beta-Sitosterol
Beta-sitosterol is a plant sterol found in many fruits, vegetables, nuts, and seeds. Multiple randomized controlled trials have shown it significantly improves urinary symptom scores and flow measures in men with benign prostatic hyperplasia. It works through anti-inflammatory mechanisms and may also inhibit 5-alpha reductase.
Pygeum (Prunus africana)
Pygeum bark extract has been used in European medicine for decades to treat benign prostatic hyperplasia symptoms. It reduces inflammation, inhibits growth factors that promote prostate cell proliferation, and may improve bladder contractility. Standard dosage is 100-200 mg daily.
Stinging Nettle Root (Urtica dioica)
Stinging nettle root is often combined with saw palmetto for synergistic effects. It appears to inhibit the binding of DHT to sex hormone-binding globulin (SHBG) and may have anti-aromatase activity. It also contains anti-inflammatory lignans.
Zinc
The prostate gland contains the highest concentration of zinc of any organ in the body. Zinc levels are significantly reduced in both benign prostatic hyperplasia and prostate cancer tissue. Naturopathic practitioners describe an intake of 15-30 mg daily as supporting normal prostate cell function and possibly helping regulate DHT metabolism. Zinc supplementation above 40 mg daily can impair copper absorption. Among 46,974 men followed for 14 years, supplemental zinc up to 100 mg/day was not associated with prostate cancer risk, while more than 100 mg/day was linked to about 2.29 times the risk of advanced prostate cancer; the authors could not rule out confounding.
Selenium
Selenium is an essential trace mineral with antioxidant properties. Some observational studies have linked adequate selenium status with reduced prostate cancer risk, though supplementation trials have shown mixed results. The largest, SELECT (35,533 men, 200 mcg selenium a day), reported hazard ratios for prostate cancer of 1.04 for selenium and 1.13 for vitamin E against placebo, and concluded that they “did not prevent prostate cancer” in relatively healthy men. Practitioners often favor food sources such as Brazil nuts, sardines, and organ meats over high-dose supplements.
Lycopene
Lycopene, the red pigment found in tomatoes, watermelon, and pink grapefruit, is a potent antioxidant that concentrates in prostate tissue. Epidemiological studies consistently associate higher lycopene intake with reduced prostate cancer risk. Cooked tomato products provide more bioavailable lycopene than raw tomatoes.
Vitamin D
Vitamin D receptors are present throughout prostate tissue, and vitamin D plays a role in regulating cell growth and differentiation. Low vitamin D levels have been associated with increased risk of aggressive prostate cancer. Naturopathic practitioners describe 40-60 ng/mL as the optimal vitamin D status, reached through sun exposure, diet, and supplementation.
Green Tea and Epigallocatechin Gallate
Epigallocatechin gallate (EGCG), the primary catechin in green tea, has demonstrated anti-proliferative and pro-apoptotic effects on prostate cancer cells in laboratory studies. Population studies from Asia show lower prostate cancer incidence among regular green tea drinkers. Drinking 3-5 cups daily or taking a standardized epigallocatechin gallate supplement is described as possibly protective. A 2020 United States Pharmacopeia review reports case reports linking liver injury to green tea extract at 140 mg to about 1,000 mg/day of epigallocatechin gallate, with wide differences between people, and the label warning in its green tea extract standard reads “Do not take on an empty stomach. Take with food. Do not use if you have a liver problem”. It names abdominal pain, dark urine and jaundice as symptoms of liver trouble.
Diet and Lifestyle Modifications
Mediterranean Diet
A Mediterranean-style diet rich in vegetables, fruits, whole grains, olive oil, fish, and legumes provides a foundation for prostate health. This dietary pattern is anti-inflammatory, rich in antioxidants, and associated with lower rates of prostate cancer and benign prostatic hyperplasia progression.
- Cruciferous vegetables (broccoli, cauliflower, kale): Contain sulforaphane and indole-3-carbinol, which support healthy estrogen metabolism
- Fatty fish (salmon, sardines, mackerel): Provide omega-3 fatty acids that reduce inflammation
- Pumpkin seeds: Rich in zinc and phytosterols that support prostate health
- Fermented foods: Support gut health, which influences hormonal balance and inflammation
Foods and Substances Linked to Worse Prostate Outcomes
- Red and processed meats: Associated with increased prostate cancer risk
- Dairy products: High calcium intake from dairy may be linked to elevated prostate cancer risk
- Refined sugars and processed foods: Promote inflammation and insulin resistance
- Excessive alcohol: Disrupts hormonal balance and liver detoxification
- Caffeine: Can worsen urinary symptoms in men with benign prostatic hyperplasia
Exercise
Regular physical activity is strongly associated with better prostate outcomes. The figure usually given is at least 150 minutes of moderate aerobic exercise per week. Resistance training can help maintain healthy testosterone levels. Exercise also reduces obesity, insulin resistance, and chronic inflammation, all of which are risk factors for prostate disease.
BPA and Endocrine Disruptors
Bisphenol A (BPA) and other endocrine-disrupting chemicals can mimic estrogen and interfere with hormonal signaling in the prostate. Common sources, and what lowers exposure:
- Plastic food containers, especially when food is heated in them
- Canned goods with BPA linings; BPA-free cans, glass and stainless steel containers are the alternatives
- Contaminants in drinking water, which filters reduce
- Pesticides on produce, which organic produce reduces
- Personal care products containing parabens and phthalates
Pelvic Floor Health
The pelvic floor muscles play a critical but often overlooked role in prostate-related symptoms, particularly in chronic pelvic pain syndrome and post-surgical recovery.
- Kegel exercises: Strengthening the pelvic floor muscles can improve urinary control, especially after prostate surgery
- Pelvic floor relaxation: For men with CPPS, the pelvic floor is often hypertonic (too tight). Relaxation techniques, diaphragmatic breathing, and stretching are more appropriate than strengthening
- Myofascial release therapy: Internal and external trigger point therapy performed by a trained pelvic floor physical therapist can significantly reduce pain in CPPS
- Stress management: Chronic stress contributes to pelvic floor tension. Practices such as yoga, meditation, and mindfulness can help break the pain-tension cycle
Cautions and Signs Hospitals Treat as Urgent
While natural approaches can be valuable for supporting prostate health, certain situations require prompt medical attention:
- Acute urinary retention (complete inability to urinate) is a medical emergency
- Blood in urine or semen is a sign doctors investigate to rule out serious conditions
- Fever with urinary symptoms may indicate acute bacterial prostatitis or urinary tract infection requiring antibiotics
- Rapidly worsening symptoms or unexplained weight loss are signs doctors investigate thoroughly
- Herbal supplements such as saw palmetto may interact with blood thinners and hormonal medications
- Suspected prostate cancer: natural remedies alone are not an established treatment for it. Integrative approaches are described as complementing, not replacing, oncological care
- Prostate-specific antigen testing: Some supplements are reported to lower prostate-specific antigen levels, potentially masking disease. For saw palmetto, the CAMUS analysis found it “does not affect serum prostate specific antigen more than placebo, even at relatively high doses” (change of 0.23 against 0.16 ng/ml, p = 0.50)
A collaborative approach between naturopathic and conventional providers offers the most comprehensive care for prostate health.
Key Research Papers
- Schroder FH, Hugosson J, Roobol MJ, et al. Prostate-cancer mortality at 11 years of follow-up (ERSPC trial). New England Journal of Medicine. 2012;366(11):981-990. Find on PubMed
- Andriole GL, Crawford ED, Grubb RL III, et al. Mortality results from a randomized prostate-cancer screening trial (PLCO). New England Journal of Medicine. 2009;360(13):1310-1319. — doi:10.1056/NEJMoa0810696
- Thompson IM, Goodman PJ, Tangen CM, et al. The influence of finasteride on the development of prostate cancer (PCPT). New England Journal of Medicine. 2003;349(3):215-224. — doi:10.1056/NEJMoa030660
- McConnell JD, Roehrborn CG, Bautista OM, et al. The long-term effect of doxazosin, finasteride, and combination therapy on the clinical progression of BPH (MTOPS). New England Journal of Medicine. 2003;349(25):2387-2398. Find on PubMed
- Gravas S, Malde S, Cornu JN, et al. From BPH to male LUTS: a 20-year journey of the EAU guidelines. Prostate Cancer and Prostatic Diseases. 2024;27(1):48-53. — PubMed PMID: 37488274
- Tacklind J, Macdonald R, Rutks I, Stanke JU, Wilt TJ. Serenoa repens for benign prostatic hyperplasia. Cochrane Database of Systematic Reviews. 2012;12:CD001423. — doi:10.1002/14651858.CD001423.pub3
- Lippman SM, Klein EA, Goodman PJ, et al. Effect of selenium and vitamin E on risk of prostate cancer (SELECT trial). JAMA. 2009;301(1):39-51. — PubMed PMID: 19066370
- Hamdy FC, Donovan JL, Lane JA, et al. 10-Year outcomes after monitoring, surgery, or radiotherapy for localized prostate cancer (ProtecT trial). New England Journal of Medicine. 2016;375(15):1415-1424. — Search PubMed
- US Preventive Services Task Force. Screening for Prostate Cancer: US Preventive Services Task Force Recommendation Statement. JAMA. 2018;319(18):1901-1913. — doi:10.1001/jama.2018.3710
- Nickel JC. Prostatitis. Canadian Urological Association Journal. 2011;5(5):306-315. PubMed PMID: 22031609
- Roehrborn CG. Benign prostatic hyperplasia: an overview. Reviews in Urology. 2005;7(Suppl 9):S3-S14. — PubMed PMID: 16985902
- Wilt TJ, Brawer MK, Jones KM, et al. Radical prostatectomy versus observation for localized prostate cancer (PIVOT trial). New England Journal of Medicine. 2012;367(3):203-213. Find on PubMed
- Franco JV, Trivisonno L, Sgarbossa NJ, et al. Serenoa repens for the treatment of lower urinary tract symptoms due to benign prostatic enlargement. Cochrane Database of Systematic Reviews. 2023;6(6):CD001423. — PubMed PMID: 37345871
- Barry MJ, Meleth S, Lee JY, et al. Effect of increasing doses of saw palmetto extract on lower urinary tract symptoms: a randomized trial (CAMUS). JAMA. 2011;306(12):1344-1351. — PubMed PMID: 21954478
- Andriole GL, McCullum-Hill C, Sandhu GS, et al. The effect of increasing doses of saw palmetto fruit extract on serum prostate specific antigen: analysis of the CAMUS randomized trial. Journal of Urology. 2013;189(2):486-492. — PubMed PMID: 23253958
- Wei JT, Barocas D, Carlsson S, et al. Early Detection of Prostate Cancer: AUA/SUO Guideline Part I: Prostate Cancer Screening. Journal of Urology. 2023;210(1):46-53. — PubMed PMID: 37096582
- Roobol MJ, de Vos II, Månsson M, et al. European Study of Prostate Cancer Screening - 23-Year Follow-up. New England Journal of Medicine. 2025;393(17):1669-1680. — PubMed PMID: 41160819
- Martin RM, Turner EL, Young GJ, et al. Prostate-Specific Antigen Screening and 15-Year Prostate Cancer Mortality: A Secondary Analysis of the CAP Randomized Clinical Trial. JAMA. 2024;331(17):1460-1470. — PubMed PMID: 38581198
- Hamdy FC, Donovan JL, Lane JA, et al. Fifteen-Year Outcomes after Monitoring, Surgery, or Radiotherapy for Prostate Cancer. New England Journal of Medicine. 2023;388(17):1547-1558. — PubMed PMID: 36912538
- Oketch-Rabah HA, Roe AL, Rider CV, et al. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicology Reports. 2020;7:386-402. — PubMed PMID: 32140423
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. Journal of the National Cancer Institute. 2003;95(13):1004-1007. — PubMed PMID: 12837837
Historical Background
The prostate gland was first described anatomically by Venetian anatomist Niccolo Massa in 1536. The first prostatectomy was performed by Theodor Billroth in 1867. Hugh Hampton Young developed the perineal prostatectomy technique in 1904, and the prostate-specific antigen (PSA) test was introduced for clinical use in the late 1980s by Thomas Stamey and colleagues, fundamentally changing prostate cancer screening.
PubMed Topic Searches
- Clinical trials on prostate health (BPH and prostatitis) — PubMed search
- PSA screening and prostate cancer outcomes — PubMed search
- Saw palmetto (Serenoa repens) for prostate health — PubMed search
- Chronic prostatitis / chronic pelvic pain syndrome — PubMed search
- Lycopene and prostate cancer risk — PubMed search
- Zinc and prostate disease — PubMed search
- Pygeum africanum for BPH — PubMed search
- Active surveillance for localized prostate cancer — PubMed search
Connections
- Urology
- Benign Prostatic Hyperplasia
- Zinc
- Erectile Dysfunction
- Saw Palmetto
- Selenium
- Low Testosterone / TRT
- Urinary Tract Infections
- Cancer Overview
- Testosterone Test
- Prostate-Specific Antigen Test
- Green Tea
- Obesity
- Insulin Resistance
- Tomatoes
- Omega-3 Fatty Acids
- Bladder Cancer
- rBGH
- Selenium and Cancer Prevention
- Selenium and Cancer Prevention (Deep Dive) — selenoprotein biology, the NPC and SELECT trials, evidence across prostate/colorectal/lung cancers, and the U-shaped dose-response curve.
- Prostate Cancer