⚠ Evidence warning: Clinical trials or other evidence do not support the claims that an absorption advantage over magnesium oxide made magnesium glycinate the clinical standard, and that muscle cramp studies consistently rank glycinate above other magnesium forms. This page keeps it as a report of what people, websites or other media say.
Magnesium Glycinate — Benefits Deep Dive
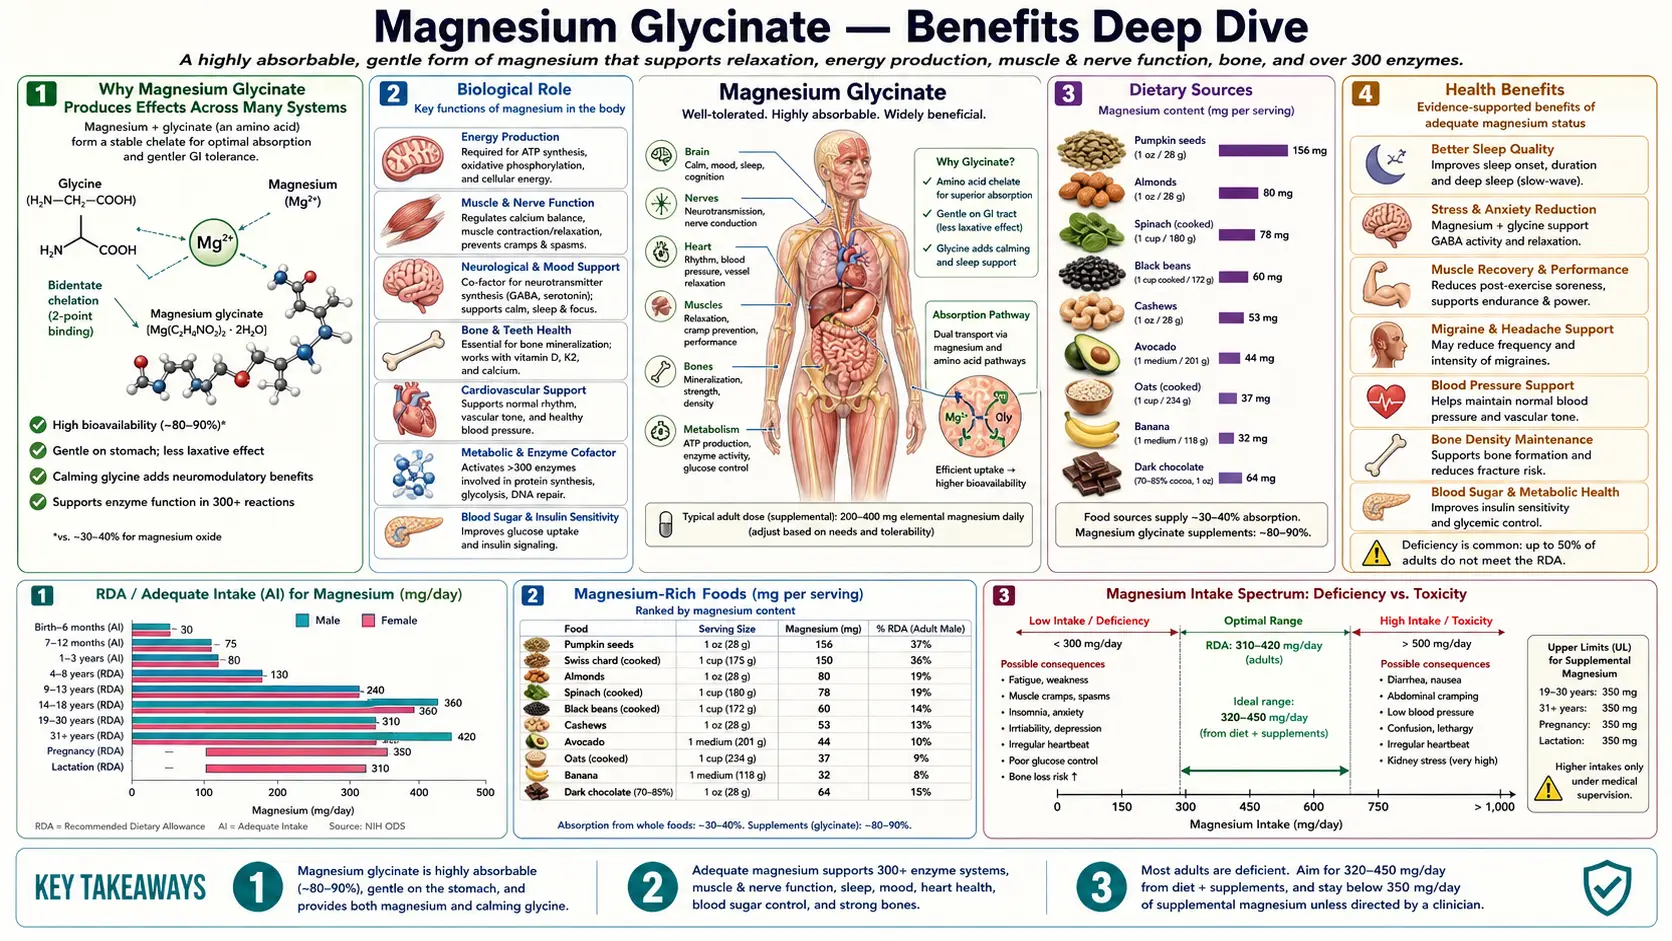
Magnesium glycinate is a form of magnesium valued for being gentle on the gut — a chelate in which the Mg2+ ion is held in a stable claw-like grip by two molecules of the inhibitory amino acid glycine. That dual identity makes it unique among magnesium supplements: the magnesium half is the cofactor for more than 600 enzymes (adenosine triphosphate (ATP) production, DNA repair, the Na/K ATPase pump, N-methyl-D-aspartate (NMDA) channel gating), while the glycine half is itself a sleep-promoting and anxiety-reducing neurotransmitter that builds collagen and feeds glutathione synthesis. The four deep-dive pages below walk through the specific uses for which magnesium glycinate is taken: the sleep effects of glycine documented in Inagawa's pre-bed glycine trial (which tested glycine alone, not magnesium glycinate), the gamma-aminobutyric acid-A potentiation and hypothalamic-pituitary-adrenal-axis modulation behind its anxiolytic effect, the muscle-relaxation profile that makes it a form practitioners often choose for nocturnal cramps and restless legs, and the chelate chemistry together with what absorption studies actually measured — in a 1994 trial in 12 patients with ileal resection, absorption was not different overall (23.5% for magnesium diglycinate versus 22.8% for magnesium oxide), although the chelate did better (23.5% versus 11.8%) in the four patients who absorbed oxide worst.
Deep-Dive Articles
Sleep Quality
Why magnesium glycinate is the most-prescribed natural sleep aid in 2026. The dual mechanism — magnesium as cofactor for the pineal serotonin-to-melatonin conversion and as N-methyl-D-aspartate receptor blocker, plus glycine's own sleep effects via peripheral vasodilation and core temperature drop. The Inagawa pre-bed glycine + sleep architecture study, REM/NREM effects, and comparison to magnesium L-threonate (central nervous system (CNS) targeting) and malate (energy/fibromyalgia).
Read the deep dive →Anxiety Relief
The neurochemistry of magnesium's anxiolytic effect: gamma-aminobutyric acid-A receptor positive allosteric modulation (the same target as benzodiazepines, without the dependence), N-methyl-D-aspartate glutamate channel blockade, and hypothalamic-pituitary-adrenal-axis dampening. Glycine's role as the dominant inhibitory neurotransmitter of the brainstem and spinal cord. The Boyle 2017 systematic review of 18 trials, the cortisol/magnesium vicious circle, and the place of glycinate in adult anxiety treatment alongside therapy and selective serotonin reuptake inhibitors (SSRIs).
Read the deep dive →Muscle Relaxation
Why glycinate is often chosen for muscle cramps over oxide and citrate, which are known for causing diarrhea. Magnesium as a physiological calcium antagonist at the sarcoplasmic reticulum, nocturnal leg cramp evidence, restless legs syndrome trials, fibromyalgia and chronic tension applications, training-induced muscle tension in athletes, and pregnancy-related leg cramps where glycinate's gentle profile matters most.
Read the deep dive →Bioavailability
The chelate chemistry that defines glycinate — manufacturers' patented chelation processes, what the absorption studies actually measured across forms (a 1994 isotope trial found 23.5% for the chelate versus 22.8% for oxide), saturation kinetics, the difference between "fully reacted" chelate and oxide-buffered-with-glycine impostors, independent testing and certification programs, label red flags that signal inferior product, and how to read a Certificate of Analysis.
Read the deep dive →Interactive Visualization Magnesium — the mineral that makes adenosine triphosphate work Bare adenosine triphosphate is useless and enzymes reject it. Watch magnesium clamp the phosphates and switch it on, plug the N-methyl-D-aspartate channel, and let a cramping muscle finally let go. Launch →
Table of Contents
- Deep-Dive Articles
- Why Magnesium Glycinate Produces Effects Across Many Systems
- Research Papers: Sleep Quality
- Research Papers: Anxiety & Stress
- Research Papers: Muscle Relaxation & Cramps
- Research Papers: Bioavailability & Chelate Chemistry
- Research Papers: Cross-Cutting (Magnesium Status, Glycine Biology)
- External Authoritative Resources
- Connections
- Featured Videos
Why Magnesium Glycinate Produces Effects Across Many Systems
Most supplements act through one principal mechanism. Magnesium glycinate is unusual because it delivers two biologically active molecules that each operate through fundamentally different mechanisms, and the two effects converge on the same therapeutic territory — sleep, anxiety, muscle tension, and nervous-system tone. Each of the two ingredients maps to a distinct family of clinical effects, and the overlap is precisely what makes the chelate so versatile.
- Magnesium as a 600-enzyme cofactor — the Mg2+ ion is required by more than 600 mammalian enzymes, including every reaction that uses adenosine triphosphate (Mg2+ is the counter-ion that stabilizes the phosphate groups), the Na/K-ATPase pump that establishes the neuronal resting potential, glutamic acid decarboxylase that produces inhibitory gamma-aminobutyric acid (GABA), and the methyltransferases that handle DNA repair and methionine cycling. Magnesium also sits as a voltage-dependent plug in the N-methyl-D-aspartate glutamate receptor ion channel, preventing calcium influx during normal neuronal activity. Loss of that N-methyl-D-aspartate block in magnesium deficiency is the proximate molecular cause of anxiety, hyperexcitability, and insomnia in deficient individuals — and the proximate target of magnesium's anxiolytic effect when status is restored.
- Glycine as an inhibitory neurotransmitter, collagen building block, and glutathione precursor — glycine is the smallest amino acid and one of the most metabolically versatile. It is the dominant inhibitory neurotransmitter of the brainstem and spinal cord (acting through strychnine-sensitive glycine receptors, separate from gamma-aminobutyric acid), one of three amino-acid precursors to glutathione (the body's master antioxidant), and one in every three amino acids in collagen. Glycine also acts as a co-agonist at the N-methyl-D-aspartate receptor (the glycine binding site is required for the receptor to open even in the presence of glutamate), and it lowers core body temperature by dilating peripheral blood vessels — the physiological signal that initiates sleep onset.
- Chelate chemistry that protects both molecules through digestion — the magnesium-glycine bisglycinate chelate is a stable five-membered ring in which two glycine molecules grip the Mg2+ ion through nitrogen and oxygen coordination. The ring structure protects the magnesium from precipitation by stomach acid, from chelation by dietary phytates and oxalates, and from saturation of the passive paracellular magnesium absorption channels. The intact chelate is absorbed through amino-acid transport pathways in the small intestinal enterocyte, then split intracellularly into free Mg2+ and free glycine for their downstream effects. The fractional absorption advantage over magnesium oxide is the engineering reason glycinate has displaced cheaper forms as the clinical standard. Measured absorption is more modest than this suggests. In a 1994 double-blind crossover trial in 12 patients with ileal resection, absorption of a 100 mg labelled dose was not different overall (23.5% for the diglycinate chelate versus 22.8% for magnesium oxide), although the chelate was absorbed better in the four patients who absorbed oxide worst (23.5% versus 11.8%) and was better tolerated by all patients. A 2003 trial that compared an amino-acid chelate, citrate and oxide at 300 mg a day for 60 days in 46 adults found citrate the most bioavailable. The 4% figure often quoted for oxide comes from a 2001 study that did not test glycinate and concluded that inorganic magnesium salts may be as bioavailable as organic ones. These studies are discussed in the bioavailability deep dive.
The clinical convergence is what makes the supplement therapeutically powerful. Magnesium and glycine each independently promote sleep (magnesium via melatonin synthesis and gamma-aminobutyric acid-A potentiation, glycine via core temperature drop and N-methyl-D-aspartate modulation), each independently reduce anxiety (magnesium via gamma-aminobutyric acid-A modulation and hypothalamic-pituitary-adrenal-axis dampening, glycine via brainstem and spinal cord glycine receptors), and each independently support muscle relaxation (magnesium via calcium antagonism at the sarcoplasmic reticulum, glycine via spinal cord motor neuron inhibition through Renshaw cell circuits). Practitioners describe the combined effect on these overlapping outcomes as greater than either ingredient alone. The combined effect on these overlapping outcomes is greater than either ingredient alone — which is why muscle cramp prevention studies consistently rank glycinate above other magnesium forms despite the absence of any difference in elemental magnesium delivered per dose. The form genuinely matters, not just the dose. The cramp trials themselves have not compared magnesium forms: the 2020 Cochrane review of muscle cramp prevention (11 randomized trials, 735 people) compared magnesium with placebo, no treatment or other therapies; it concluded that magnesium is unlikely to give clinically meaningful cramp prevention to older adults, found the evidence for pregnancy-related cramps conflicting, and found no trials of magnesium for exercise-associated cramps.
Safety limits. The Institute of Medicine set the tolerable upper intake level for magnesium from supplements and medicines at 350 mg a day for teenagers and adults, based on diarrhea, the most sensitive sign of excess; it assumed that all magnesium salts that dissolve and release magnesium share this effect. Magnesium from food does not count toward this limit. The same report notes that high blood magnesium (hypermagnesemia) can occur in people with impaired kidney function, most commonly when poor kidney function is combined with large amounts of magnesium from non-food sources such as supplements or antacids.
Research Papers: Sleep Quality
- Magnesium bisglycinate supplementation in healthy adults reporting poor sleep (RCT) — PubMed: Bisglycinate sleep RCT
- Inagawa K, Hiraoka T, Kohda T, Yamadera W, Takahashi M (2006). Subjective effects of glycine ingestion before bedtime on sleep quality. Sleep and Biological Rhythms 4(1):75–77. Not indexed in PubMed — doi:10.1111/j.1479-8425.2006.00193.x
- Bannai M, Kawai N (2012). New therapeutic strategy for amino acid medicine: glycine improves the quality of sleep. Journal of Pharmacological Sciences — PubMed PMID: 22293292
- Yamadera W, Inagawa K, Chiba S, Bannai M, Takahashi M, Nakayama K (2007). Glycine ingestion improves subjective sleep quality in human volunteers, correlating with polysomnographic changes. Sleep and Biological Rhythms 5(2):126–131. Not indexed in PubMed — doi:10.1111/j.1479-8425.2007.00262.x
- Abbasi B et al. (2012). The effect of magnesium supplementation on primary insomnia in elderly — PubMed: Abbasi magnesium insomnia
- Wienecke E, Nolden C. Long-term HRV analysis shows stress reduction by magnesium intake — PubMed: HRV and magnesium
- Held K et al. Oral magnesium supplementation improves slow wave sleep in elderly subjects — PubMed: Held slow-wave sleep
- Cao Y et al. (2018). Magnesium intake and sleep disorder symptoms in the Jiangsu Nutrition Study — PubMed: Magnesium and sleep disorders
- Hausenblas HA, Lynch T, Hooper S, Shrestha A, Rosendale D, Gu J (2024). Magnesium-L-threonate improves sleep quality and daytime functioning in adults with self-reported sleep problems: a randomized controlled trial. Sleep Medicine: X — PubMed PMID: 39252819
- Slutsky I et al. (2010). Enhancement of learning and memory by elevating brain magnesium (L-threonate) — PubMed: Slutsky brain magnesium
Research Papers: Anxiety & Stress
- Boyle NB et al. (2017). The effects of magnesium supplementation on subjective anxiety and stress: a systematic review — PubMed: Boyle 2017 systematic review
- Sartori SB et al. (2012). Magnesium deficiency induces anxiety and HPA axis dysregulation — PubMed: Magnesium HPA axis
- Pickering G et al. (2020). Magnesium status and stress: the vicious circle concept revisited — PubMed: Magnesium-stress cycle
- Botturi A et al. (2020). The role and the effect of magnesium in mental disorders — PubMed: Magnesium and mental disorders
- de Baaij JH, Hoenderop JG, Bindels RJ. Magnesium in man: implications for health and disease — PubMed: Magnesium physiology review
- Eby GA, Eby KL. Rapid recovery from major depression using magnesium treatment — PubMed: Eby magnesium depression
- Tarleton EK et al. (2017). Role of magnesium supplementation in the treatment of depression — PubMed: Tarleton depression RCT
- Kalueff AV, Nutt DJ. Role of GABA in anxiety and depression — PubMed: GABA in anxiety
- Lopez-Corcuera B et al. Glycine neurotransmitter transporters: an update — PubMed: Glycine neurotransmitter
Research Papers: Muscle Relaxation & Cramps
- Garrison SR, Korownyk CS, Kolber MR, Allan GM, Musini VM, Sekhon RK, Dugré N (2020). Magnesium for skeletal muscle cramps. Cochrane Database of Systematic Reviews — PubMed PMID: 32956536
- Roffe C et al. Randomised, cross-over, placebo controlled trial of magnesium citrate in chronic persistent leg cramps — PubMed: Roffe leg cramps trial
- Supakatisant C, Phupong V. Oral magnesium for relief in pregnancy-induced leg cramps — PubMed: Pregnancy leg cramps
- Hornyak M et al. Magnesium therapy for periodic leg movements-related insomnia and restless legs syndrome — PubMed: Hornyak RLS
- Kovacs L, Molnar BG, Huhn E, Bodis L. Magnesium substitution in pregnancy — randomized double-blind trial — PubMed: Kovacs pregnancy trial
- Bagis S et al. Is magnesium citrate treatment effective on pain, clinical parameters and functional status in patients with fibromyalgia? — PubMed: Magnesium fibromyalgia
- Tarsitano MG, Quinzi F, Folino K, Greco F, Oranges FP, Cerulli C, Emerenziani GP (2024). Effects of magnesium supplementation on muscle soreness in different type of physical activities: a systematic review. Journal of Translational Medicine — PubMed PMID: 38970118
- Setaro L et al. Magnesium status and the physical performance of volleyball players — PubMed: Magnesium volleyball
- Veronese N et al. Effect of oral magnesium supplementation on physical performance in healthy elderly — PubMed: Magnesium elderly performance
Research Papers: Bioavailability & Chelate Chemistry
- Blancquaert L, Vervaet C, Derave W. (2019). Predicting and testing bioavailability of magnesium supplements — PubMed: Bioavailability prediction
- Schuette SA, Lashner BA, Janghorbani M (1994). Bioavailability of magnesium diglycinate vs magnesium oxide in patients with ileal resection. JPEN Journal of Parenteral and Enteral Nutrition — PubMed PMID: 7815675
- Walker AF, Marakis G, Christie S, Byng M (2003). Mg citrate found more bioavailable than other Mg preparations in a randomised, double-blind study. Magnesium Research — PubMed PMID: 14596323
- Lindberg JS et al. Magnesium bioavailability from magnesium citrate and magnesium oxide — PubMed: Lindberg citrate vs oxide
- Mühlbauer B, Schwenk M, Coram WM, Antonin KH, Etienne P, Bieck PR, Douglas FL (1991). Magnesium-L-aspartate-HCl and magnesium-oxide: bioavailability in healthy volunteers. European Journal of Clinical Pharmacology — PubMed PMID: 2050185
- Ranade VV, Somberg JC. Bioavailability and pharmacokinetics of magnesium after administration of magnesium salts to humans — PubMed: Ranade pharmacokinetics
- Coudray C et al. Study of magnesium bioavailability from ten organic and inorganic salts (rats, isotope) — PubMed: Ten-salt comparison
- Firoz M, Graber M (2001). Bioavailability of US commercial magnesium preparations. Magnesium Research — PubMed PMID: 11794633
- Schwalfenberg GK, Genuis SJ. The importance of magnesium in clinical healthcare — PubMed: Schwalfenberg review
Research Papers: Cross-Cutting (Magnesium Status, Glycine Biology)
- DiNicolantonio JJ, O'Keefe JH, Wilson W. Subclinical magnesium deficiency: a principal driver of cardiovascular disease — PubMed: DiNicolantonio Mg deficiency
- Rosanoff A, Weaver CM, Rude RK. Suboptimal magnesium status in the United States — PubMed: US magnesium status
- Costello RB, Elin RJ, Rosanoff A et al. Perspective: the case for an evidence-based reference interval for serum magnesium — PubMed: Mg reference interval
- Workinger JL, Doyle RP, Bortz J. Challenges in the diagnosis of magnesium status — PubMed: Mg status diagnosis
- Wang W, Wu Z, Dai Z et al. Glycine metabolism in animals and humans: implications for nutrition and health — PubMed: Glycine metabolism
- Razak MA et al. Multifarious beneficial effect of nonessential amino acid, glycine: a review — PubMed: Razak glycine review
- Meléndez-Hevia E et al. A weak link in metabolism: the metabolic capacity for glycine biosynthesis does not satisfy collagen demand — PubMed: Glycine biosynthesis gap
- Díaz-Flores M, Cruz M, Duran-Reyes G, et al. (2013). Oral supplementation with glycine reduces oxidative stress in patients with metabolic syndrome, improving their systolic blood pressure. Canadian Journal of Physiology and Pharmacology — PubMed PMID: 24144057
- Kirkland AE, Sarlo GL, Holton KF. The role of magnesium in neurological disorders — PubMed: Mg in neurology
- Gröber U, Schmidt J, Kisters K. Magnesium in prevention and therapy — PubMed: Gröber Mg review
External Authoritative Resources
- Linus Pauling Institute — Magnesium Micronutrient Information Center — the most authoritative scientific summary of magnesium biology, regularly updated by the Oregon State University micronutrient research group
- U.S. National Institutes of Health (NIH) Office of Dietary Supplements — Magnesium Fact Sheet (Health Professionals)
- MedlinePlus — Magnesium
- MedlinePlus — Amino acids
- Independent supplement-testing services publish third-party laboratory tests of magnesium products, some of them only to paying subscribers
- Institute of Medicine (1997) — Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride, chapter 6: Magnesium — source of the 350 mg/day upper limit for supplemental magnesium
- PubMed — Magnesium glycinate / bisglycinate research
Connections
- All Minerals
- Magnesium: The Mineral That Makes Adenosine Triphosphate Work — interactive animation
- Magnesium Glycinate (Main Page)
- Magnesium Glycinate for Sleep Quality
- Magnesium Glycinate for Anxiety Relief
- Magnesium Glycinate for Muscle Relaxation
- Magnesium Glycinate Bioavailability
- Magnesium (Mineral Overview)
- Magnesium for Sleep
- Magnesium for Heart Health
- Glycine
- Calcium (Magnesium's Antagonist)
- Potassium
- Anxiety
- Insomnia
- Depression
- Migraine
- Cramp Prevention
- Sleep Hygiene
- Natural Anxiety Relief
- History