Magnesium Glycinate for Sleep Quality
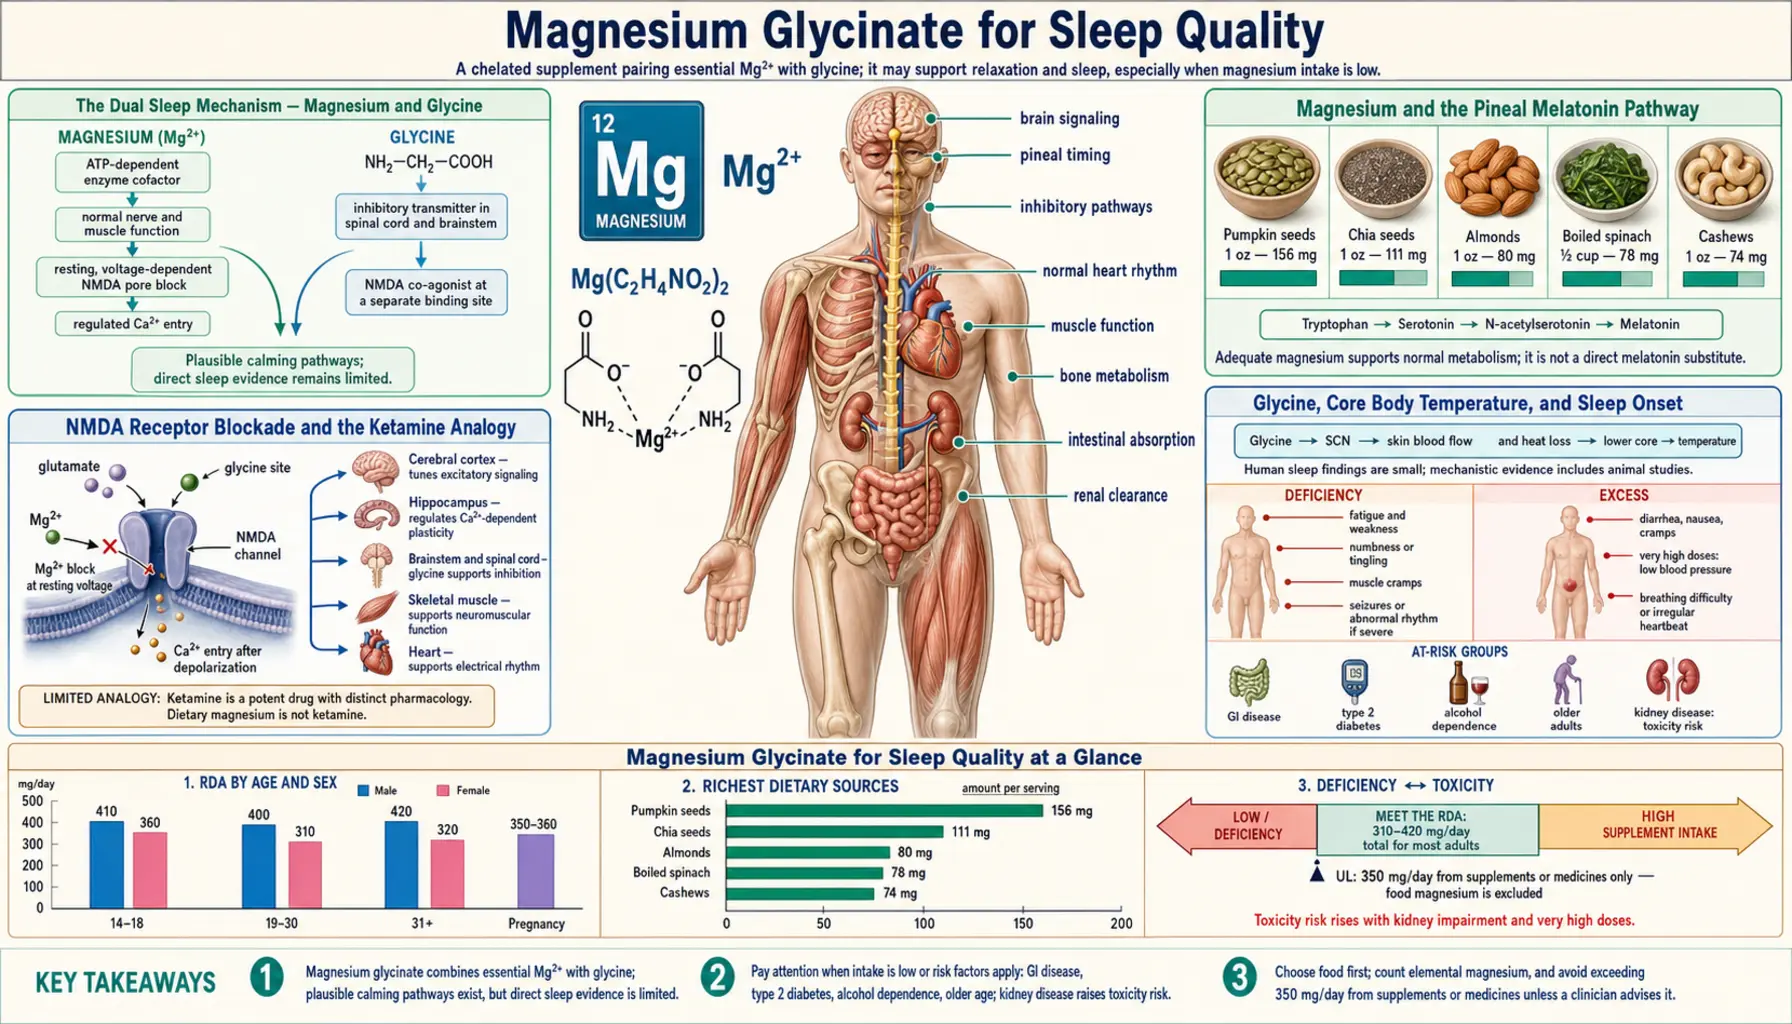
Magnesium glycinate is the single most-discussed sleep supplement of the 2025-2026 wellness moment, and the popularity is grounded in pharmacology rather than fashion. The chelate delivers two molecules — magnesium and glycine — that each independently promote sleep through different mechanisms, and the combined effect on sleep architecture is greater than either alone. Magnesium acts on the pineal serotonin-to-melatonin conversion and as a voltage-dependent plug in the N-methyl-D-aspartate (NMDA) glutamate receptor (the same receptor ketamine targets). Glycine acts as an inhibitory neurotransmitter at the brainstem and spinal cord, lowers core body temperature through peripheral vasodilation (the physiological trigger for sleep onset), and modulates the suprachiasmatic nucleus master circadian clock. Inagawa's 2006 study showed that 3 grams of glycine taken 60 minutes before bedtime shortened sleep latency, improved subjective sleep quality, and enhanced next-day cognitive performance — effects confirmed in subsequent polysomnography work showing earlier entry into slow-wave sleep. This page walks through the dual mechanism, the bisglycinate-specific clinical evidence, the comparison to other magnesium forms used for sleep, and the practical protocol for sleep-targeted dosing.
Interactive Visualization Magnesium — the mineral that makes adenosine triphosphate (ATP) work Bare adenosine triphosphate is useless and enzymes reject it. Watch magnesium clamp the phosphates and switch it on, plug the N-methyl-D-aspartate channel, and let a cramping muscle finally let go. Launch →
Table of Contents
- The Dual Sleep Mechanism — Magnesium and Glycine
- Magnesium and the Pineal Melatonin Pathway
- N-Methyl-D-Aspartate Receptor Blockade and the Ketamine Analogy
- Glycine, Core Body Temperature, and Sleep Onset
- Effects on Sleep Architecture (NREM, REM, Slow-Wave)
- The Inagawa Pre-Bed Glycine Trial and Follow-ups
- The 2025 Magnesium Bisglycinate Randomized Controlled Trial
- Sleep-Specific Comparison: Glycinate vs Threonate vs Malate vs Citrate
- Dosing Protocol for Sleep
- Cautions and What to Watch For
- Key Research Papers
- Connections
- Featured Videos
The Dual Sleep Mechanism — Magnesium and Glycine
What makes magnesium glycinate uniquely suited to sleep applications is that both halves of the chelate act on the sleep machinery independently. This is unusual for a supplement — most ingredients have one mechanism and one application. Magnesium glycinate is more like a fixed-dose combination drug in which the two components target different parts of the same outcome.
The magnesium half operates through at least four well-mapped sleep mechanisms: it serves as a cofactor for the pineal-gland conversion of serotonin to melatonin, it potentiates the gamma-aminobutyric acid-A receptor (the same target as benzodiazepines, though through positive allosteric modulation rather than competitive binding), it occupies the N-methyl-D-aspartate glutamate receptor as a voltage-dependent ion-channel plug that prevents excitotoxic calcium influx, and it dampens the hypothalamic-pituitary-adrenal (HPA) axis cortisol response that drives nighttime waking.
The glycine half operates through a completely separate set of mechanisms: it acts as the principal inhibitory neurotransmitter of the brainstem and spinal cord (through strychnine-sensitive glycine receptors that are distinct from gamma-aminobutyric acid (GABA) receptors), it lowers core body temperature by dilating peripheral skin blood vessels (the physiological signal the hypothalamus reads as "time to sleep"), and it modulates neurotransmission in the suprachiasmatic nucleus — the brain's master circadian clock — through N-methyl-D-aspartate receptor co-agonism. Glycine is also the most abundant inhibitory neurotransmitter at the brainstem motor circuits that produce the muscle atonia of REM sleep.
The convergence of these mechanisms on a single outcome — deeper, longer, more restorative sleep with shorter onset latency — explains why glycinate is consistently rated by users as more "calming" than equivalent doses of magnesium oxide or citrate, and why a number of practitioners who once recommended pure glycine for sleep have migrated to magnesium glycinate as a more practical delivery vehicle that supplies both ingredients in one capsule.
Magnesium and the Pineal Melatonin Pathway
Melatonin is the hormone that signals nightfall to every cell in the body, and its synthesis is a magnesium-dependent four-step enzymatic chain that runs in the pineal gland during the dark phase of the circadian cycle. The pathway begins with tryptophan, which is hydroxylated to 5-hydroxytryptophan (5-HTP) by tryptophan hydroxylase, then decarboxylated to serotonin by aromatic L-amino acid decarboxylase. Serotonin is then N-acetylated by arylalkylamine N-acetyltransferase (AANAT) to N-acetyl-serotonin, and finally O-methylated by hydroxyindole-O-methyltransferase (HIOMT) to melatonin proper.
Magnesium is a required cofactor at two of the four steps, most critically at the AANAT step that is the rate-limiting reaction of the entire pathway. In magnesium deficiency, melatonin production at the pineal gland falls measurably below what the same individual would produce with adequate magnesium status, which manifests as later subjective sleep onset, more fragmented sleep, and (in elderly patients particularly) shallower nocturnal melatonin peaks measured in serum or salivary assays. In a 2012 trial in 46 elderly people with primary insomnia, Abbasi and colleagues found that 500 mg of magnesium a day for 8 weeks raised serum renin and melatonin and lowered serum cortisol compared with placebo. An earlier study by Held and colleagues (2002) in 12 people aged 60–80 (not selected for insomnia; magnesium rising to 30 mmol a day for 14 days) found that renin and aldosterone rose, cortisol fell and slow-wave sleep increased (16.5 vs 10.1 minutes) — changes the authors describe as partly reversing the sleep and hormone changes of aging.
This pineal-melatonin mechanism is one of the reasons magnesium glycinate is particularly useful for sleep-onset insomnia (the trouble-falling-asleep complaint, as distinct from sleep-maintenance insomnia or early-morning waking). When the underlying problem is inadequate evening melatonin rise, repleting magnesium status sometimes restores normal melatonin production sufficiently that supplemental melatonin is not needed. When supplemental melatonin is needed, magnesium glycinate is a useful companion because adequate magnesium ensures the body can still use endogenous melatonin signaling efficiently even after the exogenous dose wears off in the second half of the night.
N-Methyl-D-Aspartate Receptor Blockade and the Ketamine Analogy
The N-methyl-D-aspartate (NMDA) glutamate receptor is the central excitatory ion channel of the mammalian brain — the molecular machinery behind learning, memory, and synaptic plasticity. Under normal conditions, a magnesium ion sits inside the N-methyl-D-aspartate receptor channel as a voltage-dependent plug, preventing calcium influx until the postsynaptic membrane has been depolarized by other receptors. This is the famous "coincidence detector" property that makes N-methyl-D-aspartate receptors the substrate of Hebbian learning — the channel only opens when both glutamate is bound and the membrane is already depolarized, ensuring that long-term potentiation occurs only when two neurons fire together.
In magnesium deficiency, the Mg2+ plug becomes unstable. The N-methyl-D-aspartate channel opens more readily even at resting membrane potential, allowing inappropriate calcium influx into neurons. The downstream consequences include neuronal hyperexcitability, excitotoxic stress, glutamate-driven anxiety, and — specifically for sleep — the inability to enter and maintain deep NREM sleep stages. Sleep requires active cortical inhibition; runaway N-methyl-D-aspartate signaling disrupts that inhibition.
The ketamine analogy is illuminating. Ketamine is a non-competitive N-methyl-D-aspartate receptor antagonist that, at subanesthetic doses, produces rapid antidepressant and pro-sleep effects in treatment-resistant patients. Its mechanism is occupying the same N-methyl-D-aspartate channel that magnesium normally plugs — only more aggressively and irreversibly. Magnesium is the natural, gentle, dose-dependent version of this same mechanism. Restoring adequate magnesium status restores the natural N-methyl-D-aspartate plug, calms cortical glutamate signaling, and permits the cortical synchronization that produces deep slow-wave sleep. This is one of the molecular reasons severely magnesium-deficient patients often describe sleep on supplementation as "feeling deeper" rather than just "more hours."
Glycine, Core Body Temperature, and Sleep Onset
The most distinctive contribution of glycine to the sleep effect of magnesium glycinate is its effect on core body temperature. Sleep onset is preceded, in every healthy human, by a drop in core body temperature of approximately 0.5 to 1.0 degrees Celsius. This temperature drop is driven by peripheral vasodilation (specifically of the skin blood vessels in the hands, feet, and face), which transfers heat from the body core to the environment. The hypothalamus reads the resulting core temperature drop as the cue to release sleep-promoting signals and initiate the cascade leading to NREM stage 1 sleep.
Glycine appears to speed up this peripheral vasodilation. In rats, oral glycine raised blood flow in the skin and lowered core body temperature (Bannai and Kawai, 2012); a 2015 rat study by Kawai and colleagues traced the effect to N-methyl-D-aspartate receptors in the suprachiasmatic nucleus, the brain's master clock, and found no effect when glycine was injected into the medial preoptic area. The researchers propose this drop in core temperature as a possible mechanism for glycine's effect on sleep.
Subjectively, the experience users report when this mechanism is working well is hands and feet getting warm, a sense of "settling" within 15-30 minutes of taking the supplement, and quicker sleep onset. The effect is gentle — not the sudden "hit" of a benzodiazepine but more like the natural sleep-onset cascade being permitted to run efficiently.
Because magnesium glycinate at typical sleep doses (300-400 mg of glycinate compound, delivering roughly 40-60 mg of elemental magnesium plus 250-350 mg of glycine) supplies meaningful amounts of glycine, the temperature-drop effect of the chelate is real but smaller in magnitude than the 3-gram pure-glycine dose used in research trials. Users who want the full Inagawa effect sometimes combine 200-400 mg of magnesium glycinate with an additional 1-3 grams of free glycine powder dissolved in water 60 minutes before bed.
Effects on Sleep Architecture (NREM, REM, Slow-Wave)
"Sleep quality" is a vague phrase. Researchers and clinicians distinguish several measurable dimensions of sleep, each of which responds differently to different interventions:
- Sleep latency — the time from lights-out to entering stage 1 NREM sleep. Normal is 10-20 minutes; insomniacs often exceed 30-60 minutes.
- Sleep efficiency — the percentage of time in bed actually spent asleep. Normal is 85% or higher; impaired sleep often falls to 70% or below.
- Slow-wave (delta) sleep — the deepest NREM stages (formerly N3 and N4, now combined as N3), characterized by large slow electroencephalogram (EEG) waves at 0.5-4 Hz. This is where most physical restoration and growth hormone release occurs. Normally about 15-25% of total sleep time.
- REM sleep — rapid eye movement sleep, the dreaming stage, characterized by electroencephalogram activation paradoxically combined with muscle atonia. Important for memory consolidation and emotional processing. Normally about 20-25% of total sleep time.
- Wake-after-sleep-onset (WASO) — minutes of wakefulness after first falling asleep. Normal is under 30 minutes; insomniacs often exceed 60-90 minutes.
Magnesium glycinate itself has not been measured on these dimensions with sleep recordings: the 2025 bisglycinate trial described below used questionnaires only, and its authors list objective measures such as actigraphy or polysomnography as work for future studies. Users describe falling asleep more easily and sleep that feels deeper. For magnesium in general, Held and colleagues (2002) recorded more slow-wave sleep on the sleep electroencephalogram (16.5 vs 10.1 minutes) in 12 people aged 60–80 after magnesium supplementation.
In the 2025 bisglycinate trial the effect was small (Cohen's d = 0.2). Practitioners contrast magnesium glycinate with prescription sleep aids such as zolpidem, which they describe as producing a larger acute change in sleep latency: they describe magnesium glycinate as not habit-forming, without next-day cognitive impairment, and as an improvement that builds over weeks rather than peaking on day one and fading as tolerance develops — the opposite of the Z-drug pattern.
The Inagawa Pre-Bed Glycine Trial and Follow-ups
The pivotal evidence for the sleep-promoting effect of the glycine component comes from a series of studies by Kentaro Inagawa and colleagues at the Ajinomoto Group's Institute of Life Sciences in Japan, beginning with a 2006 randomized crossover trial published in Sleep and Biological Rhythms. The protocol gave participants who self-reported unsatisfactory sleep either 3 grams of oral glycine or placebo, taken 60 minutes before bedtime, on separate nights with a wash-out period.
Results were measured by validated subjective sleep questionnaires (St. Mary's Hospital Sleep Questionnaire, Space Aeromedical Sleep Questionnaire) and next-day cognitive tests. The glycine condition produced significantly better subjective sleep quality (reduced fatigue on waking, more refreshed feeling), improved next-day alertness, and significantly improved next-day cognitive performance on tests of attention and reaction time.
A 2007 follow-up by Yamadera, Inagawa and colleagues recorded polysomnography in volunteers who had been experiencing unsatisfactory sleep. The same 3-gram glycine dose improved subjective sleep quality and sleep efficiency and shortened the time both to sleep onset and to slow-wave sleep, without changes in the overall sleep architecture; it also lessened daytime sleepiness and improved performance on memory recognition tasks. A separate 2012 study by Bannai and colleagues (Frontiers in Neurology) cut healthy volunteers' sleep by 25% for three nights: with 3 grams of glycine before bed they reported less fatigue on a visual analogue scale and a questionnaire, and did better on a psychomotor vigilance test the next day (this study used questionnaires and a computer test, not polysomnography).
Bannai and Kawai (2012) summarized the Japanese research program in Journal of Pharmacological Sciences, framing pre-bed glycine as a "new therapeutic strategy" for sleep problems and proposing the core body temperature drop mediated through N-methyl-D-aspartate receptor action on the hypothalamus as the leading mechanistic hypothesis. The Bannai-Kawai paper is the most-cited mechanistic synthesis of the Inagawa work and is the document most clinicians read when first encountering the glycine-sleep evidence base.
The Inagawa trials used pure glycine powder rather than magnesium glycinate, so the dose of glycine delivered (3 grams) is substantially higher than the glycine content of typical magnesium glycinate capsules (which deliver about 250-350 mg of glycine per 400 mg of compound). However, the chelate's magnesium contribution adds parallel sleep-supportive mechanisms (melatonin synthesis, gamma-aminobutyric acid-A potentiation, N-methyl-D-aspartate blockade) that pure glycine does not provide, so the comparison is not a direct dose-equivalence question. Users wanting maximum sleep effect often combine the two.
The 2025 Magnesium Bisglycinate Randomized Controlled Trial
The most important clinical trial specifically of magnesium glycinate for sleep is the 2025 randomized, double-blind, placebo-controlled trial by Schuster and colleagues at Leibniz University Hannover, which enrolled 155 adults aged 18–65 who reported poor sleep and randomized them to either magnesium bisglycinate or placebo for four weeks. The bisglycinate group took two capsules a day, 30–60 minutes before bed, each holding 893 mg of magnesium bisglycinate; together they supplied 250 mg of elemental magnesium and about 1.5 grams of glycine. The primary outcome was the Insomnia Severity Index (ISI); secondary outcomes were other questionnaires on insomnia, sleep quality, fatigue, daytime sleepiness, mood and stress. All outcomes were self-reported — there was no actigraphy or polysomnography.
Results at week 4: the magnesium bisglycinate group's ISI score fell more than the placebo group's (−3.9 vs −2.3 points; p = 0.049), with most of the improvement coming in the first 14 days and sustained thereafter. The authors describe the effect as small (Cohen's d = 0.2), a modest benefit. No significant differences were found in the other psychological outcomes. Exploratory analyses suggested larger improvements among participants who reported lower dietary magnesium intake.
Tolerability was good. Adverse events did not differ significantly between the groups, and no one in the bisglycinate group withdrew because of stomach complaints (two placebo participants withdrew with stomach pain) — a striking contrast to similar trials of magnesium citrate or oxide, in which 10-20% of participants typically drop out due to loose stools. This tolerability profile is one of the practical reasons bisglycinate has displaced other forms in clinical use: a supplement that causes diarrhea will not be taken consistently for the weeks-to-months timeframe required for cumulative sleep benefit.
The trial's 250 mg a day was elemental magnesium, supplied by two 893 mg capsules of magnesium bisglycinate — far more than the 300-400 mg of magnesium glycinate compound (roughly 40-60 mg of elemental magnesium) that many practitioners use for sleep. For comparison, the Institute of Medicine's 1997 Tolerable Upper Intake Level for magnesium from supplements is 350 mg a day for adolescents and adults. The trial measured a small improvement in self-reported insomnia over four weeks and did not test other doses.
Sleep-Specific Comparison: Glycinate vs Threonate vs Malate vs Citrate
For sleep specifically, the choice among magnesium forms is not just a bioavailability question — each form has distinct properties that affect its suitability:
- Magnesium Glycinate (bisglycinate) — the form most directly targeted at sleep applications because of the glycine co-action. Best tolerated, no laxative effect, gentle accumulation effect over weeks. Practitioners commonly describe it as their first choice for chronic sleep-onset and sleep-maintenance insomnia. Fractional absorption is roughly 80%.
- Magnesium L-Threonate — the only magnesium form clinically demonstrated to cross the blood-brain barrier and raise brain magnesium levels (Slutsky et al., 2010, in animal models; partial human confirmation in cognitive trials). Stronger central nervous system (CNS) effect per milligram than glycinate, but expensive, contains less elemental magnesium per dose, and the glycine co-action of glycinate is missing. Practitioners favor it when the primary problem is cognitive impairment, brain fog, or memory complaints alongside sleep. Some users combine L-threonate (200-400 mg in the evening) with magnesium glycinate (300-400 mg at bedtime).
- Magnesium Malate — bound to malic acid, a Krebs cycle intermediate. Practitioners favor it when fatigue and low cellular energy are prominent alongside sleep complaints (fibromyalgia, chronic fatigue). Generally taken in the morning rather than at bedtime because the malate may be mildly energizing. Less specifically sleep-targeted than glycinate.
- Magnesium Citrate — good bioavailability (~30%), but laxative at sleep-relevant doses (300-400 mg). Useful for patients who have both constipation and sleep complaints — one supplement addresses both. Otherwise the loose-stool tendency is undesirable for nighttime dosing.
- Magnesium Oxide — the form practitioners least often use for sleep. Poor bioavailability (~4%) means most of the dose is not absorbed, and the high osmotic load reliably causes a laxative effect.
- Magnesium Taurate — bound to taurine, which has its own anxiolytic and cardioprotective effects. Practitioners describe it as a second choice for sleep in people with cardiac arrhythmia or anxiety, but less well-studied for sleep specifically than glycinate.
For pure sleep-targeted use without other considerations, glycinate is the consensus first-line choice in 2026 integrative practice.
Dosing Protocol for Sleep
The sleep-targeted protocol practitioners describe for adults with normal kidney function:
- Starting dose: 200 mg of magnesium glycinate compound (delivering ~28 mg of elemental magnesium plus ~170 mg of glycine) taken 30-60 minutes before bedtime. This conservative starting dose tests tolerance and personal response.
- Maintenance dose: 300-400 mg of compound, reached after one week if tolerated and if sleep improvement is partial. Most users settle at 300-400 mg. Some go higher (up to 600-800 mg of compound).
- Combining with free glycine. Some users add 1-3 grams of pure glycine powder dissolved in water at the same pre-bedtime dose, close to the 3-gram dose of the Inagawa trials, and describe falling asleep faster. Glycine is sweet-tasting and easily dissolved.
- Nightly use rather than intermittent use is the usual practice. Practitioners describe magnesium status as building over weeks, so the cumulative effect is what they look for.
- Time course. In the four-week 2025 Schuster trial, most of the improvement came within the first 14 days and was sustained thereafter. Practitioners describe allowing 2-4 weeks before judging the effect, rather than the first few nights.
- With or without food. Glycinate is generally well tolerated on an empty stomach; some users take it with a small amount of food when morning grogginess or stomach upset occurs.
- No benefit at 8 weeks. When the maximum tolerated dose for 8 weeks produces no sleep improvement, practitioners take this as a sign that the underlying problem is probably not magnesium-glycine-responsive. Sleep apnea, restless legs syndrome and other sleep disorders are among the other causes of poor sleep; sleep apnea is diagnosed with a sleep study.
For combination with melatonin: the two work together (magnesium supports endogenous melatonin synthesis; supplemental melatonin provides peak signal during the early sleep window). Typical combined protocol is 0.3-1.0 mg of melatonin (the low physiologic doses, not the megadoses) plus 300-400 mg of magnesium glycinate, taken together 30-60 minutes before bed. Higher melatonin doses (3-10 mg) are not more effective for sleep onset and tend to produce next-day grogginess.
Cautions and What to Watch For
- Chronic kidney disease (CKD) — magnesium is cleared by the kidneys. The Institute of Medicine (1997) notes that high blood magnesium (hypermagnesemia) occurs mainly in people with impaired kidney function, most often when they also take excessive non-food magnesium such as antacids. It set the Tolerable Upper Intake Level for magnesium from supplements at 350 mg a day for adolescents and adults, based on diarrhea. Symptoms of magnesium toxicity include muscle weakness, hypotension, bradycardia, and (at extreme levels) cardiac arrest. In healthy kidneys, the body simply excretes the excess.
- Drug interactions with bisphosphonates, levothyroxine, tetracycline / fluoroquinolone antibiotics — magnesium can chelate these drugs in the gut, reducing absorption. The usual practice is to space the doses 2-4 hours apart, and at least 4 hours apart for levothyroxine.
- Initial drowsiness or grogginess — some users experience this for the first few nights, particularly at higher doses. Usually resolves within a week as the body adjusts; users describe lowering the dose when it persists.
- Vivid dreams — reported by a minority of users, likely related to improved REM consolidation when prior insomnia had suppressed REM. Generally regarded as positive (indicates restored normal sleep architecture) but can be unsettling for some.
- Not a substitute for sleep hygiene — magnesium glycinate works best as part of a broader sleep program (dark cool room, consistent bedtime, screens off 60 minutes before bed, no caffeine after noon). Supplement alone against bad sleep hygiene produces underwhelming results.
- Sleep apnea signs — loud snoring, waking up gasping, and pauses in breathing that a bed partner notices are signs of obstructive sleep apnea, which is diagnosed with a sleep study. No supplement treats obstructive sleep apnea; the standard treatments are continuous positive airway pressure (CPAP, a machine that keeps the airway open with air pressure) and oral appliances.
- Product quality when there is no effect at 8 weeks — some products labeled "magnesium glycinate" are actually magnesium oxide buffered with a small amount of glycine. The Bioavailability page describes how to tell a true bisglycinate chelate.
Key Research Papers
- Schuster J, Cycelskij I, Lopresti A, Hahn A (2025). Magnesium bisglycinate supplementation in healthy adults reporting poor sleep: a randomized, placebo-controlled trial. Nature and Science of Sleep 17:2027-2040. — PubMed PMID: 40918053
- Inagawa K et al. (2006). Subjective effects of glycine ingestion before bedtime on sleep quality. Sleep and Biological Rhythms. — PubMed
- Yamadera W, Inagawa K, Chiba S, Bannai M, Takahashi M, Nakayama K (2007). Glycine ingestion improves subjective sleep quality in human volunteers, correlating with polysomnographic changes. Sleep and Biological Rhythms 5(2):126-131. — doi:10.1111/j.1479-8425.2007.00262.x
- Bannai M, Kawai N, Ono K, Nakahara K, Murakami N (2012). The effects of glycine on subjective daytime performance in partially sleep-restricted healthy volunteers. Frontiers in Neurology 3:61. — PubMed PMID: 22529837
- Bannai M, Kawai N (2012). New therapeutic strategy for amino acid medicine: glycine improves the quality of sleep. Journal of Pharmacological Sciences. — PubMed PMID: 22293292
- Abbasi B et al. (2012). The effect of magnesium supplementation on primary insomnia in elderly: a double-blind placebo-controlled clinical trial. Journal of Research in Medical Sciences. — PubMed PMID: 23853635
- Held K et al. (2002). Oral Mg2+ supplementation reverses age-related neuroendocrine and sleep EEG changes in humans. Pharmacopsychiatry. — PubMed PMID: 12163983
- Cao Y et al. (2018). Magnesium intake and sleep disorder symptoms: findings from the Jiangsu Nutrition Study. Nutrients. — PubMed PMID: 30248967
- Slutsky I et al. (2010). Enhancement of learning and memory by elevating brain magnesium. Neuron. (L-threonate context) — PubMed PMID: 20152124
- Wienecke E, Nolden C (2016). Long-term HRV analysis shows stress reduction by magnesium intake. MMW Fortschritte der Medizin. — PubMed PMID: 27933574
- Varga P, Lehoczki A, Fekete M, et al. (2025). The role of magnesium in depression, migraine, Alzheimer's disease, and cognitive health: a comprehensive review. Nutrients 17(13):2216. — PubMed PMID: 40647320
- Kawai N et al. (2015). The sleep-promoting and hypothermic effects of glycine are mediated by NMDA receptors in the suprachiasmatic nucleus. Neuropsychopharmacology. — PubMed PMID: 25533534
PubMed Topic Searches
Connections
- All Minerals
- Magnesium: The Mineral That Makes Adenosine Triphosphate Work — interactive animation
- Magnesium Glycinate Overview
- Magnesium Glycinate Benefits Hub
- Magnesium Glycinate for Anxiety
- Magnesium Glycinate for Muscle Relaxation
- Magnesium Glycinate Bioavailability
- Magnesium (Overview)
- Magnesium for Sleep
- Glycine
- Tryptophan (Melatonin Precursor)
- Insomnia
- Anxiety
- Depression
- Sleep Hygiene
- Stress Management
- Calcium (Magnesium's Counterpart)
- History