⚠ Evidence warning: Clinical trials or other evidence do not support the claim that daily willow bark prevents migraine and chronic tension headache, alone or in a magnesium, riboflavin, coenzyme Q10 and feverfew protocol, or helps break medication-overuse headache: no controlled trial of willow bark for headache has been published, and the 2012 neurology guideline found the data for aspirin in migraine prevention conflicting or inadequate. This page keeps it as a report of what people, websites or other media say.
Willow Bark for Headache and Migraine
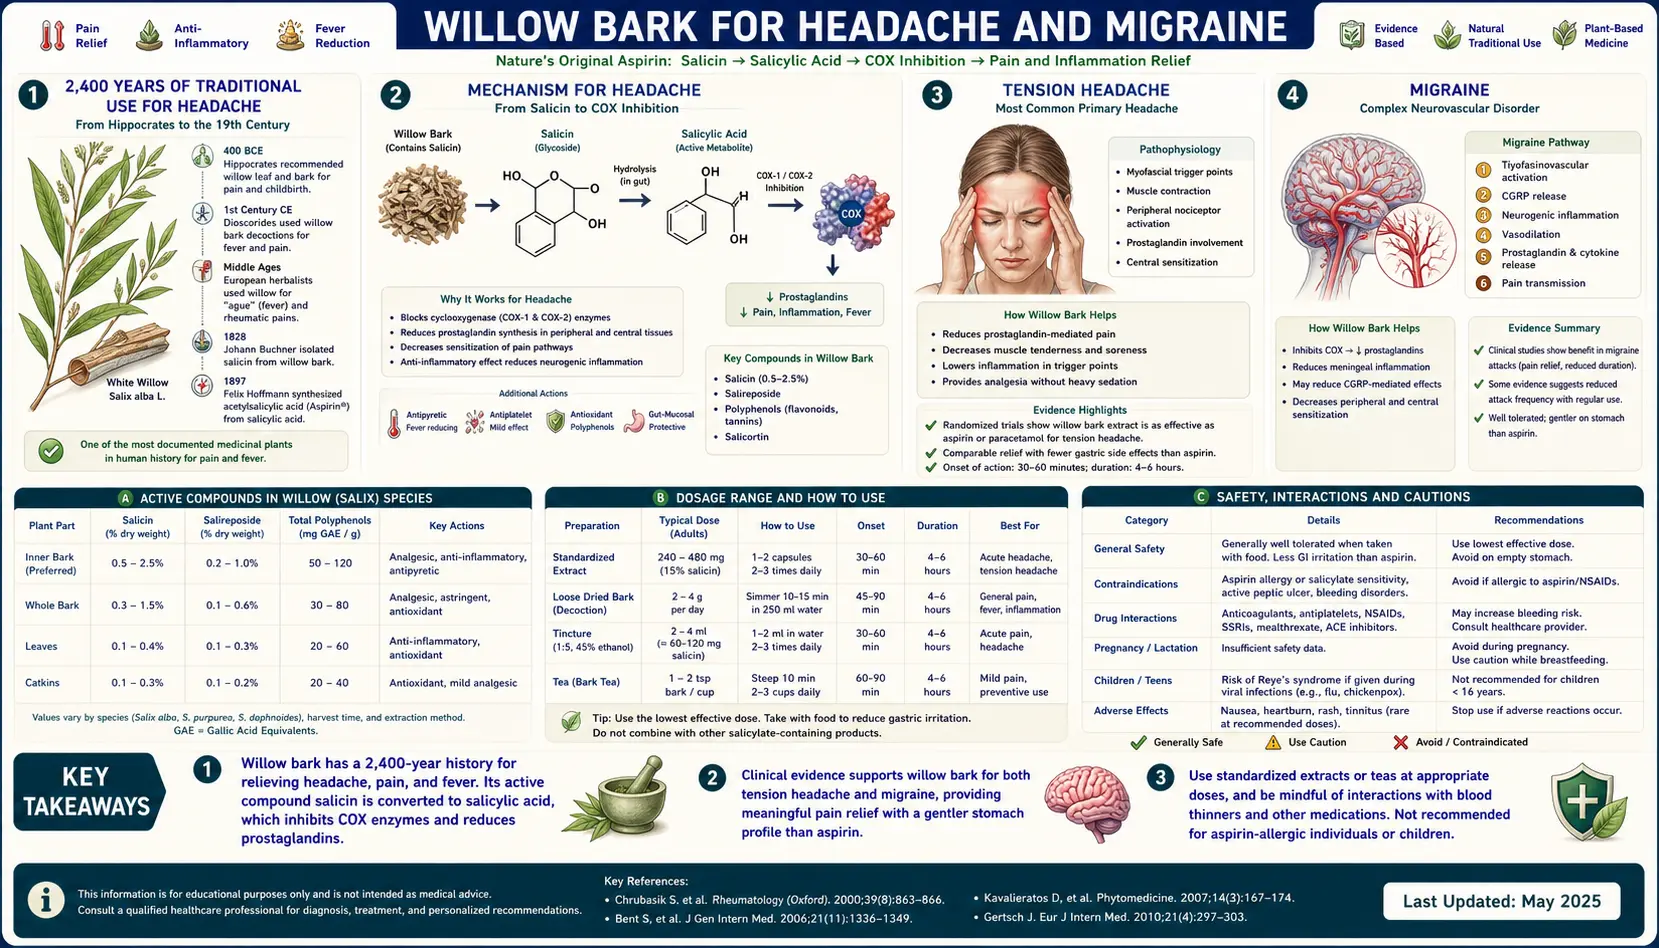
Willow bark has been used as a headache remedy for at least 2,400 years — Hippocrates' "powder of willow" was prescribed for cephalalgia in 5th-century-BCE Greece — and the usual explanation is that salicin-derived salicylic acid produces the same cyclooxygenase inhibition that makes aspirin effective for tension headache, although a 2001 study found that a 240 mg salicin dose yields far less salicylic acid than an analgesic aspirin dose. The catch is timing. Willow's indirect metabolism (intestinal hydrolysis, hepatic oxidation) delays peak blood salicylate to up to 2 hours after dosing, compared with 30-45 minutes for aspirin. For acute headache, this is a meaningful disadvantage. For chronic tension-pattern headache or migraine prophylaxis combined with feverfew, magnesium, and riboflavin, practitioners find willow's longer-duration, gastrointestinal-gentler profile more attractive; willow bark alone has not been tested in a controlled headache trial. This deep-dive walks through traditional use, the limited but encouraging modern pilot data, head-to-head comparison with aspirin and acetaminophen, and how to think about willow bark in modern headache management.
Table of Contents
- 2,400 Years of Traditional Use for Headache
- Mechanism for Headache
- Tension Headache
- Migraine
- Acute Treatment vs Prophylactic Use
- Willow Bark vs Aspirin for Headache
- Willow Bark vs Acetaminophen for Headache
- Combination Protocols for Migraine Prevention
- Medication Overuse Headache
- Dosing for Headache
- Cautions
- Key Research Papers
- Connections
- Featured Videos
2,400 Years of Traditional Use for Headache
Headache is one of the oldest documented indications for willow bark in Western medicine. Hippocrates of Cos (c. 460-370 BCE) recommended willow leaves and willow bark for cephalalgia (headache), gynecological pain in labor, and fever. The Hippocratic prescription — chew the bitter young bark or brew a tea from the powdered older bark — was carried forward by Dioscorides in the 1st century CE and remained a staple of Western herbal medicine through the medieval and early modern periods.
Independent North American ethnobotanical use is well documented: the Cherokee chewed inner willow bark for headache and toothache; the Iroquois Confederacy used Salix nigra (black willow) decoction for headache and fever; the Lenape and other Algonquian peoples used willow preparations for "head pain" and as part of fever-management compresses. The convergent discovery on two continents that willow bark relieves headache is strong evidence the effect is real and substantial — humans across cultures independently identified the same plant for the same purpose without communication.
Edward Stone's 1763 letter to the Royal Society, "An account of the success of the bark of the willow in the cure of agues", described willow bark given to about 50 patients for agues (intermittent fevers), not for headache. By the 19th century, willow bark and isolated salicin were standard analgesics in European pharmacopoeias for headache, fever, and rheumatism. Bayer's 1899 launch of aspirin (acetylsalicylic acid) was marketed heavily as a headache remedy, and aspirin's commercial success cemented salicylates as the dominant first-line headache treatment for the entire 20th century until acetaminophen (paracetamol) emerged as a comparable over-the-counter (OTC) option in the 1950s and the triptans transformed migraine-specific management starting with sumatriptan in 1991.
The historical record makes clear that willow has been used for headache continuously across 2,400 years of Western medicine. Modern willow extract preparations sit at the start of the salicylate analgesic chain that produces aspirin's headache effect — the same downstream mechanism, just with the slower-onset, gentler-on-the-stomach pharmacokinetic profile of the natural glycoside form.
Mechanism for Headache
Most headache pain is mediated by activation of trigeminovascular nociceptive pathways and by sensitization of central pain processing in the spinal trigeminal nucleus and thalamus. Prostaglandins, particularly PGE2 and PGI2 (prostacyclin), are key inflammatory mediators that:
- Sensitize peripheral nociceptors to other algogenic stimuli (kinins, serotonin, histamine), lowering the threshold for pain
- Dilate cerebral and meningeal vessels, contributing to the throbbing component of vascular headache
- Promote release of CGRP (calcitonin gene-related peptide), the principal neurotransmitter mediator of migraine, from trigeminal sensory neurons
- Drive neurogenic inflammation in the dura mater, a key element of migraine pathophysiology
Salicin-derived salicylic acid's cyclooxygenase inhibition reduces prostaglandin synthesis, which interrupts this cascade at several steps. Plus, the willow polyphenol fraction's NF-kappaB inhibition reduces the inflammatory upregulation of cyclooxygenase-2 (COX-2) in stressed brain tissue and reduces secondary cytokine production that amplifies headache pain. The combined effect is a broad-spectrum reduction in headache-relevant inflammatory signaling, similar in mechanism to aspirin but somewhat broader because of the polyphenol contribution discussed in the Anti-Inflammatory deep-dive.
The key clinical caveat is timing. Willow bark's indirect metabolism — intestinal hydrolysis of salicin to saligenin, hepatic oxidation to salicylic acid — brings blood salicylate to its peak within 2 hours (Schmid 2001). Aspirin reaches peak in 30-45 minutes. For acute headache where rapid relief is the priority, aspirin's faster onset is a meaningful advantage. Herbal practitioners regard willow's slower-onset, longer-duration profile as acceptable or even preferable for chronic recurrent headache or for tension-pattern headache that builds slowly.
In an animal headache model, a 2026 rat study found that low doses of parthenolide (from feverfew) plus salicin, given daily, prevented chronic head-pain sensitivity and the rise in calcitonin gene-related peptide (CGRP) in the brainstem pain relay (trigeminocervical complex), in both male and female rats (Shrivastava 2026). These are animal data only.
Tension Headache
Tension-type headache (TTH) is the most common primary headache disorder, affecting 30-78% of adults at some point. Episodic tension headache (less than 15 days per month) and chronic tension headache (15 or more days per month) together account for the substantial majority of headaches in the general population. The pain is typically bilateral, pressing or tightening rather than throbbing, mild to moderate intensity, not aggravated by routine physical activity, and without prominent nausea or photophobia (which would suggest migraine instead).
The pharmacological response of tension headache to nonsteroidal anti-inflammatory drugs (NSAIDs) is well-documented: aspirin 500-1000 mg or ibuprofen 400 mg produces meaningful pain reduction in 50-60% of acute tension headache episodes within 1-2 hours. Acetaminophen 1000 mg has slightly smaller effect but is the preferred choice when nonsteroidal anti-inflammatory drug (NSAID) is contraindicated. The COX-inhibition mechanism is responsible for the analgesic effect.
Modern clinical trials specifically of willow bark for tension headache are limited — the indication has not attracted significant pharmaceutical-industry research interest because aspirin is generic, over-the-counter, fast-acting, and well-established. Practitioners describe willow bark as a slower-onset, gastrointestinal-gentler alternative to chronic nonsteroidal anti-inflammatory drug use for recurrent tension headache, on the reasoning that its salicylic acid acts like aspirin (cyclooxygenase inhibition). The measured amounts differ greatly, though: in a 2001 study of 10 volunteers, willow bark extract providing 240 mg of salicin produced an average peak of 1.2 mg/L of salicylic acid and a total salicylate exposure equal to about 87 mg of aspirin — far lower blood salicylate than analgesic doses of aspirin produce. The authors concluded that salicylic acid alone is unlikely to explain willow bark's pain-relieving effects (Schmid 2001).
Practitioners suggest that for people with chronic tension headache who take a nonsteroidal anti-inflammatory drug or aspirin daily or near-daily, switching to willow bark may reduce gastrointestinal (GI) toxicity and the risk of medication-overuse headache (see below); no trial has tested this. The slower onset of willow makes it less attractive as PRN acute treatment, but as a daily background analgesic for chronic tension headache it works through a sensible mechanism.
Migraine
Migraine is a different clinical entity from tension headache: typically unilateral throbbing pain, moderate to severe intensity, aggravated by routine activity, accompanied by nausea, photophobia, phonophobia, and sometimes preceded by visual or sensory aura. Migraine pathophysiology involves cortical spreading depression, trigeminovascular activation, CGRP release, and meningeal neurogenic inflammation. The triptan class (sumatriptan, rizatriptan, others) and the newer CGRP-receptor antagonists (rimegepant, ubrogepant) target migraine-specific mechanisms and are the most effective acute migraine treatments. The CGRP-antibody class (erenumab, fremanezumab, galcanezumab, eptinezumab) targets migraine prevention.
Nonsteroidal anti-inflammatory drugs and aspirin remain useful in migraine, particularly for mild-to-moderate attacks and as part of combination protocols. Aspirin 900-1000 mg (high dose) has demonstrated efficacy in randomized trials for acute migraine, particularly when combined with metoclopramide for anti-emetic effect and improved gastric absorption. Ibuprofen 600-800 mg has similar evidence.
The role of willow bark in migraine is more limited than in tension headache. The slower onset (up to 2 hours to peak blood salicylate) is a significant disadvantage for acute migraine, where the typical attack reaches peak intensity within 1-2 hours and the patient wants relief immediately. The triptan class produces meaningful relief within 30-60 minutes; even aspirin and ibuprofen at therapeutic doses act faster than willow. Willow bark has not been shown to work for acute moderate-to-severe migraine.
Its proposed role is in migraine prophylaxis: chronic daily preventive treatment intended to reduce attack frequency rather than acute symptom relief. Practitioners use willow bark as an adjunctive component of natural migraine prevention protocols, citing its slower-onset, longer-duration profile and lower gastrointestinal toxicity, particularly combined with magnesium, riboflavin (B2), coenzyme Q10 (CoQ10), and feverfew — see the combination protocols section below, which also gives each component's guideline rating.
For comprehensive migraine information see Migraine.
Acute Treatment vs Prophylactic Use
The acute-vs-prophylactic distinction is central to thinking about willow bark in headache management:
- Acute treatment (PRN dosing at headache onset, intended to abort or relieve the current headache). The relevant pharmacokinetic property is time-to-peak plasma concentration. Aspirin (30-45 min), ibuprofen (1-2 hr), and the triptans (30-60 min for oral, 10-15 min for subcutaneous sumatriptan) reach peak at or before the time willow bark does (within 2 hr). For acute treatment, willow is generally not first-line.
- Prophylactic / preventive treatment (daily dosing intended to reduce attack frequency or severity over weeks-to-months). The relevant pharmacokinetic property is steady-state plasma concentration with daily dosing, not time-to-peak. Willow bark dosed daily at 240 mg salicin reaches stable plasma salicylate within 2-3 days and maintains it indefinitely with continued use. Practitioners regard its gastrointestinal tolerability and its much weaker antiplatelet effect as advantages for chronic use: in a randomized study, 240 mg salicin a day reduced arachidonic-acid-induced platelet clumping only modestly (61% maximal aggregation vs 78% on placebo), far less than 100 mg aspirin a day (13%) (Krivoy 2001).
The integrative headache-management approach that practitioners describe has four steps:
- Identifying the headache pattern (episodic tension, chronic tension, episodic migraine, chronic migraine, mixed)
- For acute headache, a fast-onset agent matched to the headache type (aspirin or ibuprofen for tension headache; triptan for moderate-to-severe migraine; combination triptan + nonsteroidal anti-inflammatory drug for refractory acute migraine)
- For headache prevention (chronic tension headache or frequent migraine), willow bark as part of a daily prophylactic regimen alongside other natural preventive agents (practitioner use; not tested in controlled trials)
- Keeping acute-medication days low, since frequent use causes medication-overuse headache (see below)
Willow Bark vs Aspirin for Headache
For acute headache, aspirin has clear advantages over willow bark:
- Faster onset (30-45 minutes versus up to 2 hours)
- Higher peak plasma salicylate (20-50 µg/mL after a typical 500-1000 mg aspirin dose, versus an average peak of 1.2 mg/L, the same as 1.2 µg/mL, after willow bark extract providing 240 mg salicin — a total salicylate exposure equal to about 87 mg of aspirin; Schmid 2001)
- More potent acute cyclooxygenase-1 (COX-1) and cyclooxygenase-2 inhibition
- Well-established clinical trial evidence for both tension headache and acute migraine
For chronic daily headache prophylaxis, the calculus shifts somewhat:
- Willow has substantially lower gastrointestinal toxicity than chronic daily aspirin. The risk of gastric ulceration and gastrointestinal bleeding is the principal limit on chronic aspirin use.
- Willow produces much weaker platelet inhibition than aspirin (arachidonic-acid-induced aggregation 61% on 240 mg salicin a day vs 13% on 100 mg aspirin and 78% on placebo; Krivoy 2001), which is an advantage for patients who need to maintain normal coagulation but a disadvantage for patients who have cardiovascular comorbidities where aspirin's antiplatelet effect is desired. See the Cardiovascular & Aspirin Comparison deep-dive.
- Both equally produce the salicylate Reye-syndrome risk in children — willow is NOT a "safer" salicylate for pediatric use during viral illness.
- Willow's polyphenol fraction may add modest additional anti-inflammatory benefit beyond aspirin's pure COX inhibition; the Schmid 2001 authors concluded that salicylic acid alone is unlikely to explain willow bark's pain relief, which leaves room for other constituents such as this fraction.
For acute migraine the trial evidence for aspirin is strong: a Cochrane review of 13 trials (4,222 people) found aspirin 900-1000 mg about as effective as sumatriptan 50 mg for 2-hour pain freedom and headache relief, and adding metoclopramide 10 mg reduced nausea and vomiting compared with aspirin alone (Kirthi 2013).
In summary: aspirin has the trial evidence for acute headache treatment in adults without contraindications. Willow bark is used by practitioners for chronic prophylactic use, particularly when chronic nonsteroidal anti-inflammatory drug gastrointestinal toxicity is a concern, without controlled headache trials.
Willow Bark vs Acetaminophen for Headache
Acetaminophen (paracetamol) is the other common over-the-counter headache analgesic and is mechanistically quite different from both willow bark and aspirin. Acetaminophen produces analgesic and antipyretic effect through central nervous system mechanisms that are only partially understood — it weakly inhibits central nervous system (CNS) cyclooxygenase (particularly the COX-3 splice variant in brain), activates descending serotonergic and cannabinoid analgesic pathways, and modulates the spinal nociceptive transmission. It is NOT a significant peripheral COX inhibitor and has essentially no anti-inflammatory effect at clinical doses.
Key clinical differences:
- Acetaminophen has no anti-inflammatory effect. For pure tension headache (which is not significantly inflammatory), this matters less. For migraine (which involves substantial neurogenic inflammation), willow's anti-inflammatory action provides additional mechanism not addressed by acetaminophen.
- Acetaminophen is safer in pregnancy than willow or aspirin, particularly in the third trimester. Acetaminophen is the standard-of-care analgesic in pregnancy for both headache and other pain.
- Acetaminophen lacks willow's gastrointestinal side effects entirely (no cyclooxygenase-1 inhibition, no gastric mucosal effects).
- Acetaminophen has hepatotoxicity at doses above 4000 mg/day or with alcohol use. Willow bark has minimal hepatotoxic potential at therapeutic doses.
- Acetaminophen lacks willow's polyphenol fraction — no NF-kappaB inhibition, no tumor necrosis factor-alpha suppression, no antioxidant benefit.
For acute tension headache in non-pregnant adults, acetaminophen and willow bark produce roughly comparable analgesic effect with different side effect profiles. For migraine, the anti-inflammatory mechanism gives willow a modest theoretical edge over acetaminophen. For pregnancy and breastfeeding, acetaminophen is preferred.
Combination Protocols for Migraine Prevention
Practitioners add willow bark to multi-component natural migraine prevention protocols, where the goal is reducing attack frequency by 50% or more over 3-6 months of daily use. The components, with the rating each received in the 2012 American Academy of Neurology / American Headache Society guideline on complementary treatments for episodic migraine prevention (Holland 2012):
- Magnesium (typically magnesium glycinate or magnesium citrate, 300-600 mg elemental daily). Multiple randomized controlled trials (RCTs) support magnesium for migraine prevention, with effect size of 20-40% attack frequency reduction over placebo. Rated "probably effective" (Level B) in the 2012 guideline. See Magnesium.
- Riboflavin (Vitamin B2) (400 mg daily). In the 1998 Schoenen trial (55 patients, 3 months), 59% of patients on riboflavin cut their headache days by at least half, versus 15% on placebo. Rated "probably effective" (Level B) by the 2012 American Academy of Neurology / American Headache Society guideline.
- Coenzyme Q10 (100 mg three times daily, total 300 mg daily). The 2005 Sandor trial showed 50% reduction in migraine frequency in 47.6% of patients versus 14.4% of placebo controls over 3 months. Rated "possibly effective" (Level C) in the 2012 guideline.
- Feverfew (Tanacetum parthenium, 100-300 mg standardized extract daily). Older trials showed modest preventive effect; meta-analyses are mixed but suggest a small-to-moderate preventive benefit. The 2012 guideline rated one feverfew extract, MIG-99, "probably effective" (Level B).
- Willow bark (240 mg salicin daily) is added by practitioners on top of the above as a daily background of anti-inflammatory action via COX inhibition + polyphenol effects, particularly when the person also has chronic mechanical pain (back, joints). Willow bark itself was not rated; for aspirin, the 2012 guideline found the data "conflicting or inadequate to support or refute" its use for migraine prevention.
The combination regimen practitioners describe is magnesium glycinate 400 mg + riboflavin 400 mg + coenzyme Q10 300 mg + feverfew 200 mg + willow bark extract delivering 240 mg salicin, all taken daily, with response judged after 3 months of consistent use. Trial evidence exists for several components individually (above); for willow within a combination it is limited to the small open-label study below.
The only human headache study involving willow found in a PubMed search was a 2006 open-label study with no placebo group: 12 people with migraine without aura took feverfew 300 mg plus white willow 300 mg twice daily for 12 weeks. Attack frequency fell by 61.7% at 12 weeks (a fall seen in nine of the ten who finished), 70% had a drop of at least half, and no adverse events occurred. The authors called for a double-blind, placebo-controlled trial in a larger group (Shrivastava 2006).
For comprehensive non-pharmacologic migraine management see Migraine.
Medication Overuse Headache
Medication overuse headache (MOH, formerly called "rebound headache") is a real and underrecognized complication of frequent acute headache medication use. It occurs when acute medications taken too often (under the International Classification of Headache Disorders, 3rd edition: on 15 or more days a month for simple pain relievers such as aspirin, acetaminophen or nonsteroidal anti-inflammatory drugs, and on 10 or more days a month for triptans, ergotamines, opioids or combination analgesics, for more than 3 months) themselves induce chronic daily headache.
The mechanism involves central nervous system sensitization, downregulation of endogenous antinociceptive pathways, and rebound vasodilation as the medication wears off. Patients caught in this cycle often increase medication frequency to chase relief, worsening the underlying MOH problem.
Willow bark's role in this context is dual:
- Risk: Daily willow bark used as acute treatment for daily headache can contribute to MOH similarly to daily aspirin or nonsteroidal anti-inflammatory drug use. The salicylate exposure is real.
- Proposed mitigation (practitioner view, not tested in trials): Daily willow bark used for headache PREVENTION (as part of a prophylactic regimen) rather than for acute symptom relief allows reduction in acute medication days, which can break the MOH cycle.
The approach practitioners describe: willow bark as a daily prophylactic agent (combined with the magnesium / riboflavin / coenzyme Q10 / feverfew preventive stack), with specific fast-onset agents (triptans for migraine, ibuprofen for tension headache) kept for acute breakthrough symptoms, and acute-medication days kept below the overuse thresholds above (fewer than 10 days a month stays under the threshold for every drug class).
Dosing for Headache
- For acute tension headache: 240 mg salicin (typically one or two standardized extract capsules). Onset is slow (1-2 hours for partial effect; blood salicylate peaks within 2 hours). Too slow for most acute migraine attacks.
- For chronic tension headache prophylaxis: 240 mg salicin daily, taken at the same time each day with food. Effect builds over 2-4 weeks.
- For migraine prophylaxis (as part of combination protocol): 240 mg salicin daily, combined with magnesium, riboflavin, coenzyme Q10, and feverfew as in the practitioner protocol above, with response judged after three months.
- For migraine acute treatment: Willow is NOT first-line. The treatments with trial evidence are triptans and aspirin or other nonsteroidal anti-inflammatory drugs, with metoclopramide for nausea (Kirthi 2013). Willow may be useful as add-on in mild attacks but is too slow-onset for primary acute use.
- Combining with other natural headache agents: Magnesium, riboflavin, coenzyme Q10, and feverfew all have favorable interaction profiles with willow. Glycine 3-5 g at bedtime is described by practitioners as supporting the glycine-conjugation elimination pathway (salicylic acid from willow is cleared mainly as salicyluric acid, its glycine conjugate; Schmid 2001).
Cautions
- Reye syndrome in children with viral illness — absolute pediatric contraindication. Salicylates given to children with febrile viral illness (especially influenza, chickenpox) are linked to Reye syndrome, and this applies to willow bark for headache or any other indication.
- Salicylate allergy / aspirin-exacerbated respiratory disease (AERD) — absolute contraindication. Patients with aspirin-sensitive asthma will cross-react with willow.
- Acute severe headache with red flags — sudden severe "thunderclap" headache, headache with fever and neck stiffness, headache with focal neurologic findings, headache after head trauma, or new headache after age 50 are signs hospitals treat as urgent; herbal therapy does not address their causes. Willow's traditional use is for benign primary headache disorders such as tension-type headache and migraine.
- Migraine with aura and stroke risk — women with migraine with aura have modestly elevated stroke risk. Willow does not provide aspirin's antiplatelet cardioprotection, so its use is not cardiovascular protection for this group.
- Anticoagulants — additive bleeding risk with warfarin, clopidogrel and direct oral anticoagulants (DOACs). Important consideration for older headache patients on cardiovascular medications.
- Concurrent nonsteroidal anti-inflammatory drug use — willow plus ibuprofen / naproxen / diclofenac on the same day stacks two cyclooxygenase-inhibiting agents.
- Pregnancy — salicylates carry pregnancy concerns, particularly in the third trimester, and acetaminophen is the headache analgesic usually preferred during pregnancy.
- Medication overuse headache — willow used too frequently for acute headache can contribute to MOH; counting acute-medication days is how overuse is recognized.
- Tinnitus — high-dose salicylates produce reversible tinnitus. Ringing in the ears is a sign of salicylate excess and fades when the dose is lowered.
Key Research Papers
- Diener HC et al. (2005). Efficacy and safety of 6.25 mg t.i.d. feverfew CO2-extract (MIG-99) in migraine prevention — a randomized, double-blind, multicentre, placebo-controlled study. Cephalalgia. — PubMed PMID: 16232154
- Schoenen J et al. (1998). Effectiveness of high-dose riboflavin in migraine prophylaxis. A randomized controlled trial. Neurology. — PubMed PMID: 9484373
- Sandor PS et al. (2005). Efficacy of coenzyme Q10 in migraine prophylaxis: a randomized controlled trial. Neurology. — PubMed PMID: 15728298
- Diener HC et al. (2005). The fixed combination of acetylsalicylic acid, paracetamol and caffeine is more effective than single substances and dual combination for the treatment of headache: a multicentre, randomized, double-blind, single-dose, placebo-controlled parallel group study. Cephalalgia, 25(10):776-787. — PubMed PMID: 16162254
- Lipton RB et al. (1998). Efficacy and safety of acetaminophen, aspirin, and caffeine in alleviating migraine headache pain: three double-blind, randomized, placebo-controlled trials. Archives of Neurology, 55(2):210-217. — PubMed PMID: 9482363
- Kirthi V et al. (2013). Aspirin with or without an antiemetic for acute migraine headaches in adults. Cochrane Database of Systematic Reviews. — PubMed PMID: 23633350
- Mauskop A, Varughese J (2012). Why all migraine patients should be treated with magnesium. Journal of Neural Transmission, 119(5):575-579. — PubMed PMID: 22426836
- Chrubasik S et al. (2000). Treatment of low back pain exacerbations with willow bark extract: a randomized double-blind study. American Journal of Medicine, 109(1):9-14. — PubMed PMID: 10936472
- Pareek A et al. (2011). Feverfew (Tanacetum parthenium L.): A systematic review. Pharmacognosy Reviews, 5(9):103-110. — PubMed PMID: 22096324
- Vlachojannis JE et al. (2009). A systematic review on the effectiveness of willow bark for musculoskeletal pain. Phytotherapy Research. — PubMed PMID: 19140170
- Headache Classification Committee of the International Headache Society (2018). The International Classification of Headache Disorders, 3rd edition. Cephalalgia, 38(1):1-211. — PubMed PMID: 29368949
- Diener HC, Limmroth V (2004). Medication-overuse headache: a worldwide problem. Lancet Neurology. — PubMed PMID: 15261608
- Holland S et al. (2012). Evidence-based guideline update: NSAIDs and other complementary treatments for episodic migraine prevention in adults: report of the Quality Standards Subcommittee of the American Academy of Neurology and the American Headache Society. Neurology, 78(17):1346-1353. — PubMed PMID: 22529203
- Schmid B et al. (2001). Pharmacokinetics of salicin after oral administration of a standardised willow bark extract. European Journal of Clinical Pharmacology, 57(5):387-391. — PubMed PMID: 11599656
- Krivoy N et al. (2001). Effect of salicis cortex extract on human platelet aggregation. Planta Medica, 67(3):209-212. — PubMed PMID: 11345689
- Shrivastava R et al. (2006). Tanacetum parthenium and Salix alba (Mig-RL) combination in migraine prophylaxis: a prospective, open-label study. Clinical Drug Investigation, 26(5):287-296. — PubMed PMID: 17163262
- Shrivastava R et al. (2026). Association of parthenolide and salicin as a preventive treatment on a migraine model induced by dural inflammatory soup application. Pain, 167(2):297-307. — PubMed PMID: 41512309
- Stone E (1763). An account of the success of the bark of the willow in the cure of agues. Philosophical Transactions of the Royal Society of London, 195-200. — doi:10.1098/rstl.1763.0033
PubMed Topic Searches
Connections
- All Herbs
- Willow Bark Overview
- Willow Bark Benefits Hub
- Willow Bark for Pain Management
- Willow Bark Anti-Inflammatory
- Cardiovascular & Aspirin Comparison
- Headache
- Migraine
- Migraine (Neurology)
- Aspirin
- Pain Management
- Magnesium
- Glycine
- Glycine & Aspirin Metabolism
- Turmeric
- Ginger
- Chronic Pain
- Tension Headache — the headache type willow bark suits best, since its COX-inhibition mechanism matches the aspirin response documented for TTH.
- History