Willow Bark for Pain Management
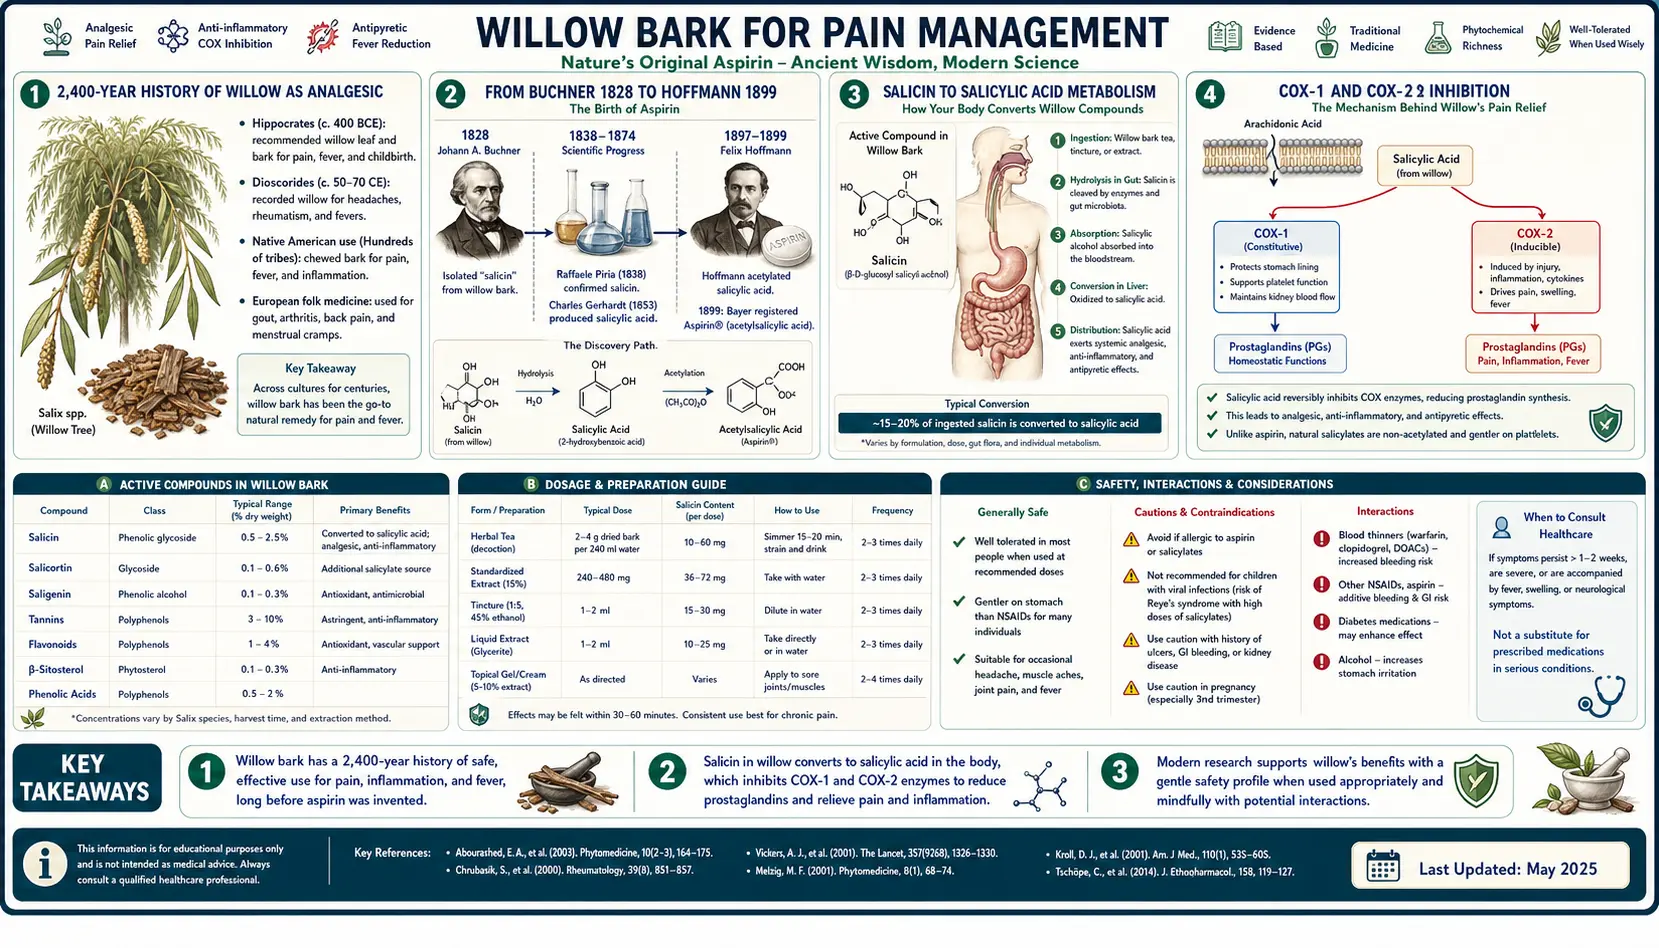
Willow bark is the original Western analgesic — a 2,400-year-old remedy whose active constituent, the glycoside salicin, was isolated by Johann Buchner in Munich in 1828; in 1897 Felix Hoffmann at Bayer acetylated salicylic acid (made from meadowsweet rather than willow bark) into acetylsalicylic acid, launched as aspirin in 1899. The pharmacology is now well-mapped at the molecular level: salicin is hydrolyzed in the gut to saligenin, oxidized in the liver to salicylic acid, and the salicylic acid inhibits cyclooxygenase-1 and cyclooxygenase-2 to reduce prostaglandin synthesis. The Chrubasik 2000 and 2001 low back pain trials and the Schmid 2001 osteoarthritis trial used 240 mg of salicin daily: willow beat placebo in low back pain and did not differ significantly from the anti-inflammatory drug rofecoxib in an open-label comparison, while in osteoarthritis a 2-week trial found a moderate effect and a later 6-week trial (Biegert 2004) found none, with the nonsteroidal anti-inflammatory drug (NSAID) diclofenac clearly more effective. This deep-dive walks through the mechanism, the pivotal clinical trials, how willow compares to ibuprofen and aspirin for musculoskeletal pain, and the practical question of where it fits in modern integrative pain management.
Table of Contents
- The 2,400-Year History of Willow as Analgesic
- From Buchner 1828 to Aspirin 1899
- Salicin → Salicylic Acid Metabolism
- Cyclooxygenase-1 and Cyclooxygenase-2 Inhibition
- Chrubasik 2000 and 2001 — Low Back Pain Trials
- Schmid 2001 — Osteoarthritis Trial
- Willow Bark vs Aspirin
- Willow Bark vs Ibuprofen
- Dosing for Pain Management
- Integrative Pain-Management Protocols
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The 2,400-Year History of Willow as Analgesic
Willow bark is one of the oldest documented analgesics in Western medicine. The Ebers Papyrus of ancient Egypt, dated approximately 1550 BCE, recommends willow leaves for inflammation and pain — making the herb's use as a medicine at least 3,500 years old. Hippocrates, writing in the 5th century BCE, prescribed willow bark and willow leaves for fever and for women in labor; his "powder of willow" is among the earliest documented Western analgesic prescriptions. Pedanius Dioscorides, the Greek physician whose 1st-century CE De Materia Medica remained the standard pharmacopoeia of Europe and the Near East for over 1,500 years, included willow as a remedy for pain, fever, and inflammation.
On the other side of the Atlantic, the Cherokee, Iroquois, Lenape, and Anishinaabe peoples independently developed analgesic preparations from species of native North American willow (Salix nigra, the black willow, and Salix discolor, the pussy willow). The inner bark was typically chewed fresh for headache, toothache, and muscle pain, or simmered as a decoction for fever and arthritis. This convergent ethnobotanical discovery on two continents is itself evidence that the active analgesic compound is real and substantial — humans across cultures independently identified the same plant as effective.
The first published Western scientific report of willow as a fever remedy came from English clergyman Edward Stone in 1763. Stone, who was rector of the parish of Chipping Norton in Oxfordshire, presented to the Royal Society a clinical report describing successful treatment of fever (likely malaria, the "ague" common in marshy English country in that era) in approximately 50 patients with dried, powdered willow bark. His paper, "An Account of the Success of the Bark of the Willow in the Cure of Agues," is the moment willow transitioned from folk medicine to systematically investigated drug.
From Buchner 1828 to Aspirin 1899
The active principle of willow bark was isolated in 1828 by Johann Andreas Buchner, professor of pharmacy at the University of Munich. Buchner extracted a bitter yellow crystalline glycoside from willow bark, which he named salicin — from the Latin Salix, the botanical genus of willow. Henri Leroux, a French pharmacist, refined the extraction in 1829 and produced larger quantities; the Italian chemist Raffaele Piria succeeded in 1838 in hydrolyzing salicin to its bitter alcohol component (saligenin) and then oxidizing it to the much sweeter and more chemically stable salicylic acid. By the 1860s, salicylic acid was being synthesized industrially from phenol and used as an analgesic and antipyretic. The German chemist Hermann Kolbe developed the first practical synthesis (the Kolbe-Schmitt reaction, still in commercial use), and Friedrich von Heyden began commercial production of salicylic acid in Dresden in 1874.
The problem with pure salicylic acid as an oral medication was severe gastric irritation. It is a fairly strong organic acid (pKa around 3.0), and direct contact with the gastric mucosa produces nausea, dyspepsia, and ulceration. By the 1890s, this had become a barrier to widespread clinical use. The breakthrough came in 1897 in the Bayer laboratory in Elberfeld, Germany, where the young chemist Felix Hoffmann — reportedly motivated by his father's rheumatic pain and the latter's intolerance of pure salicylic acid — succeeded in producing a stable acetylated derivative. By replacing the hydroxyl-group hydrogen with an acetyl group (CH₃CO–), Hoffmann produced acetylsalicylic acid, a compound that was much less acidic, far better tolerated orally, and yet hydrolyzed back to active salicylic acid (plus free acetate) in plasma after absorption.
Bayer trademarked the new product as Aspirin — from "A" (for acetyl) + "spir" (for Spiraea, an alternative botanical source of salicylates) + "in" (a standard pharmaceutical suffix). Aspirin was launched commercially in 1899 and within five years was the most widely used drug in the world. The chain of discovery is one of the cleanest examples in pharmaceutical history of a path from folk remedy (chewing willow bark) to identified natural product (salicin, 1828) to active metabolite (salicylic acid, 1838) to chemically modified pharmaceutical (aspirin, 1899) — spanning 71 years of work by chemists in four countries.
Modern willow bark preparations sit at the start of this chain: they retain the analgesic and anti-inflammatory benefits of the salicylate parent compounds, with substantially lower gastrointestinal (GI) toxicity than aspirin (because the glycoside is not hydrolyzed until after absorption) and a different antiplatelet profile (because the acetyl group is not present — see the Cardiovascular & Aspirin Comparison deep-dive).
Salicin → Salicylic Acid Metabolism
The pharmacokinetic path from a swallowed willow bark capsule to circulating salicylic acid is well-characterized:
- Intestinal hydrolysis. Salicin (a beta-D-glucoside) reaches the small intestine intact — it is too polar for significant gastric absorption. In the small intestine and (more importantly) the cecum, bacterial and brush-border beta-glucosidase enzymes hydrolyze the glycosidic bond, releasing free saligenin (also called salicyl alcohol, 2-hydroxybenzyl alcohol) plus glucose.
- Absorption. Saligenin is far less polar than salicin and is absorbed across the intestinal mucosa into the portal circulation.
- Hepatic oxidation. In the liver, alcohol dehydrogenase oxidizes saligenin's benzyl alcohol group to a carboxylic acid, producing salicylic acid. This is the same active compound produced by aspirin hydrolysis in plasma, but generated in the liver rather than in plasma.
- Distribution and elimination. Salicylic acid distributes broadly, reached peak serum levels within less than 2 hours of an oral dose of willow bark extract in a pharmacokinetic study (Schmid 2001; compared to 30-45 minutes for aspirin), and is conjugated by the liver to salicyluric acid (glycine conjugate, see Glycine & Aspirin Metabolism), salicylphenolic glucuronide, and salicylacyl glucuronide. The glycine conjugation pathway is the same dose-limiting elimination step that applies to aspirin and which makes glycine a relevant supplemental amino acid for salicylate metabolism.
The clinically important consequence of the indirect metabolism is that plasma salicylic acid concentrations after a therapeutic willow bark dose (240 mg salicin) are much lower than after a therapeutic aspirin dose (500 mg) — typically 1-3 µg/mL versus 20-50 µg/mL. Despite this, standardized willow extract did not differ significantly from rofecoxib in an open-label low back pain trial (Chrubasik 2001), although diclofenac clearly outperformed it in osteoarthritis (Biegert 2004). Schmid and colleagues concluded that the formation of salicylic acid alone is unlikely to explain willow bark's analgesic effects, which suggests that the polyphenol and flavonoid fraction of the whole-bark extract contributes additional anti-inflammatory action beyond what salicin alone would produce. See the Anti-Inflammatory deep-dive for the "whole-herb advantage" hypothesis.
Cyclooxygenase-1 and Cyclooxygenase-2 Inhibition
The molecular endpoint of willow bark analgesia is inhibition of the cyclooxygenase enzymes that convert arachidonic acid to prostaglandins. There are two principal isoforms with somewhat different physiologic roles:
- Cyclooxygenase-1 (COX-1) is constitutively expressed in most tissues, including platelets, gastric mucosa, and renal tubular cells. Cyclooxygenase-1-derived prostaglandins maintain gastric mucus production, support platelet aggregation through thromboxane A2 synthesis, and regulate renal blood flow.
- Cyclooxygenase-2 is largely inducible — it is upregulated by inflammatory stimuli (cytokines, growth factors, endotoxin) at sites of injury and inflammation. Cyclooxygenase-2-derived prostaglandins drive pain sensitization, fever, and the cardinal signs of acute inflammation.
Salicylic acid is a non-selective competitive inhibitor of both cyclooxygenase-1 and cyclooxygenase-2 — it binds reversibly in the active site cleft. This contrasts with aspirin's irreversible covalent acetylation of serine-529 in the cyclooxygenase-1 active site, which is what gives aspirin its uniquely durable antiplatelet effect. Willow-derived salicylic acid produces effective COX inhibition during the period when plasma concentration is above the inhibitory threshold, but the effect dissipates as the drug is cleared — there is no permanent enzyme modification.
The clinical translation is that willow bark's salicylate has only modest and reversible platelet effects. At 240 mg of salicin daily — the dose used in the pain trials — it does not achieve the durable platelet inhibition that low-dose aspirin (81 mg) produces in the cardioprotective context. This distinction is repeatedly important — see the dedicated Cardiovascular & Aspirin Comparison deep-dive.
Chrubasik 2000 and 2001 — Low Back Pain Trials
The pivotal modern trial of willow bark for chronic low back pain was published by Sigrun Chrubasik and colleagues in the American Journal of Medicine in 2000. Chrubasik randomized 210 patients with acute exacerbations of chronic low back pain to one of three groups: a low-dose willow bark extract delivering 120 mg of salicin daily, a high-dose willow bark extract delivering 240 mg of salicin daily, or placebo. Patients were assessed weekly over four weeks, with the principal endpoint being the proportion achieving freedom from pain in the last five days of treatment without rescue analgesia.
The results were striking:
- Placebo: 4 of 59 patients (6%) achieved the primary endpoint.
- 120 mg salicin/day: 15 of 67 patients (21%) achieved the primary endpoint.
- 240 mg salicin/day: 27 of 65 patients (39%) achieved the primary endpoint.
A total of 191 of the 210 patients completed the study.
Both willow groups outperformed placebo with statistical significance, and the high-dose group outperformed the low-dose group, demonstrating a clean dose-response relationship. The numbers-needed-to-treat from this trial (NNT around 3 for the 240 mg dose compared to placebo) compare favorably with most pharmaceutical analgesics for chronic low back pain. The response in the high-dose group was evident after only 1 week of treatment. One patient had a severe allergic reaction, perhaps to the extract; the authors concluded that willow bark extract “may be a useful and safe treatment for low back pain.”
A subsequent trial by Chrubasik in 2001 compared 240 mg/day salicin willow extract head-to-head with rofecoxib 12.5 mg/day (a then-marketed selective cyclooxygenase-2 inhibitor, since withdrawn from the market for cardiovascular safety reasons unrelated to the willow comparison) in 228 patients (114 per group) with acute exacerbations of low back pain over four weeks. In this open-label (unblinded) randomized post-marketing study, there was no significant difference in effectiveness between the two treatments, and the incidence of adverse events was similar in the two groups.
Gagnier's 2007 Cochrane review (Spine) rated the evidence for white willow bark in low back pain as moderate, behind Devil's claw (Harpagophytum procumbens), whose two high-quality trials gave strong evidence. Vlachojannis's 2009 systematic review (Phytotherapy Research) found moderate evidence for ethanolic willow bark extract in low back pain and conflicting results in osteoarthritis; the trials it covered used daily doses of up to 240 mg salicin for up to six weeks.
Schmid 2001 — Osteoarthritis Trial
Schmid and colleagues published in 2001 a randomized double-blind placebo-controlled trial of standardized willow bark extract for osteoarthritis of the hip or knee. Seventy-eight patients with WOMAC-stage moderate osteoarthritis were randomized to either a willow extract delivering 240 mg of salicin daily or placebo, over two weeks. The primary endpoint was the WOMAC (Western Ontario and McMaster Universities) pain score.
The willow group experienced a 14% reduction in WOMAC pain score versus a 2% increase in the placebo group — a modest but statistically significant difference (p = 0.047). Total WOMAC index (combining pain, stiffness, and function) improved 15% versus 4%. The trial lasted only 2 weeks. The one longer, 6-week osteoarthritis trial that followed (Biegert 2004, below) found willow no better than placebo, and Vlachojannis's 2009 review described the osteoarthritis results as conflicting.
A longer-duration trial by Biegert and colleagues (Journal of Rheumatology, 2004) compared willow bark extract (240 mg salicin/day) with diclofenac (a standard nonsteroidal anti-inflammatory drug, 100 mg/day) and with placebo in 127 osteoarthritis patients over six weeks. WOMAC pain scores fell by 8 mm (17%) with willow bark, 23 mm (47%) with diclofenac and 5 mm (10%) with placebo. The difference between willow and placebo was not statistically significant (p = 0.55), while the difference between diclofenac and placebo was (p = 0.0002). The authors concluded that the extract “showed no relevant efficacy” in osteoarthritis, and a companion trial in 26 people with rheumatoid arthritis did not indicate efficacy either. Taken together, the osteoarthritis evidence is mixed: one 2-week trial found a moderate effect, and the longer 6-week trial found none.
In integrative practice, willow bark is often combined for osteoarthritis with turmeric, ginger, glucosamine sulfate, and structured weight-bearing exercise. Practitioners describe such combinations as a way to reduce daily nonsteroidal anti-inflammatory drug use; the trials above tested willow bark on its own.
Willow Bark vs Aspirin
The differences between willow bark and aspirin are subtle but clinically important:
- Onset of action. Aspirin (after oral dosing) achieves peak plasma salicylate within 30-45 minutes. Willow bark requires intestinal hydrolysis and hepatic oxidation, so peak salicylate comes later — within less than 2 hours in a pharmacokinetic study of willow extract. For acute pain, aspirin is faster; for chronic pain management, the onset difference is irrelevant.
- Gastrointestinal toxicity. Aspirin's direct gastric mucosal contact produces dyspepsia, gastric ulceration, and gastrointestinal bleeding at meaningful rates, even at low doses. Willow bark's glycoside form is essentially inert in the stomach — gastric mucosa is never exposed to free salicylate — so gastrointestinal toxicity is dramatically lower. This is the principal practical advantage of willow over aspirin for chronic daily use.
- Antiplatelet effect. Aspirin's irreversible acetylation of platelet cyclooxygenase-1 produces durable (7-10 day) platelet inhibition. Willow bark's reversible competitive COX inhibition does not produce comparable durable effect. Willow does not substitute for aspirin in secondary cardiovascular prevention — see the dedicated Cardiovascular & Aspirin Comparison deep-dive.
- Reye syndrome. Both aspirin and willow bark are contraindicated in children with viral illness. Willow is not a "safer" salicylate — the active downstream metabolite is identical.
- Polyphenol co-effect. Willow bark's flavonoid and proanthocyanidin fraction adds COX-independent anti-inflammatory action. Aspirin is pure acetylsalicylic acid with no such co-constituents.
In summary: aspirin acts faster and has a far stronger antiplatelet effect; willow is gentler on the stomach for chronic use and may offer broader anti-inflammatory action through its polyphenol matrix. Aspirin's effect on acute pain and fever is the better established of the two; the willow trials studied chronic musculoskeletal pain, where lower gastrointestinal toxicity is the main point of difference.
Willow Bark vs Ibuprofen
Ibuprofen (a non-acetylated propionic acid nonsteroidal anti-inflammatory drug) is the most commonly used over-the-counter analgesic in the United States and provides a useful comparison point for willow bark in the integrative pain-management conversation.
Ibuprofen produces more rapid and more powerful acute analgesia than willow bark at standard over-the-counter (OTC) doses (200-400 mg). Ibuprofen reaches peak plasma concentration in 1-2 hours (willow extract's salicylic acid peaked within less than 2 hours in one pharmacokinetic study, at low levels), and the magnitude of immediate pain reduction in a single dose is greater. For acute musculoskeletal injury, dental pain, or postoperative pain, ibuprofen is the more potent of the two.
For chronic use, the calculus shifts. Daily ibuprofen 800-1200 mg/day produces meaningful gastrointestinal toxicity over months (dyspepsia, gastric ulceration, occult gastrointestinal bleeding), increases cardiovascular risk modestly, and accelerates progression of chronic kidney disease in vulnerable patients. The American Geriatrics Society Beers Criteria specifically recommend against chronic daily nonsteroidal anti-inflammatory drug use in older adults. Willow bark's lower gastrointestinal toxicity is the main reason it is discussed as a chronic-daily alternative for the same chronic-pain patients who would otherwise take ibuprofen daily.
One integrative approach practitioners describe is willow bark daily as a baseline for chronic pain, with ibuprofen kept for occasional acute flares (no more than 3-5 days per month), to limit total nonsteroidal anti-inflammatory drug exposure. Taking willow and ibuprofen on the same day adds a second cyclooxygenase inhibitor, and the combination increases gastrointestinal and renal risk without proportional analgesic benefit.
Dosing for Pain Management
- Standardized extract for chronic pain: 240 mg of salicin per day (the dose used in the Chrubasik and Schmid trials), typically delivered as one or two capsules of a 15-25% standardized extract.
- Standardized extract for mild-to-moderate symptoms: 120 mg of salicin per day. This is the lower dose that still outperformed placebo in the Chrubasik trial.
- Whole bark (non-standardized capsules): 6-12 g of dried bark daily, divided in two or three doses. Dosing is less precise than with standardized extract.
- Tincture (1:5): 4-6 mL three times daily. The bitter astringent flavor is characteristic.
- Tea / decoction: 2-3 g of dried bark simmered in water for 10-15 minutes. Strong tannin flavor; mostly used in traditional preparation rather than for measured therapeutic dosing.
- Onset of effect: Some pain relief is felt within 1-2 hours of dosing, but maximum benefit develops over 2-4 weeks of consistent daily use. This is similar to other slow-onset analgesic supplements (e.g., turmeric) and unlike acute nonsteroidal anti-inflammatory drug dosing.
- Duration of use: The clinical trials lasted up to six weeks (Vlachojannis 2009), so trial evidence on daily use over months is limited. Practitioners describe periodic 1-2 week breaks every 2-3 months.
- With food: taking it with food is the usual way to reduce the small risk of gastrointestinal upset.
Integrative Pain-Management Protocols
Willow bark is most commonly combined with other natural anti-inflammatories in modern integrative pain protocols. Practitioners describe these combinations:
- Willow bark + turmeric (curcumin). The most common pairing. Turmeric's curcuminoids inhibit NF-kappaB-driven inflammation through a distinct mechanism from COX inhibition; willow provides direct COX inhibition. Combined effect is broader than either alone. Typical: 240 mg salicin/day + 500-1000 mg curcumin (with piperine or phospholipid delivery for bioavailability).
- Willow bark + ginger. Ginger contains gingerols and shogaols that produce additional cyclooxygenase-2 and lipoxygenase inhibition. The combination is particularly effective for osteoarthritis and mechanical inflammatory pain.
- Willow bark + boswellia. Boswellia serrata extracts inhibit the 5-lipoxygenase pathway (leukotriene synthesis), which willow does not address. The combination provides COX + LOX dual coverage.
- Willow bark + tart cherry. Tart cherry is particularly useful for gout and uric-acid-driven inflammation. Willow provides general analgesia, tart cherry addresses the underlying purine pathology.
- Willow bark + magnesium. Magnesium reduces muscle tension and supports analgesia through N-methyl-D-aspartate-receptor and calcium-channel mechanisms. Useful as a pairing for tension-pattern chronic pain.
- Willow bark + glycine. Glycine supports the hepatic conjugation step that is the rate-limiting elimination pathway for salicylate. Supplemental glycine (3-5 g at bedtime) is proposed by these practitioners to reduce the risk of salicylate accumulation in people on high doses or with compromised liver function. See Glycine & Aspirin Metabolism for the detailed pharmacology, which applies equally to willow.
For comprehensive non-pharmaceutical pain management, see Pain Management. For specific conditions, see Arthritis, Chronic Low Back Pain, and Joint Pain.
Cautions
- Reye syndrome contraindication in children with viral illness. The same Reye syndrome warning that applies to aspirin applies to all salicylate-containing preparations, including willow bark, in children and adolescents (under age 18) with influenza, chickenpox, or any febrile viral illness. No pediatric dose is considered safe during viral infection.
- Salicylate allergy / AERD. Absolute contraindication. Patients with documented aspirin allergy, salicylate sensitivity, or aspirin-exacerbated respiratory disease (the Samter triad: asthma + nasal polyps + aspirin sensitivity) cross-react with willow bark.
- Anticoagulants / antiplatelets. Additive bleeding risk with warfarin, clopidogrel, dabigatran, rivaroxaban, apixaban, and aspirin itself. The theoretical risk is smaller than aspirin's but still clinically meaningful at the 240 mg salicin/day therapeutic dose.
- Concurrent nonsteroidal anti-inflammatory drug use. Combining willow with ibuprofen, naproxen, diclofenac, or other nonsteroidal anti-inflammatory drugs adds a second COX inhibitor, and the combination increases gastrointestinal and renal risk without proportional benefit.
- Active peptic ulcer or gastrointestinal bleeding. Contraindicated despite willow's lower gastric toxicity.
- Pregnancy. A concern particularly in the third trimester: salicylates can promote premature closure of the fetal ductus arteriosus and increase bleeding risk around delivery.
- Severe renal or hepatic disease. Caution; willow's active metabolites are eliminated by both routes.
- Pre-surgical use. Practitioners describe stopping at least one week before any scheduled surgery, dental extraction, or invasive procedure.
- Tinnitus. Sudden onset of ringing in the ears can be a sign of salicylate excess, a recognised signal for lowering the dose.
Key Research Papers
- Stone E (1763). An Account of the Success of the Bark of the Willow in the Cure of Agues. Philosophical Transactions of the Royal Society. — PubMed
- Chrubasik S et al. (2000). Treatment of low back pain exacerbations with willow bark extract: a randomized double-blind study. American Journal of Medicine. — PubMed PMID: 10936472
- Chrubasik S et al. (2001). Treatment of low back pain with a herbal or synthetic anti-rheumatic: a randomized controlled study. Willow bark extract for low back pain. Rheumatology (Oxford). — PubMed PMID: 11752510
- Schmid B et al. (2001). Efficacy and tolerability of a standardized willow bark extract in patients with osteoarthritis: randomized placebo-controlled, double blind clinical trial. Phytotherapy Research. — PubMed
- Biegert C et al. (2004). Efficacy and safety of willow bark extract in the treatment of osteoarthritis and rheumatoid arthritis: results of 2 randomized double-blind controlled trials (willow vs diclofenac). Journal of Rheumatology. — PubMed PMID: 15517622
- Gagnier JJ et al. (2007). Herbal medicine for low back pain: a Cochrane review. Spine. — PubMed PMID: 17202897
- Vlachojannis JE et al. (2009). A systematic review on the effectiveness of willow bark for musculoskeletal pain. Phytotherapy Research. — PubMed PMID: 19140170
- Mahdi JG (2010). Medicinal potential of willow: a chemical perspective of aspirin discovery. Journal of Saudi Chemical Society. — PubMed
- Schmid B et al. (2001). Pharmacokinetics of salicin after oral administration of a standardised willow bark extract. European Journal of Clinical Pharmacology. — PubMed PMID: 11599656
- Akao T et al. (2002). Evaluation of salicin as an antipyretic prodrug that does not cause gastric injury. Planta Medica. — PubMed PMID: 12221594
- Hoffmann F (1897). Original Bayer laboratory notebook entry, synthesis of acetylsalicylic acid. historical reference. — PubMed
- Wood JN (2015). From plant extract to molecular panacea: a commentary on Stone (1763) 'An account of the success of the bark of the willow in the cure of agues'. Philosophical Transactions of the Royal Society B. — PubMed PMID: 25750237
PubMed Topic Searches
Connections
- All Herbs
- Willow Bark Overview
- Willow Bark Benefits Hub
- Willow Bark Anti-Inflammatory
- Willow Bark for Headache & Migraine
- Cardiovascular & Aspirin Comparison
- Aspirin
- Aspirin Side Effects
- Glycine & Aspirin Metabolism
- Glycine
- Turmeric
- Ginger
- Tart Cherry
- Pain Management
- Arthritis
- Chronic Pain
- Chronic Low Back Pain
- Joint Pain
- Gout
- Magnesium
- History