⚠ Evidence warning: Clinical trials or other evidence do not support the claims that willow bark suits chronic back pain, improves osteoarthritis pain and stiffness over 2-6 weeks, matches a low-to-moderate dose of aspirin for pain at 120-240 mg of salicin, and is safe for daily use over months. This page keeps it as a report of what people, websites or other media say.
Willow Bark (Salix alba)

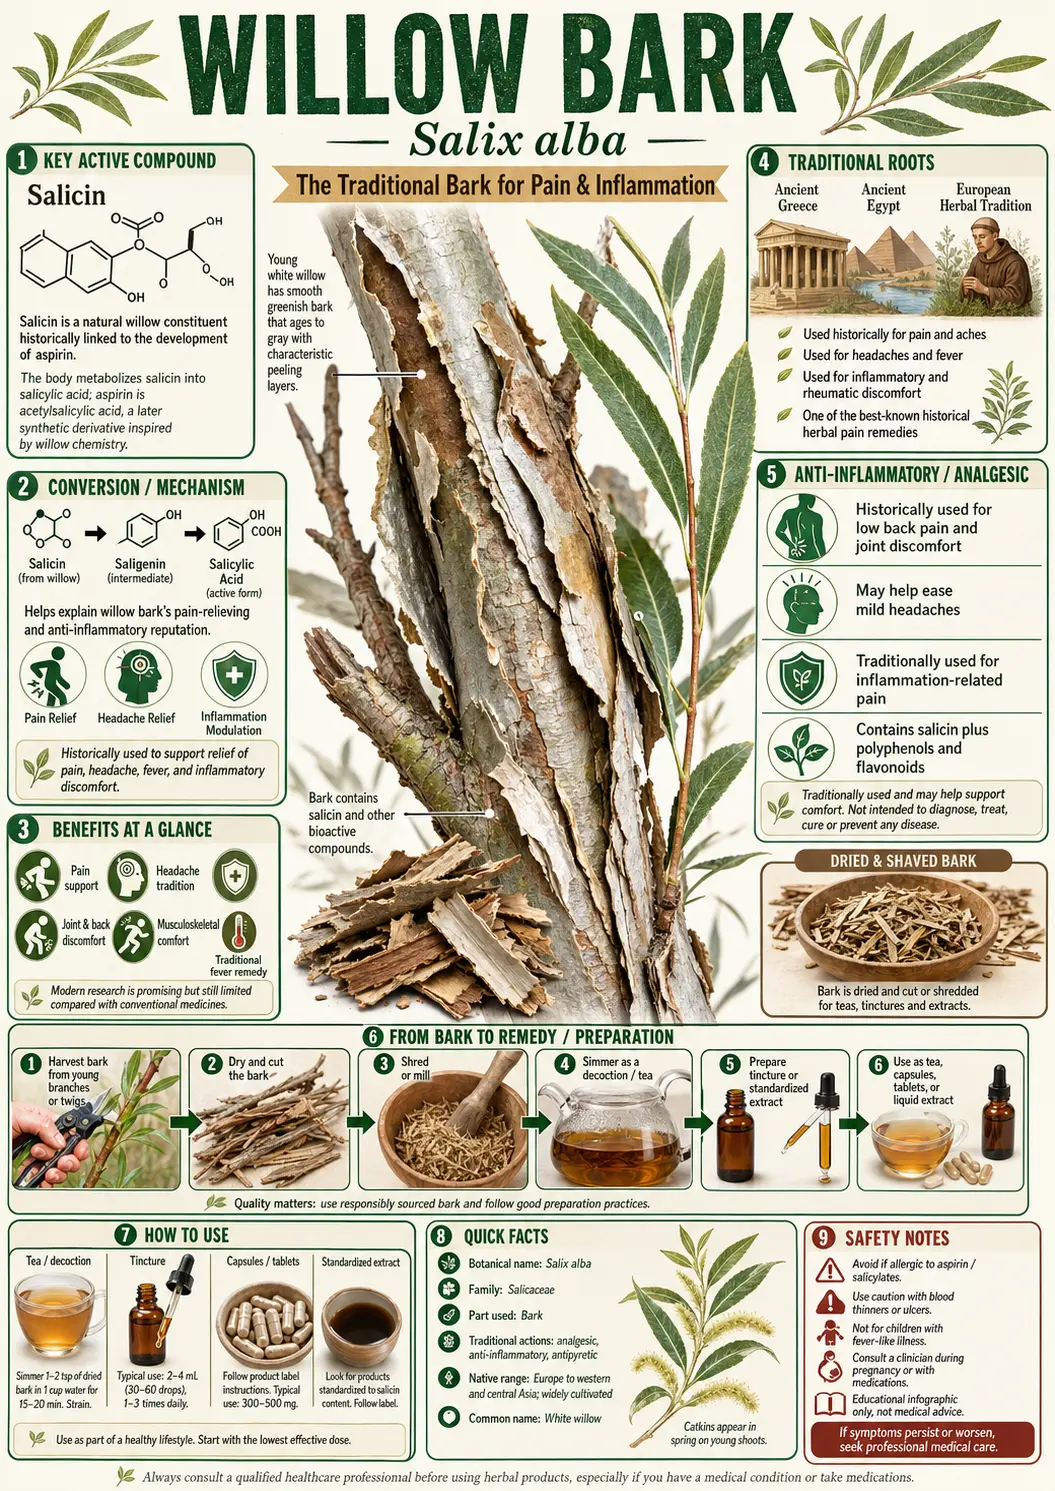
Table of Contents
The Original Aspirin
Willow bark is the prototype natural pain reliever and the historical predecessor of aspirin. The medicinal use of willow goes back at least 3,500 years — the Ebers Papyrus of ancient Egypt (c. 1550 BCE) recommends willow leaves for inflammation and pain. Hippocrates prescribed willow bark and leaves for fever and women in labor in the 5th century BCE. The Cherokee, Iroquois, and other Native American peoples chewed the inner bark for headache, muscle pain, and fever.
In 1763, English clergyman Edward Stone published a clinical report describing successful treatment of fever in 50 patients with willow bark, marking the beginning of systematic scientific investigation. In 1828, a German pharmacist isolated the active glycoside, naming it salicin after the Latin Salix. By 1899, a German drug company was marketing acetylsalicylic acid — a synthetic, chemically modified version with improved tolerability — under the trade name Aspirin.
Modern willow bark preparations occupy a clinical niche distinct from aspirin: they retain the analgesic and anti-inflammatory benefits of the salicylate parent compounds while being generally better tolerated than aspirin, with less gastrointestinal irritation and a different antiplatelet profile. They are commonly used in integrative pain management for musculoskeletal conditions where chronic nonsteroidal anti-inflammatory drug (NSAID) use is not desired.
Active Compounds
- Salicin — the principal active glycoside; metabolized in the gut and liver to salicylic acid (the same compound that aspirin is hydrolyzed to in the body)
- Salicortin and tremulacin — additional salicin-related glycosides found in many willow species
- Polyphenols and flavonoids — including catechins and proanthocyanidins, contributing additional anti-inflammatory and antioxidant activity
- Tannins — astringent compounds that contribute to mild gastrointestinal (GI) tract effects
Standardized extracts are typically calibrated to salicin content. Therapeutic dosing usually delivers 120-240 mg of salicin daily, which produces salicylic acid blood levels well below those achieved by therapeutic aspirin — but with effective analgesia for many users due to the synergistic activity of the whole-plant phytochemistry.
Mechanism of Action
Salicin is hydrolyzed in the gut to saligenin, then oxidized in the liver to salicylic acid — the same downstream active compound produced by aspirin metabolism. Salicylic acid is a non-selective inhibitor of cyclooxygenase enzymes (cyclooxygenase-1 (COX-1) and cyclooxygenase-2 (COX-2)), reducing prostaglandin synthesis and thereby producing analgesic, antipyretic, and anti-inflammatory effects.
Key pharmacological differences from aspirin:
- Reduced gastrointestinal irritation — because salicin is a glycoside that is converted to salicylic acid only after intestinal absorption, the gastric mucosa is not exposed to free salicylate; this reduces the gastrointestinal bleeding and ulceration risk that limits aspirin use
- Different antiplatelet profile — willow bark does not produce the same irreversible platelet inhibition that aspirin does, because aspirin's antiplatelet effect comes from acetylation of cyclooxygenase-1 by the acetyl group, which is not present in salicin
- Slower onset, longer duration — the conversion to salicylic acid produces a more gradual rise in plasma levels and a smoother analgesic curve
- Synergistic polyphenols — the additional flavonoids and tannins contribute to anti-inflammatory effect beyond what salicin alone produces
Low Back Pain
The strongest clinical evidence for willow bark is in chronic low back pain. Multiple randomized controlled trials have shown that 240 mg of salicin daily produces significant analgesia for low back pain comparable to or modestly less than that of standard nonsteroidal anti-inflammatory drugs (e.g., rofecoxib in the now-historical comparison trials). A 2007 Cochrane review counted two moderate-quality trials giving moderate evidence of short-term improvement in pain and rescue-medication use at 120 mg or 240 mg of salicin daily, plus one trial in which willow bark performed about the same as 12.5 mg of rofecoxib a day.
Effects build over 1-4 weeks of consistent use, more slowly than acute nonsteroidal anti-inflammatory drug dosing but with better long-term tolerability. The European Medicines Agency (EMA) herbal monograph lists willow bark for the short-term treatment of low back pain in adults and gives 4 weeks as the longest period of use. Willow bark is described as appropriate for chronic mechanical back pain in adults seeking to avoid daily nonsteroidal anti-inflammatory drug use, with medical evaluation to rule out red-flag conditions.
Osteoarthritis
Two controlled trials have tested a willow bark extract (240 mg of salicin a day) in osteoarthritis of the hip and knee, with mixed results. In a 2-week trial of 78 patients (Schmid 2001), the pain score fell 14% on willow bark against a 2% rise on placebo, a difference the authors described as a moderate pain-relieving effect. In a 6-week trial of 127 patients (Biegert 2004), pain fell 17% on willow bark, 47% on diclofenac 100 mg a day and 10% on placebo; the willow-versus-placebo difference was not statistically significant, and the authors concluded that the extract showed no relevant efficacy in osteoarthritis.
Pain and stiffness scores improve significantly over 2-6 weeks of treatment, with effect sizes smaller than full-dose pharmaceutical nonsteroidal anti-inflammatory drugs (NSAIDs) but adequate for many patients with mild to moderate osteoarthritis.
Practitioners commonly combine willow bark in osteoarthritis with turmeric, boswellia, glucosamine sulfate and weight-bearing exercise, and describe the combined mild pain relief from several plant sources as a way to reduce daily nonsteroidal anti-inflammatory drug use.
Headache and Mild Fever
Willow bark has classical use for tension headache and mild fever. While modern clinical trials specifically for headache are limited, the mechanism (cyclooxygenase inhibition by salicylic acid) is identical to that of aspirin, which is well established for tension headache. A typical therapeutic dose of 120-240 mg of salicin produces approximately the same analgesic effect as a low-to-moderate dose of aspirin. In a 2001 pharmacokinetic study, 240 mg of salicin produced a salicylic acid blood exposure equal to what about 87 mg of aspirin would give — much lower than pain-relieving aspirin doses — and the authors concluded that salicylic acid alone is unlikely to explain willow bark's pain-relieving effect.
For migraine specifically, willow bark may serve as an abortive treatment, though it has not been extensively studied for this indication. Practitioners describe combining it with magnesium, riboflavin and feverfew for migraine prevention.
Forms and Preparations
- Standardized extract — typically standardized to 15% or 25% salicin; the form used in clinical trials
- Whole bark capsules and tablets — ground inner bark; less precise dosing
- Tincture (1:5) — 15-24 mL per day in the EMA monograph's traditional-use dosing
- Tea / decoction — the EMA monograph gives 1-3 g of cut bark in 150 mL of boiling water as a tea three times daily, or 4 g boiled covered in 200 mL of water for 15 minutes as a decoction taken after meals three times a day; bitter and astringent flavor
- Combination products — often combined with turmeric, boswellia, ginger, or devil's claw for synergistic anti-inflammatory action
Dosage in Trials and the European Monograph
- Standardized extract — enough to deliver 120-240 mg of salicin daily (the dose used in low back pain trials); typically one capsule once or twice daily of a 15-25% salicin extract
- Whole bark — 6-12 g of dried bark daily, divided in two or three doses
- Tincture (1:5) — 15-24 mL per day (EMA monograph)
- Onset — some pain relief is felt acutely (1-2 hours after dosing) but maximum benefit develops over 2-4 weeks of consistent use
- Duration — the EMA monograph sets 4 weeks as the longest use for low back pain and for joint pain, and treats fever lasting more than 3 days, or headache lasting more than 1 day, during use as a reason to see a doctor; a 6-month observational study of 436 outpatients without a comparison group (Uehleke 2013) reported good tolerability; safe for daily use over months; periodic breaks are reasonable but not strictly required
Cautions and Contraindications
- Aspirin / salicylate allergy — contraindicated; cross-reactivity with salicylates
- Children and teenagers (Reye syndrome) — the EMA monograph lists everyone under 18 years of age as a contraindication because of the risk of Reye syndrome; the same Reye syndrome warning that applies to aspirin, best known for fever during influenza or chickenpox, applies to other salicylates including willow
- Glucose-6-phosphate dehydrogenase (G6PD) deficiency — listed as a contraindication in the EMA monograph
- Clotting disorders — listed as a contraindication in the EMA monograph
- Anticoagulants and antiplatelets — additive bleeding risk with warfarin, clopidogrel, dabigatran, apixaban; the EMA monograph states that willow bark may increase the effects of coumarin-type anticoagulants such as warfarin; the theoretical risk is smaller than with aspirin but still meaningful
- Nonsteroidal anti-inflammatory drugs — the EMA monograph states that use together with other salicylates and NSAIDs is not recommended without medical advice; both inhibit cyclooxygenase and the combination increases stomach, gut and kidney risk
- Active peptic ulcer or gastrointestinal bleeding — contraindicated
- Severe asthma — aspirin-exacerbated respiratory disease (AERD) means cross-reactivity with salicylates; the EMA monograph lists asthma due to salicylate sensitivity as a contraindication
- Pregnancy and breastfeeding — the EMA monograph lists the third trimester as a contraindication and states that use in the first and second trimesters and while breastfeeding is not recommended, because salicylates cross the placenta and appear in breast milk; salicylates can affect fetal ductus arteriosus closure when taken in late pregnancy and bleeding around delivery
- Surgery — because of the added bleeding risk, practitioners commonly stop willow bark at least one week before scheduled surgery
- Kidney and liver disease — the EMA monograph lists severe liver or kidney dysfunction as a contraindication; salicylates can impair kidney function
- Mild side effects — nausea, mild gastrointestinal upset, headache, rash; less common than with aspirin
Key Research Papers
The following PubMed search links provide curated entry points into the published clinical and mechanistic literature on Willow Bark (Salix alba). Each link opens directly in PubMed at the National Library of Medicine.
- Salix alba salicin for low back pain — PubMed: willow salicin low back pain
- Willow bark extract over 6 months in outpatients with osteoarthritis or back pain (observational study, no comparison group) — PubMed PMID: 23731658
- Salicin metabolism and pharmacokinetics — PubMed: salicin metabolism pharmacokinetics
- Willow bark anti-inflammatory mechanism — PubMed: willow bark anti-inflammatory
- Willow bark headache and migraine — PubMed: willow bark headache
- Willow bark safety GI bleeding — PubMed: willow bark safety bleeding
- LactMed (Drugs and Lactation Database, NCBI Bookshelf): Willow Bark — salicylic acid in breast milk — PubMed PMID: 30000964
- Schmid B, Lüdtke R, Selbmann HK, Kötter I, Tschirdewahn B, Schaffner W, Heide L. Efficacy and tolerability of a standardized willow bark extract in patients with osteoarthritis: randomized placebo-controlled, double blind clinical trial. Phytotherapy Research. 2001;15(4):344–350 — PubMed PMID: 11406860
- Biegert C, Wagner I, Lüdtke R, Kötter I, Lohmüller C, Günaydin I, Taxis K, Heide L. Efficacy and safety of willow bark extract in the treatment of osteoarthritis and rheumatoid arthritis: results of 2 randomized double-blind controlled trials. Journal of Rheumatology. 2004;31(11):2121–2130 — PubMed PMID: 15517622
- Schmid B, Kötter I, Heide L. Pharmacokinetics of salicin after oral administration of a standardised willow bark extract. European Journal of Clinical Pharmacology. 2001;57(5):387–391 — PubMed PMID: 11599656
- Gagnier JJ, van Tulder MW, Berman B, Bombardier C. Herbal medicine for low back pain: a Cochrane review. Spine. 2007;32(1):82–92 — PubMed PMID: 17202897
- European Medicines Agency, Committee on Herbal Medicinal Products. European Union herbal monograph on Salix [various species including S. purpurea L., S. daphnoides Vill., S. fragilis L.], cortex. EMA/HMPC/80630/2016 — EMA: Salicis cortex
External Authoritative Resources
Connections
- All Herbs
- Pain Management — willow bark's place among evidence-graded options
- Willow Bark Benefits Deep Dive
- Turmeric
- Ginger
- Peppermint
- Chronic Pain
- Arthritis
- Aspirin
- Glycine & Aspirin Metabolism
- Glycine
- Headache
- Migraine
- Magnesium
- Joint Pain
- Gout
- Chronic Low Back Pain
- Influenza
- Health Benefits
- Tart Cherry
- John Vane — the Nobel laureate who explained how willow bark's descendant, aspirin, actually works