Willow Bark Cardiovascular Effects and Aspirin Comparison
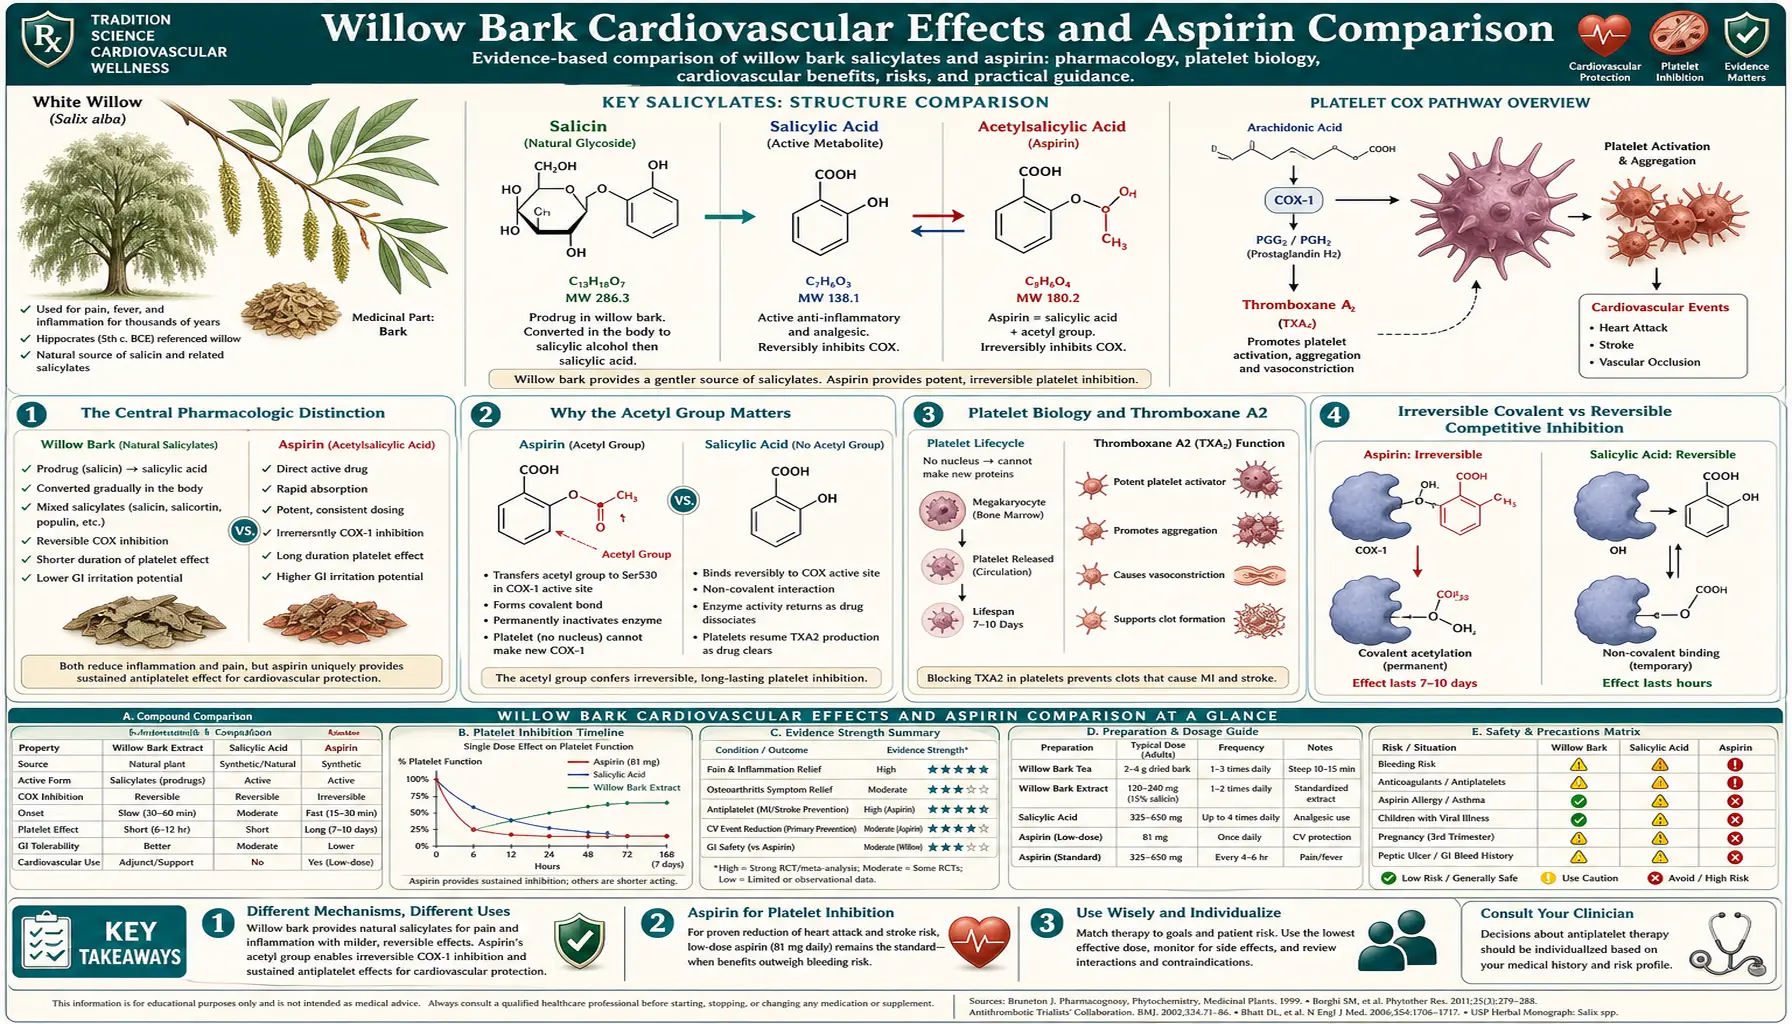
This is the most important clinical distinction in willow bark pharmacology, and it is consistently obscured in popular health writing: willow bark does NOT provide aspirin's antiplatelet cardioprotection. Aspirin's unique value in secondary prevention of myocardial infarction and stroke comes from its acetyl group covalently and irreversibly acetylating serine-529 on cyclooxygenase-1 in platelets, permanently disabling thromboxane A2 synthesis in those platelets for their 7-10 day lifespan. Salicin has no acetyl group. Salicylic acid produced from willow metabolism reversibly competes for the COX active site rather than covalently modifying it — effective for analgesia and anti-inflammatory effect, but inadequate for durable platelet inhibition. A patient taking low-dose aspirin (81 mg/day) for secondary cardiovascular prevention cannot substitute willow bark and maintain the same cardioprotective effect. This deep-dive walks through the acetylation pharmacology, the platelet biology, why aspirin is the only acetylated salicylate in clinical use, the secondary-prevention evidence base, and the appropriate (limited) cardiovascular role for willow bark.
Table of Contents
- The Central Pharmacologic Distinction
- Why the Acetyl Group Matters
- Platelet Biology and Thromboxane A2
- Irreversible Covalent vs Reversible Competitive Inhibition
- The Low-Dose Aspirin Cardioprotection Evidence
- What Willow Actually Does to Platelets
- Why Salicin Is Not an Aspirin Substitute
- Secondary Prevention: Aspirin's Evidence and Willow's Gap
- Primary Prevention: The Equation Has Shifted
- Limited Cardiovascular Applications for Willow
- Common Misconceptions
- Key Research Papers
- Connections
- Featured Videos
The Central Pharmacologic Distinction
Walk into a typical health food store and ask about willow bark, and a common response is: "It's nature's aspirin — same thing, more natural." Read most popular health-website content on willow and you'll find similar language. The framing is not entirely wrong — willow bark and aspirin do share the same downstream active metabolite (salicylic acid) and the same principal mechanism of analgesic and anti-inflammatory action (cyclooxygenase inhibition). For pain management, anti-inflammatory effect, and fever reduction, willow bark is in fact a reasonable natural analog of aspirin with somewhat different pharmacokinetic and tolerability properties.
But for one specific indication — cardiovascular prophylaxis through platelet inhibition — the analogy breaks down completely. Aspirin's ability to prevent recurrent myocardial infarction and ischemic stroke depends on a pharmacologic property that willow bark does not share: the irreversible covalent acetylation of serine-529 on cyclooxygenase-1 in platelets, by the acetyl group that is specifically present in acetylsalicylic acid and absent from salicin or salicylic acid alone.
The clinical consequence is unambiguous: a patient who has had a previous myocardial infarction or ischemic stroke and is taking low-dose aspirin (81 mg daily) for secondary prevention CANNOT substitute willow bark and maintain the same cardioprotective effect. Willow bark does not durably inhibit platelet aggregation. It will not reduce the patient's risk of a second myocardial infarction (MI) or recurrent stroke. Substituting willow for low-dose aspirin in a patient with established cardiovascular disease may meaningfully increase their cardiovascular event rate.
This is a frequent point of patient confusion. The purpose of this deep-dive is to walk through the pharmacology clearly enough that the distinction is understood and the substitution is not made inadvertently.
Why the Acetyl Group Matters
Aspirin's full chemical name is acetylsalicylic acid — the salicylic acid molecule with one of its hydroxyl-group hydrogens replaced by an acetyl group (CH₃CO–). That single chemical modification, made by Felix Hoffmann at Bayer in 1897, is what gives aspirin its unique cardiovascular properties.
The acetyl group can be transferred from acetylsalicylic acid to nucleophilic targets — in particular, the hydroxyl group of serine-529 in the active site of cyclooxygenase-1. When aspirin enters a platelet, the acetyl group is irreversibly transferred from acetylsalicylic acid to serine-529, leaving acetylated cyclooxygenase-1 (COX-1) plus free salicylic acid as the products. The acetylated serine-529 cannot participate in the cyclooxygenase-1 catalytic cycle — it permanently blocks the arachidonic acid substrate from reaching the heme-iron center where prostaglandin H2 is normally formed. The enzyme is permanently inactivated for the lifetime of that platelet.
Salicin (the willow bark glycoside) has no acetyl group available for transfer. Neither does salicylic acid, the downstream metabolite produced both from aspirin hydrolysis and from willow bark metabolism. Salicylic acid alone can occupy the cyclooxygenase-1 active site, blocking arachidonic acid binding, but it cannot covalently modify the enzyme. When the salicylic acid molecule dissociates from the active site (which it does reversibly, with a typical residence time of seconds-to-minutes), the enzyme returns to functional catalytic activity. There is no permanent inactivation.
This is the single most important pharmacologic distinction in the willow-versus-aspirin comparison. Aspirin is uniquely able to permanently modify platelet cyclooxygenase-1 because it carries an acetyl group. Willow bark, salicin, and salicylic acid alone all lack this acetyl group and cannot produce the equivalent durable effect on platelets.
Platelet Biology and Thromboxane A2
Platelets are anucleate cell fragments derived from megakaryocytes in the bone marrow. They lack a nucleus, so they cannot synthesize new mRNA or new proteins. The cyclooxygenase-1 enzyme that platelets express was synthesized in the megakaryocyte before the platelet was released into circulation, and it must last the platelet's entire lifespan (typically 7-10 days). When that cyclooxygenase-1 is irreversibly inactivated by aspirin acetylation, the platelet cannot generate new functional cyclooxygenase-1 to replace it — it is permanently disabled for thromboxane A2 synthesis until it is removed from circulation and replaced by a new platelet from the bone marrow.
Thromboxane A2 (TXA2), the principal cyclooxygenase-1 product in platelets, is a powerful vasoconstrictor and platelet aggregator. When a blood vessel is injured, activated platelets release thromboxane A2 into the local environment, which recruits additional platelets to the injury site and amplifies the aggregation response. This is essential for normal hemostasis (stopping bleeding), but the same mechanism contributes to pathological platelet aggregation in coronary artery disease, where atherosclerotic plaque rupture exposes pro-thrombotic surface that triggers platelet aggregation and arterial thrombus formation.
By irreversibly inactivating platelet cyclooxygenase-1, aspirin reduces thromboxane A2 production and shifts the platelet activation threshold higher. In the setting of atherosclerotic plaque rupture, this reduction in platelet aggregation translates to a reduction in arterial thrombus formation and a reduction in myocardial infarction or ischemic stroke risk.
The bone marrow produces approximately 10% of the total platelet pool per day (replacing the senescent platelets that are removed by the spleen). With chronic daily aspirin dosing, the bone marrow's new platelets enter a circulation environment where aspirin is still present, and they too become acetylated within hours of release. The result is sustained 90-95% suppression of platelet cyclooxygenase-1 activity with daily 81 mg aspirin dosing — the dose is sufficient to fully acetylate the newly released 10% of platelets each day while leaving extraplatelet cyclooxygenase-2 (COX-2) largely uninhibited.
This sustained platelet cyclooxygenase-1 inhibition is the mechanism behind aspirin's cardioprotection. Willow bark does not produce it.
Irreversible Covalent vs Reversible Competitive Inhibition
The distinction between irreversible covalent modification and reversible competitive inhibition is fundamental to understanding why aspirin uniquely produces durable platelet inhibition:
- Reversible competitive inhibition (the willow-salicylic-acid mechanism for COX). The inhibitor molecule occupies the enzyme's active site and prevents substrate binding, but it does not chemically modify the enzyme. When the inhibitor dissociates (which happens continuously based on the equilibrium binding constant), the enzyme returns to active form. Inhibition lasts only as long as the inhibitor remains in the active site, which depends on inhibitor concentration. Once the inhibitor is cleared from circulation, enzyme activity returns to normal within minutes.
- Irreversible covalent inhibition (the aspirin mechanism for platelet cyclooxygenase-1). The inhibitor molecule transfers a chemical group to the enzyme's active site, permanently modifying the enzyme. The enzyme cannot return to its original functional form even after the inhibitor is cleared from circulation. In a cell with active protein synthesis, the modified enzyme is eventually replaced by newly synthesized enzyme, restoring function. In platelets, which cannot synthesize new proteins, the modified enzyme remains modified for the platelet's lifetime.
Almost all clinically used drug-enzyme interactions are reversible competitive inhibition. The aspirin-platelet-COX-1 interaction is one of the few clinically important examples of irreversible covalent inhibition. The clinical implication: a single low-dose aspirin produces platelet inhibition lasting 7-10 days. A single dose of willow bark or any other reversible salicylate produces platelet inhibition lasting hours. There is no way to achieve aspirin's durable platelet effect with a reversible inhibitor — the irreversibility is the entire mechanism.
The Low-Dose Aspirin Cardioprotection Evidence
Low-dose aspirin's cardioprotective effect has been demonstrated in an enormous body of randomized clinical trial evidence. The key studies and consensus:
- ISIS-2 (1988) — 17,187 patients with acute myocardial infarction randomized to streptokinase, aspirin (160 mg), both, or neither. Aspirin alone reduced 5-week vascular mortality by 23%; aspirin plus streptokinase reduced mortality by 42%. This trial established aspirin as standard-of-care in acute myocardial infarction management.
- ATC meta-analysis (Antithrombotic Trialists' Collaboration, 2002 and 2009) — pooled analysis of 287 randomized trials in over 200,000 patients confirmed that antiplatelet therapy (predominantly aspirin) reduced serious vascular events by approximately 25% in patients with established cardiovascular disease. In the 2002 analysis, non-fatal heart attack fell by one third, non-fatal stroke by one quarter and vascular death by one sixth, and aspirin at 75-150 mg a day was at least as effective as higher doses. The benefit was clearest in patients with prior myocardial infarction, prior stroke, prior transient ischemic attack (TIA), established coronary artery disease, or established peripheral arterial disease.
- Secondary prevention guidelines — ACC/AHA, ESC, NICE, and WHO guidelines all recommend low-dose aspirin (typically 75-100 mg daily) for secondary prevention in patients with established cardiovascular disease, unless contraindicated by bleeding history or active gastrointestinal (GI) bleeding.
The mechanism is the durable platelet inhibition described above. Every randomized trial that has demonstrated aspirin's secondary prevention benefit has used acetylated salicylates — either aspirin itself or related acetylated derivatives. No randomized trial has ever demonstrated equivalent cardioprotection from non-acetylated salicylates (including willow bark, salicin alone, salicylic acid alone, or the sodium salicylate formulations historically used as anti-inflammatories before aspirin).
This is the strongest possible evidence-based argument that willow bark cannot substitute for aspirin in secondary cardiovascular prevention. The drug-class effect that produces the cardioprotection requires the acetyl group, and the entire trial evidence base used acetylated formulations.
What Willow Actually Does to Platelets
To be precise about willow bark's effect on platelets: it is not nothing. Several mechanisms produce mild reversible antiplatelet effect:
- Plasma salicylic acid from willow metabolism produces low-level reversible cyclooxygenase-1 inhibition in platelets while it is present, for the duration of measurable plasma concentration. After clearance, platelet function returns to normal.
- Polyphenol antiplatelet effects. Some willow polyphenols (catechins, proanthocyanidins) have mild antiplatelet activity, similar to that seen with green tea, dark chocolate, and red wine. The effect is real but small.
- Possible direct salicylate reversible inhibition. At sufficiently high plasma salicylic acid concentrations, reversible cyclooxygenase-1 inhibition could produce measurable platelet inhibition during peak plasma concentration; the Krivoy study below measured a modest effect at the standard dose of 240 mg salicin a day.
The net effect, as measured: in the Krivoy 2001 double-blind study, people with low back pain taking willow bark extract with 240 mg salicin a day had a mean maximal arachidonic-acid-induced platelet aggregation of 61%, against 78% on placebo and 13% in heart patients taking aspirin 100 mg a day. Willow differed significantly from placebo when aggregation was triggered by arachidonic acid (p = 0.04) or ADP (p = 0.01), but not by collagen, and the authors conclude it affects aggregation “to a far lesser extent” than aspirin. The study did not report how the effect varies through the day, and whether this smaller effect matters for bleeding or clotting in real patients was not studied. By comparison, low-dose aspirin (81 mg/day) produces sustained 90-95% suppression of platelet thromboxane A2 production over 24 hours, every day.
The mild willow antiplatelet effect raises a bleeding concern — willow bark is commonly stopped before surgery, an additive effect with anticoagulants and antiplatelet drugs is expected, and it contributes to peri-procedural bleeding concerns, though the Krivoy authors note its clinical relevance is not yet established — but it is far from sufficient to provide aspirin's secondary prevention cardioprotection.
Why Salicin Is Not an Aspirin Substitute
The simple summary:
- Aspirin = acetylsalicylic acid. The acetyl group covalently modifies platelet cyclooxygenase-1, producing irreversible enzyme inactivation lasting the platelet's 7-10 day lifespan.
- Willow bark salicin → salicylic acid. No acetyl group. Salicylic acid produces reversible competitive COX inhibition, lasting only while plasma concentration is sufficient.
You could in principle imagine taking pharmaceutical-grade salicin and chemically acetylating it — the resulting compound would actually be a synthetic acetylsalicin and would have somewhat different properties from aspirin (because of the glycoside attachment), but the more direct path is what Bayer's Felix Hoffmann did in 1897: take salicylic acid (the active downstream metabolite) and acetylate it, producing acetylsalicylic acid = aspirin. The acetylation step is what produces the irreversible platelet inhibition, regardless of whether you start with salicin or salicylic acid.
This is also why other naturally occurring salicylates — methyl salicylate (in wintergreen and birch), salicylate in meadowsweet, salicylate in poplar bark — all behave similarly to willow bark and similarly differently from aspirin. None of them are acetylated. None of them produce the durable platelet inhibition. The historical use of these natural sources for fever and pain is consistent across cultures and centuries, but their cardiovascular profile is fundamentally different from aspirin's.
Secondary Prevention: Aspirin's Evidence and Willow's Gap
For patients with established cardiovascular disease — previous myocardial infarction, previous ischemic stroke or transient ischemic attack, established coronary artery disease (with prior PCI or CABG), established peripheral arterial disease, or stable angina — low-dose aspirin (75-100 mg daily) is a Class I recommendation in all major cardiovascular practice guidelines (ACC/AHA, ESC, NICE) unless contraindicated by active bleeding, salicylate allergy, or specific high-bleeding-risk circumstances.
The cardioprotective effect — approximately 25% reduction in serious vascular events in established cardiovascular disease (CVD) — is one of the most robust findings in cardiovascular medicine. In the 2002 Antithrombotic Trialists' meta-analysis, antiplatelet therapy prevented 36 serious vascular events for every 1,000 patients with a previous myocardial infarction treated for two years; in the 2009 analysis of secondary-prevention trials, aspirin lowered serious vascular events from 8.2% to 6.7% a year.
Willow bark does not produce this effect. A patient with established cardiovascular disease who replaces their low-dose aspirin with willow bark is removing the cardioprotective intervention without an effective substitute. The expected consequence is an increase in cardiovascular event rate proportional to the duration of aspirin discontinuation.
What the guidelines and trials show:
- No trial supports willow bark in place of aspirin for secondary cardiovascular prevention. This is the central message of this deep-dive.
- If gastrointestinal tolerance of low-dose aspirin is poor, the options used in practice are enteric-coated aspirin (which delays gastric exposure), aspirin combined with a proton pump inhibitor (which reduces gastric acid and ulcer risk), or an alternative antiplatelet drug such as clopidogrel. In the 2002 meta-analysis, clopidogrel reduced serious vascular events by 10% compared with aspirin, and in the 2025 SMART-CHOICE 3 trial (5,506 high-risk patients in South Korea after a coronary stent), long-term clopidogrel alone was followed by fewer deaths, heart attacks or strokes than aspirin alone (4.4% vs 6.6% at 3 years) with the same bleeding rate (3.0% vs 3.0%). Willow bark has no such evidence.
- If true aspirin allergy or major bleeding risk requires discontinuation, cardiologists choose an alternative antiplatelet drug. Willow bark has no trial evidence in this role.
- Willow bark can still be used for pain management or anti-inflammatory effect alongside low-dose aspirin in patients with established cardiovascular disease — but with awareness that the additive bleeding risk needs to be balanced against analgesic benefit. Many cardiologists prefer acetaminophen as the pain-management adjunct for cardiovascular disease patients on aspirin, to minimize the additive bleeding burden.
See Aspirin for comprehensive coverage of aspirin's cardiovascular indications and Aspirin Side Effects for the bleeding and gastrointestinal considerations that complicate aspirin use.
Primary Prevention: The Equation Has Shifted
The role of aspirin in primary prevention — daily aspirin in patients without established cardiovascular disease, intended to prevent a first cardiovascular event — has shifted substantially in recent guidelines based on three large 2018 trials (ASPREE, ARRIVE, ASCEND). These trials showed that in low-to-moderate cardiovascular risk patients without established cardiovascular disease, the bleeding risk of daily aspirin approximately balances or exceeds the cardiovascular event prevention benefit. In numbers: ASPREE (19,114 people aged 70 and over, median 4.7 years) found no gain in disability-free survival and major bleeding of 3.8% against 2.8%; ASCEND (15,480 people with diabetes, mean 7.4 years) found serious vascular events of 8.5% against 9.6% but major bleeding of 4.1% against 3.2%; ARRIVE (12,546 adults at moderate risk) found no difference in first vascular events (4.29% against 4.48%) and gastrointestinal bleeding of 0.97% against 0.46%. In the 2009 meta-analysis of primary-prevention trials, major gastrointestinal and other extracranial bleeds ran at 0.10% against 0.07% a year.
Current 2019 ACC/AHA guidelines and 2022 U.S. Preventive Services Task Force (USPSTF) recommendations reflect this:
- For most adults without established cardiovascular disease, routine daily aspirin is no longer recommended for primary prevention.
- For adults aged 40-59 with elevated cardiovascular risk (10-year ASCVD risk ≥ 10%), aspirin may be considered after shared decision-making weighing benefit and bleeding risk.
- For adults aged 60 and older without established cardiovascular disease, the U.S. Preventive Services Task Force recommends against initiating aspirin for primary prevention.
For patients in the no-longer-aspirin primary-prevention category, willow bark is not an obvious substitute either — the rationale for using aspirin in primary prevention required aspirin's antiplatelet effect, and that effect is what current evidence does not support for low-risk patients. Willow bark for these patients would be primarily for anti-inflammatory or pain-management indications, not for cardiovascular protection.
The evidence does not support primary cardiovascular benefit from willow bark, and the antiplatelet effect is insufficient to confer aspirin-like secondary prevention.
Limited Cardiovascular Applications for Willow
What cardiovascular-adjacent applications does willow bark legitimately have?
- Anti-inflammatory effect in atherosclerosis-relevant inflammation. Chronic systemic inflammation contributes to atherosclerosis progression. Willow bark's anti-inflammatory effect (COX inhibition + NF-kappaB / tumor necrosis factor-alpha suppression) may modestly reduce inflammatory markers like C-reactive protein (CRP) and interleukin-6 (IL-6). This is theoretically beneficial for long-term atherosclerosis but has not been demonstrated to translate to cardiovascular event reduction in clinical trials. Treating elevated C-reactive protein without a specific anti-inflammatory cardiovascular indication is not standard of care.
- Pain management for cardiovascular patients with chronic musculoskeletal pain. Patients with cardiovascular disease often need pain management for arthritis, chronic back pain, or post-procedural pain. Willow bark is described as gentler on the stomach, and no QT prolongation, blood pressure or heart-failure signal has been reported, but no cardiovascular safety trial exists: a 2015 review (Shara and Stohs) notes that relatively few human and animal studies have been published, and that adverse effects appear minimal compared with non-steroidal anti-inflammatory drugs including aspirin, the main concern being allergic reactions in salicylate-sensitive people. Concurrent aspirin or anticoagulants add to the bleeding risk.
- Adjunctive blood pressure considerations. Unlike nonsteroidal anti-inflammatory drugs (which can raise blood pressure by 2-5 mmHg through renal prostaglandin effects and sodium retention), willow bark at therapeutic doses appears to have minimal effect on blood pressure. This may be preferable to nonsteroidal anti-inflammatory drugs (NSAIDs) in patients with hypertension. But this is not the same as having a blood pressure benefit.
The bottom line: willow bark is used for pain and inflammation by people who happen to have cardiovascular disease, with an additive bleeding risk alongside aspirin or anticoagulants. Willow bark is not a cardiovascular prophylactic intervention: no trial shows it preventing cardiovascular events.
Common Misconceptions
Common patient and consumer misconceptions about willow bark and cardiovascular protection:
- "Willow is just a natural form of aspirin, so I can use it instead of my low-dose aspirin." Incorrect. Willow lacks the acetyl group that produces aspirin's cardioprotective platelet inhibition. Substitution will reduce cardiovascular protection.
- "My doctor said to take a baby aspirin every day, but I prefer natural alternatives, so I take willow bark instead." If the aspirin is for secondary cardiovascular prevention, no trial supports this substitution, and stopping the aspirin removes the protection shown in the trials above.
- "Willow bark thins the blood like aspirin." Partially true but misleading. Willow has a mild reversible antiplatelet effect at the standard dose of 240 mg salicin a day (aggregation 61%, against 78% on placebo and 13% on aspirin, in the Krivoy study), but does not produce sustained platelet inhibition. It is not equivalent to aspirin's "blood thinning" for cardiovascular indications.
- "Willow bark prevents heart attacks naturally." Not supported by evidence. No randomized trial has demonstrated willow bark cardiovascular event prevention.
- "Willow is safer than aspirin for the heart." Willow is not "safer for the heart" because it provides less cardioprotection — that's actually less safe for patients who need cardioprotection. Willow may be safer for the stomach, but not for the heart.
In summary:
- Willow bark is used for pain and inflammation; a small number of clinical studies support its use in chronic lower back and joint pain and osteoarthritis (Shara and Stohs 2015).
- Willow bark is gentler on the stomach than chronic aspirin.
- Willow bark is not a substitute for low-dose aspirin in cardiovascular protection.
- Stopping low-dose aspirin prescribed for cardiovascular protection removes the protection shown in the trials.
- Willow bark taken with low-dose aspirin adds a further antiplatelet effect (Krivoy 2001), so the bleeding risks add up.
Key Research Papers
- Roth GJ, Majerus PW (1975). The mechanism of the effect of aspirin on human platelets. I. Acetylation of a particulate fraction protein. Journal of Clinical Investigation. — PubMed PMID: 1159076
- Patrono C (1994). Aspirin as an antiplatelet drug. NEJM. — PubMed PMID: 8145785
- ISIS-2 Collaborative Group (1988). Randomised trial of intravenous streptokinase, oral aspirin, both, or neither among 17,187 cases of suspected acute myocardial infarction: ISIS-2. Lancet. — PubMed PMID: 2899772
- Antithrombotic Trialists' Collaboration (2002). Collaborative meta-analysis of randomised trials of antiplatelet therapy for prevention of death, myocardial infarction, and stroke in high-risk patients. BMJ. — PubMed PMID: 11786451
- Antithrombotic Trialists' Collaboration (2009). Aspirin in the primary and secondary prevention of vascular disease: collaborative meta-analysis of individual participant data from randomised trials. Lancet. — PubMed PMID: 19482214
- Vane JR (1971). Inhibition of prostaglandin synthesis as a mechanism of action for aspirin-like drugs. Nature New Biology, 231(25):232-5. — PubMed PMID: 5284360
- McNeil JJ et al. (2018). Effect of aspirin on disability-free survival in the healthy elderly (ASPREE trial). NEJM. — PubMed PMID: 30221596
- Gaziano JM et al. (2018). Use of aspirin to reduce risk of initial vascular events in patients at moderate risk of cardiovascular disease (ARRIVE trial). Lancet. — PubMed PMID: 30158069
- ASCEND Study Collaborative Group (2018). Effects of aspirin for primary prevention in persons with diabetes mellitus. NEJM. — PubMed PMID: 30146931
- Shara M, Stohs SJ (2015). Efficacy and safety of white willow bark (Salix alba) extracts. Phytotherapy Research. — PubMed PMID: 25997859
- Krivoy N et al. (2001). Effect of salicis cortex extract on human platelet aggregation. Planta Medica. — PubMed PMID: 11345689
- Bjarnason I, Scarpignato C, Holmgren E, Olszewski M, Rainsford KD, Lanas A (2018). Mechanisms of damage to the gastrointestinal tract from nonsteroidal anti-inflammatory drugs (relevant to aspirin GI toxicity). Gastroenterology, 154(3):500-514. — PubMed PMID: 29221664
- Choi KH, Park YH, Lee JY, et al.; SMART-CHOICE 3 investigators (2025). Efficacy and safety of clopidogrel versus aspirin monotherapy in patients at high risk of subsequent cardiovascular event after percutaneous coronary intervention (SMART-CHOICE 3): a randomised, open-label, multicentre trial. Lancet, 405(10486):1252-1263. — PubMed PMID: 40174599
- USPSTF (2022). Aspirin use to prevent cardiovascular disease: US Preventive Services Task Force recommendation statement. JAMA. — PubMed PMID: 35471505
PubMed Topic Searches
Connections
- All Herbs
- Willow Bark Overview
- Willow Bark Benefits Hub
- Willow Bark for Pain Management
- Willow Bark Anti-Inflammatory
- Willow Bark for Headache & Migraine
- Aspirin
- Aspirin Health Benefits
- Aspirin Side Effects
- Glycine
- Glycine & Aspirin Metabolism
- Heart Disease
- Atherosclerosis
- Stroke
- Pain Management
- Turmeric
- Ginger
- Magnesium
- History