Migraine

Deep-Dive Articles
Aura & Visual Disturbances
Visual scintillations, scotoma, zig-zag fortifications, sensory aura, aphasic aura, brainstem aura, and hemiplegic migraine. How to recognize aura, stroke look-alikes, and when to go to the ER.
Read the deep dive →Triptans & Gepants (Acute)
Sumatriptan, rizatriptan, eletriptan, and newer gepants (rimegepant, ubrogepant, zavegepant nasal). Timing, routes (oral, nasal, injectable), contraindications, and rescue stacking.
Read the deep dive →CGRP Inhibitors & Preventives
Erenumab, galcanezumab, fremanezumab, eptinezumab, and daily oral CGRP blockers (atogepant, rimegepant). How they work, insurance hurdles, response rates, and when to switch.
Read the deep dive →Chronic Migraine & MOH
15+ headache days/month definition, medication-overuse headache mechanisms, onabotulinumtoxinA injection protocols, and the hardest part — detoxing from overused acute meds.
Read the deep dive →Menstrual & Hormonal Migraine
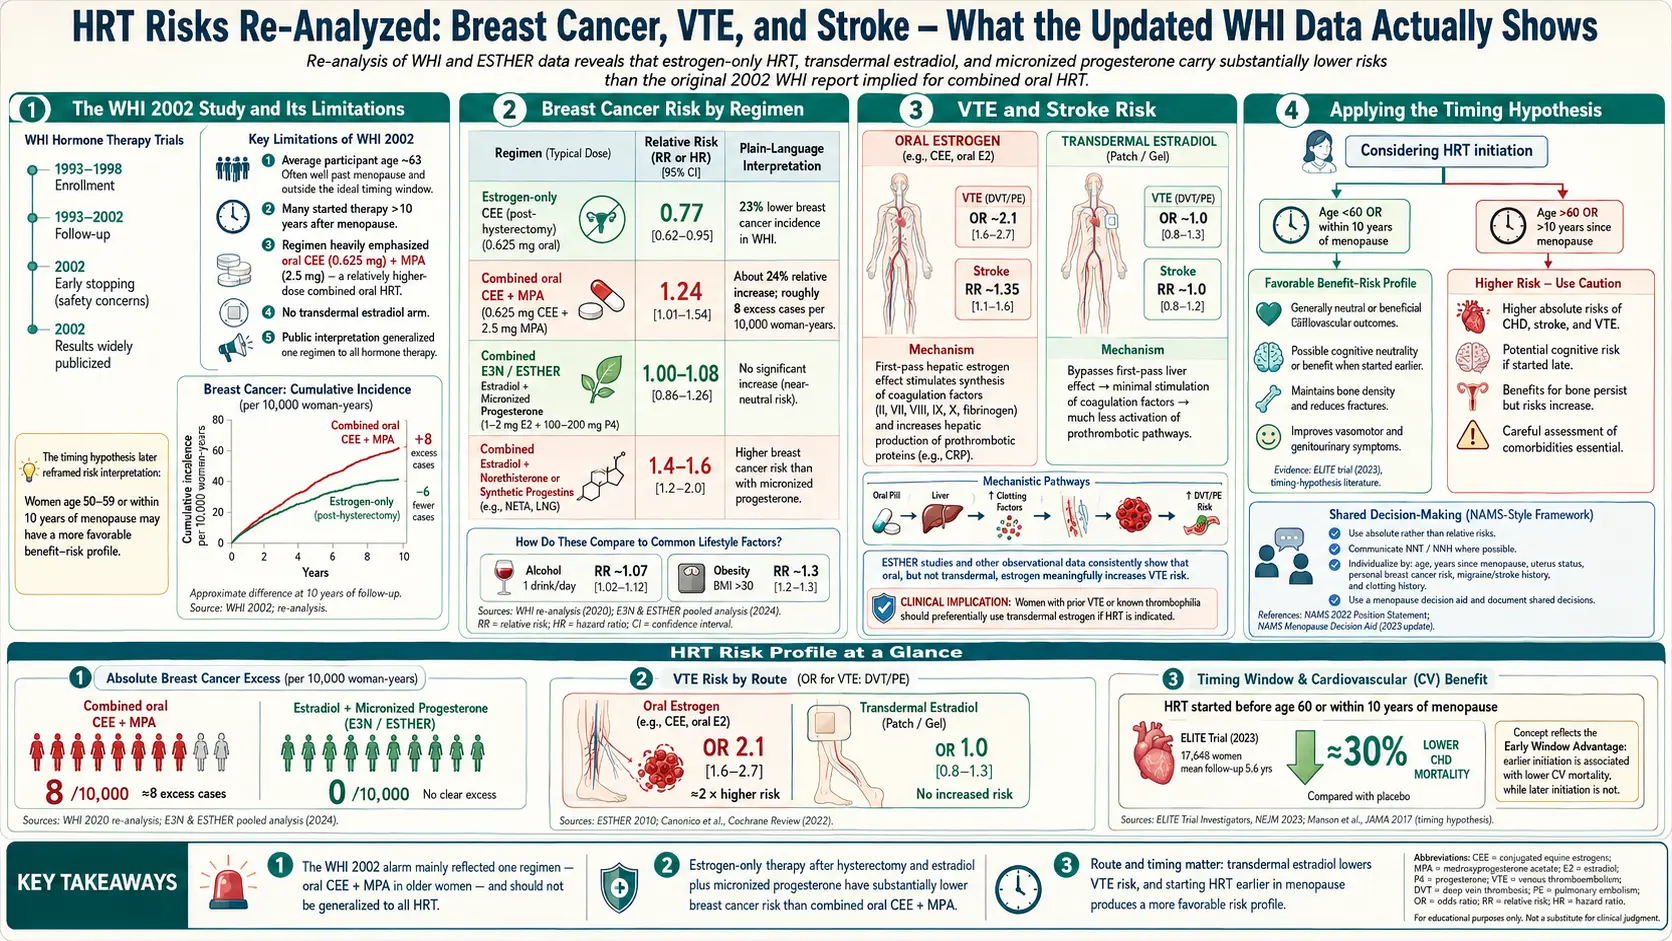
Estrogen withdrawal as trigger, perimenstrual patterns, continuous-dose contraception, mini-prevention with frovatriptan, hormone replacement therapy (HRT) decisions, perimenopause and pregnancy.
Read the deep dive →Vestibular Migraine
Dizziness-dominant migraine, Bárány Society criteria, VEMP/VNG testing, vestibular rehab, and why head pain is often absent in these attacks.
Read the deep dive →Diet Triggers & Elimination
Tyramine, histamine, nitrates, MSG, aspartame, alcohol. A published 6-week elimination protocol, reintroduction methodology, and myth-busting.
Read the deep dive →Magnesium, Riboflavin & Supplements
Rated in the 2012 AAN/AHS guideline: butterbur (PA-free) Level A; magnesium 400-600 mg, riboflavin 400 mg and feverfew Level B; coenzyme Q10 (CoQ10) 300 mg Level C. Dosing, timelines, side effects.
Read the deep dive →Migraine in Pregnancy & Breastfeeding
Safe acute and preventive options, stroke risk, and postpartum flare patterns.
Read the deep dive →Table of Contents
What a Migraine Is
Migraine is a neurological condition characterized by intense, throbbing headaches, often accompanied by other symptoms such as nausea, vomiting, and sensitivity to light and sound. Migraines can last from a few hours to several days and can significantly impact daily life.
Types of Migraines
1. Migraine Without Aura
- Most common type: Characterized by a throbbing headache usually on one side of the head.
- Symptoms: Nausea, vomiting, and sensitivity to light and sound.
2. Migraine With Aura
- Includes sensory disturbances known as "aura" that typically occur before the headache.
- Aura symptoms: Visual disturbances (flashes of light, blind spots), tingling sensations, and difficulty speaking.
3. Chronic Migraine
- Defined by the International Classification of Headache Disorders (ICHD-3) as headache on 15 or more days per month for more than three months, with the features of migraine on at least 8 of those days.
- May be accompanied by more severe symptoms and affect daily functioning.
4. Hemiplegic Migraine
- Rare type: Can cause temporary weakness or paralysis on one side of the body.
- Other symptoms: Dizziness, vision changes, and speech difficulties.
5. Vestibular Migraine
- Associated with vertigo: May or may not include a headache.
- Common in those with a history of motion sickness.
Common Symptoms of Migraine
- Severe, throbbing headache: Often on one side of the head but can affect both sides.
- Nausea and vomiting
- Sensitivity to light and sound
- Visual disturbances: Flashes of light, blind spots, or zigzag patterns.
- Tingling or numbness: Often in the face or hands.
- Dizziness and vertigo
- Fatigue and difficulty concentrating
Causes and Triggers
- Genetics: Family history can increase the risk of developing migraines.
- Hormonal changes: Common in women, especially during menstruation, pregnancy, or menopause.
- Stress: Can trigger or worsen migraines.
- Diet: Certain foods and drinks, such as aged cheese, alcohol (especially red wine), and caffeine, can trigger migraines.
- Environmental factors: Bright lights, loud sounds, or strong smells.
- Sleep disturbances: Both lack of sleep and oversleeping can trigger migraines.
Diagnosis
- Medical history and symptom review: A doctor will evaluate the patient’s history of headaches and related symptoms.
- Neurological examination: To assess brain function and rule out other causes.
- Imaging tests: Such as magnetic resonance imaging (MRI) or computed tomography (CT) scans, to rule out more severe conditions if needed.
Treatment Options
- Medications:
- Pain relievers: Over-the-counter options like ibuprofen and aspirin.
- Triptans: Prescription drugs that can block pain pathways in the brain (e.g., sumatriptan, rizatriptan).
- Gepants: Newer acute tablets that block the calcitonin gene-related peptide (CGRP) receptor, an option for people who cannot take triptans. In the ACHIEVE II trial (1,686 adults), 21.8% of people were pain-free 2 hours after ubrogepant 50 mg, against 14.3% after placebo; nausea (2.0%) and dizziness (1.4%) were no more common than with placebo.
- Preventive medications: Such as beta-blockers, antidepressants, and anticonvulsants, for frequent migraines.
- Calcitonin gene-related peptide (CGRP)-targeting preventives: The antibody injections erenumab, fremanezumab, galcanezumab and eptinezumab, and the gepant tablets rimegepant and atogepant. A 2024 American Headache Society position statement found their evidence “vastly exceeds that for any other preventive treatment approach,” that serious adverse events with them are rare, and that they “should be considered as a first-line approach for migraine prevention” without first failing other classes of preventive drug.
- Anti-nausea drugs: Used to control symptoms like vomiting.
- Lifestyle changes:
- Regular sleep schedule: Helps maintain overall well-being and prevent migraines.
- Stress management: Techniques such as meditation, deep breathing, and yoga.
- Diet modifications: Identifying and cutting out a person’s own food triggers.
- Alternative treatments:
- Acupuncture
- Biofeedback: Helps control physical responses related to stress.
- Herbal supplements: Such as butterbur and feverfew. The 2012 American Academy of Neurology and American Headache Society (AAN/AHS) guideline rated butterbur Level A (effective) and feverfew Level B (probably effective) for preventing migraine; a 2019 review reports that concerns over liver toxicity with butterbur led to that whole guideline being retired, with new guidelines pending.
Prevention Strategies
- A consistent routine: Regular meals, sleep patterns, and physical activity.
- Hydration: Dehydration is a commonly reported migraine trigger.
- Known triggers: Many people keep a headache diary to spot patterns related to diet, stress, or environmental factors, and then steer clear of their own triggers.
- Stress management: Relaxation techniques built into the daily routine.
Complications of Migraines
- Chronic migraine: If migraines become frequent, occurring 15 or more days a month.
- Medication overuse headache: Can result from taking pain relief medications too frequently.
- Impaired quality of life: Affects work, social activities, and overall well-being.
- Mental health issues: Higher risk of depression and anxiety.
Key Research Papers
- Goadsby PJ, Lipton RB, Ferrari MD. Migraine: current understanding and treatment. New England Journal of Medicine. 2002;346(4):257-270. — doi:10.1056/nejmra010917
- Ashina M. Migraine. New England Journal of Medicine. 2020;383(19):1866-1876. — doi:10.1056/nejmra1915327
- GBD 2016 Disease and Injury Incidence and Prevalence Collaborators. Global, regional, and national incidence, prevalence, and years lived with disability for 328 diseases and injuries for 195 countries, 1990-2016: a systematic analysis for the Global Burden of Disease Study 2016. The Lancet. 2017;390(10100):1211-1259. — PubMed PMID: 28919117
- Headache Classification Committee of the International Headache Society. The International Classification of Headache Disorders, 3rd edition (ICHD-3). Cephalalgia. 2018;38(1):1-211. — doi:10.1177/0333102417738202
- Silberstein SD, Dodick DW, Bigal ME, et al. Fremanezumab for the preventive treatment of chronic migraine. New England Journal of Medicine. 2017;377(22):2113-2122. — doi:10.1056/NEJMoa1709038
- Goadsby PJ, et al. A controlled trial of erenumab for episodic migraine. New England Journal of Medicine. 2017;377(22):2123-2132. — doi:10.1056/nejmoa1705848
- Lipton RB, et al. Migraine prevalence, disease burden, and the need for preventive therapy. Neurology. 2007;68(5):343-349. — doi:10.1212/01.wnl.0000252808.97649.21
- Moskowitz MA. The neurobiology of vascular head pain. Annals of Neurology. 1984;16(2):157-168. — doi:10.1002/ana.410160202
- Charles A. The pathophysiology of migraine: implications for clinical management. The Lancet Neurology. 2018;17(2):174-182. — doi:10.1016/s1474-4422(17)30435-0
- Silberstein SD. Preventive migraine treatment. Continuum (Minneap Minn). 2015;21(4 Headache):973-989. — doi:10.1212/con.0000000000000199
- Holland S, et al. Evidence-based guideline update: NSAIDs and other complementary treatments for episodic migraine prevention in adults. Neurology. 2012;78(17):1346-1353. — doi:10.1212/wnl.0b013e3182535d0c
- Dodick DW. A phase-by-phase review of migraine pathophysiology. Headache. 2018;58(Suppl 1):4-16. — doi:10.1111/head.13300
- Lipton RB, Dodick DW, Ailani J, et al. Effect of ubrogepant vs placebo on pain and the most bothersome associated symptom in the acute treatment of migraine: the ACHIEVE II randomized clinical trial. JAMA. 2019;322(19):1887-1898. — doi:10.1001/jama.2019.16711
- Charles AC, Digre KB, Goadsby PJ, et al. Calcitonin gene-related peptide-targeting therapies are a first-line option for the prevention of migraine: an American Headache Society position statement update. Headache. 2024;64(4):333-341. — doi:10.1111/head.14692
- Wells RE, Beuthin J, Granetzke L. Complementary and integrative medicine for episodic migraine: an update of evidence from the last 3 years. Current Pain and Headache Reports. 2019;23(2):10. — doi:10.1007/s11916-019-0750-8
Historical Background
Migraine has been described since antiquity, with Hippocrates documenting visual aura symptoms around 400 BCE. The term "hemicrania" was coined by Galen in the 2nd century CE. Thomas Willis provided the first modern medical description in 1672. Harold Wolff's vascular theory dominated the 20th century until the discovery of the trigeminovascular system by Michael Moskowitz in the 1980s. The development of triptans by Pat Humphrey in 1991 revolutionized acute migraine treatment.
PubMed Topic Searches
Explore current literature on migraine via PubMed topic searches. These links open live PubMed searches for the listed keywords — results update as new studies are indexed.
- Clinical trials on migraine — PubMed search
- Clinical trials on CGRP antagonist migraine — PubMed search
- Clinical trials on migraine prophylaxis — PubMed search
- Clinical trials on triptan acute migraine — PubMed search
- Clinical trials on chronic migraine botulinum toxin — PubMed search
- Clinical trials on migraine aura pathophysiology — PubMed search
- Clinical trials on vestibular migraine — PubMed search
Connections
- Pain & Allergy
- What Happens in a Migraine — interactive animation
- Vestibular Migraine
- Migraine in Pregnancy and Breastfeeding
- Chronic Migraine and Medication Overuse
- Magnesium, Riboflavin, and Supplements
- Menstrual Migraine and Hormonal Triggers
- Diet Triggers and Elimination Protocol
- CGRP Inhibitors and Preventives
- Triptans and Gepants — Acute Treatment
- Aura and Visual Disturbances
- Headache
- Magnesium
- Depression
- Anxiety
- Dizziness
- Nausea and Vomiting
- Chronic Pain
- Insomnia
- Vertigo and Meniere's Disease
- Dr. Bryan Ardis: Nicotine Patches for Arthritis
- Allergies
- Feverfew
Featured Videos