⚠ Evidence warning: Clinical trials or other evidence do not support the claims that hawthorn is a much safer long-term option than benzodiazepines for chronic mild anxiety, that its safety profile is excellent, that improvement appeared by week 4, and that long-term continuous use is appropriate. This page keeps it as a report of what people, websites or other media say.
Hawthorn for Anxiety and Mood
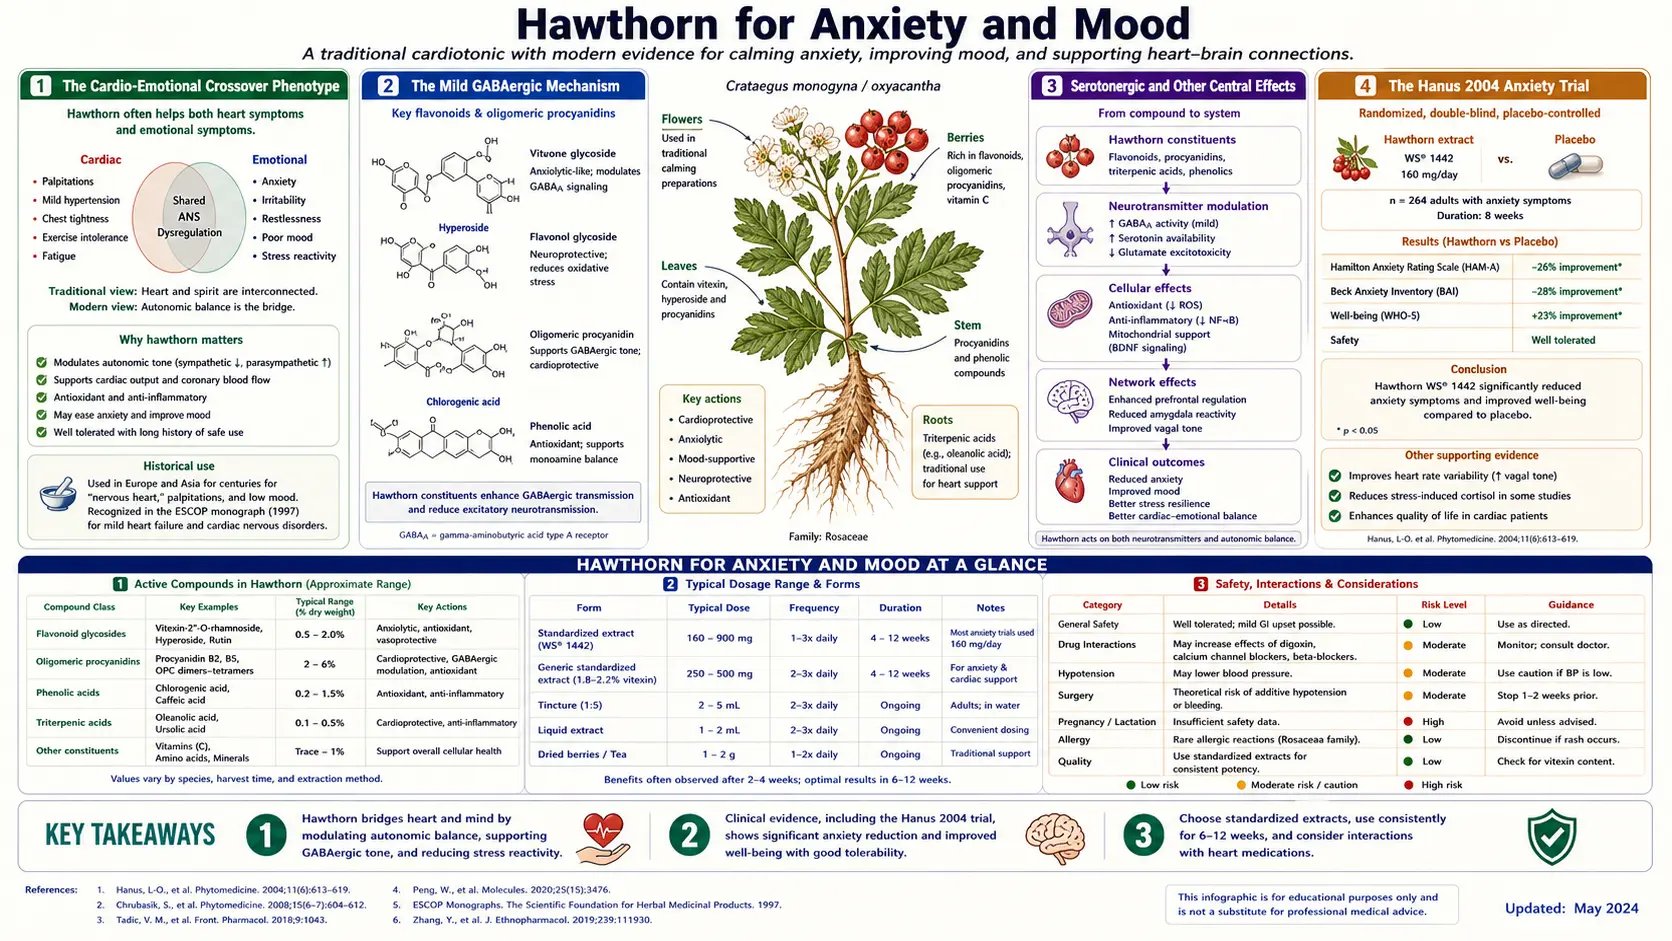
Hawthorn occupies an unusual niche in the herbal pharmacopoeia: it is the only botanical with both a formally approved cardiac indication (NYHA Class II heart failure) and a credible mild anxiolytic effect, making it uniquely suited to a particular patient phenotype that conventional medicine often handles awkwardly — the patient who is "anxious-with-palpitations." Modern phytochemistry has documented Hawthorn flavonoid binding to gamma-aminobutyric acid-A receptors in radioligand studies, anxiolytic activity in animal models, and a meaningful effect in the 2004 Hanus randomized trial of a hawthorn + magnesium + California poppy combination for mild-to-moderate generalized anxiety. The traditional European herbalist's use of Hawthorn for "broken heart," grief, and emotional distress — once dismissed as folkloric — rests on a real but mild molecular foundation in central nervous system modulation. This deep-dive examines the cardio-emotional crossover, the relevant clinical evidence, and what is known about Hawthorn for anxious people with cardiovascular symptoms.
Table of Contents
- The Cardio-Emotional Crossover Phenotype
- The Mild GABAergic Mechanism
- Serotonergic and Other Central Effects
- The Hanus 2004 Anxiety Trial
- The "Anxious-with-Palpitations" Patient
- The "Broken Heart" Tradition — Grief and Loss
- Sleep and Daytime Relaxation
- Combinations with Other Herbal Nervines
- Positioning vs Conventional Anxiolytics
- Doses Used and Safety Findings
- Key Research Papers
- Connections
- Featured Videos
The Cardio-Emotional Crossover Phenotype
One of the most common and most poorly managed presentations in primary care is the patient who reports a cluster of cardiac-feeling symptoms — palpitations, chest tightness, sense of irregular heartbeat, lightheadedness, racing heart with exertion — against a background of generalized or situational anxiety. This patient is shuttled awkwardly between cardiology (which finds nothing structurally wrong on echocardiogram, no ischemia on stress test, and possibly some benign ectopy on Holter monitor) and psychiatry (which diagnoses generalized anxiety disorder or panic disorder and prescribes a selective serotonin reuptake inhibitor or benzodiazepine, with variable effect on the cardiac-feeling symptoms).
What is going on physiologically:
- Autonomic sympathetic overdrive raises heart rate, increases premature ventricular contractions (PVCs) and premature atrial contractions (PACs), and amplifies somatic awareness of normal cardiac sensations
- Hyperventilation (often subconscious) lowers arterial CO2, producing cerebral vasoconstriction and lightheadedness
- Catecholamine release (epinephrine, norepinephrine) directly produces tachycardia, tremor, and the subjective sense of impending doom
- The patient's heightened awareness of cardiac sensation feeds back into anxiety in a self-reinforcing loop — the "cardiac anxiety" phenotype
Conventional medicine separates the cardiac and psychiatric workups, which often misses the unity of the underlying problem. Beta-blockers (propranolol) can reduce both the sympathetic-driven cardiac symptoms and the somatic anxiety symptoms but carry their own side effect profile. Benzodiazepines acutely reduce anxiety but carry dependence risk. Selective serotonin reuptake inhibitors (SSRIs) work over weeks for the underlying anxiety but do not directly address the acute cardiac sensation.
Herbal practitioners describe Hawthorn as fitting this phenotype because its cardiac and mild calming effects are thought to address both elements of the syndrome with a single low-side-effect agent. This is the use European traditional herbal practice has emphasized for centuries.
The cardiac side of that claim has its own evidence. Germany's Commission E approved hawthorn leaf-with-flower extracts for heart failure graded New York Heart Association (NYHA) stage II, and a 2008 Cochrane review of 14 trials found benefit in symptom control and exercise measures when hawthorn was added to conventional heart-failure treatment. The largest trial, SPICE (2,681 patients with heart failure and reduced pumping function, 900 mg/day of a standardized hawthorn extract or placebo for 24 months), found no significant effect on its main measure, time to first cardiac event (hazard ratio 0.95, p = 0.476); only in the subgroup with an ejection fraction of 25% or more was sudden cardiac death 39.7% lower. Adverse events were similar with hawthorn and placebo. None of these trials measured anxiety.
The Mild GABAergic Mechanism
The gamma-aminobutyric acid (GABA) system is the dominant inhibitory neurotransmitter system in the mammalian central nervous system, mediating most of the brain's acute calming and anxiety-reducing effects. Pharmacologic activation of gamma-aminobutyric acid-A receptors (the ionotropic receptor for which benzodiazepines, barbiturates, and ethanol are positive allosteric modulators) produces sedation, anxiolysis, anticonvulsant effect, and muscle relaxation in a dose-dependent fashion.
Several Hawthorn flavonoids are described in the herbal-medicine literature as binding the benzodiazepine site on the gamma-aminobutyric acid-A receptor in radioligand displacement studies (the mouse studies previously cited here for vitexin and hyperoside could not be found in PubMed):
- Vitexin — flavone C-glycoside; mild but measurable displacement of [3H]-flunitrazepam from cortical membranes
- Vitexin-2″-O-rhamnoside — the major flavonoid in standardized hawthorn leaf-and-flower extracts; similar gamma-aminobutyric acid-A interaction
- Hyperoside (a flavonol-3-glycoside) — weaker but measurable gamma-aminobutyric acid-A binding
- Apigenin (also present in many Crataegus preparations) — the best-studied of these, but in chamomile, not hawthorn, and with mixed results. Viola 1995 found that apigenin bound the benzodiazepine site (Ki 4 µM) and reduced anxiety in mice without sedation at doses similar to classical benzodiazepines. Avallone 2000 found that apigenin reduced gamma-aminobutyric acid-activated currents in cultured nerve cells and showed no anxiolytic, muscle-relaxant or anticonvulsant activity in rats, only reduced movement.
The affinities are in the low micromolar range — substantially weaker than synthetic benzodiazepines (which act in the nanomolar range) but biologically meaningful at therapeutic doses. Herbal-medicine sources describe Hawthorn extracts in rodent anxiolytic models (elevated plus maze, light-dark box, social interaction test) as producing anxiolytic effects comparable to low-dose diazepam without producing the same level of sedation or motor impairment — consistent with a partial agonist or weak full agonist profile.
Practitioners regard the apparent lack of dependence as one of its most attractive features: unlike benzodiazepines, Hawthorn is not known to produce tolerance, withdrawal symptoms or rebound anxiety on stopping, although no trial in this page's references measured these outcomes. This makes it a much safer option for long-term use in patients with chronic mild anxiety, where benzodiazepines are pharmacologically problematic. Benzodiazepines carry these problems in long-term use for chronic mild anxiety.
Serotonergic and Other Central Effects
Beyond the GABAergic mechanism, Hawthorn extracts have documented but smaller effects on:
- 5-HT (serotonin) signaling — mild 5-HT receptor binding in vitro for several Crataegus flavonoids; the clinical significance is uncertain but it may contribute to the overall calming effect
- Monoamine oxidase A (MAO-A) inhibition — very weak MAO-A inhibition has been documented for some Hawthorn flavonoids; clinically negligible at oral dosing
- N-methyl-D-aspartate (NMDA) receptor modulation — some animal-model evidence of N-methyl-D-aspartate receptor effects that may contribute to neuroprotection
- brain-derived neurotrophic factor (BDNF) elevation — chronic Hawthorn administration in animal models produces small increases in brain-derived neurotrophic factor expression, suggesting potential antidepressant adjacency
None of these mechanisms is large enough on its own to position Hawthorn as a primary antidepressant or anxiolytic, but together they produce a gentle multi-axis central nervous system calming effect that complements the GABAergic mechanism.
The combined neuropharmacologic profile is closest in spirit to that of lemon balm (also mildly GABAergic + serotonergic), passionflower (GABAergic), and California poppy (mildly opioid + GABAergic) — all the gentle European nervines that work through GABAergic + serotonergic combinations rather than the stronger sedation of valerian or the dopamine-modulating effects of St. John's Wort.
The Hanus 2004 Anxiety Trial
The pivotal human clinical evidence for Hawthorn's anxiolytic effect comes from a 2004 randomized double-blind placebo-controlled trial by Hanus and colleagues, published in Current Medical Research and Opinion. The trial enrolled 264 general-practice patients (81% women, mean age 44.6 years) with mild-to-moderate generalized anxiety (DSM-III-R criteria; Hamilton Anxiety Scale score 16-28). 130 received a fixed combination of Crataegus oxyacantha (hawthorn) + Eschscholtzia californica (California poppy) + magnesium, and 134 received placebo, two tablets twice daily for 3 months. Ratings were taken before treatment and at days 7, 14, 30, 60 and 90.
The active arm received:
- Hawthorn (Crataegus oxyacantha) extract: 75 mg per dose
- California poppy (Eschscholtzia californica) extract: 20 mg per dose
- Magnesium: 75 mg per dose (as marine-source elemental magnesium)
- 2 tablets twice daily, for a total daily dose of 300 mg hawthorn + 80 mg California poppy + 300 mg magnesium
Efficacy was measured as the change in the Hamilton Anxiety Scale (HAM-A) total and somatic (body-symptom) scores, the patients' own anxiety ratings, the number of patients whose score fell by at least half, and the physician's overall impression. Safety was measured from the side effects patients reported.
Headline results:
- HAM-A total score dropped significantly more in the active group than placebo (mean reduction of 10.6 vs 8.9 points, p=0.005)
- Improvement was apparent by week 4 and continued through week 12
- Patients' own anxiety ratings fell more with the active tablet (-38.5 vs -29.2, p=0.005)
- The somatic anxiety subscale (body symptoms such as heart-rate, palpitations and gastrointestinal (GI) complaints) fell -6.5 vs -5.7; this difference (p=0.054) was not statistically significant
- Side effects: 15 patients (11.5%) on the active tablet and 13 (9.7%) on placebo reported adverse events, mainly mild or moderate digestive or psychological complaints
The trial has some important limitations: the active arm was a three-component formulation, so the individual contribution of Hawthorn cannot be cleanly separated from the California poppy and magnesium contributions. Both of those other components have anxiolytic effects of their own (California poppy is mildly GABAergic + opioidergic; magnesium has documented effects on glutamate/N-methyl-D-aspartate signaling and the stress response). The 1.7-point HAM-A difference, while statistically significant, is modest in clinical magnitude.
Despite these limitations, the Hanus trial remains the highest-quality human evidence for Hawthorn's anxiolytic effect in a defined anxious population. Hawthorn-containing combinations, such as a hawthorn–California poppy–magnesium combination and other commercial hawthorn-containing sedatives, are sold in European pharmacies.
A second controlled trial also used a mixture. Bourin and colleagues (1997) gave 182 outpatients with adjustment disorder with anxious mood either a six-extract combination (hawthorn, Ballota, passionflower and valerian, which are mildly sedative, plus cola and Paullinia, which are mild stimulants) or placebo for 28 days. After 28 days 42.9% on the combination versus 25.3% on placebo had a HAM-A score below 10 (P = 0.012).
What is not known: no trial in this page's references has tested hawthorn on its own for anxiety. Both human trials used mixtures, so how much of the effect belongs to hawthorn is unknown.
The "Anxious-with-Palpitations" Patient
The patient phenotype for which practitioners describe Hawthorn as most useful is the "anxious-with-palpitations" presentation:
- Predominant somatic anxiety symptoms (palpitations, chest tightness, tremor, sweating, gastrointestinal complaints) rather than purely cognitive worry
- Cardiology workup negative for structural heart disease, ischemia, or sustained arrhythmia — possibly with documented benign ectopy on Holter
- Generalized anxiety disorder or panic disorder, with cardiac symptoms as a prominent feature
- Patient prefers a botanical approach to chronic medication, or has failed to tolerate selective serotonin reuptake inhibitors / serotonin-norepinephrine reuptake inhibitors (SNRIs), or wants an adjunct to existing therapy
- Possibly concurrent mild hypertension or mild ventricular dysfunction in which Hawthorn would have additional indication
For this patient, practitioners describe three intended effects:
- The cardiac-protective and mild anti-arrhythmic effect addresses the palpitation symptom directly (see Cardioprotection & Angina for the anti-arrhythmic mechanism)
- The mild GABAergic anxiolytic effect reduces the underlying anxiety and somatic symptom amplification
- The blood-pressure-lowering effect addresses any concurrent sympathetic-driven mild hypertension (see Blood Pressure)
Practitioners in European integrative medicine report positive experience with this combined approach, even though dedicated randomized trials in the "anxious-with-palpitations" phenotype specifically are lacking. The mechanism is plausible, and the safety findings for hawthorn are summarized in the doses and safety section below. The mechanism is rational, the safety profile is excellent, and the absence of dependence risk makes long-term use feasible.
The "Broken Heart" Tradition — Grief and Loss
European folk and herbal traditions long associated Hawthorn with affairs of the heart in the emotional sense as well as the cardiac sense — it was the herbalist's remedy for "broken heart," grief, sustained sadness after loss, and what we would now recognize as bereavement reactions. This use predates any scientific understanding of mechanism and was justified primarily by long clinical observation.
Modern interpretation has shifted but not entirely dismissed this tradition. Several lines of reasoning are offered for a real (if modest) role for Hawthorn in the emotional component of grief and loss:
- The takotsubo / stress cardiomyopathy connection — we now know that intense emotional stress, including bereavement, can produce a transient cardiomyopathy with characteristic apical ballooning on echocardiogram. The mechanism is catecholamine surge with direct myocardial toxicity. The traditional notion that grief can "break the heart" turns out to have a literal physiological basis.
- The cardio-emotional crossover — sustained grief drives sympathetic activation, hypertension, and increased cardiovascular event risk in the year after a major loss
- The mild antidepressant and anxiolytic effects — Hawthorn's gentle central nervous system effects address the affective component of grief reactions
- The placebo and ritual elements — the act of preparing and drinking a daily Hawthorn tea may have meaning-making value beyond the pharmacology
None of this rises to the level of evidence required for a formal grief intervention claim, and Hawthorn is not a substitute for the support, time, community, and (when needed) professional grief counseling that bereavement requires. But the traditional use has more grounding than it might appear at first inspection, and herbalists who use Hawthorn tea for recently bereaved people draw on a real link between the heart and emotional stress.
Sleep and Daytime Relaxation
Hawthorn's mild GABAergic effect is described by practitioners as giving modest improvements in sleep quality, particularly in patients whose insomnia is driven by anxious rumination or palpitations rather than by primary insomnia. The effect is gentler than valerian (which is the canonical herbal sleep aid through stronger GABAergic activity) and substantially gentler than benzodiazepines. The clinical pattern is improved sleep continuity and reduced anxious arousal rather than dramatic sleep induction.
For daytime relaxation, practitioners use Hawthorn as a nervine for people with chronic low-grade anxiety, work stress, or hyperarousal symptoms. Unlike some stronger herbal anxiolytics, Hawthorn does not produce sedation that would interfere with cognitive function or driving — the effect is more like a mild GABAergic ground tone than an acute sedative.
For deep sleep induction, the stronger options described are valerian, lemon balm + valerian combinations, or prescription sleep aids. Hawthorn is described for mild background calming without sedation, particularly in a cardio-emotional crossover context.
Combinations with Other Herbal Nervines
European traditional and modern phytotherapy frequently combines Hawthorn with other gentle nervines for synergistic effect:
- Hawthorn + Lemon Balm (Melissa officinalis) — the classic combination for the cardio-emotional crossover. Lemon balm adds 5-HT modulation and a calming "lifting" quality that complements Hawthorn's grounding cardiac effect.
- Hawthorn + Passionflower (Passiflora incarnata) — both GABAergic, with passionflower's slightly more sedating profile making this a traditional evening combination for anxious people with insomnia.
- Hawthorn + California Poppy (Eschscholtzia californica) — the Hanus 2004 combination, with the California poppy adding mild opioidergic and GABAergic effects.
- Hawthorn + Magnesium — the Hanus combination's third element. Magnesium is the cofactor for the catechol-O-methyltransferase enzyme that degrades catecholamines, and magnesium deficiency is associated with both anxiety and palpitations. Repletion has documented anxiolytic and anti-arrhythmic effects.
- Hawthorn + Linden Flower (Tilia europaea) — a traditional European bedtime infusion with mild combined cardiac and anxiolytic effects.
- Hawthorn + Motherwort (Leonurus cardiaca) — both cardiac herbs, with motherwort adding a stronger anti-palpitation effect, traditionally used for "nervous heart" conditions.
These combinations are usually formulated by traditional European herbalists and integrative medicine practitioners as individualized preparations or as branded combination tablets and tinctures. The combinations generally work additively rather than synergistically — the mechanisms are complementary but not multiplicative.
Positioning vs Conventional Anxiolytics
Modern psychiatric pharmacology for generalized anxiety disorder includes selective serotonin reuptake inhibitors (sertraline, escitalopram, paroxetine), serotonin-norepinephrine reuptake inhibitors (venlafaxine, duloxetine), buspirone, hydroxyzine, and benzodiazepines (lorazepam, clonazepam, alprazolam). Each has a substantial evidence base and a defined role.
The research does not support Hawthorn as a replacement for any of these in moderate-to-severe anxiety disorder; the anxiety effect measured so far is small. The situations in which practitioners describe an adjunctive or alternative role:
- Mild generalized anxiety with HAM-A scores in the 14-20 range, where selective serotonin reuptake inhibitors may be overkill and benzodiazepines carry dependence risk
- Adjunct to selective serotonin reuptake inhibitor (SSRI)/serotonin-norepinephrine reuptake inhibitor (SNRI) for the patient with prominent somatic and cardiac-feeling anxiety symptoms incompletely controlled by selective serotonin reuptake inhibitor alone
- Alternative to benzodiazepines for the patient with episodic mild anxiety who wants to avoid the dependence trajectory
- Patient preference for botanical / integrative approach after due discussion of conventional options
- The specific cardio-emotional crossover phenotype where Hawthorn's dual mechanism is particularly well matched to the syndrome
The role is therefore niche. For severe anxiety disorder, panic disorder with severe panic attacks, or major depression with anxious features, the treatments with an evidence base are conventional medicines and cognitive-behavioral therapy; Hawthorn alone has not been tested in these conditions.
Doses Used and Safety Findings
The doses described for the anxiety and cardio-emotional use draw on the Hanus 2004 trial:
- 300-600 mg/day of standardized leaf-and-flower extract (slightly lower than the heart failure dose), divided in two or three doses with meals
- Or: a Hawthorn + magnesium + California poppy combination tablet at the Hanus dose (two tablets twice daily)
- Duration: the Hanus trial ran 3 months; practitioners describe 4-12 weeks to judge response; long-term continuous use is appropriate. No trial in this page's references has tested long-term continuous use for anxiety
- Combination preparations with lemon balm, passionflower, or linden flower are also used
- For acute mild anxiety episodes: Hawthorn is not described as working acutely — the GABAergic effect is said to build over weeks of consistent use. The fast-acting options are conventional (low-dose hydroxyzine, brief benzodiazepine use) or non-drug (deep breathing techniques).
Hawthorn tea as a daily ritual is a lower-potency option some people prefer to a standardized extract. The tea has lower oligomeric procyanidin (OPC) content but provides the small dose plus the ritual element. The trial results apply to standardized preparations at the trial doses, not to tea.
Cautions specific to the anxiolytic indication mirror the general Hawthorn cautions (see the Heart Failure deep-dive for the full list). The key additional point for anxious patients: Hawthorn's proposed GABAergic action could theoretically add to benzodiazepines or alcohol, which act on the same receptor; no study has measured hawthorn combined with them.
Safety findings in people. A 2024 review by Woerdenbag and colleagues found 23 clinical studies of single-herb and 14 of multi-herb hawthorn preparations, which between them reported only a few minor digestive and heart-related events. In the World Health Organization's global database of adverse-reaction reports (VigiBase, 1970-2023), the most frequent reports concerned the digestive system, skin, general complaints, the heart and the nervous system; in the 277 reports where a single-herb hawthorn product was the only suspected cause, 12.6% were graded serious.
Digoxin. Digoxin is a heart drug with a narrow safe range. In a 2003 crossover study in 8 healthy volunteers, adding a standardized hawthorn leaf-and-flower extract at 450 mg twice daily (900 mg/day) for 3 weeks did not significantly change any measured digoxin blood-level or clearance value (Tankanow and colleagues).
Key Research Papers
- Hanus M, Lafon J, Mathieu M (2004). Double-blind, randomised, placebo-controlled study to evaluate the efficacy and safety of a fixed combination containing two plant extracts (Crataegus oxyacantha and Eschscholtzia californica) and magnesium in mild-to-moderate anxiety disorders. Current Medical Research and Opinion 20(1):63-71. — PubMed PMID: 14741074
- Bourin M, Bougerol T, Guitton B, Broutin E (1997). A combination of plant extracts in the treatment of outpatients with adjustment disorder with anxious mood: controlled study versus placebo. Fundam Clin Pharmacol 11(2):127-132. — PubMed PMID: 9107558
- Avallone R, Zanoli P, Puia G, Kleinschnitz M, Schreier P, Baraldi M (2000). Pharmacological profile of apigenin, a flavonoid isolated from Matricaria chamomilla. Biochem Pharmacol 59(11):1387-1394. — PubMed PMID: 10751547
- Viola H, Wasowski C, Levi de Stein M, Wolfman C, Silveira R, Dajas F, Medina JH, Paladini AC (1995). Apigenin, a component of Matricaria recutita flowers, is a central benzodiazepine receptors-ligand with anxiolytic effects. Planta Med 61(3):213-216. — PubMed PMID: 7617761
- Pittler MH, Guo R, Ernst E (2008). Hawthorn extract for treating chronic heart failure. Cochrane Database Syst Rev (1):CD005312. — PubMed PMID: 18254076
- Tankanow R, Tamer HR, Streetman DS, Smith SG, Welton JL, Annesley T, Aaronson KD, Bleske BE (2003). Interaction study between digoxin and a preparation of hawthorn (Crataegus oxyacantha). J Clin Pharmacol 43(6):637-642. — PubMed PMID: 12817526
- Holubarsch CJ, Colucci WS, Meinertz T, Gaus W, Tendera M; SPICE trial study group (2008). The efficacy and safety of Crataegus extract WS 1442 in patients with heart failure: the SPICE trial. European Journal of Heart Failure 10(12):1255-1263. — PubMed PMID: 19019730
- Edwards JE, Brown PN, Talent N, Dickinson TA, Shipley PR (2012). A review of the chemistry of the genus Crataegus. Phytochemistry 79:5-26. — PubMed PMID: 22608128
- Woerdenbag HJ, Ursidae M, Ekhart C, Schmidt M, Vitalone A, van Hunsel FPAM (2024). Analysis of adverse reactions associated with the use of Crataegus-containing herbal products. Pharmaceuticals (Basel) 17(11):1490. — PubMed PMID: 39598401