⚠ Evidence warning: Clinical trials or other evidence do not support the claim that hawthorn prevents heart attacks, relieves stable, microvascular or vasospastic angina, eases atrial fibrillation and aids recovery after a heart attack. This page keeps it as a report of what people, websites or other media say.
Hawthorn for Cardioprotection and Angina
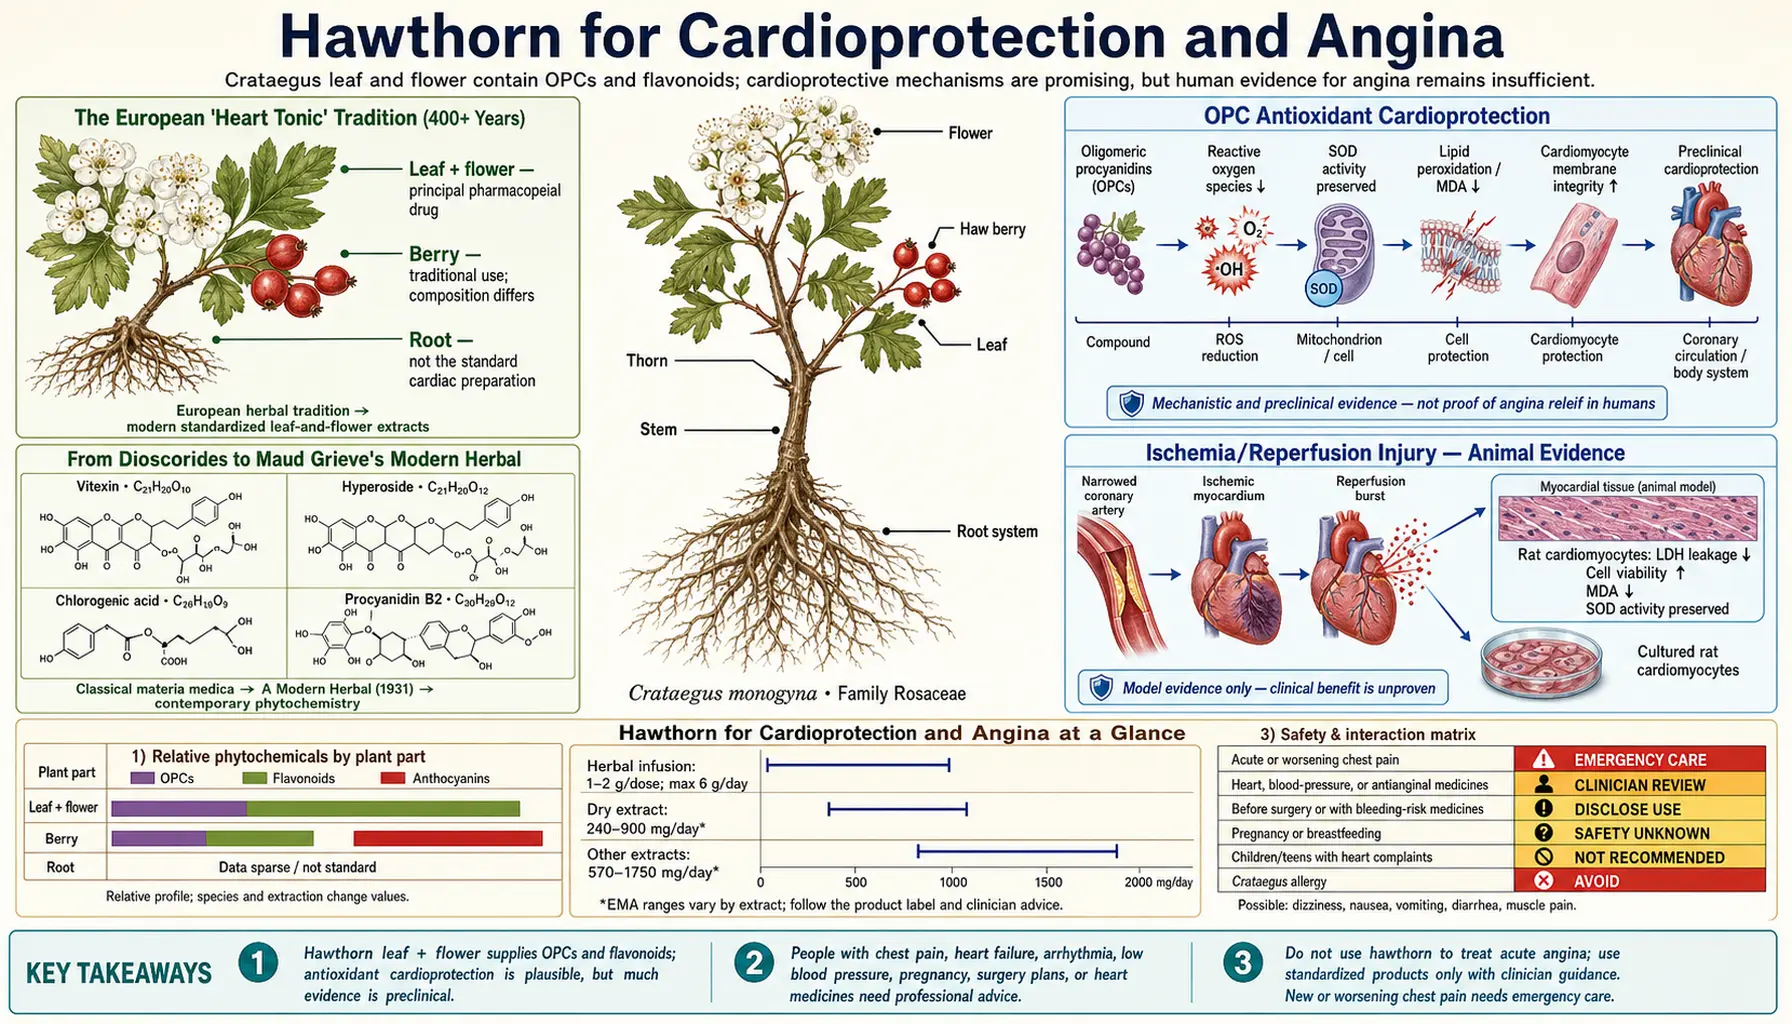
Beyond its formally approved indication for New York Heart Association (NYHA) Class II heart failure, Hawthorn has been used for over four centuries in European herbal medicine as a general "heart tonic" a gentle daily preparation for cardiac strengthening, prevention of ischemic events, and management of stable angina. Modern phytochemistry has explained much of this traditional use: Hawthorn flavonoids prolong the cardiac effective refractory period (anti-arrhythmic), oligomeric proanthocyanidins (OPCs) are among the most potent reactive-oxygen-species scavengers in the plant kingdom (cardioprotective against ischemia-reperfusion injury), and the combined OPC + flavonoid fraction increases coronary blood flow through endothelial nitric oxide release (anti-anginal). This deep-dive examines the cardioprotective and anti-anginal evidence, traces the long European history of the "heart herb" from Dioscorides through Grieve's 1931 Modern Herbal, and outlines how Hawthorn has been positioned for people with ischemic heart disease, stable angina, or atrial fibrillation.
Table of Contents
- The European "Heart Tonic" Tradition (400+ Years)
- From Dioscorides to Maud Grieve's Modern Herbal
- OPC Antioxidant Cardioprotection
- Ischemia/Reperfusion Injury — Animal Evidence
- The Anti-Arrhythmic Mechanism
- Stable Angina — Clinical Evidence
- Atrial Fibrillation Considerations
- Coronary Blood Flow Enhancement
- Post-Myocardial-Infarction Recovery
- Where Hawthorn Has Been Proposed in Heart Care
- Key Research Papers
- Connections
- Featured Videos
The European "Heart Tonic" Tradition (400+ Years)
Hawthorn (Crataegus) has been the European traditional remedy for cardiac complaints since at least the sixteenth century, when it first appears in vernacular herbals as a treatment for "weakness of the heart," "palpitations," and "cardiac exhaustion." By the eighteenth century it was an established item in continental European pharmacopoeias under the indication of tonicum cordis — a tonic for the heart.
The phrase "heart tonic" in the herbalist's lexicon meant something specific that has no direct equivalent in modern allopathic pharmacology. A tonic was understood as a long-term restorative agent that strengthened an organ's function without producing dramatic acute effects — closer in spirit to a vitamin or a structural support than to a drug. The patient was expected to take a tonic daily for months or years, not for a discrete pharmacologic event, and the benefit was expected to emerge slowly. This is in fact the pattern modern trials have confirmed for Hawthorn: the effect develops over 6-8 weeks, the magnitude is modest, and continuous long-term use is the well-established mode.
The most influential nineteenth-century clinical advocate was Irish-American physician Charles Cullen Greene, whose 1896 paper in the New York Medical Journal described striking clinical improvement in patients with "cardiac decompensation" treated with Hawthorn tincture. Greene's observations spread rapidly through North American eclectic and homeopathic practice and back to Europe, where they reinforced the existing herbal tradition and inspired more systematic phytochemical investigation in the twentieth century.
By the 1930s, German physiologists had begun to isolate the active fractions. By the 1970s, the OPC content of the leaf-and-flower extract had been characterized and standardized. The 1984 German Commission E approval was followed by two large modern heart-failure trials, SPICE and HERB CHF. Both were null on their main outcomes, and HERB CHF found more adverse events in the hawthorn group.
In SPICE (2,681 patients with heart failure, 900 mg a day of the WS 1442 extract or placebo for 24 months), the extract had no significant effect on the main outcome, time to the first cardiac event (hazard ratio 0.95), and the trend toward fewer cardiac deaths was not statistically significant; adverse events were comparable in both groups. The HERB CHF trial gave 120 people with heart failure (New York Heart Association class II–III), all on standard medicines, 450 mg of hawthorn twice a day or placebo for 6 months. It found no difference in 6-minute walking distance, quality of life, exercise capacity, hormone markers, or markers of oxidative stress and inflammation; a modest difference in left ventricular ejection fraction favoured hawthorn, and there were significantly more adverse events in the hawthorn group, most of them not heart-related. Its authors concluded that hawthorn "provides no symptomatic or functional benefit when given with standard medical therapy to patients with heart failure."
From Dioscorides to Maud Grieve's Modern Herbal
The earliest documented medicinal use of Hawthorn appears in the first-century AD De Materia Medica of the Greek physician Pedanius Dioscorides, who recommended the fruit and bark for digestive complaints rather than for cardiac use. The specifically cardiac indication emerges later, in the early-modern European herbal tradition.
Key historical sources documenting the cardiac use:
- John Gerard, Herball (1597) — references the use of Hawthorn berries to "stay the bloody flux" but does not yet emphasize cardiac use
- Nicholas Culpeper, The English Physitian Enlarged (1653) — recommends Hawthorn for "stones in the kidneys" and dropsy (which we now recognize as cardiac edema)
- French and German pharmacopoeial monographs (eighteenth century) — the cardiac indication becomes formalized
- Maud Grieve, A Modern Herbal (1931) — the canonical English-language reference of the early twentieth century, which devotes a substantial chapter to Hawthorn and quotes Greene's 1896 observations approvingly. Grieve writes: "The fruit is an excellent cardiac tonic, useful in organic and functional heart troubles."
Grieve's entry captures the early-twentieth-century state of knowledge well. By her account, Hawthorn was used clinically for:
- "Functional heart trouble" (what we would now call anxious palpitations — see the Anxiety & Mood deep-dive)
- "Organic heart trouble" (structural heart disease, the modern equivalent of valvular disease and dilated cardiomyopathy)
- "Dropsy" (peripheral edema from cardiac failure)
- "Insomnia and nervousness arising from cardiac irritability"
This pattern of use — spanning structural heart disease, arrhythmia, edema, and the cardio-emotional crossover — is remarkably close to the indications modern phytochemistry has validated. The traditional knowledge was substantially correct; what modern research has added is mechanism, standardization, and dose-response.
OPC Antioxidant Cardioprotection
Oligomeric proanthocyanidins (OPCs) are among the most potent free-radical scavengers in the plant kingdom on a mole-for-mole basis. They sit alongside the proanthocyanidins of grape seed extract, pine bark, and dark cocoa as the dominant dietary source of high-potency polyphenolic antioxidants. The mechanism is direct hydrogen-atom transfer from the catechin / epicatechin hydroxyl groups to reactive oxygen species (ROS), neutralizing them before they can damage cellular structures.
In the cardiovascular system, the relevant reactive oxygen species are:
- Superoxide anion (O2•-) — generated by reduced nicotinamide adenine dinucleotide phosphate (NADPH) oxidase in inflammatory cells and by mitochondrial electron transport chain leak; principal driver of vascular endothelial dysfunction
- Hydroxyl radical (•OH) — the most reactive oxygen species; generated by the Fenton reaction; principal driver of cellular lipid peroxidation and DNA damage
- Peroxynitrite (ONOO-) — generated from NO + O2•- combination; nitrates protein tyrosines and impairs endothelial nitric oxide synthase (eNOS) function
- Lipid hydroperoxides — oxidized phospholipids and oxidized low-density lipoprotein (LDL); drive atherosclerotic plaque formation
Hawthorn OPCs scavenge all of these species in cell-free assays at concentrations achievable with oral dosing. The clinical translation has been studied most rigorously in:
- Animal models of ischemia/reperfusion injury (see next section)
- Markers of oxidative stress in heart failure patients (the HERB CHF trial, 450 mg twice daily for 6 months, found no difference from placebo)
- Markers of endothelial function (modestly improved flow-mediated dilation in some trials)
The size of the antioxidant effect in humans is modest compared to the in vitro potency, because of the substantial first-pass metabolism, bioavailability limitations, and competition from the body's endogenous antioxidant systems.
Ischemia/Reperfusion Injury — Animal Evidence
Ischemia/reperfusion (I/R) injury is the paradoxical cellular damage that occurs not during the ischemic interval itself but immediately upon restoration of blood flow. It is the mechanism that limits the clinical benefit of reperfusion after myocardial infarction (after percutaneous coronary intervention (PCI) or thrombolysis), liver transplantation, organ transplant generally, and stroke recanalization. The injury is driven by a burst of reactive oxygen species generation during the first minutes of reperfusion, when mitochondria suddenly resume electron transport in the presence of accumulated metabolic substrates and oxygen.
Hawthorn extract has been tested in multiple animal I/R models with consistently favorable results:
- Veveris et al. 2004 (rat model) — rats were given WS 1442 by mouth (10 or 100 mg/kg a day) for 7 days before a coronary artery was tied off for 240 minutes and then reopened for 15 minutes. At the higher dose, the dead (infarcted) part of the at-risk heart muscle was 42.8% versus 78.4% in untreated controls (64.3% at the lower dose); ventricular fibrillation fell from 67% to 27% and deaths from 47% to 9%, and heart pumping function (the pressure-rate product) fell less. In plain words: rats given the extract for a week before a blocked artery lost less heart muscle and died less often. The authors suggested that antioxidant effects, inhibition of the enzyme leukocyte elastase and increased endothelial nitric oxide production explain the effect.
- Al Makdessi et al. 1996 (isolated rat heart) — rats ate a diet containing 2% Crataegus oxyacantha powder for 3 months; their isolated (Langendorff-perfused) hearts then underwent 110 minutes of blockage of the left anterior descending coronary artery and 30 minutes of reperfusion. On reperfusion, release of lactate dehydrogenase, a marker of heart-muscle cell damage, was about half that of controls (1,777 vs 3,795 mU/min).
- Jayalakshmi and Devaraj 2004 (rat model of isoproterenol-induced myocardial infarction, MI) — Hawthorn pretreatment reduced both infarct size and markers of oxidative damage (lipid peroxidation, protein carbonylation) in cardiac tissue.
The animal evidence has not been directly translated to large human trials of Hawthorn for acute myocardial infarction or for cardioprotection during planned cardiac surgery, primarily because the regulatory and funding pathway for such trials of a non-patentable botanical is challenging. Practitioners cite this animal work as the rationale for long-term Hawthorn use as an add-on in people with established ischemic heart disease.
The Anti-Arrhythmic Mechanism
Hawthorn extracts prolong the cardiac effective refractory period (ERP) in isolated cardiac muscle preparations — an electrophysiologic effect that is broadly anti-arrhythmic for re-entrant arrhythmias such as paroxysmal supraventricular tachycardia, atrial flutter, and many cases of ventricular tachycardia. The mechanism appears to involve mild blockade of repolarizing potassium currents, similar in concept (though much weaker in magnitude) to the Class III antiarrhythmic drug amiodarone. In isolated guinea pig hearts, a hawthorn extract lengthened the effective refractory period by up to 10%, while epinephrine, digoxin, milrinone and amrinone shortened it (Joseph 1995). In anaesthetized rats with a blocked coronary artery, a hawthorn (Crataegus meyeri) flower extract cut ventricular ectopic beats from 1,494 to 634 and shortened the time spent in ventricular fibrillation (Garjani 2000).
The clinical correlate cited is a SPICE trial subgroup finding: in patients with left ventricular ejection fraction (LVEF) of 25–35%, WS 1442 reduced sudden cardiac death by 39.7% (hazard ratio 0.59; see the Heart Failure deep-dive). The trial's main outcome, time to the first cardiac event, did not differ from placebo (hazard ratio 0.95), and the trend toward fewer cardiac deaths was not statistically significant. Sudden cardiac death in heart failure patients is overwhelmingly due to ventricular arrhythmia, and the subgroup reduction is consistent with the anti-arrhythmic effect documented in isolated heart-muscle preparations.
Beyond the SPICE signal, smaller observational studies and case reports suggest reduced frequency of palpitations and benign ectopy in patients taking Hawthorn for general cardiovascular wellness. For atrial fibrillation specifically, see the next section.
An important contrast: while Hawthorn is broadly anti-arrhythmic and pro-arrhythmic effects are not seen in trials, it has not been tested as a replacement for established antiarrhythmic drugs in people with documented dangerous arrhythmias. Sustained ventricular tachycardia, cardiomyopathy severe enough for an automatic implantable cardioverter-defibrillator (AICD), and persistent atrial fibrillation are treated with established rate-control and rhythm-control strategies; where Hawthorn is used, it is used alongside them, not as primary therapy.
Stable Angina — Clinical Evidence
The European clinical literature on Hawthorn for stable angina is older and less rigorous than the heart failure data, because most modern trials have focused on the heart failure indication that received Commission E approval. However, multiple older European observational and uncontrolled studies, and the proposed mechanism (anti-arrhythmic + coronary vasodilator + antioxidant), are cited for adjunctive use:
- Hanak and Bruckel 1983 — an early German observational study of 60 patients with stable angina treated with Crataegus extract for 6 weeks reported reduction in anginal episode frequency and improved exercise tolerance on bicycle ergometry. The trial was open-label and uncontrolled.
- Iwamoto et al. 1981 (Japanese trial) — a multicenter double-blind study of a Crataegus extract in heart disease of ischemic or hypertensive origin, published in German in Planta Medica; reductions in angina frequency and nitroglycerin consumption versus placebo are reported from it, but no abstract is indexed in PubMed to confirm the details.
- Weng et al. 1984 (China) — a double-blind study of Chinese hawthorn (Crataegus pinnatifida) in 46 people with angina; only its title is indexed in PubMed, so its results cannot be checked there.
- Jalaly et al. 2015 (Iran) — 80 people aged 45–65 with stable angina were randomly assigned to a Crataegus oxyacantha extract, aerobic exercise, both, or neither for 12 weeks. Blood levels of two blood-vessel inflammation markers, intercellular adhesion molecule-1 (ICAM-1) and E-selectin, fell in the treated groups, and the extract-plus-exercise group had lower ICAM-1 than the extract-alone and untreated groups. The study measured these markers, not angina attacks.
- Animal coronary vasodilation studies — multiple studies in isolated coronary preparations demonstrate Hawthorn-induced vasodilation at concentrations achievable with oral dosing
Practitioners who use Hawthorn for stable angina describe it as:
- Adjunctive to established antianginal therapy (beta-blocker for first-line, nitrates for symptomatic episodes, sometimes calcium channel blocker)
- An addition for people who want a botanical, with the hope of slightly better exercise tolerance and fewer angina attacks
- Not a replacement for any established secondary-prevention therapy — aspirin, statin, angiotensin-converting enzyme inhibitor (ACE inhibitor) or angiotensin receptor blocker (ARB), beta-blocker as indicated
- Not a treatment for unstable angina, which hospitals treat as a medical emergency — see Chest Pain for red-flag features
Atrial Fibrillation Considerations
Atrial fibrillation is the most common sustained arrhythmia, affecting an estimated 6 million Americans, with prevalence climbing steeply with age. Modern management involves anticoagulation for stroke prevention (warfarin or a direct oral anticoagulant), rate control (typically a beta-blocker or calcium channel blocker), and selective rhythm control (cardioversion, antiarrhythmics, ablation) in symptomatic patients.
Hawthorn's role in atrial fibrillation has not been well studied in dedicated trials, but the mechanistic profile suggests several potential roles:
- Symptom palliation — the mild anti-arrhythmic and rate-modulating effects may reduce palpitations and the subjective sense of cardiac irregularity, particularly in paroxysmal atrial fibrillation (AF) where episodes are intermittent. This is most relevant for patients on rate-control therapy who continue to have symptom burden.
- Adjunct in the "anxious-with-palpitations" phenotype — patients whose atrial fibrillation episodes are particularly distressing due to associated anxiety may benefit from the combined cardiac and mild anxiolytic effects (see the Anxiety & Mood deep-dive)
- Long-term cardioprotection — the antioxidant and endothelial-supportive effects are theoretically beneficial in a population at elevated cardiovascular risk
Important cautions:
- Hawthorn does not replace anticoagulation for stroke prevention. For people with atrial fibrillation and an elevated CHA2DS2-VASc stroke-risk score, cardiology guidelines call for an anticoagulant such as warfarin, dabigatran, rivaroxaban, apixaban, or edoxaban.
- Hawthorn does not reliably restore sinus rhythm or bring heart rate to target — that is done with conventional rate-control or rhythm-control treatment
- The mild antiplatelet activity of Hawthorn flavonoids is theoretically additive with anticoagulants; the clinical size of this effect is thought to be small
Coronary Blood Flow Enhancement
One of the older traditional uses of Hawthorn was as a "coronary vasodilator" for patients with ischemic heart disease. Modern phytochemistry has confirmed this effect through the endothelial nitric oxide synthase pathway already described.
The clinical relevance:
- In healthy coronary arteries, increased coronary blood flow improves myocardial oxygen delivery
- In atherosclerotic coronary arteries with fixed obstructive lesions, the magnitude of vasodilation is limited by the rigid stenosed segment, but the upstream and downstream segments can still vasodilate
- In coronary microvascular dysfunction (a recognized cause of angina with non-obstructive coronaries, particularly in women), the endothelial nitric oxide pathway is specifically impaired, and Hawthorn's eNOS activation could theoretically restore some microvascular function
The relevance to specific clinical contexts:
- Patient with established coronary artery disease on optimal medical therapy with residual exercise-induced angina — Hawthorn has been proposed as an add-on for symptom relief
- Patient with ischemia with non-obstructive coronary arteries (INOCA), where conventional therapy options are limited — Hawthorn has been proposed because of the microvascular dysfunction mechanism
- Patient with vasospastic (Prinzmetal's) angina — calcium channel blockers and nitrates are the first-line treatments; an adjunctive role for Hawthorn has been suggested
Post-Myocardial-Infarction Recovery
Practitioners cite the animal I/R data as a basis for chronic Hawthorn use in people recovering from myocardial infarction or undergoing cardiac rehabilitation, as one element of a comprehensive cardioprotective strategy. The conventional foundation remains:
- Dual antiplatelet therapy (aspirin + P2Y12 inhibitor for typically 12 months post-stent)
- High-intensity statin
- Angiotensin-converting enzyme inhibitor or angiotensin receptor blocker (especially with reduced ejection fraction or anterior myocardial infarction)
- Beta-blocker (especially with reduced ejection fraction)
- Cardiac rehabilitation program (exercise, education, risk-factor modification)
- Smoking cessation, weight loss, blood pressure control
The theoretical benefits proposed for Hawthorn as an add-on to this regimen are antioxidant cardioprotection against ongoing oxidative stress, mild anti-arrhythmic effect reducing the small but real residual sudden cardiac death risk in post-MI patients with reduced ejection fraction, and mild improvement in exercise tolerance during the recovery and rehabilitation phase.
None of this is established by dedicated randomized trials in post-MI populations — the existing trial data is for chronic stable heart failure, not for post-MI cardioprotection — and the mechanistic rationale comes from animal studies. On safety, SPICE found adverse events comparable to placebo, while HERB CHF reported significantly more adverse events in the hawthorn group, most of them not heart-related. Hawthorn has not been tested as a replacement for any of the guideline-directed treatments listed above.
Where Hawthorn Has Been Proposed in Heart Care
Beyond the formally approved NYHA Class II heart failure indication and the blood pressure data, the add-on uses proposed for Hawthorn in heart care are:
- Stable angina — proposed as an adjunct to beta-blocker, statin, aspirin, for symptoms and exercise tolerance
- Atrial fibrillation — symptom palliation in rate-controlled patients with continued palpitations; not a replacement for anticoagulation or rate/rhythm control
- Post-MI recovery — adjunct to guideline-directed therapy; antioxidant and mild anti-arrhythmic effects theoretically beneficial
- Vasospastic / microvascular angina — eNOS activation pathway aligned with the underlying pathophysiology
- General cardiac wellness in elderly patients — the older European herbalist's "heart tonic" use for the patient over 70 with structural heart disease, mild symptoms, and a desire for a gentle long-term cardiotonic
Hawthorn has not been shown to work as:
- Replacement for any established secondary-prevention therapy after myocardial infarction
- Replacement for anticoagulation in atrial fibrillation
- Primary therapy for unstable angina, acute coronary syndrome, or sustained dangerous arrhythmia
- Treatment for severe valvular disease or advanced systolic dysfunction
A 2020 systematic review written for the Australian heart-failure guidelines placed hawthorn extract among the supplements whose studies "were too small or underpowered to properly appraise clinical outcomes"; of all the supplements reviewed, only omega-3 polyunsaturated fatty acids received a positive recommendation in those guidelines.
Key Research Papers
- Veveris M, Koch E, Chatterjee SS (2004). Crataegus special extract WS 1442 improves cardiac function and reduces infarct size in a rat model of prolonged coronary ischemia and reperfusion. Life Sci 74(15):1945-1955. — PubMed PMID: 14761675
- Al Makdessi S et al. (1996). Myocardial protection by pretreatment with Crataegus oxyacantha: an assessment by means of the release of lactate dehydrogenase by the ischemic and reperfused Langendorff heart. Arzneimittelforschung 46(1):25-27. — PubMed PMID: 8821513
- Jayalakshmi R, Devaraj SN (2004). Cardioprotective effect of tincture of Crataegus on isoproterenol-induced myocardial infarction in rats. J Pharm Pharmacol 56(7):921-926. — PubMed
- Wang J, Xiong X, Feng B (2013). Effect of crataegus usage in cardiovascular disease prevention: an evidence-based approach. Evid Based Complement Alternat Med. — PubMed
- Tassell MC et al. (2010). Hawthorn (Crataegus spp.) in the treatment of cardiovascular disease. Pharmacogn Rev 4(7):32-41. — PubMed PMID: 22228939
- Garjani A, Nazemiyeh H, Maleki N, Valizadeh H (2000). Effects of extracts from flowering tops of Crataegus meyeri A. Pojark. on ischaemic arrhythmias in anaesthetized rats. Phytother Res 14(6):428-431. — PubMed PMID: 10960896
- Schwinger RH et al. (2000). Crataegus special extract WS 1442 increases force of contraction in human myocardium cAMP-independently. J Cardiovasc Pharmacol 35(5):700-707. — PubMed PMID: 10813370
- Joseph G, Zhao Y, Klaus W (1995). [Pharmacologic action profile of crataegus extract in comparison to epinephrine, amirinone, milrinone and digoxin in the isolated perfused guinea pig heart] (in German). Arzneimittelforschung 45(12):1261-1265. — PubMed PMID: 8595081
- Holubarsch CJ, Colucci WS, Meinertz T, et al. (2008). The efficacy and safety of Crataegus extract WS 1442 in patients with heart failure: the SPICE trial. Eur J Heart Fail 10(12):1255-1263. — PubMed PMID: 19019730
- Zick SM, Vautaw BM, Gillespie B, Aaronson KD (2009). Hawthorn Extract Randomized Blinded Chronic Heart Failure (HERB CHF) trial. Eur J Heart Fail 11(10):990-999. — PubMed PMID: 19789403
- Iwamoto M, Sato T, Ishizaki T (1981). [The clinical effect of Crataegutt in heart disease of ischemic or hypertensive origin. A multicenter double-blind study] (in German). Planta Med 42(1):1-16. — PubMed PMID: 7019949
- Weng WL, Zhang WQ, Liu FZ, et al. (1984). Therapeutic effect of Crataegus pinnatifida on 46 cases of angina pectoris — a double blind study. J Tradit Chin Med 4(4):293-294. — PubMed PMID: 6397664
- Jalaly L, Sharifi G, Faramarzi M, et al. (2015). Comparison of the effects of Crataegus oxyacantha extract, aerobic exercise and their combination on the serum levels of ICAM-1 and E-Selectin in patients with stable angina pectoris. Daru 23:54. — PubMed PMID: 26687477
- Hopper I, Connell C, Briffa T, et al. (2020). Nutraceuticals in patients with heart failure: a systematic review. J Card Fail 26(2):166-179. — PubMed PMID: 31704198