Hawthorn for Blood Pressure
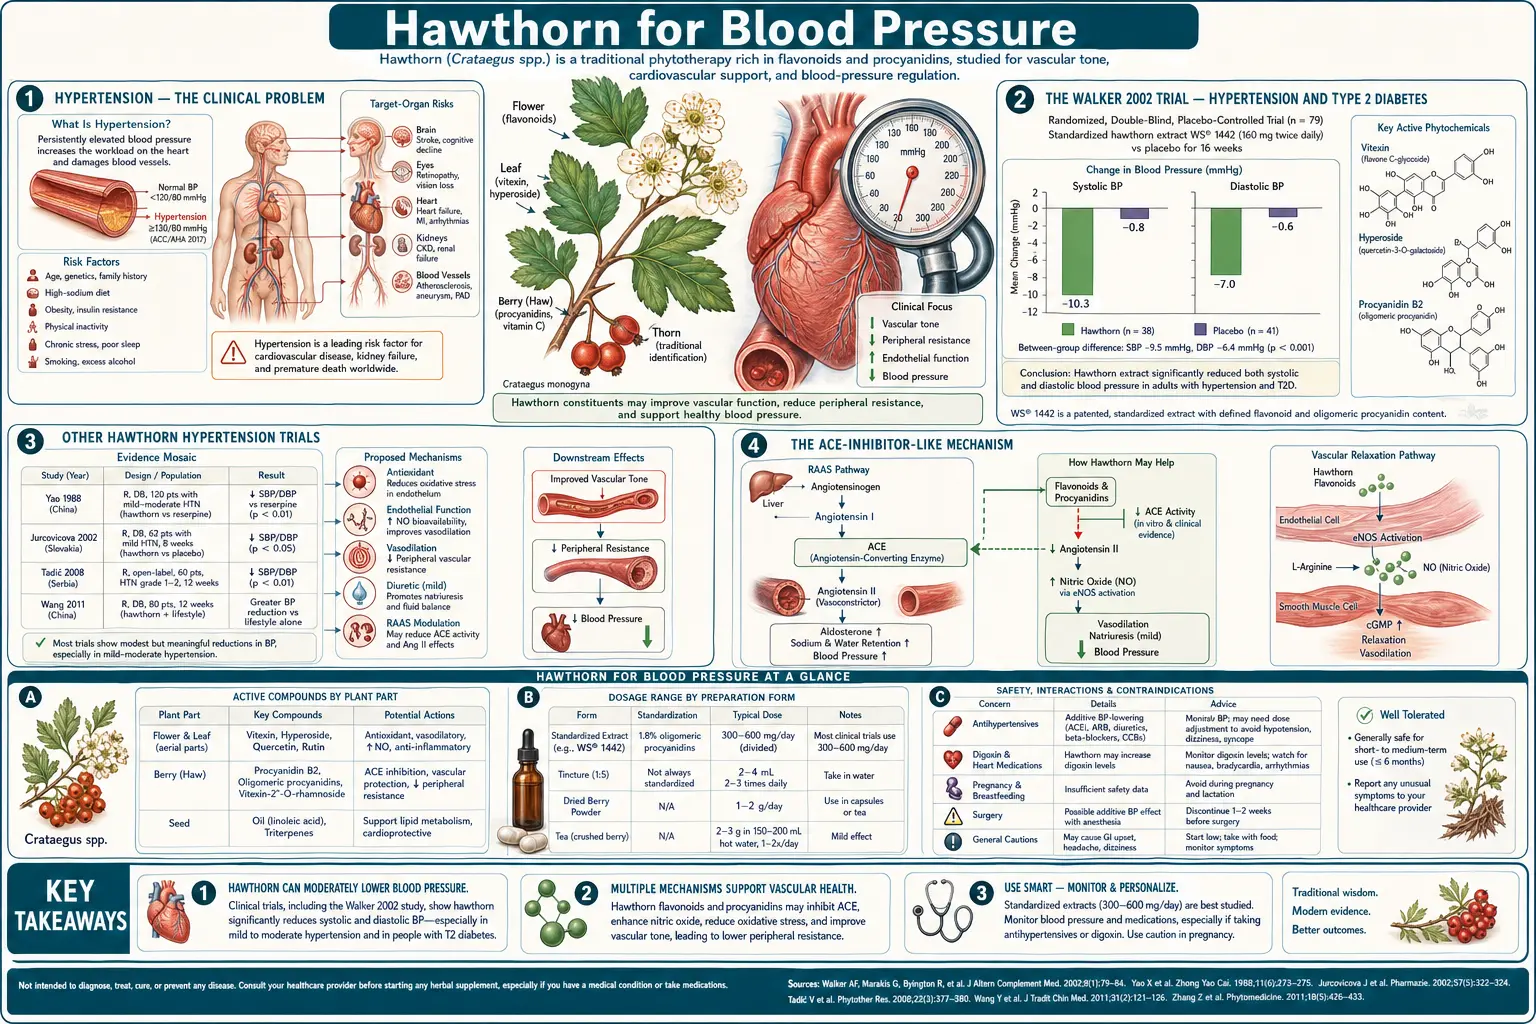
Hawthorn is one of a small number of herbal preparations with credible clinical-trial evidence for a mild blood-pressure-lowering effect. In Walker et al.'s 2006 randomized controlled trial in 79 people with type 2 diabetes, most of them already taking blood-pressure drugs, diastolic pressure fell from 85.6 to 83.0 mmHg over 16 weeks on 1,200 mg/day hawthorn extract, while on placebo it went from 84.5 to 85.0 mmHg (a significant group difference); systolic pressure did not differ between the groups. A 2025 meta-analysis of six placebo-controlled trials found an average 6.65 mmHg fall in systolic pressure. The mechanism is dual: oligomeric proanthocyanidins (OPCs) and several flavonoids weakly inhibit angiotensin-converting enzyme (the same enzyme blocked by lisinopril), while vitexin and hyperoside trigger endothelial nitric oxide release that produces vasodilation. The research covers mild hypertension (stage 1: systolic 130-139 or diastolic 80-89 mmHg); it does not cover hawthorn as a replacement for conventional therapy in moderate-to-severe hypertension, where mortality-benefit data exist for drug treatment.
Table of Contents
- Hypertension — The Clinical Problem
- The Walker Trials (2002 and 2006) — Mild Hypertension and Type 2 Diabetes
- Other Hawthorn Hypertension Trials
- The ACE-Inhibitor-Like Mechanism
- The Vasodilator Mechanism (Nitric Oxide)
- Clinical Positioning — Stage 1 Hypertension
- Stacking with Conventional Antihypertensives
- Dosing and Standardized Products
- Monitoring, Cautions, and Drug Interactions
- The Lifestyle Context (DASH, Sodium, Exercise)
- Key Research Papers
- Connections
- Featured Videos
Hypertension — The Clinical Problem
Hypertension affects approximately 47% of American adults under the 130/80 mmHg threshold set by the 2017 American College of Cardiology/American Heart Association (ACC/AHA) guideline. It is the single most powerful modifiable risk factor for stroke, the largest contributor to ischemic heart disease, and a major driver of heart failure and chronic kidney disease. Despite the availability of multiple effective drug classes (angiotensin-converting enzyme inhibitors (ACE inhibitors), angiotensin receptor blockers (ARBs), calcium channel blockers, thiazide diuretics, mineralocorticoid receptor antagonists), only about 24% of hypertensive adults have their blood pressure controlled to target.
The reasons for poor control are multiple: medication side effects (cough with angiotensin-converting enzyme inhibitors, edema with calcium channel blockers, electrolyte disturbance with diuretics), polypharmacy reluctance, inertia of intensification, and a substantial cohort of patients who decline pharmacologic management in favor of lifestyle or complementary approaches. Hawthorn is one of several food-based interventions (along with hibiscus tea, beetroot, garlic, and magnesium) with reasonable evidence in this niche.
The 2017 ACC/AHA stratification is:
- Normal blood pressure: less than 120/80
- Elevated blood pressure: 120-129 systolic, less than 80 diastolic. Lifestyle intervention only.
- Stage 1 hypertension: 130-139 systolic OR 80-89 diastolic. Lifestyle intervention; pharmacotherapy if 10-year atherosclerotic cardiovascular disease (ASCVD) risk is greater than 10%. Most hawthorn blood-pressure trials enrolled people with mild hypertension in or near this range.
- Stage 2 hypertension: greater than or equal to 140 systolic OR 90 diastolic. Lifestyle plus pharmacotherapy.
- Hypertensive crisis: greater than 180/120. Treated by hospitals as urgent.
In 2025 the American Heart Association, the American College of Cardiology and partner societies published a new high blood pressure guideline that “retires and replaces” the 2017 one. As summarised in a 2026 commentary from European Renal Best Practice, it still defines hypertension as systolic pressure of 130 mmHg or more or diastolic pressure of 80 mmHg or more. It recommends starting drug treatment for people at high cardiovascular-disease risk and finds it reasonable for people at lower risk when lifestyle change does not correct their blood pressure. The target is below 130/80 mmHg, with encouragement to reach a systolic pressure below 120 mmHg. The European guidelines (2024 European Society of Cardiology, 2023 European Society of Hypertension) instead call 130-139/80-89 mmHg “high normal” or “elevated” blood pressure and treat it with drugs only in high-risk groups.
The Walker Trials (2002 and 2006) — Mild Hypertension and Type 2 Diabetes
The most-cited Hawthorn hypertension trials come from Ann Walker and colleagues at the University of Reading. The first, a 2002 pilot study published in Phytotherapy Research, randomized 36 people with mild hypertension to one of four daily supplements for 10 weeks: 600 mg magnesium, 500 mg hawthorn extract, both together, or placebo. Blood pressure fell in every group, including placebo, and the main analysis found no difference between treatments. Taken together, the 19 people assigned to hawthorn showed a reduction in resting diastolic pressure at week 10 compared with the other groups that did not reach statistical significance (p = 0.081), and a trend toward less anxiety (p = 0.094). The authors called the result promising, “particularly in view of the low dose of hawthorn extract used”.
The second, a 2006 randomized controlled trial published in the British Journal of General Practice, ran in general practices in Reading. It enrolled 79 people with type 2 diabetes and randomized them to 1,200 mg/day hawthorn extract (39 people) or placebo (40 people) for 16 weeks. Most were already medicated: 71% took blood-pressure drugs, and participants took an average of 4.4 diabetes and/or blood-pressure drugs each.
Headline results of the 2006 trial:
- Diastolic blood pressure fell in the Hawthorn group from 85.6 to 83.0 mmHg, while in the placebo group it went from 84.5 to 85.0 mmHg. The difference between the groups was statistically significant (P = 0.035).
- Systolic blood pressure fell 3.6 mmHg in the Hawthorn group and 0.8 mmHg in the placebo group; the difference between the groups was not statistically significant (P = 0.329).
- No herb-drug interaction was found, even though most participants were taking several prescription drugs for diabetes and blood pressure.
- Minor health complaints fell from baseline in both groups.
For context, the seminal HOPE-3 trial of low-dose candesartan-plus-hydrochlorothiazide produced approximately 6/3 mmHg systolic/diastolic reduction in mid-range hypertensive patients. A 5-6 mmHg reduction in diastolic blood pressure is associated, in epidemiologic data, with roughly a 20-25% reduction in stroke risk over the long term.
Both Walker trials have important limitations: they were small (36 and 79 people), neither was powered for hard cardiovascular endpoints such as strokes or heart attacks, the 2006 population was specifically people with type 2 diabetes taking many medicines, and neither found a significant systolic effect.
Other Hawthorn Hypertension Trials
The supporting evidence base beyond the Walker trials includes:
- Asgary et al. 2004 — an Iranian randomized double-blind trial of a leaf-and-flower extract of Crataegus curvisepala, taken three times daily for more than 4 months by 92 men and women aged 40-60 with mild hypertension, found a significant decrease in both systolic and diastolic blood pressure after 3 months in this placebo-controlled trial.
- Schröder et al. 2003 — an observational (non-randomized) study of people aged 50-75 with mild heart failure (New York Heart Association class II) compared a homeopathic hawthorn preparation (110 people) with ACE-inhibitor/diuretic treatment (102 people) for 8 weeks. The hawthorn preparation was non-inferior on most of 15 measures, but not on blood-pressure reduction (systolic pressure during exercise and diastolic pressure at rest), although the differences between treatments on those two were not statistically significant.
- Szikora et al. 2025 meta-analysis — pooled six randomized placebo-controlled trials (428 participants, treatment for 10 weeks to 6 months, 250-1,200 mg/day). Hawthorn lowered systolic pressure by an average 6.65 mmHg, which was statistically significant; the average 7.19 mmHg fall in diastolic pressure was not statistically significant. The authors call the effect clinically significant and say larger, well-designed trials are still needed to establish dosing, duration and efficacy.
The aggregate picture is of a mild blood-pressure-lowering effect, with the trials differing on which number moved — diastolic pressure in the 2006 Walker trial, systolic pressure in the 2025 pooled analysis. The evidence base is small and has not tested Hawthorn as a primary therapy for moderate or severe hypertension.
The ACE-Inhibitor-Like Mechanism
Angiotensin-converting enzyme (ACE) is the enzyme that converts the inactive decapeptide angiotensin I to the potent vasoconstrictor and aldosterone-releasing octapeptide angiotensin II. It is the principal pharmacologic target of the angiotensin-converting enzyme inhibitor (ACE inhibitor) drug class (lisinopril, enalapril, ramipril, etc.), one of the most successful drug classes in modern cardiology with multiple positive mortality trials in hypertension, heart failure, and post-myocardial-infarction left ventricular dysfunction.
In cell-free ACE inhibition assays and in animal models, multiple Hawthorn constituents demonstrate ACE inhibitory activity:
- Oligomeric proanthocyanidins (OPCs) — the dimeric procyanidin B-2 and pentameric proanthocyanidins inhibit ACE with IC50 values in the low micromolar range. The mechanism appears to be a non-covalent interaction with the active-site zinc atom of ACE.
- Hyperoside (a flavonol glycoside) — inhibits ACE in vitro at concentrations achievable with oral Hawthorn dosing
- Vitexin and its derivatives — weak but documented ACE inhibitory activity
The combined effect produces a mild ACE-inhibitor-like reduction in angiotensin II, leading to mild vasodilation, reduced aldosterone secretion, and reduced sodium and water retention. The magnitude of effect is substantially smaller than that of synthetic angiotensin-converting enzyme inhibitors (which produce nearly complete enzyme inhibition at therapeutic doses), but the mechanism is qualitatively the same.
An important practical implication: because the ACE-inhibitor-like effect is the dominant mechanism, Hawthorn is theoretically additive with synthetic angiotensin-converting enzyme inhibitors (lisinopril, enalapril) and angiotensin receptor blockers (losartan, valsartan). The clinical magnitude of this additive effect appears to be small: in the 2006 Walker trial, where 71% of participants took blood-pressure drugs, no herb-drug interaction was found.
Hawthorn does not, importantly, produce the dry cough side effect that limits angiotensin-converting enzyme inhibitor tolerability in approximately 10-15% of patients (the cough is mediated by bradykinin accumulation, not by ACE inhibition per se, and Hawthorn's effect on bradykinin metabolism is minimal). This is one reason Hawthorn is sometimes proposed as an option for the patient who needs ACE-inhibitor-like effects but cannot tolerate a synthetic angiotensin-converting enzyme inhibitor for cough.
The Vasodilator Mechanism (Nitric Oxide)
Independent of the ACE-inhibitor-like effect, Hawthorn flavonoids also produce direct vasodilation through endothelial nitric oxide release. This mechanism has been characterized in isolated rat aortic ring preparations and in human coronary artery samples:
- A standardized hawthorn leaf-and-flower extract triggers calcium-dependent activation of endothelial nitric oxide synthase (eNOS) in endothelial cells
- The released NO diffuses to the underlying vascular smooth muscle and activates guanylate cyclase, raising cyclic GMP
- Elevated cGMP triggers smooth muscle relaxation through reduced calcium sensitivity and reduced intracellular calcium concentration
- The net effect is vasodilation, reduced peripheral vascular resistance, and reduced blood pressure
This is the same nitric oxide pathway exploited by nitroglycerin (in angina) and sildenafil (in erectile dysfunction), though Hawthorn's effect is much milder. The vasodilator mechanism is also responsible for Hawthorn's coronary vasodilatory effect, which is relevant to its anti-anginal use.
The dual ACE-inhibitor-like plus vasodilator mechanism means a single botanical acts on several complementary pathways at once. The combined action has been offered as the reason some trials see a clearer effect on diastolic pressure (which is more directly governed by peripheral vascular resistance) than on systolic pressure (which is more strongly influenced by stroke volume and large-artery compliance), although the 2025 pooled analysis found the clearer effect on systolic pressure.
Clinical Positioning — Stage 1 Hypertension
The people the hawthorn blood-pressure research most closely matches have:
- Stage 1 hypertension (130-139 systolic OR 80-89 diastolic)
- Low 10-year atherosclerotic cardiovascular disease (ASCVD) risk (under 10%) — under the 2017 guideline, lifestyle modification alone, with pharmacotherapy reserved for higher-risk patients; the 2025 guideline finds drug treatment reasonable at lower risk when lifestyle change does not correct blood pressure
- An interest in a food-based / botanical approach alongside lifestyle modification (DASH diet, sodium restriction, exercise, weight loss)
- No condition in which a further fall in blood pressure is a hazard, such as orthostatic hypotension or severe aortic stenosis
- Time for the effect to show: the trials ran 10 weeks to 6 months before measuring it
For stage 2 hypertension (greater than or equal to 140 systolic OR 90 diastolic), the blood pressure reduction needed exceeds what the hawthorn trials have shown, and guidelines pair lifestyle change with conventional drugs that have mortality-trial evidence (angiotensin-converting enzyme inhibitors, angiotensin receptor blockers, thiazides, calcium channel blockers (CCBs)). Hawthorn has been studied alongside such drugs: in the 2006 Walker trial, 71% of participants took blood-pressure drugs.
For patients with concurrent heart failure who also have hypertension, Hawthorn has been studied for both conditions — one of the few herbal preparations with research in both.
Stacking with Conventional Antihypertensives
When Hawthorn is added to an existing conventional antihypertensive regimen, the practical considerations differ by drug class:
- Angiotensin-converting enzyme inhibitors and angiotensin receptor blockers — additive effect on the renin-angiotensin axis; the concern is a larger-than-intended fall in blood pressure. In the 2006 Walker trial no herb-drug interaction was found.
- Thiazide diuretics — minimal interaction at the mechanism level (thiazides act on the renal distal convoluted tubule, not the renin-angiotensin axis or vascular tone). Mild additive blood-pressure effect possible.
- Calcium channel blockers (amlodipine, nifedipine) — mild additive effect via different vasodilation pathways. Generally well tolerated in combination.
- Beta-blockers — minimal interaction; the beta-blocker negative inotropic and chronotropic effects are independent of the renin-angiotensin and nitric oxide pathways Hawthorn acts on.
- Mineralocorticoid receptor antagonists (spironolactone) — additive antihypertensive effect; this drug class can raise blood potassium.
- Direct renin inhibitors (aliskiren) — theoretical additive effect on the renin-angiotensin axis.
The general principle is that Hawthorn's mild antihypertensive effect adds to (but does not synergize with or dramatically amplify) conventional drug effects. Most patients tolerate the addition without dose adjustment of conventional drugs; in some, blood pressure falls further than intended and a lower conventional dose follows. Home blood pressure readings show whether that is happening.
Dosing and Standardized Products
For blood pressure specifically, the Walker trials used 500 mg/day of hawthorn extract (2002) and 1,200 mg/day (2006), and the trials pooled in the 2025 meta-analysis used 250-1,200 mg/day. Heart failure trials have used around 900 mg/day. The dose-response curve for blood pressure has not been well characterized.
Doses and forms described in practice:
- 600-900 mg/day standardized leaf-and-flower extract, divided in two or three doses
- Duration: the trials measured the effect after 10 weeks to 6 months; long-term continuous use is the typical pattern
- Timing: taking it with meals is described as reducing the rare gastrointestinal (GI) upset
- Form: tinctures and crude herb capsules are less reliable for reproducing trial doses than standardized dry extract tablets or capsules
Home blood pressure readings are the way to confirm a response objectively rather than relying on subjective wellness reports, and to detect over-correction if Hawthorn is added to an existing antihypertensive regimen. A validated upper-arm cuff used in the morning before medications and the evening before dinner, with the results logged over 2-4 weeks, provides much better data than occasional office measurements.
Monitoring, Cautions, and Drug Interactions
- Orthostatic hypotension — rarely, the additive antihypertensive effect can produce postural lightheadedness, particularly in elderly patients or those on multiple antihypertensives. Getting up slowly from sitting or lying reduces this lightheadedness.
- Angiotensin-converting enzyme inhibitors and angiotensin receptor blockers — additive antihypertensive effect; in the 2006 Walker trial, where 71% of participants took blood-pressure drugs, no herb-drug interaction was found.
- Other antihypertensives — see the section above for class-by-class considerations.
- Digoxin — see the Heart Failure deep-dive for the additive inotropic theoretical interaction.
- Anticoagulants and antiplatelets — mild antiplatelet activity from Hawthorn flavonoids; clinical magnitude is small but theoretically additive.
- Sildenafil and other PDE5 inhibitors — theoretical additive vasodilation; clinical experience suggests this is not problematic; the concern is a larger fall in blood pressure.
- Pregnancy — there is no good safety data on hawthorn in pregnancy.
- Hypotension at baseline — in people whose blood pressure is already low (systolic less than 100), a further fall can cause dizziness and fainting.
The Lifestyle Context (DASH, Sodium, Exercise)
Hawthorn is best understood as one element in a broader blood-pressure-management strategy, not as a standalone solution. The interventions with the largest established blood-pressure reduction are:
- Sodium restriction to under 1,500 mg/day — can produce 4-8 mmHg systolic reduction in salt-sensitive individuals
- DASH dietary pattern (Dietary Approaches to Stop Hypertension — emphasizes fruits, vegetables, whole grains, fish, poultry; limits red meat, sugar, sodium) — can produce 8-14 mmHg systolic reduction
- Regular aerobic exercise (150 minutes/week moderate intensity) — 4-9 mmHg systolic reduction
- Weight loss (5-10% of body weight in overweight or obese patients) — 5-20 mmHg systolic reduction
- Alcohol limitation (no more than 2 drinks/day for men, 1 for women) — 2-4 mmHg systolic reduction
- Stress reduction practices — modest but real, particularly for patients with high baseline sympathetic tone
Hawthorn's effect in trials — a significant diastolic difference in the 2006 Walker trial and an average 6.65 mmHg systolic fall in the 2025 pooled analysis — fits into this list as an addition but not the largest contributor. For the patient committed to the full lifestyle package, Hawthorn provides incremental benefit on top of the foundational interventions. For the patient who will not change diet, exercise, or weight, Hawthorn alone is unlikely to produce dramatic blood pressure improvement.
Key Research Papers
- Walker AF et al. (2002). Promising hypotensive effect of hawthorn extract: a randomized double-blind pilot study of mild, essential hypertension. Phytotherapy Research 16(1):48-54. — PubMed PMID: 11807965
- Walker AF et al. (2006). Hypotensive effects of hawthorn for patients with diabetes taking prescription drugs: a randomised controlled trial. Br J Gen Pract 56(527):437-443. — PubMed PMID: 16762125
- Asgary S, Naderi GH, Sadeghi M, Kelishadi R, Amiri M (2004). Antihypertensive effect of Iranian Crataegus curvisepala Lind.: a randomized, double-blind study. Drugs Exp Clin Res 30(5-6):221-225. — PubMed PMID: 15700749
- Pittler MH et al. (2003). Hawthorn extract for treating chronic heart failure: meta-analysis of randomized trials. Am J Med 114(8):665-674. A heart failure meta-analysis, not a blood-pressure one. — PubMed PMID: 12798455
- Brixius K et al. (2006). Crataegus special extract WS 1442 induces an endothelium-dependent, NO-mediated vasorelaxation. Cardiovasc Drugs Ther 20(3):177-184. — PubMed PMID: 16779533
- Tassell MC et al. (2010). Hawthorn (Crataegus spp.) in the treatment of cardiovascular disease. Pharmacogn Rev 4(7):32-41. — PubMed PMID: 22228939
- Wang J, Xiong X, Feng B (2013). Effect of crataegus usage in cardiovascular disease prevention: an evidence-based approach. Evid Based Complement Alternat Med 2013:149363. — PubMed PMID: 24459528
- Bahorun T, Gressier B, Trotin F, Brunet C, Dine T, Luyckx M, Vasseur J, Cazin M, Cazin JC, Pinkas M (1996). Oxygen species scavenging activity of phenolic extracts from hawthorn fresh plant organs and pharmaceutical preparations. Arzneimittelforschung 46(11):1086-1089. — PubMed PMID: 8955870
- Schröder D, Weiser M, Klein P (2003). Efficacy of a homeopathic Crataegus preparation compared with usual therapy for mild (NYHA II) cardiac insufficiency: results of an observational cohort study. Eur J Heart Fail 5(3):319-326. — PubMed PMID: 12798830
- Szikora Z, Mátyus RO, Szabó BV, Csupor D, Tóth B (2025). Hawthorn (Crataegus spp.) Clinically Significantly Reduces Blood Pressure in Hypertension: A Meta-Analysis of Randomized Placebo-Controlled Clinical Trials. Pharmaceuticals (Basel) 18(7):1027. — PubMed PMID: 40732315
- Writing Committee Members, Jones DW, Ferdinand KC, Taler SJ, et al. (2025). 2025 AHA/ACC/AANP/AAPA/ABC/ACCP/ACPM/AGS/AMA/ASPC/NMA/PCNA/SGIM Guideline for the Prevention, Detection, Evaluation and Management of High Blood Pressure in Adults. Hypertension 82(10):e212-e316. — PubMed PMID: 40811516
- Kanbay M, Copur S, Sarafidis P, Ferro CJ, Ortiz A (2026). 2025 AHA/ACC/AANP/AAPA/ABC/ACCP/ACPM/AGS/AMA/ASPC/NMA/PCNA/SGIM guideline for the prevention, detection, evaluation and management of high blood pressure in adults: a commentary from the European Renal Best Practice (ERBP). Nephrol Dial Transplant 41(10):1909-1918. — PubMed PMID: 41805831