⚠ Evidence warning: Clinical trials or other evidence do not support the claim that valerian relaxes muscles and helps restless legs, fibromyalgia, tension-type headache, temporomandibular joint (TMJ) problems and irritable bowel syndrome cramping. This page keeps it as a report of what people, websites or other media say.
Valerian for Muscle Relaxation
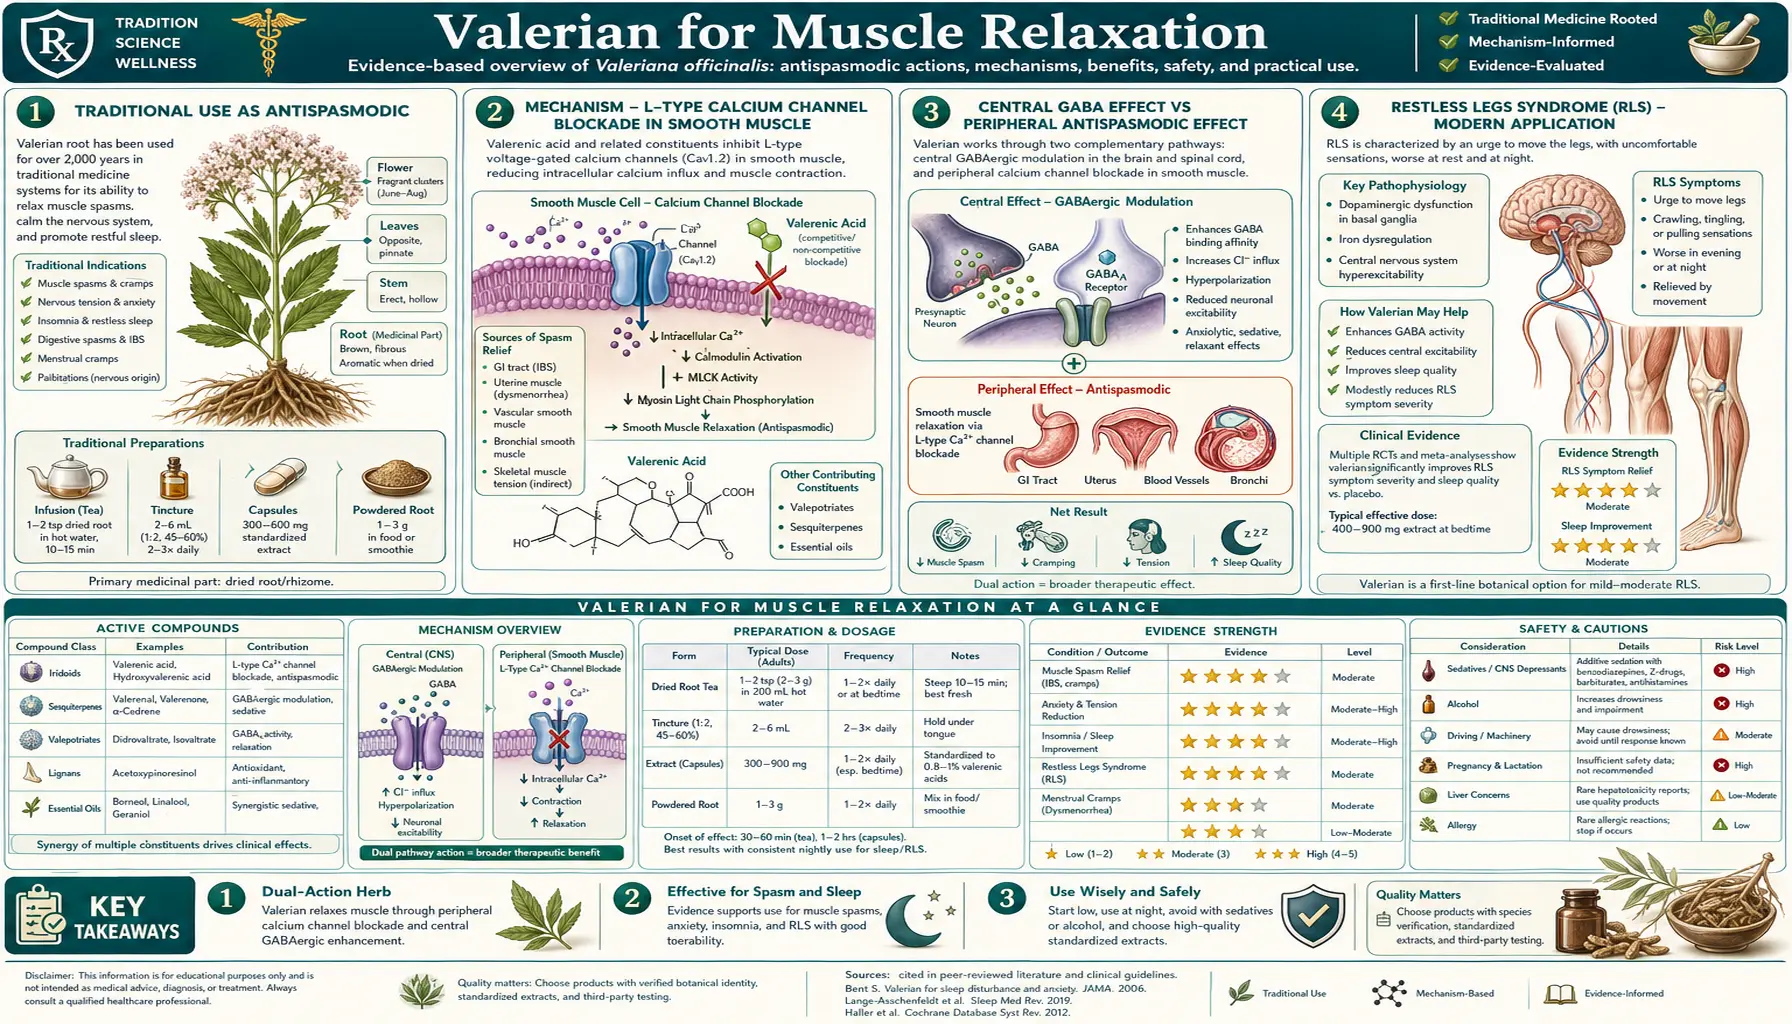
Valerian has been used as a smooth-muscle relaxant in European herbal medicine since classical antiquity, with documented use for what would now be called intestinal cramping, biliary colic, dysmenorrhea, and bronchospasm. The modern mechanistic picture is uncertain: laboratory studies on isolated animal gut tissue show valerian compounds relaxing smooth muscle directly, a weak blockade of L-type voltage-gated calcium channels (the target of nifedipine and verapamil) has been proposed and was reported for a related Asian valerian species, and a gamma-aminobutyric acid-mediated reduction of central sympathetic outflow is proposed to lower smooth-muscle tone indirectly. The traditional application that has generated the most modern clinical research is restless legs syndrome (RLS), where valerian has been tested in two small randomized trials, one against placebo and one against the drug gabapentin. Beyond the gut, uterus, and restless-legs indications, valerian's mild skeletal-muscle relaxation has positioned it as an adjunctive option in fibromyalgia, tension-type headache, and chronic temporomandibular joint dysfunction, where it complements pharmacologic muscle relaxants like cyclobenzaprine and methocarbamol with a markedly better tolerability profile.
Table of Contents
- Traditional Use as Antispasmodic
- Mechanism — Smooth-Muscle Relaxation and the Calcium-Channel Question
- Central Gamma-Aminobutyric Acid Effect vs Peripheral Antispasmodic Effect
- Restless Legs Syndrome (RLS) — Modern Application
- Compared to Prescription Muscle Relaxants
- Fibromyalgia — Adjunctive Role
- Tension-Type Headache and Temporomandibular Joint (TMJ) Problems
- Gastrointestinal Smooth-Muscle Spasm (Irritable Bowel Syndrome, Biliary Colic)
- Historical Bronchospasm Application
- Dose, Form, and Timing for Muscle-Relaxant Indications
- Combination Protocols (Valerian + Magnesium, Valerian + Skullcap)
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Traditional Use as Antispasmodic
The earliest European medical references to valerian as an antispasmodic appear in Dioscorides's De Materia Medica (first century CE) and Galen's writings (second century CE), where it is described as a treatment for "cramps," "uterine pain," and "convulsions" (a category that would have included epilepsy, dystonia, and other diverse hyperkinetic disorders not well distinguished at the time). Medieval herbals from Hildegard of Bingen onward describe valerian for "shaking palsy" (likely some combination of tremor, dystonia, and restless movements) and "wandering pains" (a description that maps reasonably well onto fibromyalgia, RLS, or restless extremity sensations of unclear etiology).
The 19th-century United States Pharmacopeia, which listed valerian from 1820 to 1942, recognized two distinct clinical indications: a sedative-hypnotic indication for "nervous restlessness and insomnia" and an antispasmodic indication for "intestinal cramps, painful menstruation, and muscle spasm." Both indications were carried over from the European traditional materia medica. The antispasmodic indication was largely displaced from clinical practice by atropine derivatives (hyoscine, scopolamine, dicyclomine) for gastrointestinal (GI) smooth-muscle indications and by aspirin and acetaminophen for analgesic indications, but persisted in folk practice and in the herbal medicine tradition.
Modern interest in valerian as a smooth-muscle relaxant has been driven by two converging trends: increasing patient resistance to prescription muscle relaxants (which all have meaningful side-effect profiles), and accumulating mechanistic evidence for valerian's calcium-channel and gamma-aminobutyric acid-mediated effects on smooth muscle. The clinical research base is still modest compared with the sleep-and-anxiety literature, but the mechanistic plausibility and the traditional-use history support the use of valerian as an adjunctive smooth-muscle relaxant in appropriate clinical contexts.
Mechanism — Smooth-Muscle Relaxation and the Calcium-Channel Question
Smooth muscle contraction is initiated by an increase in cytosolic calcium concentration, which can come either from extracellular calcium entering through voltage-gated calcium channels (primarily L-type in vascular, gastrointestinal, uterine, and airway smooth muscle) or from intracellular calcium released from the sarcoplasmic reticulum. The calcium activates calmodulin, which activates myosin light chain kinase, which phosphorylates myosin, which then cross-links with actin to produce contraction.
Pharmacologic interruption of this cascade can occur at multiple points:
- Block calcium entry through L-type channels (nifedipine, verapamil, diltiazem)
- Prevent calcium release from sarcoplasmic reticulum
- Inhibit myosin light chain kinase
- Activate parallel relaxant pathways (nitric oxide, prostacyclin, beta-adrenergic agonists)
Laboratory studies on isolated animal tissue show that valerian compounds can relax smooth muscle, but they point to more than one mechanism. In guinea-pig gut (ileum), Hazelhoff and colleagues (1982) found that the active compounds were the valepotriates (isovaltrate, valtrate, didrovaltrate) and valeranone from the essential oil; they relaxed stimulated muscle directly, acting as “musculotropic agents” rather than through nerve receptors, and valeranone and didrovaltrate were about as strong as the drug papaverine. In rabbit gut (jejunum) and rabbit aorta, an extract of the related species Valeriana wallichii relaxed muscle mainly by opening potassium channels (KATP channels) and had only a weak effect on contractions caused by high potassium (Gilani and colleagues, 2005). A calcium-channel-blocking effect similar to verapamil was reported for another species, Valeriana hardwickii, in rabbit jejunum (Bashir and colleagues, 2011). Whether the common valerian (Valeriana officinalis) blocks calcium channels in human smooth muscle is not known.
The clinical implications of a weak, uncertain effect are important: valerian is not a substitute for a calcium channel blocker in conditions where strong calcium-channel blockade is needed (hypertension, severe angina, severe Raynaud's syndrome). But the modest potency is potentially advantageous in indications where strong calcium-channel blockade would cause unacceptable adverse effects (hypotension, headache, ankle edema, constipation), making valerian a useful gentle option in conditions like primary dysmenorrhea, irritable bowel syndrome-spasm, or RLS where the smooth-muscle relaxation need is modest.
Central Gamma-Aminobutyric Acid Effect vs Peripheral Antispasmodic Effect
The smooth-muscle relaxation produced by valerian almost certainly reflects a combination of central and peripheral mechanisms operating simultaneously:
Central mechanism (the larger contributor for most indications). Gamma-aminobutyric acid-mediated reduction of central sympathetic outflow lowers smooth-muscle tone throughout the body indirectly. Sympathetic tone, transmitted via norepinephrine release at alpha-1 receptors on vascular smooth muscle, beta-2 receptors on bronchial smooth muscle, and via cholinergic outflow to gastrointestinal smooth muscle, is the dominant determinant of resting smooth-muscle tone in most tissues. Reducing central sympathetic outflow (the same mechanism by which a benzodiazepine produces some smooth-muscle relaxation) is probably the dominant peripheral consequence of valerian's reported central effects on gamma-aminobutyric acid type A receptors and on gamma-aminobutyric acid transaminase, the enzyme that breaks gamma-aminobutyric acid down.
Peripheral mechanism (the smaller contributor, but mechanistically more interesting). Direct relaxation of smooth muscle, as discussed above (the exact channels involved are uncertain). The peripheral effect is detectable in isolated tissue preparations (where the central sympathetic input is absent) but is modest in absolute potency.
The proportions of central and peripheral contribution probably vary by tissue and by clinical context. In dysmenorrhea, where the uterine spasm is largely driven by local prostaglandins and is not heavily sympathetically driven, the peripheral smooth-muscle mechanism may be relatively more important. In RLS and anxiety-related muscle tension, where central activation drives the peripheral symptoms, the central gamma-aminobutyric acid (GABA) mechanism is probably the larger contributor.
The clinical implication: valerian's muscle-relaxant effect is generally maximal in conditions where both the central and peripheral mechanisms can contribute. Patients with combined anxiety-driven muscle tension and primary smooth-muscle spasm tend to respond better than patients with pure peripheral spasm without central activation.
What is not known. In mice and rats, Hattesohl and colleagues (2008) gave valerian extracts by mouth at doses up to 500 or 1000 mg per kg of body weight. Several extracts reduced anxiety-like behaviour at 100-500 mg/kg, but none had a sedative effect, and no muscle-relaxing effect was seen on the horizontal-wire test at doses up to 1000 mg/kg. The central and peripheral contributions described above therefore remain proposals rather than measured effects.
Restless Legs Syndrome (RLS) — Modern Application
Restless legs syndrome (RLS, also known as Willis-Ekbom disease) is a neurological disorder characterized by an unpleasant urge to move the legs, typically at rest in the evening or at night, partially relieved by movement. Prevalence in adults is approximately 5-10%, with a meaningful subset (1-2% of the general population) experiencing symptoms severe enough to require treatment. The 2025 American Academy of Sleep Medicine (AASM) guideline gives strong recommendations for gabapentin enacarbil, gabapentin, pregabalin and intravenous ferric carboxymaltose, and suggests against the standard use of the dopamine agonists pramipexole, ropinirole and the rotigotine patch because of long-term worsening (augmentation). For iron, the guideline lists oral or intravenous iron for adults whose ferritin is 75 ng/mL or lower or whose transferrin saturation is below 20%, and intravenous iron only when ferritin is between 75 and 100 ng/mL. The same guideline suggests against the use of valerian for restless legs (a conditional recommendation based on very low certainty evidence).
Many RLS patients seek alternatives to dopamine agonists for one of several reasons:
- Augmentation — the well-documented worsening of RLS symptoms with chronic dopamine agonist use (earlier onset of symptoms, spread to upper extremities, increased intensity). Augmentation affects approximately 30% of patients on chronic dopamine agonists after 5-10 years of use.
- Impulse control disorders — pathological gambling, hypersexuality, compulsive shopping, and binge eating are well-documented complications of dopamine agonist therapy in the RLS population.
- Daytime sleepiness and "sleep attacks" — some patients experience profound sleepiness on dopamine agonists, occasionally including unanticipated sleep onset while driving.
The Cuellar and Ratcliffe 2009 trial (published in Alternative Therapies in Health and Medicine) was a triple-blinded, randomized, placebo-controlled trial: 37 people aged 36 to 65 with RLS took valerian 800 mg or a placebo for 8 weeks. Both groups reported improvement in RLS symptom severity (International RLS Symptom Severity Scale) and in sleep, so valerian did not stand out from placebo overall. In a smaller analysis of the 17 people who took valerian, those who were sleepy in the daytime at the start (Epworth Sleepiness Scale score of 10 or more) showed significant before-and-after improvements in sleepiness (P = .01) and RLS symptoms (P = .02), and the authors concluded valerian may be an alternative for symptom management in that group.
A second trial, by Hajizadeh and colleagues (2023), enrolled 40 people on hemodialysis with restless legs in a crossover design: one group took valerian and the other gabapentin one hour before bedtime for one month, then the treatments were swapped, with a one-month wash-out. After the first month, restless-legs scores were lower in the gabapentin group, while sleep-quality scores did not differ between the two. The authors concluded that gabapentin is more effective than valerian for restless legs, and that both improve sleep quality equally.
The mechanistic plausibility for valerian in RLS rests on the combined central gamma-aminobutyric acid effect (reducing the central component of restless sensations) and the peripheral muscle relaxation (reducing the somatic component). The regimen practitioners describe for RLS is 600-900 mg of standardized extract one hour before bed, combined with iron when ferritin is low, evening leg stretching, and cutting out evening alcohol and tobacco (both known to worsen RLS). Practitioners report symptomatic benefit in roughly half of people using valerian alone for mild-to-moderate RLS.
Compared to Prescription Muscle Relaxants
The clinical positioning of valerian against prescription muscle relaxants depends on the specific drug and the specific indication.
Cyclobenzaprine. Cyclobenzaprine is the most commonly prescribed muscle relaxant for acute musculoskeletal pain. It is a tricyclic-related compound with significant anticholinergic effects (dry mouth, urinary retention, constipation, orthostatic hypotension) and substantial sedation. It is on the American Geriatrics Society (AGS) Beers Criteria for avoidance in older adults due to anticholinergic burden and fall risk. Valerian is meaningfully gentler on all of these dimensions but is also less potent. For acute musculoskeletal injury the prescription drug is the more potent of the two; for long-term use in older adults, practitioners favour valerian because it lacks the anticholinergic burden behind cyclobenzaprine's Beers listing.
Methocarbamol. Methocarbamol has less anticholinergic burden than cyclobenzaprine but produces more sedation. It is generally considered to have a modest evidence base for skeletal muscle relaxation, with much of its clinical effect probably being sedative rather than direct muscle-relaxant. Valerian is comparable in tolerability with similar gentle effect.
Carisoprodol. Carisoprodol metabolizes to meprobamate, a Schedule IV controlled substance with abuse potential. It is generally not recommended for chronic use. Practitioners favour valerian over it for chronic muscle-tension complaints.
Tizanidine. Tizanidine is an alpha-2 agonist with documented efficacy in spasticity (multiple sclerosis, spinal cord injury, stroke) and chronic tension headache. It produces significant sedation, dry mouth, and occasional hepatotoxicity. For specific spasticity indications, tizanidine is more effective than valerian. For non-spastic muscle tension, valerian is more tolerable.
Baclofen. Baclofen is a gamma-aminobutyric acid-B receptor agonist used primarily for spasticity. It has a more rigorous mechanism than valerian and is more effective for true spasticity. It also has significant withdrawal complications including seizures with abrupt discontinuation. Valerian and baclofen target related but distinct mechanisms (gamma-aminobutyric acid-A for valerian, gamma-aminobutyric acid-B for baclofen) and are not direct substitutes.
Benzodiazepines (diazepam, clonazepam). Benzodiazepines have meaningful muscle-relaxant effect at higher doses, mediated by the same gamma-aminobutyric acid-A receptor that valerenic acid weakly modulates. Diazepam is occasionally used for acute muscle spasm. The dependence and tolerance issues that limit chronic benzodiazepine use are not problems with valerian.
The clinical positioning of valerian for muscle-relaxant indications is as a gentle option for chronic mild-to-moderate tension, an alternative to anticholinergic-burdened muscle relaxants in older patients, and an adjunct to non-pharmacologic interventions (physical therapy, stretching, heat, massage). It is not a substitute for properly indicated stronger pharmacology in specific spasticity or severe acute spasm settings.
Fibromyalgia — Adjunctive Role
Fibromyalgia is a chronic pain disorder characterized by widespread musculoskeletal pain, fatigue, sleep disturbance, and cognitive symptoms ("fibro fog"). The pathophysiology is now understood to involve central sensitization (amplified pain processing in the central nervous system), with hyperactive descending pain facilitation and impaired descending pain inhibition. Sleep architecture is consistently disrupted, with reduced slow-wave sleep, frequent micro-arousals, and non-restorative quality.
The U.S. Food and Drug Administration-approved pharmacologic treatments are duloxetine, milnacipran, and pregabalin. Many patients tolerate these poorly or have partial response. Adjunctive interventions that address sleep and muscle tension specifically can produce meaningful symptomatic improvement.
The role of valerian in fibromyalgia is primarily as a sleep adjunct, addressing the well-documented sleep architecture disturbance that drives much of the daytime symptom burden. Improved slow-wave sleep on chronic valerian (per the polysomnographic data discussed on the Sleep Quality page) is particularly relevant for fibromyalgia, where slow-wave sleep is preferentially disrupted. The muscle-tension-reducing effect provides a secondary benefit for the chronic muscle tightness and trigger points that characterize the disorder.
Integrative practitioners use valerian as a low-risk adjunct for people with fibromyalgia who continue to have sleep and muscle-tension symptoms despite first-line therapy, and report improvement in sleep quality and morning stiffness. No clinical trial of valerian in fibromyalgia was found in PubMed.
The combined regimen for fibromyalgia commonly used by integrative practitioners: valerian 600-900 mg one hour before bed for sleep and muscle tension; magnesium glycinate 200-400 mg twice daily for muscle tension and headache prevention; D-ribose 5 g three times daily for fatigue; consistent moderate aerobic exercise; cognitive behavioral therapy (CBT) for chronic pain. The component contributions are individually modest but cumulatively meaningful for many patients.
Tension-Type Headache and Temporomandibular Joint (TMJ) Problems
Tension-type headache (TTH) is the most common headache disorder, affecting up to 80% of adults at some point and 1-3% chronically. It is characterized by bilateral pressing or tightening pain (the classic "band around the head"), mild-to-moderate intensity, and not aggravated by routine physical activity. The pathophysiology involves a combination of pericranial muscle tension (trapezius, splenius capitis, temporalis, masseter) and central pain sensitization.
The first-line pharmacologic treatment for episodic TTH is over-the-counter analgesics (acetaminophen, ibuprofen, naproxen). For chronic TTH (more than 15 headache days per month), the first-line preventive is amitriptyline 10-50 mg at bedtime, with mirtazapine and venlafaxine as alternatives.
Valerian's role in TTH is as an adjunct to address two contributing factors: the muscle tension that perpetuates the headache pattern, and the sleep disturbance that frequently accompanies chronic TTH. The regimen practitioners describe is 600 mg of standardized valerian extract at bedtime, combined with magnesium glycinate and consistent sleep hygiene. For patients with prominent TMJ involvement (jaw clenching, morning soreness, audible joint sounds), the combination addresses both the headache and the jaw component.
Temporomandibular joint dysfunction (TMD) is a clinical syndrome involving the jaw joint and the muscles of mastication. Bruxism (tooth grinding, particularly nocturnal) is a major driver. The first-line treatments are dental night guards, jaw exercises, and stress management. Pharmacologic adjuncts include low-dose tricyclic antidepressants and muscle relaxants. Valerian can serve as a gentle muscle relaxant for TMD with concurrent benefit on sleep quality and reduced nocturnal bruxism in some patients. See the broader Migraine page for related discussions of headache management.
Gastrointestinal Smooth-Muscle Spasm (Irritable Bowel Syndrome, Biliary Colic)
The traditional indication for valerian as a "nervous indigestion" remedy maps onto the modern concept of stress-related visceral hypersensitivity, the dominant pathophysiology of irritable bowel syndrome (IBS). Both gut motility (smooth-muscle contraction patterns) and visceral nociception (gut-derived pain signaling) are dysregulated in irritable bowel syndrome, with substantial bidirectional communication with the central nervous system through the gut-brain axis.
Herbal practitioners use valerian-containing combinations for irritable bowel syndrome cramping and stool-pattern complaints. No clinical trial of valerian in irritable bowel syndrome was found in PubMed (the records found are rat studies of a related species, Valeriana jatamansi), and in multi-herb combinations the specific valerian contribution cannot be separated from the other herbs.
The first-line evidence-based interventions for irritable bowel syndrome are dietary (low-FODMAP diet for irritable bowel syndrome-mixed and irritable bowel syndrome-diarrhea, soluble fiber for irritable bowel syndrome-constipation), pharmacologic (loperamide and rifaximin for diarrhea-predominant irritable bowel syndrome (IBS-D), linaclotide and plecanatide for constipation-predominant irritable bowel syndrome (IBS-C), low-dose tricyclic antidepressants for visceral pain), and behavioral (cognitive behavioral therapy for irritable bowel syndrome, gut-directed hypnotherapy). Peppermint oil (enteric-coated) has the strongest herbal evidence base for irritable bowel syndrome, with positive randomized controlled trial (RCT) data and a documented mechanism (calcium-channel blockade in intestinal smooth muscle, the same mechanism postulated for valerian but with higher potency).
Valerian's role in irritable bowel syndrome is primarily as an adjunct for the anxiety-and-stress component that drives irritable bowel syndrome flares in many patients, with secondary benefit on the smooth-muscle component. Practitioners combine it with peppermint oil for irritable bowel syndrome-spasm and with chamomile for the broader gut-brain-axis modulation. See our Irritable Bowel Syndrome page for the broader irritable bowel syndrome management framework.
Biliary colic (the cramping pain from gallbladder contraction against a stone or sludge) is a separate indication where valerian's modest smooth-muscle effect is unlikely to be clinically useful at standard doses. Biliary colic typically requires acute pain management with nonsteroidal anti-inflammatory drugs (NSAIDs) or opioids and definitive treatment with cholecystectomy. Valerian is not a substitute for either.
Historical Bronchospasm Application
The early-20th-century use of valerian for "spasmodic cough" and "nervous asthma" reflected the pre-bronchodilator era when antispasmodic herbs were among the few options for managing bronchospastic conditions. With the development of beta-2-agonists (albuterol), inhaled corticosteroids, and leukotriene modifiers, valerian has no meaningful current role in asthma or chronic obstructive pulmonary disease (COPD) management. The peripheral smooth-muscle relaxation potency is far too low to produce clinically meaningful bronchodilation. Active bronchospasm is treated with rescue bronchodilators and controller anti-inflammatory therapy; herbal antispasmodics have no part in that treatment.
The historical use is mentioned here only to round out the traditional materia medica picture, not as a current clinical recommendation. For people with asthma who use valerian for sleep or anxiety, valerian does not replace inhaled controller or rescue medications.
Dose, Form, and Timing for Muscle-Relaxant Indications
The standard dose range for valerian as a muscle relaxant is the same as for its sedative-hypnotic and anxiolytic indications: 600-900 mg of standardized 0.8% valerenic acid extract. The timing varies by indication:
- For RLS — one hour before bed, given that symptoms are most prominent at rest in the evening
- For fibromyalgia sleep and morning stiffness — one hour before bed
- For tension-type headache prevention — one hour before bed
- For daytime tension headache or TMJ — a smaller daytime dose (300-400 mg) can be considered, with attention to sedation; this is more often prescribed as the lemon-balm or magnesium combinations to limit daytime sedation
- For irritable bowel syndrome adjunct — can be split between morning and evening doses, or concentrated at bedtime if anxiety-driven sleep disturbance is part of the picture
Practitioners describe a 1-2 week trial before judging effect. Like all valerian indications, the muscle-relaxant effect develops over days to weeks rather than appearing on the first dose.
Combination Protocols (Valerian + Magnesium, Valerian + Skullcap)
Valerian + magnesium glycinate. The combination practitioners use most for muscle tension. Magnesium acts at the N-methyl-D-aspartate (NMDA) receptor and as a calcium-channel modulator at the neuromuscular junction; valerian acts on the gamma-aminobutyric acid system. The combined effect on muscle tension, sleep, and (in fibromyalgia) pain is greater than either alone. The regimen practitioners describe: valerian 600 mg one hour before bed plus magnesium glycinate 200 mg twice daily. See our Magnesium Glycinate page.
Valerian + skullcap (Scutellaria lateriflora). Skullcap is a traditional American herb with documented gamma-aminobutyric acid-A modulating activity from its scutellarin and baicalin flavonoids. The combination is widely used in herbal sleep formulas for the patient with prominent muscle tension and sleep disturbance.
Valerian + cramp bark (Viburnum opulus). Cramp bark has historical use as a uterine antispasmodic with documented effects on smooth muscle. The combination is occasionally used for severe dysmenorrhea (see also the Menstrual Cramps page).
Valerian + passionflower. Passionflower provides additional gamma-aminobutyric acid-A modulation through different flavonoids. Combined sedative effect is greater than either alone. See our Passionflower page.
Valerian + chamomile (Matricaria recutita). Chamomile has its own modest anxiolytic and antispasmodic activity through apigenin's gamma-aminobutyric acid-A modulation. The combination is particularly used for "nervous indigestion" with combined gastrointestinal cramping and anxiety. See our Chamomile page.
Cautions and Drug Interactions
- Central nervous system (CNS) depressant interactions. Additive sedative effect with alcohol, benzodiazepines, opioids, prescription muscle relaxants. Taken together, the sedative effects add up.
- Spasticity is not a valerian indication. True spasticity (multiple sclerosis, spinal cord injury, stroke) is treated with antispastic drugs (baclofen, tizanidine); valerian has no established role in it.
- Acute back spasm or severe acute injury. Valerian's slow onset and modest potency make it a poor match for acute severe spasm, where prescription muscle relaxants are the standard treatment.
- RLS with significant iron deficiency. The 2025 AASM guideline asks clinicians to test iron (ferritin and transferrin saturation) in everyone with clinically significant RLS, and lists oral or intravenous iron for adults with ferritin of 75 ng/mL or lower or transferrin saturation below 20%. Iron repletion may resolve RLS entirely in iron-deficient people; valerian does not correct iron deficiency.
- Driving and operating machinery. Sedation in the first few days of a new valerian regimen can affect driving and machinery use, particularly with daytime dosing.
- Pregnancy and lactation. There is no good safety data on valerian in pregnancy or breastfeeding, and World Health Organization (WHO) and European Medicines Agency (EMA) guidance does not support its use then. Uterine smooth-muscle effects, while desirable for dysmenorrhea (in the non-pregnant patient), are theoretically concerning in pregnancy.
- Calcium channel blocker interaction. For people on prescription calcium channel blockers (nifedipine, amlodipine, verapamil, diltiazem), the concern is a possible added drop in blood pressure, based on the laboratory smooth-muscle data described above.
- Anesthesia. Common herbal-safety guidance lists stopping valerian at least 1 week before elective surgery.
- Failure to improve at 2 weeks. If a proper 2-week trial of valerian for muscle tension or RLS produces no perceptible benefit, additional duration is unlikely to help, and the lack of benefit can mean the underlying diagnosis needs another look.
Key Research Papers
- Cuellar NG, Ratcliffe SJ (2009). Does valerian improve sleepiness and symptom severity in people with restless legs syndrome? Alternative Therapies in Health and Medicine. — PubMed PMID: 19284179
- Hattesohl M, Feistel B, Sievers H, Lehnfeld R, Hegger M, Winterhoff H (2008). Extracts of Valeriana officinalis L. s.l. show anxiolytic and antidepressant effects but neither sedative nor myorelaxant properties. Phytomedicine. — PubMed PMID: 18160026
- Hazelhoff B, Malingre TM, Meijer DK (1982). Antispasmodic effects of valeriana compounds: an in-vivo and in-vitro study on the guinea-pig ileum. Archives Internationales de Pharmacodynamie et de Thérapie. — PubMed PMID: 7114974
- Sichardt K, Vissiennon Z, Koetter U, Brattström A, Nieber K (2007). Modulation of postsynaptic potentials in rat cortical neurons by valerian extracts macerated with different alcohols: involvement of adenosine A(1)- and GABA(A)-receptors. Phytotherapy Research. — PubMed PMID: 17582590
- Wasowski C, Marder M (2012). Flavonoids as GABAA receptor ligands: the whole story? Journal of Experimental Pharmacology. — PubMed PMID: 27186113
- Mineo L, Concerto C, Patel D, et al. (2017). Valeriana officinalis root extract modulates cortical excitatory circuits in humans. Neuropsychobiology. — PubMed PMID: 29035887
- Bourin M, Bougerol T, Guitton B, Broutin E (1997). A combination of plant extracts in the treatment of outpatients with adjustment disorder with anxious mood: controlled study versus placebo. Fundamental and Clinical Pharmacology. — PubMed PMID: 9107558
- Plushner SL (2000). Valerian: Valeriana officinalis. American Journal of Health-System Pharmacy. — PubMed PMID: 10714969
- Houghton PJ (1999). The scientific basis for the reputed activity of valerian. Journal of Pharmacy and Pharmacology. — PubMed PMID: 10411208
- Bos R, Woerdenbag HJ, Hendriks H, et al. (1996). Analytical aspects of phytotherapeutic valerian preparations. Phytochemical Analysis. — doi:10.1002/(SICI)1099-1565(199605)7:3<143::AID-PCA284>3.0.CO;2-1
- Marder M, Viola H, Wasowski C, et al. (2003). 6-methylapigenin and hesperidin: new valeriana flavonoids with activity on the CNS. Pharmacology, Biochemistry, and Behavior. — PubMed PMID: 12895671
- Gilani AH, Khan AU, Jabeen Q, Subhan F, Ghafar R (2005). Antispasmodic and blood pressure lowering effects of Valeriana wallichii are mediated through K+ channel activation. Journal of Ethnopharmacology, 100(3), 347-352. — PubMed PMID: 16002246
- Bashir S, Memon R, Gilani AH (2011). Antispasmodic and antidiarrheal activities of Valeriana hardwickii Wall. rhizome are putatively mediated through calcium channel blockade. Evidence-Based Complementary and Alternative Medicine, 2011, 304960. — PubMed PMID: 21423691
- Hajizadeh I, Jamshidi M, Kazemi M, Kargar H, Sadeghi T (2023). Comparison the effect of valerian and gabapentin on RLS and sleep quality in hemodialysis patients: a randomized clinical trial. Therapeutic Apheresis and Dialysis, 27(4), 621-628. — PubMed PMID: 37039703
- Winkelman JW, Berkowski JA, DelRosso LM, et al. (2025). Treatment of restless legs syndrome and periodic limb movement disorder: an American Academy of Sleep Medicine clinical practice guideline. Journal of Clinical Sleep Medicine, 21(1), 137-152. — PubMed PMID: 39324694
PubMed Topic Searches
Connections
- All Herbs
- Valerian Overview
- Valerian Benefits Hub
- Valerian for Sleep
- Valerian for Anxiety
- Valerian for Menstrual Cramps
- Passionflower
- Lemon Balm
- Chamomile
- Lavender
- Magnesium
- Magnesium Glycinate
- Migraine and Tension Headache
- Heart Palpitations
- Insomnia
- Anxiety
- Cramp Prevention
- Sleep Hygiene
- Stress Management
- Natural Anxiety Relief
- Calcium — the ion entering through L-type channels to trigger the smooth-muscle contraction valerian weakly blunts.
- History