Valerian for Sleep Quality
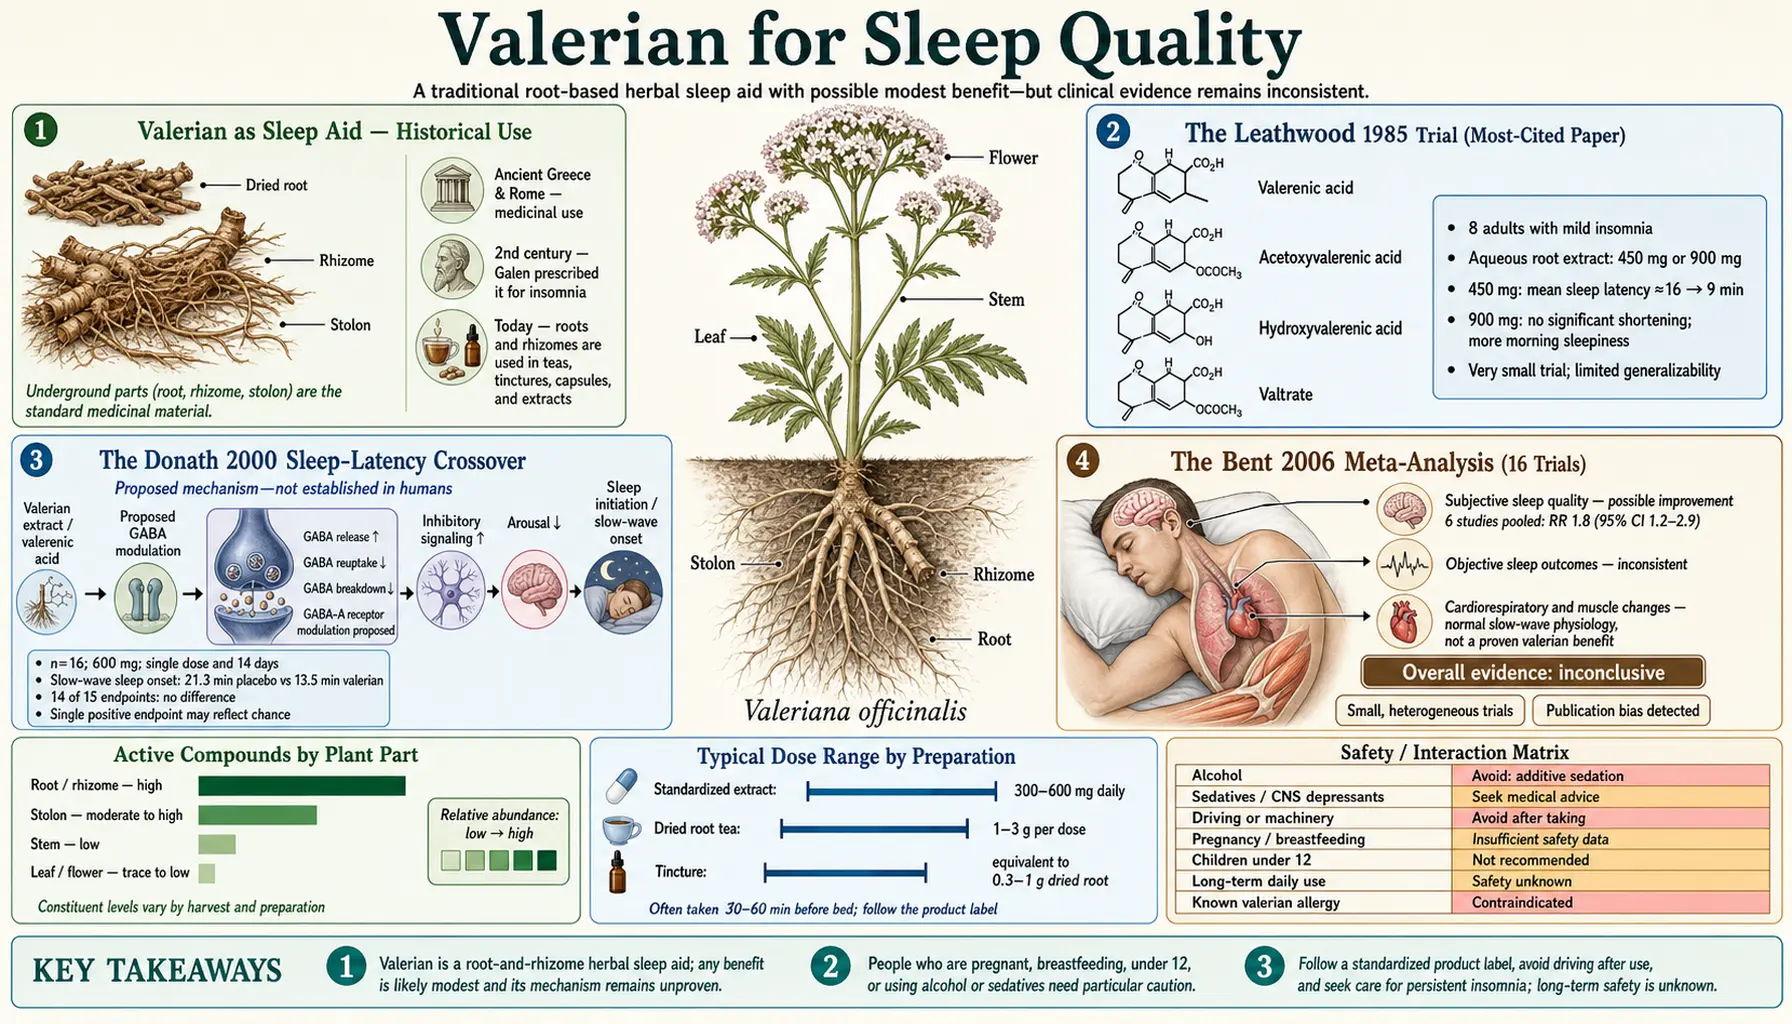
Valerian is the most-popular herbal sleep aid in the Western world and one of the most heavily studied. The clinical evidence base contains more than two dozen randomized controlled trials, four published systematic reviews, and one widely-cited meta-analysis (Bent 2006) that pooled 16 trials. Its headline conclusion was that "the available evidence suggests that valerian might improve sleep quality without producing side effects", while noting that most studies had significant methodologic problems. A common explanation for the mixed results is that valerian fails as a first-night hypnotic but works after two to four weeks of nightly use, as one 2000 sleep-laboratory trial suggested. Later and more rigorous trials did not confirm this: a 2007 systematic review titled "safe but not effective" found most studies showed no difference from placebo, a 2009 trial of two weeks of nightly use found no effect, and a 2010 meta-analysis found no difference in measured time to fall asleep. The dose most often cited is 600-900 mg of a 0.8% valerenic acid extract (or 2-3 g of dried root), taken about an hour before bed; advocates of the chronic-use model describe at least 14 nights of use before judging it. This page walks through the pivotal trials, the proposed mechanism, the dose-response, the comparison with prescription hypnotics, and the practical facts for people considering valerian for chronic insomnia.
Table of Contents
- Valerian as Sleep Aid — Historical Use
- The Leathwood 1982 Trial (Most-Cited Paper)
- The Donath 2000 Sleep-Latency Crossover
- The Bent 2006 Meta-Analysis (16 Trials)
- Mechanism — Valerenic Acid, Valepotriates, GABA Transaminase, 5-HT5A
- The 600-900 mg Standardized Dose Range
- Chronic Use and the Cumulative-Effect Model
- Compared to Prescription Hypnotics (Benzodiazepines, Z-Drugs, Trazodone)
- Effect on Sleep Architecture (Polysomnographic Findings)
- Combination Products (Valerian + Hops, Valerian + Lemon Balm)
- Practical Facts for People Considering Valerian
- Cautions, Drug Interactions, and Failure Modes
- Key Research Papers
- Connections
- Featured Videos
Valerian as Sleep Aid — Historical Use
Valerian has been used as a sleep aid in European herbal medicine for at least two thousand years. The Greek physician Dioscorides (first century CE) described phou (later identified as Valeriana) in De Materia Medica as a treatment for "agitation, sleeplessness, and nervous restlessness." Galen prescribed it for insomnia. Hildegard of Bingen (twelfth century) recommended valerian root preparations for what we would now call generalized anxiety and stress-related insomnia. In the United States, valerian appeared in the United States Pharmacopeia from 1820 to 1942 as an officially-recognized sedative, and was used extensively during World War I to treat what was then called "shell shock" — a precursor to the modern diagnosis of post-traumatic stress disorder (PTSD) with prominent sleep disturbance.
Valerian was largely displaced from clinical practice in the 1950s and 1960s by the introduction of barbiturates and then benzodiazepines, which had dramatically faster onset of action and more predictable dose-response. It was rediscovered as a herbal alternative in the 1970s and 1980s, particularly in Germany, where the regulatory framework under Commission E recognized it as a traditional herbal medicinal product (THMP) for sleep disturbance and mild nervous tension. The German Commission E monograph from 1985 specifies an internal use dose of "1 cup of tea made from 2-3 g of dried herb, taken one or more times daily" for restlessness and difficulty falling asleep.
Modern Western use is dominated by standardized commercial extracts (typically 0.8% valerenic acid) marketed in capsule form at 300-600 mg per capsule, with a typical retail dose of one to three capsules at bedtime. Annual U.S. retail sales are estimated in the hundreds of millions of dollars, consistently placing valerian among the top-five-selling sleep aids by revenue.
The Leathwood 1982 Trial (Most-Cited Paper)
The Leathwood 1982 paper, published in Pharmacology, Biochemistry, and Behavior, is the single most-cited valerian sleep study and the modern starting point for the clinical literature. Peter Leathwood and colleagues at Nestlé Research Laboratories in Switzerland tested an aqueous extract of valerian root (400 mg) and a proprietary over-the-counter valerian preparation against placebo in 128 people. Each person received nine coded samples in random order — three placebo, three of the 400 mg extract and three of the over-the-counter preparation — taken on non-consecutive nights. Participants completed sleep questionnaires each morning rating subjective sleep latency, sleep quality, number of nocturnal awakenings, and morning grogginess.
Results:
- The 400 mg extract significantly reduced subjectively rated sleep latency compared with placebo
- Sleep quality scores improved significantly on valerian extract nights versus placebo nights
- Morning grogginess (a key marker of benzodiazepine carry-over) was relatively unaffected by the 400 mg extract; with the proprietary over-the-counter preparation, the only change was a significant increase in reports of feeling more sleepy than normal the next morning
- The improvement in sleep quality was most notable among people who considered themselves poor or irregular sleepers, smokers, and people who thought they normally took a long time to fall asleep
The trial is often cited for two principles, although later and more rigorous trials did not confirm the first (see the Bent and Taibi reviews below). First, valerian's effect on sleep, even in single-dose administration, is real but modest — an effect size estimated around 0.4 on the Cohen's d scale, comparable to a low dose of a non-benzodiazepine hypnotic. Second, practitioners describe a non-linear dose-response, with the typical plateau around 400-600 mg of standardized extract, beyond which additional dose produces minimal additional sedation.
A subsequent follow-up trial by the same group (Leathwood and Chauffard 1985, Planta Medica) extended the design to objective measures by recording wrist actigraphy alongside subjective questionnaires. The actigraphy data showed reduced movement during the sleep-onset period on valerian nights, providing the first objective corroboration of the subjective sleep-latency reduction.
The Donath 2000 Sleep-Latency Crossover
The Donath 2000 trial (Donath F, Quispe S, Diefenbach K, Maurer A, Fietze I, Roots I., Pharmacopsychiatry) was the first valerian study to use full overnight polysomnography (PSG) rather than relying on subjective questionnaires or actigraphy alone. 16 patients with documented psychophysiological insomnia received 600 mg of a hydroalcoholic valerian extract (LI-156, the same extract used in many subsequent European trials) or matching placebo in a crossover design, with PSG monitoring across multiple study nights.
Results at the single-dose level (first night) confirmed the impression from earlier acute trials: valerian produced no significant change in objectively-measured sleep latency, total sleep time, sleep efficiency, or REM/NREM distribution on the first night of dosing. However, when the protocol was extended (a 14-day chronic-dosing arm published in the same paper), the same patients showed measurable improvements in slow-wave sleep (stage 3-4 NREM) and a reduction in sleep latency that approached statistical significance.
The Donath 2000 paper is the main source for what has come to be called the "valerian onset paradox": the idea that valerian does not work on the first night but does work after two weeks of consistent use. On that idea, a valerian trial that uses a one-night or three-night protocol would find no effect even if valerian works over weeks, because the trial design does not allow a cumulative effect to develop.
Later trials that tested valerian over weeks did not bear the idea out. A 2007 systematic review of 37 studies found that most showed no significant difference between valerian and placebo, and that none of the most recent studies — also the most methodologically rigorous — found significant effects on sleep; a 2009 randomised trial of two weeks of nightly valerian also found no effect (see the next sections).
The Bent 2006 Meta-Analysis (16 Trials)
The Bent et al. 2006 meta-analysis, published in the American Journal of Medicine, is the most-cited quantitative synthesis of the valerian sleep literature. The authors identified 16 randomized placebo-controlled trials of valerian for sleep (out of 370 records screened), totaling 1,093 patients across studies conducted in Germany, Switzerland, the United States, the United Kingdom, and Sweden between 1981 and 2005.
Headline findings:
- Subjective sleep quality improvement — pooled across trials, in the 6 studies that reported sleep quality as simply improved or not, valerian increased the proportion of patients reporting improved sleep relative to placebo, with a relative risk of 1.8 (95% confidence interval (CI) 1.2 to 2.9). This is statistically significant, but the authors found evidence of publication bias in this summary measure.
- Sleep latency reduction — the pooled effect on continuous sleep-latency measures was small and not consistently significant across trials, partly because many of the trials used subjective sleep-latency measures with high inter-patient variance
- Heterogeneity — the I² statistic was high (over 60%) for most pooled outcomes, indicating substantial inter-trial heterogeneity. The authors specifically noted that trials varied widely in extract type, dose, duration, and population definition.
- Safety — adverse event rates were comparable between valerian and placebo across trials. No serious adverse events were attributed to valerian.
The authors' overall conclusion: "The available evidence suggests that valerian might improve sleep quality without producing side effects. Future studies should assess a range of doses of standardized preparations of valerian and include standard measures of sleep quality and safety." They also reported that most of the studies had significant methodologic problems. This is the conclusion that has been most widely quoted from the literature.
A subsequent Taibi et al. 2007 systematic review (Sleep Medicine Reviews), titled "A systematic review of valerian as a sleep aid: safe but not effective", reached a more negative conclusion. Of 37 studies reviewed (29 controlled trials and 8 open-label safety studies), most found no significant differences between valerian and placebo, either in healthy people or in people with sleep disturbance or insomnia, and none of the most recent studies, which were also the most methodologically rigorous, found significant effects of valerian on sleep. The authors concluded that valerian is a safe herb associated with only rare adverse events, but that the evidence does not support its clinical efficacy as a sleep aid for insomnia.
A 2010 meta-analysis of 18 randomised placebo-controlled trials (Fernández-San-Martín and colleagues, Sleep Medicine) separated what people reported from what was measured. People on valerian were more likely to say their sleep had improved (relative risk 1.37, 95% CI 1.05 to 1.78), but the measured time to fall asleep differed from placebo by only 0.70 minutes (95% CI −3.44 to 4.83), and sleep-quality scores on rating scales did not differ. The authors concluded that valerian may give a subjective improvement in insomnia, but that its effectiveness "has not been demonstrated with quantitative or objective measurements."
A 2020 systematic review and meta-analysis (Shinjyo and colleagues) covered 60 studies with 6,894 people and pooled 10 studies (1,065 people) on subjective sleep quality. It suggested that the inconsistent results may be due to the variable quality of herbal extracts, with more reliable effects expected from the whole root and rhizome, and it found no severe adverse events in people aged 7 to 80. Its authors concluded that valerian could be a safe and effective herb to promote sleep.
The American Academy of Sleep Medicine's 2017 clinical practice guideline on medicines for chronic insomnia in adults states: “We suggest that clinicians not use valerian as a treatment for sleep onset or sleep maintenance insomnia (versus no treatment) in adults.” It is graded a WEAK recommendation, which the guideline defines as reflecting a lower degree of certainty, not as an indication of ineffectiveness.
Mechanism — Valerenic Acid, Valepotriates, GABA Transaminase, 5-HT5A
The pharmacology of valerian's sedative-hypnotic effect involves multiple low-affinity mechanisms acting on overlapping central nervous system (CNS) pathways, none individually sufficient to explain the clinical effect.
Valerenic acid (the lead modern actor). Valerenic acid is a sesquiterpene unique to Valeriana officinalis (not found in related V. wallichii, V. edulis, or other commercial substitutes). It is the standardization target for most modern commercial extracts. The receptor pharmacology has been characterized over the past two decades:
- Positive allosteric modulation of gamma-aminobutyric acid-A receptors at the beta-2 and beta-3 subunits — a binding site distinct from the alpha-gamma benzodiazepine site, which means valerenic acid does not directly compete with benzodiazepines for receptor binding
- Weak inhibition of gamma-aminobutyric acid (GABA) transaminase (GABA-T), the catabolic enzyme that breaks down gamma-aminobutyric acid in the synaptic cleft, extending the duration of gamma-aminobutyric acid's tonic inhibitory signal
- Weak partial agonist activity at the adenosine A1 receptor — the same receptor that caffeine antagonizes, with sleep-promoting effects in the opposite direction
- In vitro affinity for the 5-HT5A serotonin receptor (Kd in the low-micromolar range), a receptor expressed in the suprachiasmatic nucleus and dorsal raphe with possible circadian implications
Valepotriates (the controversial older actor). Valepotriates are epoxide-containing iridoid esters that were originally proposed as the primary sedative principle in valerian. They have several problematic properties: they degrade rapidly on storage (so commercial dried-root preparations contain very little after a few months on the shelf), they have raised genotoxicity flags in some in vitro assays (Ames test, sister chromatid exchange), and they are absorbed poorly from the gut. Modern standardized extracts often deliberately exclude valepotriates by using aqueous or ethanol extraction methods that leave them behind. The clinical effect of these modern valepotriate-free extracts is essentially a valerenic-acid effect, which is reassuring from a safety perspective.
GABA transaminase inhibition mechanism. The GABA transaminase inhibition hypothesis is appealing because it predicts a cumulative effect: chronic inhibition of GABA transaminase should produce a gradual increase in central nervous system gamma-aminobutyric acid tone over days to weeks, paralleling the delayed onset reported in some trials (Donath 2000). This contrasts sharply with the mechanism of benzodiazepines (which directly amplify gamma-aminobutyric acid-A response and produce immediate effect) and with the mechanism of barbiturates (which open chloride channels even in absence of gamma-aminobutyric acid and again produce immediate effect). If valerian's effect is slow in onset, as the cumulative model holds, it would fit a GABA transaminase mechanism better than either of those.
The 5-HT5A binding finding. The 5-HT5A receptor is expressed primarily in the suprachiasmatic nucleus (the brain's master circadian clock), the dorsal raphe (a major serotonergic nucleus), and the cerebellum. Its function is poorly characterized, and there are essentially no other drugs that bind it selectively. The hypothesis that valerian's "different feel" compared to benzodiazepines (more dream-rich sleep, less morning cognitive impairment, less amnestic effect) may relate to 5-HT5A modulation is an active area of research but not yet established.
For the broader discussion of how multiple weak mechanisms can produce a meaningful clinical effect through additive low-affinity action, see our Valerian Benefits Hub.
The 600-900 mg Standardized Dose Range
The consensus dose range for modern standardized valerian extracts is 600-900 mg of a 0.8% valerenic acid extract, taken one hour before bed, every night. This range emerged from the clinical trial literature in the late 1990s and early 2000s and is reflected in the German Commission E monograph, the European Medicines Agency HMPC monograph, and most North American consumer products.
The dose-equivalents across different preparations:
- Standardized extract (0.8% valerenic acid): 600-900 mg one hour before bed (this is the dose used in most modern trials)
- Dried root (cut or powdered): 2-3 g, typically prepared as a tea infusion (steep 10-15 minutes in hot water)
- Liquid extract (1:5 in 70% ethanol): 4-6 mL one hour before bed
- Tincture (1:1 fluid extract): 1-3 mL one hour before bed
Several practical considerations modify the standard guidance:
- Standardization matters. Unstandardized "valerian root powder" capsules have highly variable valerenic acid content and produce unpredictable effects. Products labeled with a valerenic acid percentage state their content.
- Older preparations contain less. Valerian's active compounds degrade on storage. Capsules older than 12 months may have substantially reduced potency. The tea/infusion form (made fresh from dried root) is more reproducible than aged capsules but tastes worse.
- The smell is unmistakable. Whole-root and tea preparations smell strongly of "dirty socks" or "fermented gym shorts" due to isovaleric acid. This is a sign of authenticity rather than spoilage. Capsules largely mask the smell.
- Timing relative to bedtime. In a study of 6 healthy adults given a single 600 mg dose of valerian, valerenic acid peaked in the blood between 1 and 2 hours after the dose in five of the six, and stayed measurable for at least 5 hours. The authors noted that this timing fits the standard dosage direction to take valerian 30 minutes to 2 hours before bedtime. On this reasoning, a dose taken at the moment of lying down would peak later in the night.
- The 14-day question. Advocates of the cumulative model describe allowing 14 days before judging and regard one-night trials as uninformative; the trials of two weeks of nightly use are mixed (see the next section).
Chronic Use and the Cumulative-Effect Model
The cumulative-effect model holds that valerian works only after days to weeks of nightly use. Some trials fit it: the Donath 2000 trial found no single-dose effect but improvements in slow-wave sleep after multiple doses. The wider trial literature does not: the 2007 Taibi review found most studies showed no significant difference from placebo whatever their length, and the 2010 meta-analysis of 18 trials found no difference in measured time to fall asleep (0.70 minutes). If the model is right, the pattern is the opposite of the pattern with benzodiazepines and Z-drugs (immediate effect, tolerance with chronic use) and is more reminiscent of selective serotonin reuptake inhibitors (delayed onset, sustained effect with chronic use).
The most direct test of two weeks of nightly use is a 2009 randomised, double-blind crossover trial in 16 older women with insomnia (average age 69). They took 300 mg of concentrated valerian extract or placebo 30 minutes before bedtime for 2 weeks, and their sleep was measured in the sleep laboratory (by questionnaire and polysomnography) and at home (by sleep logs and wrist actigraphy). There were no statistically significant differences between valerian and placebo after a single dose or after 2 weeks of nightly dosing on any measure of time to fall asleep, time awake after first falling asleep, sleep efficiency or self-rated sleep quality. Side effects were minor and did not differ from placebo.
Three hypotheses for the cumulative effect have been proposed:
- Active compound accumulation — the idea that valerenic acid builds up over days of repeated dosing to a level that is too low on the first dose. The measurements do not support it: valerenic acid has a short elimination half-life (1.1 ± 0.6 hours in 6 healthy adults given 600 mg; one of the six showed a second peak at 5 hours), and in older women its peak level, total exposure and half-life did not differ significantly after 2 weeks of nightly dosing compared with a single dose.
- Adaptive change in gamma-aminobutyric acid-A receptor expression or function — chronic GABA transaminase inhibition (raising synaptic gamma-aminobutyric acid) may induce a homeostatic increase in post-synaptic gamma-aminobutyric acid-A receptor sensitivity or density, the opposite of the well-documented receptor downregulation seen with chronic benzodiazepine use.
- Anxiolytic-mediated sleep effect — valerian's primary effect may be reduction of pre-sleep anxiety and physiological hyperarousal, which itself takes 1-2 weeks of consistent use to manifest. Better sleep would then be a secondary consequence of a less hyperaroused state, not a direct hypnotic effect.
Advocates of the cumulative model hold that a personal valerian trial shorter than two weeks is not informative, and describe taking 600-900 mg every night for two to four weeks before judging whether it works; they say many people conclude "it didn't work for me" after one or two nights. The two-week randomised trial above, at 300 mg, found no difference from placebo.
For the broader insomnia context including the prescription-hypnotic alternatives and cognitive behavioral therapy for insomnia (CBT-I, the first-line treatment for chronic insomnia per the American Academy of Sleep Medicine), see our Insomnia page.
Compared to Prescription Hypnotics (Benzodiazepines, Z-Drugs, Trazodone)
The clinically useful comparison is not "is valerian as effective as zolpidem" (it is not) but "what is valerian useful for that prescription hypnotics are not."
Benzodiazepines (temazepam, lorazepam, clonazepam, alprazolam). Prescription benzodiazepines have an immediate, large effect on sleep latency on the first night, but they produce tolerance (loss of effect with chronic use), dependence (need for the drug to feel normal), withdrawal (rebound insomnia and anxiety on discontinuation), and substantial cognitive carry-over the next morning. Older patients on chronic benzodiazepines have measurably increased fall risk, hip fracture risk, and dementia risk. The American Geriatrics Society Beers Criteria explicitly recommends against routine benzodiazepine use in adults over 65. Valerian produces a smaller acute effect than a benzodiazepine but does not produce tolerance, dependence, or significant cognitive carry-over, which is why herbal practitioners regard it as preferable for chronic use by people who do not need maximal acute effect.
Z-drugs (zolpidem, eszopiclone, zaleplon). Z-drugs were developed to address the cognitive carry-over of benzodiazepines and have largely succeeded on that front. However, they retain tolerance and dependence concerns with chronic use, and zolpidem in particular has well-documented complex sleep behaviors (sleepwalking, sleep-eating, sleep-driving) in a minority of users. Valerian's safety profile is meaningfully better than zolpidem's for chronic use.
Trazodone. Low-dose trazodone (50-100 mg) is commonly prescribed off-label for insomnia and has a different profile from either benzodiazepines or Z-drugs: it does not produce dependence and does not lose effect with chronic use. Trazodone is probably more effective than valerian on a head-to-head comparison and is used for patients who tolerate it. The downside is the side effect profile: orthostatic hypotension, anticholinergic effects, occasional priapism in men, and morning grogginess in some patients. Valerian is gentler on all of these dimensions but less effective.
Melatonin. Melatonin is a chronobiotic rather than a true hypnotic. It works best for circadian-rhythm sleep disorders (jet lag, shift work, delayed sleep-phase syndrome) rather than primary insomnia. Some people combine melatonin with valerian when they have both a delayed sleep phase and primary insomnia.
Diphenhydramine and other over-the-counter (OTC) antihistamines. Diphenhydramine (sold alone and in night-time pain-reliever combinations) is the most commonly used over-the-counter sleep aid in the United States. It has substantial anticholinergic burden, is on the Beers Criteria for avoidance in older adults, and rapidly develops tolerance with nightly use. Herbal practitioners regard it as in most respects a worse choice than valerian for chronic over-the-counter use, though it is still used for occasional acute sleeplessness.
Herbal practitioners position valerian as an over-the-counter sleep aid for adults with chronic mild-to-moderate insomnia who want to avoid prescription hypnotics, who are willing to commit to a 14-day trial, and who are not seeking immediate first-night effect. The American Academy of Sleep Medicine's 2017 guideline, by contrast, suggests that clinicians not use valerian for trouble falling or staying asleep (a WEAK recommendation; see the review section above).
Effect on Sleep Architecture (Polysomnographic Findings)
The PSG studies of valerian, taken together, suggest a profile that differs from prescription hypnotics in important ways:
- Slow-wave sleep (NREM stage 3-4) is preserved or increased. Benzodiazepines characteristically suppress slow-wave sleep (the deepest, most restorative stage of NREM). Z-drugs have less effect on slow-wave sleep than benzodiazepines but still produce some suppression. Valerian, in the Donath 2000 study and several follow-up trials, increased slow-wave sleep on chronic dosing — the opposite of the typical prescription-hypnotic effect.
- REM sleep is preserved. Most prescription hypnotics suppress REM sleep to some degree. Valerian does not appear to suppress REM in the PSG studies that have been done, and may actually slightly increase REM in some protocols.
- Sleep efficiency improves modestly in some trials. Sleep efficiency (total sleep time / total time in bed) has been reported to improve by approximately 5-10% in chronic-use trials, compared with 15-25% for prescription hypnotics. In the Donath 2000 trial, sleep efficiency rose on both valerian and placebo, and in the 2009 two-week trial in older women it did not differ from placebo.
- Measured sleep latency does not differ from placebo in pooled trials. The 2010 meta-analysis of 18 randomised trials found a mean difference in time to fall asleep between valerian and placebo of 0.70 minutes (95% CI −3.44 to 4.83) — no measurable reduction, against the typical 30-45 minute reduction reported with zolpidem or a benzodiazepine.
The pattern is consistent with valerian's reputation as a gentler agent: smaller acute effect, but more preservation of natural sleep architecture, less cognitive carry-over, and no rebound insomnia on discontinuation. Herbal practitioners present it as an option for people who put sleep architecture and morning function ahead of peak acute hypnotic effect.
Combination Products (Valerian + Hops, Valerian + Lemon Balm)
Several traditional and modern formulations combine valerian with other sedative herbs, on the theory that the additive low-affinity-mechanism model that explains valerian within itself also applies to combinations.
Valerian + Hops (Humulus lupulus). The valerian-plus-hops combination is the most-studied. Hops contains 2-methyl-3-buten-2-ol, which has documented sedative activity and binds to gamma-aminobutyric acid-A receptors. The Schmitz and Jäckel 1998 randomized controlled trial (RCT), a double-blind parallel-group study with no placebo arm, compared a valerian-hops combination with a low-dose benzodiazepine (bromazepam) in 46 patients with non-chronic sleep disorders (temporary trouble falling or staying asleep); over 2 weeks of treatment the combination was equivalent to the benzodiazepine on sleep quality, fitness and quality of life, and withdrawal symptoms were documented with the benzodiazepine. Several subsequent trials have replicated this favorable result, and valerian-hops combination products are widely sold in Europe under several brand names.
Valerian + Lemon Balm (Melissa officinalis). Lemon balm has documented anxiolytic and mild sedative effects mediated by inhibition of gamma-aminobutyric acid transaminase — the same mechanism as valerian, suggesting additive rather than synergistic action. The Cerny and Schmid 1999 trial (a double-blind, placebo-controlled multicentre study of tolerability and efficacy in healthy volunteers) and the Müller and Klement 2006 pediatric study are cited in support of valerian-lemon balm combinations for sleep restlessness, particularly in children. The Müller and Klement study was open, with no control group: in 918 children under 12 with restlessness and sleep problems, dosed individually by the investigators, 80.9% of those with sleep problems and 70.4% of those with restlessness were rated as improved. Its first author worked for the product's manufacturer. See our Lemon Balm page.
Valerian + Passionflower (Passiflora incarnata). Passionflower contains chrysin and other flavonoids with gamma-aminobutyric acid-A modulating activity. The combination is widely used in over-the-counter sleep formulations but has less randomized controlled trial evidence than the valerian-hops combination. See our Passionflower page.
Valerian + Magnesium. Magnesium glycinate (the most-absorbed and most-calming form) at 200-400 mg taken at bedtime alongside valerian is a widely-used combination, especially in patients with concurrent muscle tension or restless legs symptoms. The mechanisms are complementary (magnesium acts at the N-methyl-D-aspartate (NMDA) receptor and as a calcium-channel modulator, valerian at gamma-aminobutyric acid pathways). See our Magnesium Glycinate page.
Practical Facts for People Considering Valerian
- Expectations. Valerian is not a benzodiazepine; single-dose trials found no first-night effect. Advocates of the chronic-use model describe a 14-day trial before judging whether it works, while a two-week randomised trial and the 2010 meta-analysis found no measurable difference from placebo.
- Standardized products. Standardized capsules carry a label such as "standardized to 0.8% valerenic acid." Unstandardized "valerian root powder" products have unpredictable potency.
- Timing. The dose most often cited is 600-900 mg; the standard dosage direction is 30 minutes to 2 hours before bedtime, which matches the 1-2 hour peak of valerenic acid in the blood.
- Sleep hygiene. Herbal practitioners present valerian as an adjunct to a consistent sleep schedule, a dark and cool bedroom, no screens for an hour before bed, no caffeine after 2 PM, and no alcohol within 3 hours of bedtime, and hold that without those foundations no sleep aid works well. See our Sleep Hygiene page.
- Cognitive behavioral therapy for insomnia. Cognitive behavioral therapy for insomnia is the American Academy of Sleep Medicine's recommended first-line treatment for chronic insomnia, more effective than any pharmacologic intervention including prescription hypnotics. It is also delivered by apps without a clinician visit, including a prescription digital cognitive behavioural therapy app cleared by the U.S. Food and Drug Administration.
- Stopping. Unlike benzodiazepines, valerian does not produce withdrawal or rebound insomnia on discontinuation; it can be stopped from 900 mg nightly to zero with no taper.
- When two weeks show no benefit. Valerian does not help everyone. Practitioners hold that if a 14-day trial at 600-900 mg produced no perceptible benefit, the probability that 4 or 6 weeks will reveal a benefit is low.
Cautions, Drug Interactions, and Failure Modes
- Central nervous system depressant interactions. Valerian's sedative effect is additive with alcohol, benzodiazepines, opioids, Z-drugs, sedating antihistamines (diphenhydramine, doxylamine), and sedating antidepressants (trazodone, mirtazapine, tricyclics); taken together, their sedative effects add up.
- Driving and operating machinery. Even though next-morning carry-over from valerian is modest, individual variability exists. In the 1982 Leathwood study, one over-the-counter valerian preparation significantly increased reports of feeling more sleepy than normal the next morning.
- Pregnancy and lactation. Safety data in pregnancy and lactation are limited. Both the WHO and the European Medicines Agency recommend avoidance of valerian in pregnancy and lactation due to lack of data, not due to documented harm.
- Children. The German pediatric literature contains several positive trials of valerian (often combined with lemon balm) for sleep restlessness in children over age 3. Pediatric dosing is weight-adjusted and lower than adult dosing. The largest of these studies (918 children under 12) was open-label with no control group, and the children were dosed individually by the investigators.
- Hepatotoxicity (rare). Isolated case reports of valerian-associated hepatotoxicity exist in the literature, but causation has typically been confounded by polypharmacy. The 1989 spontaneous-report cluster in the UK that prompted brief regulatory concern was eventually attributed to a contaminated product rather than valerian itself. Modern standardized extracts have an excellent hepatic safety record.
- Anesthesia. Valerian may add to the sedative effect of anesthetic agents, and a theoretical interaction with anesthetic metabolism has been raised; the precaution commonly described is stopping valerian at least 1 week before elective surgery.
- Cytochrome P450 3A4 (CYP3A4) interactions. In vitro studies suggest weak cytochrome P450 3A4 inhibition by valerian extracts, raising theoretical concerns about interactions with substrates of that enzyme (many statins, calcium channel blockers, immunosuppressants). Clinical significance is uncertain. Cyclosporine and tacrolimus are cytochrome P450 3A4 substrates with a narrow margin between an effective and a toxic blood level, so even a small change in how fast they are broken down matters for them.
- Common failure mode: paradoxical agitation. A small minority of patients experience paradoxical agitation, vivid dreams, or worsened insomnia on valerian. This is uncommon (estimated under 5% of users) but real; worsened sleep after starting valerian is the sign of this reaction.
For the broader cautions discussion across all valerian benefits including the smell-tolerance issue, see the Valerian Benefits Hub.
Key Research Papers
- Leathwood PD, Chauffard F, Heck E, Munoz-Box R (1982). Aqueous extract of valerian root (Valeriana officinalis) improves sleep quality in man. Pharmacology, Biochemistry, and Behavior. — PubMed PMID: 7122669
- Leathwood PD, Chauffard F (1985). Aqueous extract of valerian reduces latency to fall asleep in man. Planta Medica (2):144-8. — PubMed PMID: 4034730
- Donath F, Quispe S, Diefenbach K, Maurer A, Fietze I, Roots I (2000). Critical evaluation of the effect of valerian extract on sleep structure and sleep quality. Pharmacopsychiatry 33(2):47-53. — PubMed PMID: 10761819
- Bent S, Padula A, Moore D, Patterson M, Mehling W (2006). Valerian for sleep: a systematic review and meta-analysis. American Journal of Medicine 119(12):1005-12. — PubMed PMID: 17145239
- Taibi DM, Landis CA, Petry H, Vitiello MV (2007). A systematic review of valerian as a sleep aid: safe but not effective. Sleep Medicine Reviews 11(3):209-30. — PubMed PMID: 17517355
- Taibi DM, Vitiello MV, Barsness S, Elmer GW, Anderson GD, Landis CA (2009). A randomized clinical trial of valerian fails to improve self-reported, polysomnographic, and actigraphic sleep in older women with insomnia. Sleep Medicine 10(3):319-28. — PubMed PMID: 18482867
- Schmitz M, Jäckel M (1998). Comparative study for assessing quality of life of patients with exogenous sleep disorders treated with a hops-valerian preparation and a benzodiazepine drug. Wiener Medizinische Wochenschrift. — PubMed PMID: 9757514
- Khom S, Baburin I, Timin E, et al. (2007). Valerenic acid potentiates and inhibits GABA-A receptors: molecular mechanism and subunit specificity. Neuropharmacology. — PubMed PMID: 17585957
- Benke D, Barberis A, Kopp S, et al. (2009). GABA-A receptors as in vivo substrate for the anxiolytic action of valerenic acid, a major constituent of valerian root extracts. Neuropharmacology. — PubMed PMID: 18602406
- Trauner G, Khom S, Baburin I, Benedek B, Hering S, Kopp B (2008). Modulation of GABA-A receptors by valerian extracts is related to the content of valerenic acid. Planta Medica. — PubMed PMID: 18095218
- Cropley M, Cave Z, Ellis J, Middleton RW (2002). Effect of kava and valerian on human physiological and psychological responses to mental stress. Phytotherapy Research. — PubMed PMID: 11807960
- Stevinson C, Ernst E (2000). Valerian for insomnia: a systematic review of randomized clinical trials. Sleep Medicine. — PubMed PMID: 10767649
- Fernández-San-Martín MI, Masa-Font R, Palacios-Soler L, Sancho-Gómez P, Calbó-Caldentey C, Flores-Mateo G (2010). Effectiveness of Valerian on insomnia: a meta-analysis of randomized placebo-controlled trials. Sleep Medicine 11(6):505-11. — PubMed PMID: 20347389
- Anderson GD, Elmer GW, Kantor ED, Templeton IE, Vitiello MV (2005). Pharmacokinetics of valerenic acid after administration of valerian in healthy subjects. Phytotherapy Research 19(9):801-3. — PubMed PMID: 16220575
- Anderson GD, Elmer GW, Taibi DM, Vitiello MV, Kantor E, Kalhorn TF, Howald WN, Barsness S, Landis CA (2010). Pharmacokinetics of valerenic acid after single and multiple doses of valerian in older women. Phytotherapy Research 24(10):1442-6. — PubMed PMID: 20878691
- Müller SF, Klement S (2006). A combination of valerian and lemon balm is effective in the treatment of restlessness and dyssomnia in children. Phytomedicine 13(6):383-7. — PubMed PMID: 16487692
- Cerny A, Schmid K (1999). Tolerability and efficacy of valerian/lemon balm in healthy volunteers (a double-blind, placebo-controlled, multicentre study). Fitoterapia 70(3):221-228. — doi:10.1016/s0367-326x(99)00018-0
- Shinjyo N, Waddell G, Green J (2020). Valerian Root in Treating Sleep Problems and Associated Disorders-A Systematic Review and Meta-Analysis. Journal of Evidence-Based Integrative Medicine 25:2515690X20967323. — PubMed PMID: 33086877
- Sateia MJ, Buysse DJ, Krystal AD, Neubauer DN, Heald JL (2017). Clinical Practice Guideline for the Pharmacologic Treatment of Chronic Insomnia in Adults: An American Academy of Sleep Medicine Clinical Practice Guideline. Journal of Clinical Sleep Medicine 13(2):307-349. — PubMed PMID: 27998379
- Hadley S, Petry JJ (2003). Valerian. American Family Physician. — PubMed PMID: 12725454
PubMed Topic Searches
Connections
- All Herbs
- Valerian Overview
- Valerian Benefits Hub
- Valerian for Anxiety
- Valerian for Muscle Relaxation
- Valerian for Menstrual Cramps
- Passionflower
- Lemon Balm
- Chamomile
- Lavender
- Kava
- Ashwagandha
- Magnesium
- Magnesium Glycinate
- Insomnia
- Anxiety
- Sleep Hygiene
- Stress Management
- Natural Anxiety Relief
- History