⚠ Evidence warning: Clinical trials or other evidence do not support the claims that valerian eases the whole-body symptoms of period pain and that herb combinations add to each other. This page keeps it as a report of what people, websites or other media say.
Valerian for Menstrual Cramps
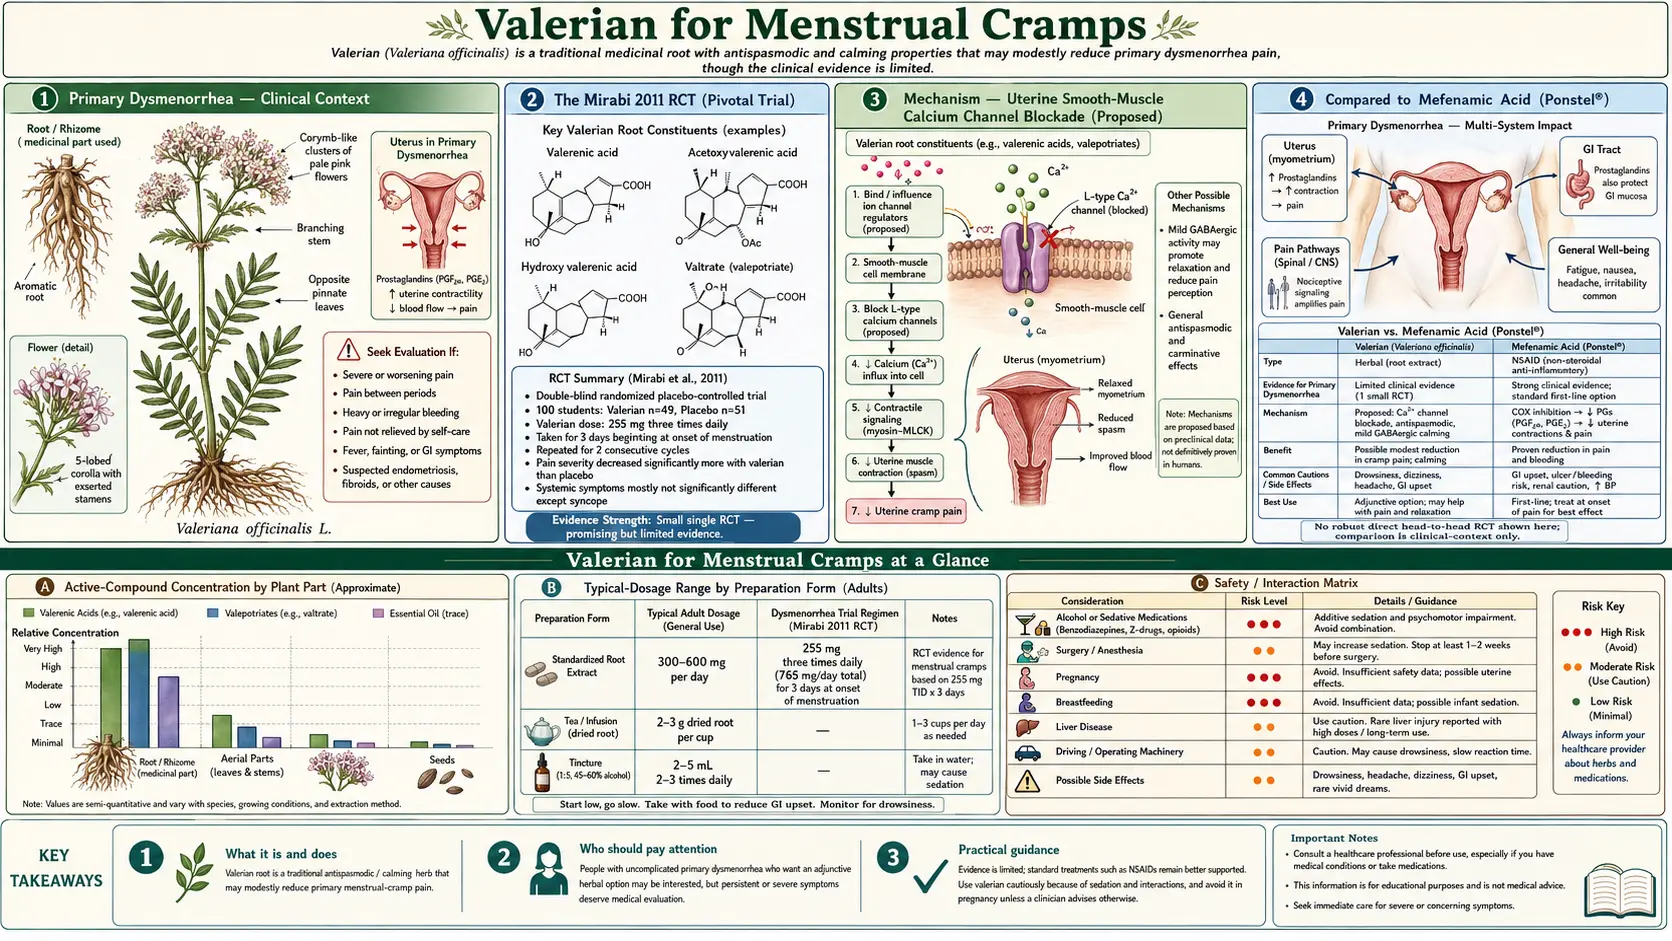
Primary dysmenorrhea — painful menstrual cramps without underlying pelvic pathology — affects roughly half of menstruating women and is severe enough to disrupt daily activity in 10-15%. The first-line pharmacologic treatment is nonsteroidal anti-inflammatory drugs (ibuprofen, naproxen, mefenamic acid), which work by inhibiting cyclooxygenase-mediated prostaglandin synthesis in the endometrium. Valerian has emerged from the Iranian, Turkish, and broader Middle Eastern gynecology research as an adjunct studied mainly for cramp severity, with practitioners also describing effects on the broader systemic symptoms of dysmenorrhea (nausea, fatigue, headache, mood). The pivotal trial is Mirabi et al. 2011 (International Journal of Gynaecology and Obstetrics), which compared valerian 255 mg three times daily with placebo over two menstrual cycles in 100 students with primary dysmenorrhea and found a larger fall in pain severity than with placebo; systemic symptoms fell in both groups, with a difference between groups only for syncope (fainting or lightheadedness). The proposed mechanism is uterine smooth-muscle calcium-channel blockade (the same final pathway as nifedipine, which has been used off-label for severe dysmenorrhea, though with substantially higher potency and worse tolerability than valerian). The place discussed for it is as an adjunct to or partial substitute for mefenamic acid in people who cannot tolerate full nonsteroidal anti-inflammatory drug (NSAID) dosing, who have nonsteroidal anti-inflammatory drug-induced gastrointestinal (GI) symptoms, or who prefer plant-based options. This page synthesizes the published evidence, the proposed mechanism, the comparison with mefenamic acid and other first-line treatments, and the practical dosing and timing for the dysmenorrhea indication.
Table of Contents
- Primary Dysmenorrhea — Clinical Context
- The Mirabi 2011 Randomized Controlled Trial (Pivotal Trial)
- Mechanism — Uterine Smooth-Muscle Calcium Channel Blockade
- Compared to Mefenamic Acid
- Compared to Ibuprofen, Naproxen, and Other Nonsteroidal Anti-Inflammatory Drugs
- Compared to Oral Contraceptives
- The Iranian and Turkish Gynecology Research Tradition
- Systemic Symptoms (Nausea, Fatigue, Headache, Mood)
- Combination Protocols (Valerian + Chamomile, Valerian + Fennel, Valerian + Ginger)
- Dosing and Timing for Dysmenorrhea
- Endometriosis and Secondary Dysmenorrhea
- Cautions and Drug Interactions
- Key Research Papers
- Connections
- Featured Videos
Primary Dysmenorrhea — Clinical Context
Dysmenorrhea is the medical term for painful menstrual periods. Primary dysmenorrhea is painful menstruation in the absence of identifiable pelvic pathology — the pain is generated by the normal physiologic processes of menstruation, primarily uterine contractions stimulated by prostaglandin release from the shedding endometrium. Secondary dysmenorrhea is painful menstruation due to an identifiable underlying condition (endometriosis, adenomyosis, fibroids, pelvic inflammatory disease, intrauterine device complications).
Primary dysmenorrhea typically begins within 6-12 months of menarche, once ovulatory cycles establish, and follows a characteristic pattern: cramping pain in the lower abdomen and back, beginning hours before or at the start of menstrual flow, peaking in the first 24-48 hours, and resolving within 2-3 days. Associated systemic symptoms (nausea, vomiting, diarrhea, headache, fatigue, dizziness) reflect the systemic effects of prostaglandin release.
The pathophysiology is dominated by prostaglandin F2-alpha (PGF2a) and prostaglandin E2 (PGE2), produced in the endometrium during menstruation from arachidonic acid via cyclooxygenase enzymes. PGF2a is a potent vasoconstrictor and uterine contractant; PGE2 contributes to inflammation and pain sensitization. Women with severe primary dysmenorrhea have measurably higher endometrial prostaglandin production than women with mild or no dysmenorrhea, providing the basis for the dominance of nonsteroidal anti-inflammatory drugs (cyclooxygenase inhibitors) in pharmacologic management.
First-line evidence-based treatments per ACOG (American College of Obstetricians and Gynecologists) and similar international guidelines:
- Nonsteroidal anti-inflammatory drugs (ibuprofen 400-600 mg every 6 hours, naproxen 250-500 mg every 12 hours, mefenamic acid 500 mg as a first dose, then 250 mg every 6 hours, per its US label) — the most effective single class
- Combined oral contraceptives or other hormonal suppression of ovulation
- Heat application (heating pads, hot water bottles)
- Exercise (moderate aerobic exercise has small but real effect)
- TENS (transcutaneous electrical nerve stimulation) — modest evidence
Adjunctive interventions with smaller but real evidence bases include omega-3 fatty acids, magnesium, thiamine, vitamin B6, and the herbal interventions including valerian, chamomile, fennel, ginger, and dill that this page and related pages cover.
The Mirabi 2011 Randomized Controlled Trial (Pivotal Trial)
The Mirabi et al. 2011 trial, published in International Journal of Gynaecology and Obstetrics, is the foundational and most-cited randomized controlled trial of valerian for primary dysmenorrhea. Parvaneh Mirabi and colleagues (the paper lists the Department of Midwifery, Zanjan Branch, Islamic Azad University, Iran) ran a double-blind trial in 100 female students with primary dysmenorrhea, randomized to valerian (n=49) or placebo (n=51): valerian 255 mg three times daily (765 mg/day) for three days starting at the onset of menstruation, over two consecutive menstrual cycles.
The primary outcomes were:
- Pain severity, measured by visual analog scale (VAS) on the worst day of each cycle
- Severity of systemic manifestations, measured by a composite score covering nausea, vomiting, syncope, fatigue, diarrhea, and mood disturbance
Results at the end of the second cycle:
- Pain severity — pain fell significantly in both groups (P<0.001), but the fall was larger in the valerian group, and the difference between the groups was statistically significant (P<0.05). The abstract gives no point difference; the 2016 Cochrane review of dietary supplements, which re-analysed this trial, gives a mean difference of 0.76 points on the 0–10 scale in favour of valerian (95% CI 0.08 to 1.44; one trial, 100 women), with the evidence rated low or very low quality.
- Systemic manifestations — total systemic-symptom scores fell after treatment in both groups, with no significant difference between the groups except for syncope (fainting or lightheadedness), which improved more with valerian (P<0.05).
- Side effects — no significant difference between valerian and placebo for any adverse event. No serious adverse events.
The trial established that a relatively short course of valerian (three days per cycle, starting at menses onset) at a moderate dose (765 mg/day in divided doses) produced a larger fall in pain than placebo in primary dysmenorrhea, while overall systemic symptoms improved equally in both groups apart from syncope. It is one of the cleaner positive randomized controlled trials (RCTs) in the valerian clinical literature, with a well-defined population, a standard pain scale and a reasonable dose; the effect size was modest (0.76 points on 0–10 in the Cochrane re-analysis).
The trial does have limitations: single-center, modest sample size, no head-to-head comparison with mefenamic acid or other nonsteroidal anti-inflammatory drug, no objective measure of uterine contractility (such as intrauterine pressure recording), no biochemical correlates (such as endometrial prostaglandin levels). A larger multi-center replication with active comparator would strengthen the evidence base. Such a replication has not been published, though several follow-up Iranian and Turkish studies have extended the framework.
Mechanism — Uterine Smooth-Muscle Calcium Channel Blockade
The proposed mechanism for valerian's analgesic effect in dysmenorrhea is uterine smooth-muscle relaxation via L-type voltage-gated calcium channel blockade, the same mechanism discussed in detail on the Muscle Relaxation page. The uterus, like the gut, contains abundant smooth muscle with L-type calcium channels mediating excitation-contraction coupling.
The mechanistic plausibility is supported by several lines of evidence:
- In vitro tissue studies — isolated rat uterus preparations (the standard pharmacologic model) show concentration-dependent inhibition of spontaneous and oxytocin-induced contractions by valerian extracts and isolated valerenic acid. The potency is modest (high-micromolar range) but the effect is consistent and dose-dependent.
- Clinical analogy with prescription calcium channel blockers — nifedipine, a potent L-type calcium channel blocker primarily marketed for hypertension and Raynaud's syndrome, has documented off-label use in severe dysmenorrhea and in preterm labor (tocolysis). The same mechanism produces both clinical effects. The tolerability of nifedipine is poor (headache, flushing, ankle edema, reflex tachycardia), which limits its use for dysmenorrhea despite documented efficacy. Valerian's much weaker calcium-channel effect avoids these adverse effects while providing modest benefit.
- Effect on systemic symptoms — the systemic symptoms of dysmenorrhea (nausea, syncope, fatigue) are largely mediated by prostaglandin-driven sympathetic dysregulation and visceral pain signaling. Valerian's central anxiolytic and sympatholytic effects are a proposed mechanism for the effect on syncope seen in the Mirabi trial, in addition to the direct uterine effect.
Secondary mechanisms that may contribute include:
- Central pain modulation via gamma-aminobutyric acid-A — valerenic acid's gamma-aminobutyric acid-A modulation provides central pain reduction independent of the uterine mechanism
- Anxiolytic effect on pain perception — reduction of anxiety amplification of pain, particularly in patients with anticipatory anxiety about menstrual pain
- Sleep improvement — better sleep during menses (often disrupted by pain) reduces pain sensitization the following day
- Possible direct prostaglandin modulation — some in vitro evidence suggests valerian extracts may have weak effects on cyclooxygenase activity, though this is not a primary mechanism and the potency is far below nonsteroidal anti-inflammatory drugs (NSAIDs)
The clinical interpretation: valerian's modest analgesic effect in dysmenorrhea is mechanistically plausible and operates through multiple parallel low-potency pathways. It is discussed as an adjunct, or as a partial substitute for people who cannot tolerate nonsteroidal anti-inflammatory drugs, rather than as a full replacement for them in moderate-to-severe primary dysmenorrhea.
Compared to Mefenamic Acid
Mefenamic acid is a fenamate nonsteroidal anti-inflammatory drug that has been specifically promoted for primary dysmenorrhea since the 1970s. It is the usual active comparator in the Iranian and Turkish herbal trials for period pain. The US label's dose for period pain is 500 mg as a first dose, followed by 250 mg every 6 hours, starting with the onset of bleeding and associated symptoms; an older version of the label adds that treatment "should not be necessary for more than 2 to 3 days".
Mefenamic acid's pharmacology is unusual among nonsteroidal anti-inflammatory drugs: in addition to the standard cyclooxygenase inhibition shared with all nonsteroidal anti-inflammatory drugs, a 1979 laboratory study on isolated human womb muscle found that mefenamate and two related fenamates greatly reduced contractions set off by a prostaglandin endoperoxide analogue, and its authors proposed that this blocking action, together with reduced prostaglandin production, may explain how fenamates relieve period pain (Sanger and Bennett 1979). The trials do not show it to be stronger than other NSAIDs, however: the 2015 Cochrane review of 80 randomized trials (5,820 women) found little evidence that any individual NSAID was superior to another for pain relief or safety, and concluded that there is insufficient evidence to determine which, if any, individual NSAID is the safest and most effective for dysmenorrhea.
The downside is the side-effect profile shared by the drug class: in the same Cochrane review, NSAIDs caused more side effects than placebo, including more gastrointestinal side effects (odds ratio 1.58); the review names indigestion among the side effects commonly reported with NSAIDs. The US label for mefenamic acid states that long-term use of drugs of this family, including mefenamic acid, has resulted in renal papillary necrosis and other kidney injury; its adverse-reactions list also names interstitial nephritis and hemolytic anemia.
The Mirabi trial did not directly compare valerian with an NSAID. The 2016 Cochrane review of dietary supplements found one trial (99 women) that did: it reports a mean difference of 0.62 points on the 0–10 pain scale (95% CI 0.03 to 1.21) and lists this comparison among those showing no evidence of a difference. All of the evidence in that review was rated low or very low quality, and it found the side-effect data too scanty to reach any conclusions about safety.
Compared to Ibuprofen, Naproxen, and Other Nonsteroidal Anti-Inflammatory Drugs
Ibuprofen and naproxen are the most-prescribed nonsteroidal anti-inflammatory drugs globally and the first-line treatment for primary dysmenorrhea in most Western practice settings. Standard regimens:
- Ibuprofen — 400-600 mg every 6 hours starting at onset of menses or, preferably, in anticipation 1-2 days before predicted menses
- Naproxen — 250-500 mg every 12 hours (the longer half-life reduces dosing burden)
- Diclofenac — 50 mg every 8 hours; effective but with higher cardiovascular risk in chronic use
- Celecoxib (cyclooxygenase-2 (COX-2) selective) — 200 mg every 12 hours; useful in patients with nonsteroidal anti-inflammatory drug-related gastrointestinal sensitivity, but cardiovascular risk profile limits chronic use
The valerian-vs-NSAID comparison for dysmenorrhea rests on the same single trial described above, which the Cochrane review lists as showing no evidence of a difference. NSAIDs carry the gastrointestinal, kidney and cardiovascular concerns that limit their long-term use; the valerian trials reported few side effects, but the Cochrane review found too little safety data to compare the two.
Situations in which NSAIDs carry known risks or are unwanted, and where valerian is sometimes used as a partial substitute:
- Patients with nonsteroidal anti-inflammatory drug-related dyspepsia, gastritis, or a history of peptic ulcer disease (PUD)
- Patients on anticoagulation (warfarin, direct oral anticoagulants (DOACs)) where nonsteroidal anti-inflammatory drug-induced bleeding risk is concerning
- Patients with chronic kidney disease where chronic nonsteroidal anti-inflammatory drug use is contraindicated
- Patients with nonsteroidal anti-inflammatory drug allergy or AERD (aspirin-exacerbated respiratory disease)
- Patients who explicitly prefer plant-based or non-pharmacologic options
- Adolescent patients whose parents prefer not to start regular nonsteroidal anti-inflammatory drug use early
Situations in which the trials give little support for valerian on its own, and in which NSAIDs are the standard first-line treatment:
- Moderate-to-severe primary dysmenorrhea (VAS pain >6)
- Dysmenorrhea associated with documented endometriosis or adenomyosis
- Acute pain rescue (valerian's slow onset is not useful for acute pain)
- Dysmenorrhea that has been previously well-controlled with nonsteroidal anti-inflammatory drugs without intolerance
Compared to Oral Contraceptives
Combined oral contraceptive pills (OCPs; estrogen-progestin pills) are highly effective for primary dysmenorrhea, typically reducing pain severity by 70-80% through suppression of ovulation and thinning of endometrial prostaglandin production. They are used by patients who also want contraception or whose severe dysmenorrhea is not adequately controlled by nonsteroidal anti-inflammatory drugs.
Valerian and oral contraceptives are complementary rather than competitive in clinical practice. Patients on OCPs generally have minimal dysmenorrhea and rarely use valerian for this indication. Patients who cannot tolerate OCPs (smokers over 35, history of migraine with aura, history of venous thromboembolism (VTE, blood clots), breastfeeding) often use valerian and nonsteroidal anti-inflammatory drug combinations as the alternative approach.
For patients on OCPs who continue to experience breakthrough dysmenorrhea (perhaps 10-15% of OCP users), valerian is sometimes used as an adjunct. The combination is well-tolerated and the mechanisms are non-overlapping (OCP suppresses ovulation and endometrial development; valerian relaxes uterine smooth muscle and modulates central pain perception).
Continuous (extended-cycle) OCPs that eliminate the placebo week and skip menstrual bleeding entirely are a widely used approach for severe primary dysmenorrhea in people who can take OCPs: by skipping the monthly bleed, they also skip the cramps that come with it.
The Iranian and Turkish Gynecology Research Tradition
The most active research community studying valerian in dysmenorrhea is in Iran, with additional contributions from Turkey, Iraq, and the broader Middle Eastern academic medicine ecosystem. Iranian universities (Babol University of Medical Sciences, Tehran University of Medical Sciences, Tarbiat Modares University, and others) have published several dozen randomized controlled trials of herbal interventions for primary dysmenorrhea over the past 15 years, frequently using mefenamic acid as the active comparator.
The herbs studied include valerian, chamomile, fennel (Foeniculum vulgare), ginger (Zingiber officinale), dill (Anethum graveolens), saffron (Crocus sativus), peppermint (Mentha piperita), and many others. The research tradition reflects both the strong local pharmacy curriculum and the cultural prominence of herbal medicine in Iranian, Persian, and broader Middle Eastern medical practice.
The pooled findings across this research literature support several conclusions:
- Multiple herbs produce measurable benefit — valerian, ginger, chamomile, and fennel all have positive randomized controlled trial (RCT) data in primary dysmenorrhea with comparable effect sizes
- Head-to-head comparisons with NSAIDs mostly found no difference — ginger matched mefenamic acid and ibuprofen in 150 students (Ozgoli 2009), fennel did not differ from mefenamic acid (Modaress Nejad 2006), and the 2016 Cochrane review found no evidence of a difference between NSAIDs and dill, fennel, rhubarb or valerian, with very limited evidence that chamomile was more effective than NSAIDs
- Safety data are thin — in the Cochrane review only four of 27 trials reported side effects in both groups; there was no evidence of a difference, but the data were too scanty to reach conclusions, and the reviewers state that evidence of safety is lacking
- Combination herbal protocols appear to be additive — ginger plus valerian, or chamomile plus fennel, produce larger effects than either alone in the small comparative studies that have looked at this
Two later meta-analyses pooled this literature. A 2025 meta-analysis of valerian alone combined 5 controlled trials (201 women on valerian, 207 controls) comparing valerian with placebo or NSAIDs: pain fell more with valerian than with the control treatments (standardized mean difference −1.03; 95% CI −1.74 to −0.33), which the authors describe as about 1 point on a 0–10 scale, and valerian was well tolerated. The results varied greatly between trials (I² = 90%), and the authors call for more standardized trials. A 2026 meta-analysis of plant-based treatments (47 trials reviewed, 22 pooled) found herbal products no different in pain relief from conventional drugs such as mefenamic acid or ibuprofen (1,133 women; mean difference 0.12 points, 95% CI −0.29 to 0.53) and better than placebo (941 women; mean difference −1.83 points). Side effects were infrequent and mild, but the certainty of the evidence was rated low to very low.
This regional research tradition has not been heavily incorporated into Western dysmenorrhea guidelines (which still focus almost exclusively on nonsteroidal anti-inflammatory drugs and OCPs), but it provides a substantial empirical base for the herbal adjunctive options that integrative practitioners and patients in the West increasingly seek out.
The Mirabi 2011 trial is a representative example of this research tradition, both in study design (active herb vs placebo, primary dysmenorrhea population, two-cycle duration, VAS pain primary outcome with systemic symptom secondary outcome) and in its institutional setting (an Iranian university midwifery department) and authorship (Iranian gynecology and pharmacology faculty).
Systemic Symptoms (Nausea, Fatigue, Headache, Mood)
Practitioners describe valerian's effect in dysmenorrhea as reaching beyond the uterine cramping pain to the systemic symptoms that frequently accompany it. The Mirabi 2011 trial measured these with a multidimensional verbal scale covering symptoms such as nausea, vomiting, syncope (lightheadedness), fatigue, diarrhea, and mood disturbance. Total systemic-symptom scores fell in both the valerian and placebo groups, with no significant difference between the groups except for syncope, which improved more with valerian (P<0.05).
The proposed links to valerian's broader pharmacology:
- Anxiolytic effect reduces the mood-disturbance and anticipatory-anxiety component of dysmenorrhea
- Sympathetic-tone reduction reduces the syncope/lightheadedness and palpitations
- Sleep effect reduces the fatigue, particularly when menstrual pain is disrupting sleep
- Gastrointestinal smooth-muscle effect reduces the diarrhea and abdominal cramping outside the uterine component
- Central pain modulation reduces the headache component, which is itself driven in part by prostaglandin-mediated cerebral vasodilation
Practitioners see the systemic-symptom effect as a possible advantage of valerian over single-mechanism analgesics, although in the Mirabi trial only syncope differed from placebo. Nonsteroidal anti-inflammatory drugs primarily address the uterine pain through prostaglandin inhibition but do less for the mood and sleep components. Acetaminophen is even more narrowly targeted. Practitioners report that patients on valerian for dysmenorrhea often describe "feeling better overall during my period" rather than just "less cramping"; the Mirabi trial did not find a difference from placebo in overall systemic symptoms.
For patients with prominent menstrual-cycle mood symptoms (premenstrual syndrome (PMS) or premenstrual dysphoric disorder (PMDD)), the broader pattern of valerian's benefit may be more useful than the cramp-specific application. The combination of valerian with calcium, magnesium, and vitamin B6 (the standard PMS supplement stack) is widely used and has modest supporting evidence.
Combination Protocols (Valerian + Chamomile, Valerian + Fennel, Valerian + Ginger)
The Iranian and Turkish gynecology research has examined several herbal combinations for dysmenorrhea, with valerian appearing as a component in many protocols.
Valerian + chamomile. Chamomile (Matricaria recutita) contains apigenin, a flavonoid with gamma-aminobutyric acid-A modulating activity, and bisabolol with antispasmodic effects. The combination addresses uterine spasm and central anxiety through partially overlapping mechanisms. Chamomile tea (1-2 cups daily during menses) plus valerian capsules is a common Iranian and Turkish protocol. See our Chamomile page.
Valerian + fennel. Fennel (Foeniculum vulgare) is a documented antispasmodic with positive randomized controlled trial data in primary dysmenorrhea. The Modaress Nejad 2006 trial in 110 high-school girls (mean age 13) found no significant difference in pain relief between fennel extract and mefenamic acid: 80% of the fennel group and 73% of the mefenamic acid group had complete pain relief or less pain. The combination with valerian addresses uterine and gastrointestinal smooth-muscle spasm simultaneously. Practitioners use it particularly for people with prominent gastrointestinal symptoms during menses.
Valerian + ginger. Ginger (Zingiber officinale) has multiple positive randomized controlled trials in primary dysmenorrhea (Ozgoli 2009, Rahnama 2012, and others), with effect sizes comparable to nonsteroidal anti-inflammatory drugs. The mechanism involves cyclooxygenase inhibition (giving ginger pharmacology that overlaps with nonsteroidal anti-inflammatory drugs in target) plus anti-inflammatory and antiemetic effects. Combination with valerian addresses pain (overlapping pharmacology) plus anxiety and sleep (valerian-specific effects). The ginger plus valerian combination is one of the more empirically supported herbal regimens for dysmenorrhea.
Valerian + cramp bark (Viburnum opulus). Cramp bark, as the name suggests, has a strong reputation in Western herbalism for menstrual cramps, with documented uterine antispasmodic effects in animal models. The combination is widely used in Western herbal practice though less studied in formal randomized controlled trials.
Valerian + magnesium glycinate. Magnesium has been studied for menstrual-cycle symptoms. Quaranta 2007 was an open-label pilot study without a control group in 41 women with premenstrual syndrome (PMS), not period pain: after three cycles of a modified-release magnesium tablet, the total PMS score fell by 35.1% as rated by the investigator and 33.5% as rated by the women. The mechanism involves calcium-channel modulation (parallel to valerian's mechanism) and central N-methyl-D-aspartate (NMDA) receptor effects. The two act on related pathways. See our Magnesium Glycinate page.
Valerian + omega-3 fatty acids. Omega-3 fatty acids (eicosapentaenoic acid (EPA) + docosahexaenoic acid (DHA)) compete with arachidonic acid as cyclooxygenase substrate, shifting prostaglandin production toward less inflammatory PGE3 series and away from the inflammatory PGE2 and PGF2a series that drive dysmenorrhea. Daily eicosapentaenoic acid + docosahexaenoic acid supplementation reduces dysmenorrhea severity in trials, with effect that develops over months rather than within a single cycle.
An integrative protocol practitioners describe for chronic primary dysmenorrhea: daily omega-3 fish oil (1-2 g eicosapentaenoic acid + docosahexaenoic acid), daily magnesium glycinate (200-400 mg), valerian during menses (600-900 mg/day starting at menses onset for 2-3 days), nonsteroidal anti-inflammatory drug as needed for breakthrough pain. Practitioners describe the components as individually modest but cumulatively helpful and well tolerated.
Dosing and Timing for Dysmenorrhea
The standard valerian regimen for dysmenorrhea, based on the Mirabi trial and follow-up Iranian and Turkish studies:
- Dose — 250-300 mg of standardized valerian extract three times daily, totaling 750-900 mg/day during menses
- Duration — start at the onset of menstrual flow, continue for 3 days, then discontinue until next menses
- Form — capsules of standardized 0.8% valerenic acid extract; tincture forms can be used but are less convenient
- Timing of doses — morning, mid-afternoon, and evening; the bedtime dose provides sleep benefit during the typically sleep-disrupting menses period
An alternative regimen is anticipatory dosing — start valerian 1-2 days before predicted menses to allow some accumulation, then continue through the first 2-3 days of flow. This may produce better effect for patients with very acute and severe onset on the first day.
Practical considerations:
- The daytime doses can produce mild sedation in some patients, particularly the first cycle. Many patients find that they tolerate this fine after the first cycle. Some adjust to twice-daily dosing (morning and bedtime) to avoid midday sedation.
- Heat (a heating pad on the lower abdomen or back) is often used alongside it; heat has its own pain-relieving effect, proposed to work through gate-control mechanisms.
- Practitioners describe judging the effect over 2-3 cycles, because individual response varies widely and the first cycle may not be representative.
- Nonsteroidal anti-inflammatory drugs are commonly kept for breakthrough pain; in moderate or severe dysmenorrhea valerian is generally used as an adjunct rather than a substitute for them.
Endometriosis and Secondary Dysmenorrhea
Endometriosis is a chronic condition in which endometrial-like tissue grows outside the uterus, producing chronic pelvic pain, dysmenorrhea, dyspareunia (painful intercourse), and frequently infertility. It affects approximately 10% of reproductive-age women and is a major cause of secondary dysmenorrhea (painful menses due to identifiable pathology rather than normal physiology).
The first-line treatments for endometriosis are hormonal suppression (combined OCPs, progestins, gonadotropin-releasing hormone (GnRH) agonists or antagonists, danazol), nonsteroidal anti-inflammatory drugs for pain, and surgical excision of lesions for definitive diagnosis and tissue reduction. The condition is chronic and often requires combination therapy over many years.
The role of valerian in endometriosis is much more limited than in primary dysmenorrhea. The pain in endometriosis is driven by ectopic endometrial tissue with associated inflammation, fibrosis, and pelvic anatomic distortion — not primarily by uterine smooth-muscle contraction in normal endometrium. Valerian's uterine smooth-muscle calcium-channel mechanism is less relevant when the pain generator is extra-uterine.
Practitioners describe valerian as an adjunct in endometriosis for:
- Sleep disturbance from chronic pelvic pain
- Anxiety and depression related to chronic disease management
- Modest reduction of associated functional gastrointestinal symptoms (bowel endometriosis or coincident irritable bowel syndrome, IBS)
- Reduction of central pain sensitization through gamma-aminobutyric acid (GABA) mechanisms
Endometriosis is treated with the hormonal, pain-relief and surgical options listed above; valerian's role is limited to these adjunct uses and does not replace endometriosis-specific treatment.
Cautions and Drug Interactions
- Pregnancy. There is not enough safety data on valerian in pregnancy. Uterine smooth-muscle relaxant activity, while desirable in the non-pregnant patient with dysmenorrhea, is a theoretical concern in pregnancy. The World Health Organization (WHO) and the European Medicines Agency (EMA) both advise against use in pregnancy; the EMA monograph gives the lack of data as the reason.
- Lactation. Limited data; the WHO and European Medicines Agency advise against use while breastfeeding.
- Secondary dysmenorrhea. Valerian has been studied only in primary dysmenorrhea. New-onset severe dysmenorrhea in adulthood, dysmenorrhea that has changed character, or dysmenorrhea with other symptoms (heavy bleeding, dyspareunia, infertility) can be signs of endometriosis, adenomyosis, fibroids, or other pathology, which gynecologists investigate.
- Concurrent nonsteroidal anti-inflammatory drugs. No significant pharmacokinetic interaction between valerian and nonsteroidal anti-inflammatory drugs is known, and the combination is the most common clinical use pattern.
- Concurrent hormonal contraception. No significant pharmacokinetic interaction between valerian and oral contraceptives has been documented.
- Central nervous system (CNS) depressant interactions. Additive sedative effect with alcohol, benzodiazepines, opioids: the combined sedation can be stronger than either alone.
- Driving and operating machinery. The 3x daily dosing for dysmenorrhea includes daytime doses that may produce mild sedation, which can affect driving.
- Anesthesia. Valerian's sedative effect can add to that of anesthetic drugs; pre-surgery guidance commonly lists stopping it at least 1 week before elective surgery.
- Inadequate response. If valerian produces no perceptible benefit after 2-3 cycles, a higher dose is unlikely to help. The other options covered on this page are nonsteroidal anti-inflammatory drugs and hormonal treatment, and symptoms that persist can point to secondary dysmenorrhea.
Key Research Papers
- Mirabi P, Dolatian M, Mojab F, Majd HA (2011). Effects of valerian on the severity and systemic manifestations of dysmenorrhea. International Journal of Gynaecology and Obstetrics. — PubMed PMID: 21959068
- Mirabi P, Mojab F (2013). The effects of valerian root on hot flashes in menopausal women. Iranian Journal of Pharmaceutical Research. — PubMed PMID: 24250592
- Modaress Nejad V, Asadipour M (2006). Comparison of the effectiveness of fennel and mefenamic acid on pain intensity in dysmenorrhoea. Eastern Mediterranean Health Journal. — PubMed PMID: 17037712
- Ozgoli G, Goli M, Moattar F (2009). Comparison of effects of ginger, mefenamic acid, and ibuprofen on pain in women with primary dysmenorrhea. Journal of Alternative and Complementary Medicine. — PubMed PMID: 19216660
- Rahnama P, Montazeri A, Huseini HF, Kianbakht S, Naseri M (2012). Effect of Zingiber officinale R. rhizomes (ginger) on pain relief in primary dysmenorrhea: a placebo randomized trial. BMC Complementary and Alternative Medicine. — PubMed PMID: 22781186
- Quaranta S, Buscaglia MA, Meroni MG, Colombo E, Cella S (2007). Pilot study of the efficacy and safety of a modified-release magnesium 250 mg tablet (Sincromag) for the treatment of premenstrual syndrome. Clinical Drug Investigation. (Open-label pilot study in 41 women with premenstrual syndrome, no control group.) — PubMed PMID: 17177579
- Marjoribanks J, Ayeleke RO, Farquhar C, Proctor M (2015). Nonsteroidal anti-inflammatory drugs for dysmenorrhoea. Cochrane Database of Systematic Reviews. — PubMed PMID: 26224322
- Pattanittum P, Kunyanone N, Brown J, et al. (2016). Dietary supplements for dysmenorrhoea. Cochrane Database of Systematic Reviews. — PubMed PMID: 27000311
- Rabiei F, Delavar MA, Mirabi P, Masoumi P, Jahanshahi A (2025). Effect of Valeriana officinalis on Primary Dysmenorrhea: A Systematic Review and Meta-Analysis. Reviews on Recent Clinical Trials. — PubMed PMID: 40965071
- Wu L, Xu Lou I, Hu Z, Wang G, Deshpande SV, Cáceres-Matos R (2026). Efficacy of Plant-Derived Therapies for Primary Dysmenorrhea: A Systematic Review and Meta-Analysis of Randomized Controlled Trials. Phytotherapy Research. — PubMed PMID: 41983255
- Iorno V, Burani R, Bianchini B, Minelli E, Martinelli F, Ciatto S (2008). Acupuncture treatment of dysmenorrhea resistant to conventional medical treatment. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 18604253
- Jenabi E, Fereidoony B (2015). Effect of Achillea millefolium on relief of primary dysmenorrhea: a double-blind randomized clinical trial. Journal of Pediatric and Adolescent Gynecology. — PubMed PMID: 26238568
- Dawood MY (2006). Primary dysmenorrhea: advances in pathogenesis and management. Obstetrics and Gynecology. — PubMed PMID: 16880317
- Proctor M, Farquhar C (2006). Diagnosis and management of dysmenorrhoea. BMJ. — PubMed PMID: 16690671
- Sanger GJ, Bennett A (1979). Fenamates may antagonize the actions of prostaglandin endoperoxides in human myometrium. British Journal of Clinical Pharmacology 8(5):479-82. — PubMed PMID: 508555
PubMed Topic Searches
Connections
- All Herbs
- Valerian Overview
- Valerian Benefits Hub
- Valerian for Sleep
- Valerian for Anxiety
- Valerian for Muscle Relaxation
- Chamomile
- Passionflower
- Lemon Balm
- Lavender
- Magnesium
- Magnesium Glycinate
- Anxiety
- Insomnia
- Heart Palpitations
- Migraine
- Cramp Prevention
- Sleep Hygiene
- Stress Management
- Natural Anxiety Relief
- Endometriosis — a leading cause of secondary dysmenorrhea, where valerian is only an adjunct.
- History