Valerian — Benefits Deep Dive
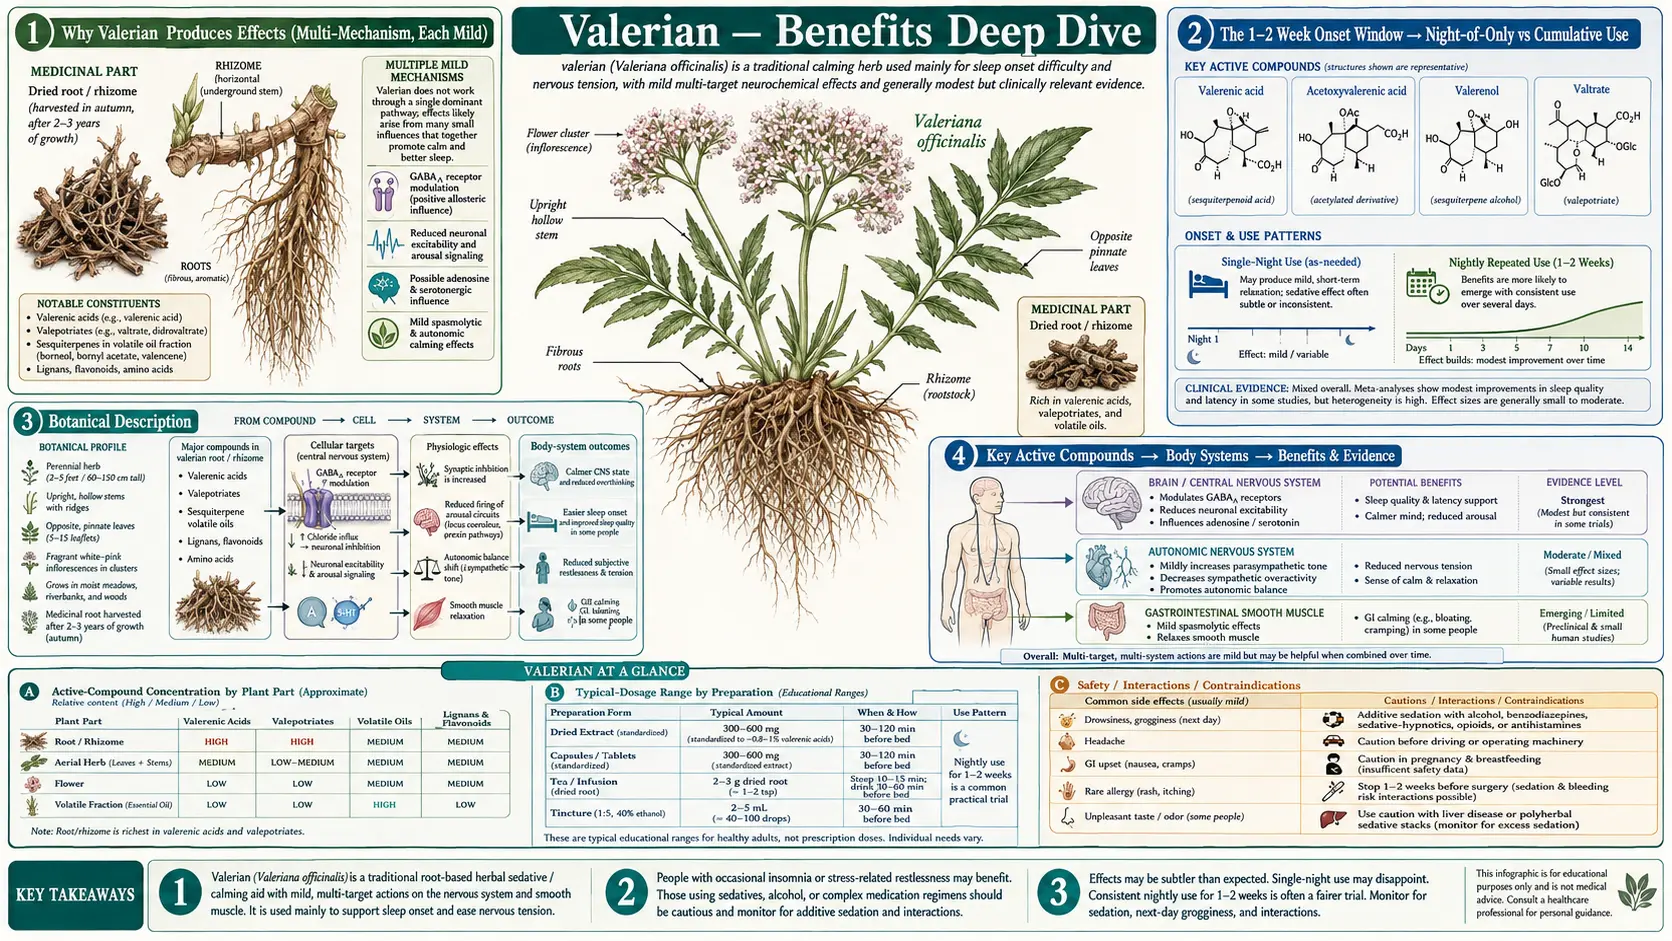
Valeriana officinalis is the most-popular herbal sleep aid in the Western world, with sales in the hundreds of millions of dollars annually across Europe, North America, and Japan. It is also one of the most polarizing herbal medicines — clinical trials that test it as a fast-acting hypnotic (compared head-to-head with a benzodiazepine on the first night of use) typically find little or no effect, while trials that test it for two to four weeks of continuous use typically find a meaningful improvement in sleep latency and sleep quality. The active chemistry is split between the controversial valepotriates (epoxide-containing compounds that degrade rapidly on storage and may be genotoxic in vitro) and the better-tolerated valerenic acid (a sesquiterpene with documented gamma-aminobutyric acid-A receptor binding). The smell is unmistakable — old valerian root preparations are routinely described as "dirty socks" or "fermented gym shorts," which has limited consumer acceptance. The four benefit pages below explore the conditions where valerian produces measurable clinical effect — the chronic-insomnia application that founded its modern reputation, generalized anxiety, smooth-muscle relaxation including the traditional restless-legs application, and the surprisingly well-documented Iranian and Turkish gynecology literature on primary dysmenorrhea.
Deep-Dive Articles
Sleep Quality
The Bent 2006 meta-analysis (16 trials), the Donath 2000 sleep-latency crossover trial, the Leathwood 1982 sleep-quality study and 1985 sleep-latency paper, among the most-cited valerian sleep studies, the dual valerenic-acid + valepotriate active-compound model, gamma-aminobutyric acid (GABA) transaminase (gamma-aminobutyric acid-T) inhibition combined with 5-HT5A receptor binding, and the doses used in the trials, which Bent 2006 found varied considerably — no settled dose has emerged for chronic insomnia.
Read the deep dive →Anxiety Relief
The Andreatini 2002 generalized anxiety disorder pilot trial (valepotriates vs diazepam vs placebo in 36 outpatients for 4 weeks, with no significant difference among the three groups on the main anxiety score), valerenic acid as a positive allosteric modulator at the gamma-aminobutyric acid-A receptor (binding at a site distinct from benzodiazepines), and the proposed 1-2 week onset window, which would fit ongoing anxiety better than sudden panic.
Read the deep dive →Muscle Relaxation
Antispasmodic effect on intestinal and uterine smooth muscle, the traditional restless-legs-syndrome application that has been formalized in a small but encouraging clinical literature, comparison with prescription muscle relaxants (cyclobenzaprine, methocarbamol, baclofen), and the emerging fibromyalgia adjunctive role for patients seeking non-pharmacologic options.
Read the deep dive →Menstrual Cramps
The Mirabi 2011 placebo-controlled dysmenorrhea randomized controlled trial (100 students, valerian 255 mg three times a day for two cycles; pain fell more with valerian than with placebo), the proposed uterine smooth-muscle calcium-channel-blockade mechanism, how valerian compares with the prescription pain reliever mefenamic acid (the Mirabi trial itself had no mefenamic acid group), and the broader Iranian and Turkish gynecology literature in which valerian has been studied alongside chamomile, fennel, and ginger as a tolerable adjunct to nonsteroidal anti-inflammatory drug (NSAID) therapy for primary dysmenorrhea.
Read the deep dive →Table of Contents
Why Valerian Produces Effects (Multi-Mechanism, Each Mild)
Valerian is unusual among sedative-hypnotic compounds in that it has no single dominant active compound and no single dominant mechanism. The traditional "active ingredient" question — the one that pharmacologists asked from the 1960s through the 1990s about valerian — never resolved cleanly because valerian root is a mixture of dozens of biologically active small molecules, none of which is potent enough alone to fully explain the clinical effect. The modern model is that valerian works through four parallel low-affinity mechanisms that act additively on the same final pathway (central nervous system (CNS) depression and smooth-muscle relaxation), and the failure of any single fraction to reproduce whole-root effects in animal studies is itself evidence for the multi-mechanism model.
- Gamma-aminobutyric acid transaminase (gamma-aminobutyric acid-T) inhibition — valerenic acid and its derivatives weakly inhibit the enzyme that catabolizes gamma-aminobutyric acid in the synaptic cleft and presynaptic terminal. The net effect is to extend gamma-aminobutyric acid's tonic inhibitory signal, which is the same final pathway as benzodiazepines (which positively modulate gamma-aminobutyric acid-A receptors) and Z-drugs (zolpidem at the alpha-1 subunit), but achieved upstream by raising local gamma-aminobutyric acid concentration rather than amplifying its receptor effect. See Sleep Quality for the clinical translation.
- Gamma-aminobutyric acid-A receptor positive allosteric modulation (separate site from benzodiazepines) — valerenic acid binds to the gamma-aminobutyric acid-A receptor at the beta-2 and beta-3 subunits, at a site distinct from the benzodiazepine-binding site at the alpha-gamma interface. This produces a positive allosteric effect on the receptor's response to gamma-aminobutyric acid, similar in mechanism (but much weaker in potency) to benzodiazepines and barbiturates. The clinical anxiolytic effect appears to be driven primarily by this mechanism — see Anxiety Relief.
- 5-HT5A serotonin receptor binding — in vitro radioligand binding studies have identified affinity for the 5-HT5A receptor, a poorly-characterized serotonin receptor subtype expressed in the suprachiasmatic nucleus and dorsal raphe. This may explain why valerian feels "different from a benzodiazepine" in subjective reports — some patients describe more dream-rich sleep and less morning cognitive impairment than with prescription hypnotics.
- Adenosine A1 receptor activity and calcium channel blockade — multiple valerian fractions have weak partial agonist activity at the adenosine A1 receptor (the same receptor caffeine blocks, which is why caffeine is wake-promoting and adenosine accumulation is sleep-promoting), and additional weak blockade of L-type voltage-gated calcium channels in smooth muscle. These together explain the antispasmodic and uterine-relaxant effects discussed in Muscle Relaxation and Menstrual Cramps.
The chemistry is split between two compound classes with very different reputations. Valerenic acid (a sesquiterpene unique to Valeriana officinalis and not found in related Valeriana species) is the most consistently studied and most likely the dominant clinical actor. It is stable on storage, has reasonably well-characterized receptor binding, and is the standardization target for most modern commercial extracts (the 0.8% valerenic acid standardized extract is the de facto industry standard). Valepotriates (epoxide-containing iridoid esters) are the older "controversial" active class — they degrade rapidly on storage (so old preparations contain very little), they have raised genotoxicity flags in some in vitro assays, and modern extracts often deliberately exclude them by using ethanol or aqueous extraction methods that leave the lipophilic valepotriates behind. The clinical effect of standardized modern extracts is largely a valerenic-acid effect with valepotriate exclusion.
A 2020 systematic review and meta-analysis (Shinjyo and colleagues; 60 studies, 6,894 people) linked the inconsistent results of earlier valerian trials to the variable quality of the herbal extracts, and found that more reliable effects could be expected from the whole root and rhizome. It found no severe side effects linked to valerian in people aged 7 to 80. The authors note that some active constituents are unstable, so standardization methods and shelf life may need revisiting.
The 1-2 Week Onset Window — Night-of-Only vs Cumulative Use
The single most important practical fact about valerian — the one that explains both the disappointing acute trials and the favorable chronic trials — is that its onset of action is described as not "night of." Practitioners describe people who take 600 mg of standardized valerian extract for the first time, an hour before bed, on the night of a stressful day, as often noticing no effect, and the same people, after 600 mg every night for two weeks, as reporting that they fall asleep faster, wake less in the early morning, and sleep better. This two-week pattern is a working hypothesis rather than an established finding. One small trial fits it: in Donath 2000 (16 people with insomnia), a single dose had no effect on sleep structure, while after 14 days the time to reach deep (slow-wave) sleep was shorter with valerian than with placebo (13.5 vs 21.3 minutes); overall sleep efficiency rose with both valerian and placebo. The Bent 2006 meta-analysis pooled 16 trials with 1,093 patients; most had significant methodologic problems, and the doses, preparations and length of treatment varied considerably. In the 6 studies that reported sleep quality as improved or not, valerian gave a relative risk of improved sleep of 1.8 (95% CI 1.2–2.9), but with evidence of publication bias. This pattern is the opposite of the benzodiazepines and Z-drugs, which work on the first night (often dramatically) but lose effect with chronic use due to tolerance.
The mechanism of the cumulative effect is not fully understood. Three hypotheses have been advanced:
- Active metabolite accumulation — the idea that valerian constituents build up with repeated dosing to a steady-state level that a single dose does not reach. This does not fit valerenic acid itself: in six healthy adults given a single 600 mg dose, its elimination half-life was short, 1.1 ± 0.6 hours, with peak levels 1 to 2 hours after the dose (Anderson 2005)
- Adaptive change in gamma-aminobutyric acid-A receptor density or sensitivity — some animal models suggest that chronic gamma-aminobutyric acid-T inhibition leads to upregulation of post-synaptic gamma-aminobutyric acid-A response, analogous (in opposite direction) to the well-documented downregulation seen with chronic benzodiazepine use
- Anxiolytic effect translating to sleep effect — valerian's primary mechanism may actually be reduction of pre-sleep anxiety and hyperarousal, which itself takes 1-2 weeks of consistent use to manifest, and the better sleep is a secondary consequence of less hyperaroused state
If the pattern holds, people who try valerian once, "the night before a big presentation," and notice nothing are describing what single-dose trials found. Practitioners describe two weeks of nightly use, at 600-900 mg of a standardized 0.8% valerenic acid extract one hour before bed, as giving a clearer picture of whether valerian helps a given person; the trials themselves used doses that varied considerably (Bent 2006). Marketing that implies a first-night effect sets up a different expectation from what the longer trials tested. For the contrast with prescription hypnotics that do work on the first night, see our Insomnia page.
Key Research Papers
- Bent S, Padula A, Moore D, Patterson M, Mehling W (2006). Valerian for sleep: a systematic review and meta-analysis. American Journal of Medicine 119(12):1005-1012. — PubMed PMID: 17145239
- Donath F, Quispe S, Diefenbach K, Maurer A, Fietze I, Roots I (2000). Critical evaluation of the effect of valerian extract on sleep structure and sleep quality. Pharmacopsychiatry 33(2):47-53. — PubMed PMID: 10761819
- Leathwood PD, Chauffard F, Heck E, Munoz-Box R (1982). Aqueous extract of valerian root (Valeriana officinalis L.) improves sleep quality in man. Pharmacology, Biochemistry, and Behavior 17(1):65-71. — PubMed PMID: 7122669
- Leathwood PD, Chauffard F (1985). Aqueous extract of valerian reduces latency to fall asleep in man. Planta Medica (2):144-148. — PubMed PMID: 4034730
- Andreatini R, Sartori VA, Seabra ML, Leite JR (2002). Effect of valepotriates (valerian extract) in generalized anxiety disorder: a randomized placebo-controlled pilot study. Phytotherapy Research 16(7):650-654. — PubMed PMID: 12410546
- Mirabi P, Dolatian M, Mojab F, Majd HA (2011). Effects of valerian on the severity and systemic manifestations of dysmenorrhea. International Journal of Gynaecology and Obstetrics 115(3):285-288. — PubMed PMID: 21959068
- Anderson GD, Elmer GW, Kantor ED, Templeton IE, Vitiello MV (2005). Pharmacokinetics of valerenic acid after administration of valerian in healthy subjects. Phytotherapy Research 19(9):801-803. — PubMed PMID: 16220575
- Shinjyo N, Waddell G, Green J (2020). Valerian root in treating sleep problems and associated disorders — a systematic review and meta-analysis. Journal of Evidence-Based Integrative Medicine 25:2515690X20967323. — PubMed PMID: 33086877
PubMed Topic Searches
External Authoritative Resources
- U.S. National Institutes of Health (NIH) Office of Dietary Supplements — Valerian Fact Sheet (Health Professionals) — the most authoritative single summary of valerian pharmacology, clinical trials, and safety
- U.S. National Center for Complementary and Integrative Health (NCCIH) (National Center for Complementary and Integrative Health) — Valerian
- European Medicines Agency — Valerianae radix monograph (HMPC traditional-use registration)
- LiverTox (U.S. National Institutes of Health) — Valerian
- PubMed — All research on Valeriana officinalis (~2,000+ papers)
Connections
- All Herbs
- Valerian (Main Page)
- Valerian for Sleep Quality
- Valerian for Anxiety Relief
- Valerian for Muscle Relaxation
- Valerian for Menstrual Cramps
- Passionflower
- Lemon Balm
- Chamomile
- Lavender
- Kava
- Ashwagandha
- Rhodiola Rosea
- Magnesium
- Magnesium Glycinate
- Insomnia
- Anxiety
- Depression
- Stress Management
- Sleep Hygiene
- Natural Anxiety Relief
- Cramp Prevention
- History