⚠ Evidence warning: Clinical trials or other evidence do not support the claim that a 12-week trial of standardized black cohosh extract is reasonable for breast-cancer survivors on tamoxifen who get no relief from venlafaxine or gabapentin. This page keeps it as a report of what people, websites or other media say.
Black Cohosh for Menopause & Hot Flashes
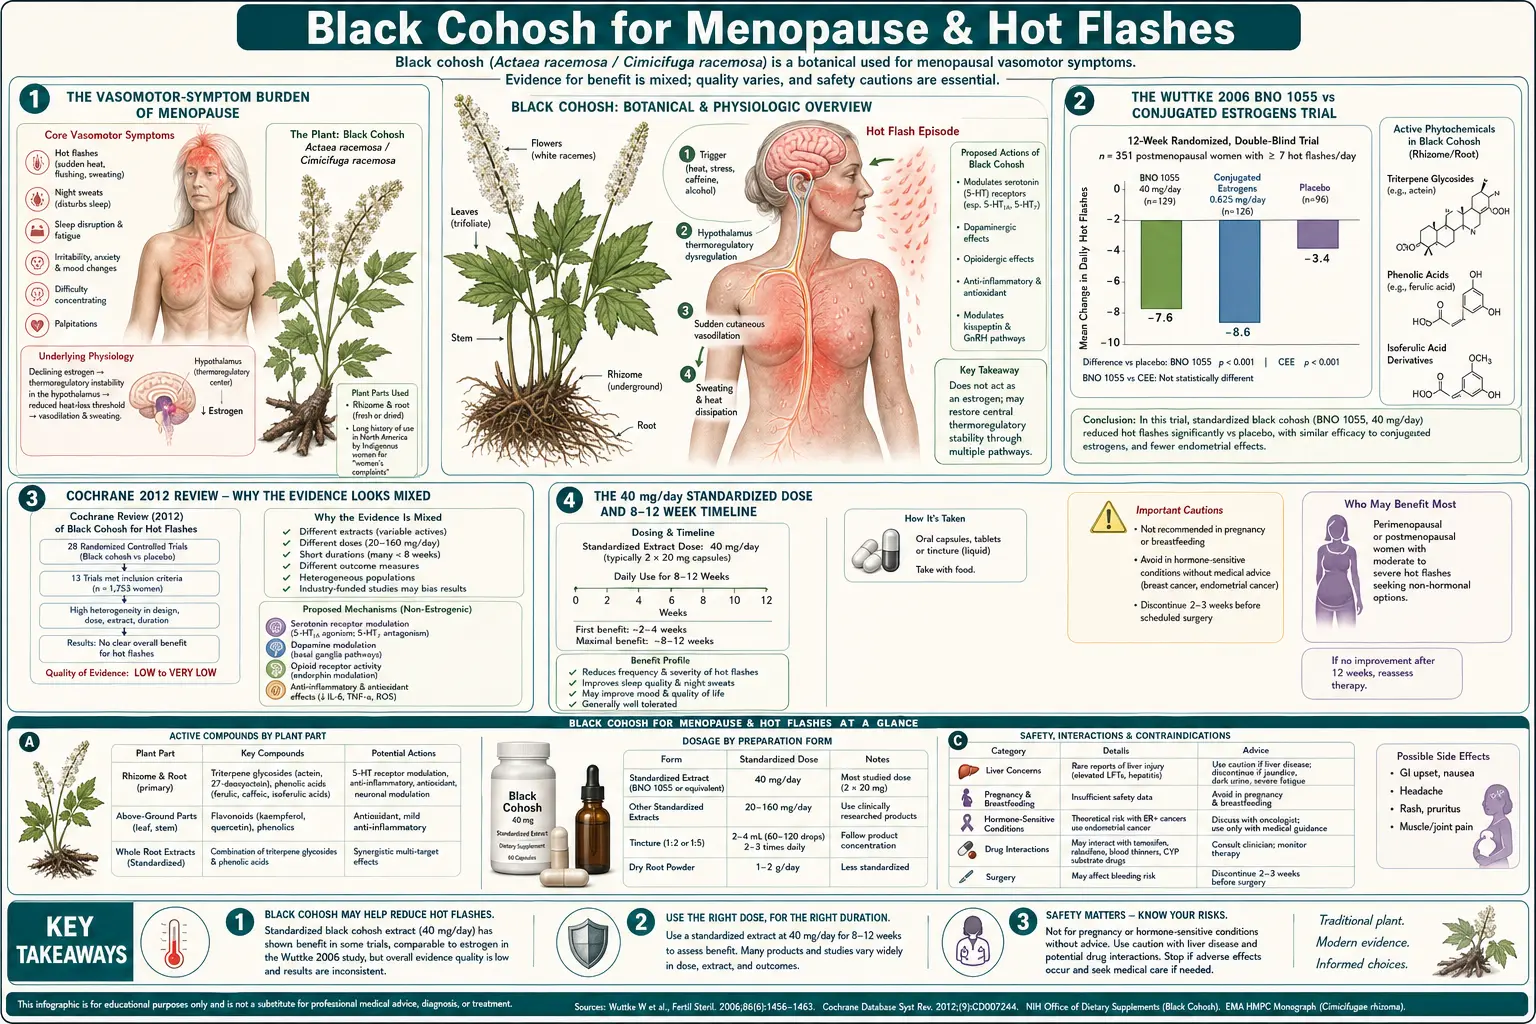
Vasomotor symptoms — hot flashes and night sweats — affect approximately 75% of perimenopausal and postmenopausal women in Western populations and, in the long-running Study of Women's Health Across the Nation (SWAN), persisted a median of 7.4 years. For women who cannot or choose not to use systemic hormone therapy, Black Cohosh is the most-studied herbal alternative. The pivotal Wuttke trial (published in 2003, with a fuller report in 2006) found an ethanolic black cohosh extract as effective as 0.6 mg/day conjugated estrogens, and better than placebo, on the Menopause Rating Scale over 12 weeks, without the thickening of the womb lining seen with estrogen. The Cochrane 2012 review of 16 trials found no significant difference from placebo in hot flushes and concluded that there is insufficient evidence to support black cohosh for menopausal symptoms; a 2013 re-analysis by other researchers disputes that reading. The most-studied dose is 40 mg/day of standardized extract in one or two doses; benefit is described as taking 4 to 8 weeks to develop, and 12 weeks is the typical timepoint at which trials assess efficacy.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone (FSH) climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →
Table of Contents
- The Vasomotor-Symptom Burden of Menopause
- The Wuttke Trial — Ethanolic Black Cohosh Extract vs Conjugated Estrogens
- Cochrane 2012 Review — Why the Evidence Looks Mixed
- The 40 mg/day Standardized Dose and 8–12 Week Timeline
- Extract Standardization — Why the Extract Type Matters
- Comparison to Hormone Replacement Therapy — Where Black Cohosh Is Used Instead
- Women with Breast-Cancer History
- Combination Protocols (Black Cohosh + St. John's Wort, SERMs)
- Non-Responders — Options Described After Black Cohosh
- Safety, Monitoring, and Discontinuation
- Key Research Papers
- Connections
- Featured Videos
The Vasomotor-Symptom Burden of Menopause
Hot flashes are not "just" an annoyance. The Study of Women's Health Across the Nation (SWAN), a multi-ethnic longitudinal cohort begun in 1994, has produced the most authoritative natural-history data we have. SWAN's 2015 duration analysis followed 1,449 women with frequent vasomotor symptoms: the median total duration was 7.4 years; symptoms persisted a median 4.5 years after the final menstrual period; women whose symptoms began while they were still premenopausal or early perimenopausal had the longest duration (median more than 11.8 years); and African American women reported the longest duration of any racial or ethnic group (median 10.1 years). SWAN research also shows that women with severe symptoms have measurable disruptions in sleep, mood, cognitive function, work productivity, and cardiovascular risk markers.
The clinical impact: severe vasomotor symptoms triple the risk of clinically significant insomnia, double the rate of depressive symptoms during the perimenopausal window, and contribute to a measurable increase in systolic blood pressure, fasting glucose, and adverse cardiovascular events over the symptomatic years. This is not a "soft" indication — it is a major source of morbidity for the half of the adult population that lives through menopause.
Systemic estrogen therapy (transdermal estradiol or oral conjugated estrogens) reduces vasomotor symptoms by approximately 75–90% in randomized trials and remains the most effective therapy. For women who cannot use hormone therapy — due to personal or family breast-cancer history, prior thromboembolic disease, active liver disease, or simply patient preference — the non-hormonal options are selective serotonin reuptake inhibitors (paroxetine 7.5 mg/day is U.S. Food and Drug Administration-approved for vasomotor symptoms), serotonin-norepinephrine reuptake inhibitors (venlafaxine 75 mg/day), gabapentin 300–900 mg/day, clonidine, and herbal therapies. Among the herbal options, Black Cohosh has by far the deepest clinical-trial evidence base.
A newer drug class works in the brain's temperature-control centre. In May 2023 the U.S. Food and Drug Administration approved fezolinetant, a 45 mg once-daily pill and the first neurokinin 3 receptor antagonist approved for moderate to severe hot flashes from menopause; it is not a hormone, and it targets the nerve activity that causes hot flashes. The 2023 nonhormone therapy position statement of the North American Menopause Society (NAMS) rates cognitive behavioural therapy, clinical hypnosis, selective serotonin and serotonin-norepinephrine reuptake inhibitors, gabapentin and fezolinetant as recommended (Level I), and lists clonidine and “supplements/herbal remedies” (Levels I–II) as not recommended. See Non-Hormonal Options: SSRIs, Gabapentin and Fezolinetant.
The Wuttke Trial — Ethanolic Black Cohosh Extract vs Conjugated Estrogens
The most influential single clinical trial of Black Cohosh for vasomotor symptoms was conducted by Wolfgang Wuttke and colleagues at the University of Göttingen, first published in Maturitas in 2003, with further reports of the same trial in 2006 (the Cochrane review groups them as one study). The trial was a three-arm randomized, double-blind, placebo-controlled comparison:
- Arm 1: An ethanolic Black Cohosh extract, 40 mg/day (corresponding to 40 mg dried rhizome equivalent)
- Arm 2: Conjugated equine estrogens 0.6 mg/day (the low-dose conjugated equine estrogen formulation that became standard after the Women's Health Initiative results scaled back high-dose use)
- Arm 3: Matched placebo
62 postmenopausal women with menopausal symptoms were randomized for 12 weeks of treatment, with the Menopause Rating Scale (MRS) as the primary endpoint along with bone-formation markers (serum osteocalcin, bone-specific alkaline phosphatase) and bone-resorption markers (urinary CrossLaps). Key findings:
- MRS reduction: Black Cohosh arm reduced MRS by an average of 50%; conjugated estrogens arm reduced MRS by an average of 47%; placebo arm by 22%. The difference between active treatments and placebo was statistically significant for both; the difference between Black Cohosh and estrogens was not significant (equivalence).
- Hot-flash frequency: reduced from a baseline of 4.9 to 1.2 per day in the Black Cohosh arm and 4.7 to 1.3 in the estrogen arm; placebo reduced from 4.8 to 3.1.
- Bone markers: Both Black Cohosh and conjugated estrogens decreased the bone-resorption marker CrossLaps and increased the bone-formation marker osteocalcin, suggesting a positive net effect on bone remodeling for both treatments. Placebo showed no change.
- Endometrial thickness: Conjugated estrogens caused statistically significant endometrial thickening on transvaginal ultrasound at 12 weeks. Black Cohosh did NOT cause endometrial thickening — this is the strongest single piece of clinical evidence that Black Cohosh is not acting as an estrogen.
- Side effects: Both active arms had a low adverse-event rate; the only between-group difference was that the conjugated-estrogens arm had more breast tenderness and a small but real signal for breakthrough vaginal bleeding.
The 2003 report concluded that the extract was “equipotent” to 0.6 mg/day conjugated estrogens and superior to placebo for menopausal complaints, had no effect on endometrial thickness (which estrogen significantly increased), and had beneficial effects on bone metabolism in blood tests. It remains the strongest single piece of evidence for comparable effect to low-dose conjugated estrogens at 12 weeks. Critics have pointed out the small sample size (n=62) and the relatively short follow-up; defenders have pointed to the consistency with other Wuttke-group results and the mechanistic plausibility from the same group's receptor-binding studies. See the related Hormonal Balance deep-dive for the mechanism work.
Cochrane 2012 Review — Why the Evidence Looks Mixed
The Cochrane Collaboration published a systematic review and meta-analysis of Black Cohosh for menopausal symptoms in September 2012 (Leach & Moore, Cochrane Database CD007244). The review included 16 randomized controlled trials enrolling 2,027 perimenopausal and postmenopausal women, with treatment durations ranging from 8 to 52 weeks.
The headline conclusion was that "there is currently insufficient evidence to support the use of black cohosh for menopausal symptoms." The trials used a median dose of 40 mg/day for a mean of 23 weeks. Against placebo, the pooled mean difference in hot flushes was 0.07 flushes per day (95% confidence interval -0.43 to 0.56; 3 trials, 393 women) — no significant difference — and menopausal symptom scores also did not differ (4 trials). Hormone therapy reduced menopausal symptom scores more than black cohosh (standardized mean difference 0.32; 5 trials, 468 women). This conclusion has been widely cited in subsequent reviews and clinical guidelines as evidence against Black Cohosh efficacy.
The review reported moderate between-study heterogeneity for hot flushes (I-squared = 47%), low heterogeneity for symptom scores (I-squared = 21%) and substantial heterogeneity (I-squared = 69%) for the hormone-therapy comparison, and said the findings should be interpreted with caution. Of its 16 trials, six used an ethanolic extract, six an isopropanolic extract, and four did not state the solvent; its planned subgroup analyses were by dose and treatment duration, not by extract type.
Researchers on the other side of the debate dispute the conclusion. A 2013 commentary (Beer and colleagues) re-analysed what its authors judged to be all appropriate placebo-controlled trials and reported a standardized mean difference of 0.385 in favour of black cohosh (p < 0.0001). Individual trials also show how results depend on who is studied: in a Swiss trial of 122 women with at least 3 hot flashes a day (Frei-Kleiner 2005), a dried ethanolic extract was no better than placebo overall over 12 weeks, but in the subgroup with at least moderate symptoms (Kupperman Index of 20 or more) the index fell 47% with black cohosh versus 21% with placebo.
The interpretive question is whether the average effect across all preparations is the relevant clinical answer, or whether the effect of a single well-studied preparation is the relevant answer for women considering using it. The German Commission E monograph and the European Medicines Agency herbal monograph both accept Black Cohosh as efficacious based largely on European trials of standardized extracts, while the U.S. National Institutes of Health (NIH) Office of Dietary Supplements takes a more cautious "evidence is mixed" position consistent with the Cochrane meta-analysis pooling all preparations together.
The large negative U.S. trial most often cited against efficacy is the Herbal Alternatives for Menopause (HALT) trial of 351 women aged 45 to 55, reported by Newton 2006 (Annals of Internal Medicine, symptom results) and Reed 2008 (Menopause, vaginal, endometrial and hormone results) — two papers from one trial. Black cohosh 160 mg/day did not differ from placebo in symptoms per day, symptom intensity or the Wiklund vasomotor score at 3, 6 or 12 months, while hormone therapy reduced vasomotor symptoms by 4.06 per day compared with placebo; Reed found no effect of any herbal regimen on the vaginal lining, the endometrium or reproductive hormones. The Cochrane review classes the HALT extract as ethanolic, and HALT used four times the 40 mg/day dose of most European trials.
The 40 mg/day Standardized Dose and 8–12 Week Timeline
The canonical evidence-based dose of Black Cohosh, derived from the Wuttke trials and the German Commission E monograph, is 40 mg/day of standardized extract — the median dose across the trials in the 2012 Cochrane review — used for both the isopropanolic extract and the ethanolic extract of the Wuttke trials. This corresponds to a daily dose equivalent to 40 mg of dried rhizome, delivered as one tablet twice daily or two tablets once daily depending on the product's standardization. The 40 mg figure refers to the dried-herb equivalent, not the mass of pure extract powder — this is a frequent source of consumer confusion.
Some clinicians, particularly in the U.S. integrative-medicine community, use higher doses (80–160 mg/day). The HALT trial (reported by Newton and by Reed) used 160 mg/day. There is no clear dose-response evidence that higher doses produce greater efficacy — if anything, the negative high-dose U.S. trial suggests that more is not better, possibly because of differences between preparations. 40 mg/day remains the most-studied amount.
Timeline expectations:
- Week 1–2: Most patients notice no change. Some report mild gastrointestinal (GI) upset that typically resolves with food. A small fraction notice mild headache.
- Week 3–4: Approximately 30–40% of responders begin to notice reduction in hot-flash intensity or frequency. The reduction is typically partial — flashes are shorter, less intense, or less frequent rather than disappearing entirely.
- Week 6–8: Most of the eventual benefit is established. This is the timepoint at which a fair assessment of efficacy can be made. Patients who have noticed no improvement at all by week 8 are unlikely to respond.
- Week 12: The standard trial-endpoint timepoint. By this point, responders typically have 40–60% reduction in hot-flash frequency and intensity.
- Beyond 12 weeks: Most responders experience sustained benefit on continued therapy. The longest published continuous-use trials extend to 12 months with maintained efficacy and no signal of tachyphylaxis.
Black Cohosh is not a "take and feel better the next day" remedy — the response timeline is comparable to that of a selective serotonin reuptake inhibitor for depression, with weeks of consistent use before efficacy is assessed in trials. Stopping at week 2 or 3 because "it's not working" is described as one of the most common reasons for apparent treatment failure.
Extract Standardization — Why the Extract Type Matters
"Black Cohosh" on a U.S. supplement label can refer to several pharmacologically distinct preparations:
- Iso-propanolic extract — the original German pharmaceutical-grade preparation, extracted from authenticated Actaea racemosa rhizome with iso-propanol (40% v/v). Standardized to a defined triterpene-glycoside content. It was used in six of the 16 trials in the 2012 Cochrane review, in the Uebelhack St. John's Wort combination trial, and in the German breast-cancer cohort study described below.
- Ethanolic extract — alcoholic tinctures and dried extracts using ethanol as the solvent. Pharmacologically similar to iso-propanolic but with subtle differences in the extracted triterpene profile. The Cochrane review classes the extracts of the Wuttke trial, the Swiss Frei-Kleiner trial and the U.S. HALT trial as ethanolic; the Wuttke extract is a different product from the isopropanolic one.
- CO2 supercritical extract — uses pressurized carbon dioxide as the solvent. Produces a different phytochemical profile, with lower polar triterpene-glycoside content.
- Methanolic / aqueous extract — less commonly marketed; phytochemically quite different.
- Bulk powdered rhizome — ground dried herb, no extraction. Cheap but inconsistent and the most likely to be adulterated with related Asian Cimicifuga species.
HPLC and DNA-barcoding analyses of U.S. retail Black Cohosh products have repeatedly documented adulteration rates of 10–30% with related but distinct species — primarily Cimicifuga foetida, C. heracleifolia, and C. dahurica, which are cheaper and more widely cultivated in China. These species have different triterpene profiles and unknown efficacy and safety profiles in humans. Batch-level Certificates of Analysis with HPLC (high-performance liquid chromatography) fingerprints and DNA authentication, which some manufacturers publish, are the available checks against adulteration.
Comparison to Hormone Replacement Therapy — Where Black Cohosh Is Used Instead
Systemic estrogen therapy is more effective than Black Cohosh for vasomotor-symptom relief in head-to-head comparisons (the Wuttke trial showed comparable effect at the doses used, and the 2012 Cochrane review found hormone therapy reduced menopausal symptom scores more than black cohosh, but most non-equivalence studies have shown hormone replacement therapy (HRT) outperforms Black Cohosh on hot-flash frequency by approximately 15–25%). Hormone replacement therapy also produces additional benefits that Black Cohosh does not — reliable resolution of genitourinary syndrome of menopause (vaginal dryness, dyspareunia, urinary urgency), measurable preservation of bone density (Black Cohosh shows a smaller signal here, see the Bone Health deep-dive), and possible cardiovascular and cognitive benefits when initiated within the "window of opportunity" of approximately the first 10 years after menopause.
The case for Black Cohosh over hormone replacement therapy is built on situations where hormone replacement therapy is contraindicated, relatively contraindicated, or actively undesired by the patient:
- Personal history of estrogen-receptor-positive breast cancer — absolute contraindication to systemic estrogen. The non-estrogenic mechanism of Black Cohosh (see the Hormonal Balance deep-dive) makes it the most-studied herbal option for breast-cancer survivors with disabling vasomotor symptoms, though the evidence base in this specific population is still limited.
- Strong family history of breast or ovarian cancer — relative contraindication; many patients in this category prefer non-hormonal options regardless of formal guidelines.
- History of venous thromboembolism, pulmonary embolism, or stroke — oral conjugated estrogens carry a 2- to 3-fold elevated thrombotic risk. Transdermal estradiol is safer in this regard but still relatively contraindicated.
- Active liver disease — absolute contraindication to oral estrogens. Also a contraindication to Black Cohosh because of the rare idiosyncratic hepatotoxicity signal.
- Patient preference — many women have strong preferences for non-hormonal therapy for reasons that may include risk perception (often shaped by the 2002 Women's Health Initiative results, which were specific to oral conjugated estrogens plus medroxyprogesterone acetate in older women), religious or philosophical beliefs about pharmaceutical hormones, or prior negative experience with hormone replacement therapy.
- Mild-to-moderate vasomotor symptoms that don't require the full effect size of hormone replacement therapy — many women have symptoms that interfere with sleep and quality of life but don't rise to a level that demands the most effective therapy. Black Cohosh is used as a less-intensive option.
Women with Breast-Cancer History
Breast-cancer survivors with disabling vasomotor symptoms (often induced or worsened by tamoxifen or aromatase-inhibitor therapy) face a specific clinical dilemma: systemic estrogen is absolutely contraindicated, and the antidepressants commonly used as alternatives can interact with tamoxifen metabolism (paroxetine and fluoxetine are strong cytochrome P450 2D6 (CYP2D6) inhibitors and reduce conversion of tamoxifen to its active metabolite endoxifen — this interaction is clinically significant). Venlafaxine and gabapentin avoid the cytochrome P450 2D6 issue but have their own side-effect burden.
The clinical-trial evidence for Black Cohosh in breast-cancer survivors is limited but encouraging. The Hernández Muñoz 2003 trial enrolled 136 young premenopausal breast-cancer survivors aged 35 to 52 with hot flushes from tamoxifen. It was open-label, with no placebo: women were randomly assigned to tamoxifen alone (46) or tamoxifen plus the ethanolic extract of the Wuttke trials (90) for 12 months. Severe hot flushes were reported by 24.4% of the black cohosh group versus 73.9% of the tamoxifen-alone group (P < 0.01), and almost half of the black cohosh group were free of hot flushes. The Pockaj 2006 NCCTG (North Central Cancer Treatment Group) double-blind crossover trial of 132 women (black cohosh 20 mg twice daily, two 4-week periods) found hot-flash frequency fell 17% on black cohosh and 26% on placebo (P = .36); the authors reported no evidence that black cohosh reduced hot flashes more than placebo.
The mechanistic case is strong (Black Cohosh does not bind estrogen receptors, does not stimulate MCF-7 breast-cancer cell proliferation, does not produce uterotrophic effects, and a 2007 Henneicke-von Zepelin retrospective cohort study from a German medical-records database — 18,861 breast-cancer patients, 1,102 of whom had received the isopropanolic extract, followed a mean 3.6 years — found the extract was not associated with more recurrences, with a recurrence hazard ratio of 0.83, 95% confidence interval 0.69 to 0.99). The German Commission E and European Medicines Agency monographs accept short-term Black Cohosh use for menopausal complaints. The 2023 North American Menopause Society (NAMS) nonhormone therapy position statement, by contrast, lists “supplements/herbal remedies” (Levels I–II) as not recommended for hot flashes. For a breast-cancer survivor on tamoxifen with disabling hot flashes who is not getting relief from venlafaxine or gabapentin, a 12-week trial of 40 mg/day standardized iso-propanolic Black Cohosh extract is described as reasonable after baseline liver-function testing and with oncologist concurrence.
Among drugs, a newer option has been tested in this group. Elinzanetant, a hormone-free pill that targets the source of hot flashes in the brain, reduced the number and severity of hot flashes in four randomized trials (OASIS 1 to 4), including OASIS-4 in women with hot flashes caused by endocrine therapy after initial breast-cancer treatment; the most common side effects were headache, fatigue and sleepiness (2026 plain-language review of the OASIS trials). See Elinzanetant.
The liver-injury warnings below carry extra weight for people who are also on chemotherapy regimens that can harm the liver.
Combination Protocols (Black Cohosh + St. John's Wort, SERMs)
Several combination products and protocols have been studied:
- Black Cohosh + St. John's Wort — the Uebelhack 2006 trial in 301 women with menopausal symptoms and significant mood symptoms tested a fixed combination of isopropanolic black cohosh extract and ethanolic St. John's Wort extract against placebo for 16 weeks. The Menopause Rating Scale score fell 50% with the combination versus 19.6% with placebo, and the Hamilton Depression Rating Scale score fell 41.8% versus 12.7% (both P < .001), with no relevant difference in adverse events. The trial had no black-cohosh-alone arm. The interaction concern is that St. John's Wort is a potent cytochrome P450 3A4 (CYP3A4) inducer — drugs affected include tamoxifen, warfarin, oral contraceptives, immunosuppressants, anti-HIV drugs, and many anticonvulsants. See the Mood & Sleep deep-dive for more on the perimenopausal-mood applications.
- Black Cohosh + soy isoflavones — a logical combination since the two would act through different mechanisms (Black Cohosh non-estrogenic, soy mildly phytoestrogenic). Limited trial evidence; the few studies have not shown a clearly additive effect, and soy carries its own complexity for breast-cancer survivors.
- Black Cohosh + venlafaxine or paroxetine — not formally studied in randomized trials but commonly used clinically in patients who respond partially to either alone. No known pharmacokinetic interaction; described as an empirical combination.
- Black Cohosh as bridge to or off hormone replacement therapy — some clinicians use Black Cohosh during hormone replacement therapy tapering to soften the rebound vasomotor symptoms that commonly occur. Limited evidence base but mechanistically reasonable.
Non-Responders — Options Described After Black Cohosh
When a 12-week course of 40 mg/day standardized Black Cohosh extract brings no meaningful reduction in hot-flash frequency or intensity, the options described, in escalating order, are:
- Extract quality and adherence. A surprising fraction of "non-responders" turn out to have been taking an unstandardized or adulterated preparation or have been inconsistent with dosing. Another 8 weeks of an authenticated, standardized extract taken consistently twice daily is the step described before calling it non-response.
- Higher dose (80 mg/day). Evidence for added benefit is weak but the safety profile at this dose is well-established. 8–12 week trial.
- Non-hormonal prescription drugs. Paroxetine 7.5 mg/day (U.S. Food and Drug Administration-approved for vasomotor symptoms), venlafaxine 75 mg/day, gabapentin 300–900 mg/day at bedtime, and fezolinetant 45 mg once daily (U.S. Food and Drug Administration-approved in 2023). Paroxetine reduces tamoxifen's conversion to its active form (see the breast-cancer section above).
- Hormone therapy. For women without contraindications, low-dose transdermal estradiol (0.025–0.05 mg/day patch) is by far the most effective option and has the most favorable safety profile of all hormone replacement therapy formulations.
- Cognitive behavioral therapy for hot flashes (CBT-HF). A structured psychological intervention developed by Myra Hunter and colleagues that has shown 25–40% reduction in hot-flash bother (not necessarily frequency) in randomized trials. Especially useful for women who continue to have residual symptom impact despite partial response to other therapies.
- Lifestyle interventions: weight loss in overweight women (each 5 kg loss reduces hot-flash frequency measurably), reduction of alcohol and spicy foods (common individual triggers), bedroom temperature optimization, paced breathing.
Safety, Monitoring, and Discontinuation
The dominant safety concern is the rare idiosyncratic hepatotoxicity discussed in detail on the Benefits hub Hepatotoxicity section. The monitoring schedule commonly described:
- Baseline alanine aminotransferase (ALT), aspartate aminotransferase (AST), alkaline phosphatase, total bilirubin before starting if any risk factor for liver disease is present (alcohol, statins, methotrexate, prior hepatitis, non-alcoholic steatohepatitis, NASH).
- Repeat liver function tests (LFTs) at 6 months for any user continuing beyond that timepoint.
- Annual LFTs for any user continuing >1 year.
- Warning signs of liver injury: jaundice (yellow skin or eyes), dark urine, pain in the right upper part of the belly (right upper quadrant), unusual fatigue, loss of appetite, or nausea. Hospitals treat these signs as urgent; stopping the product and same-day liver function tests are the standard response described.
Other safety considerations:
- Pregnancy and lactation: Contraindicated. Black Cohosh has uterotonic effects in vitro and has been used historically as a parturient to induce labor.
- Active liver disease: Absolute contraindication.
- Drug interactions: Limited evidence for clinically significant CYP-mediated interactions with Black Cohosh alone. Combination products with St. John's Wort carry the full set of St. John's Wort interactions (cytochrome P450 3A4 induction).
- Common minor side effects: Mild gastrointestinal upset (5–10% of users), headache (3–5%), rash (rare).
- Stopping after long-term use: No withdrawal syndrome. Vasomotor symptoms may return over 2–4 weeks after discontinuation if the underlying menopause physiology is still active.
Key Research Papers
- Wuttke W, Seidlová-Wuttke D, Gorkow C (2003). The Cimicifuga preparation BNO 1055 vs. conjugated estrogens in a double-blind placebo-controlled study: effects on menopause symptoms and bone markers. Maturitas 44 Suppl 1:S67-77. — PubMed PMID: 12609561
- Wuttke W, Rauš K, Gorkow C (2006). Efficacy and tolerability of the Black cohosh (Actaea racemosa) ethanolic extract BNO 1055 on climacteric complaints: a double-blind, placebo- and conjugated estrogens-controlled study. Maturitas 55 Suppl 1:S83-S91. — doi:10.1016/j.maturitas.2006.06.020
- Leach MJ, Moore V (2012). Black cohosh (Cimicifuga spp.) for menopausal symptoms. Cochrane Database of Systematic Reviews 9:CD007244. — PubMed PMID: 22972105
- Newton KM, Reed SD, LaCroix AZ, Grothaus LC, Ehrlich K, Guiltinan J (2006). Treatment of vasomotor symptoms of menopause with black cohosh, multibotanicals, soy, hormone therapy, or placebo: a randomized trial. Annals of Internal Medicine 145(12):869-79. — PubMed PMID: 17179056
- Frei-Kleiner S, Schaffner W, Rahlfs VW et al. (2005). Cimicifuga racemosa dried ethanolic extract in menopausal disorders: a double-blind placebo-controlled clinical trial. Maturitas 51(4):397-404. — PubMed PMID: 16039414
- Pockaj BA et al. (2006). Phase III double-blind, randomized, placebo-controlled crossover trial of black cohosh in the management of hot flashes: NCCTG Trial N01CC1. Journal of Clinical Oncology 24(18):2836-41. — PubMed PMID: 16782922
- Hernandez Munoz G, Pluchino S (2003). Cimicifuga racemosa for the treatment of hot flushes in women surviving breast cancer. Maturitas 44 Suppl 1:S59-65. — PubMed PMID: 12609560
- Uebelhack R et al. (2006). Black cohosh and St. John's wort for climacteric complaints: a randomized trial. Obstetrics & Gynecology 107(2 Pt 1):247-55. — PubMed PMID: 16449108
- Reed SD et al. (2008). Vaginal, endometrial, and reproductive hormone findings: randomized, placebo-controlled trial of black cohosh, multibotanical herbs, and dietary soy for vasomotor symptoms: the Herbal Alternatives for Menopause (HALT) Study. Menopause 15(1):51-8. — PubMed PMID: 18257142
- Henneicke-von Zepelin HH (2017). 60 years of Cimicifuga racemosa medicinal products: clinical research milestones, current study findings and current development. Wiener Medizinische Wochenschrift 167(7-8):147-159. — PubMed PMID: 28155126
- Beer AM, Osmers R, Schnitker J et al. (2013). Efficacy of black cohosh (Cimicifuga racemosa) medicines for treatment of menopausal symptoms — comments on major statements of the Cochrane Collaboration report 2012. Gynecological Endocrinology 29(12):1022-5. — PubMed PMID: 23992293
- Henneicke-von Zepelin HH, Meden H, Kostev K, Schröder-Bernhardi D, Stammwitz U, Becher H (2007). Isopropanolic black cohosh extract and recurrence-free survival after breast cancer. International Journal of Clinical Pharmacology and Therapeutics 45(3):143-54. — PubMed PMID: 17416109
- The North American Menopause Society (2023). The 2023 nonhormone therapy position statement of The North American Menopause Society. Menopause 30(6):573-590. — PubMed PMID: 37252752
- Avis NE, Crawford SL, Greendale G, et al.; Study of Women's Health Across the Nation (2015). Duration of menopausal vasomotor symptoms over the menopause transition. JAMA Internal Medicine 175(4):531-9. — PubMed PMID: 25686030
- Pinkerton JV, Nappi RE, Soares CN, et al. (2026). Elinzanetant for the treatment of menopausal hot flashes: a plain language review of the OASIS-1-4 clinical trial results. Women's Health (London) 22:17455057261462773. — PubMed PMID: 42447004
- U.S. Food and Drug Administration (2023). FDA approves novel drug to treat moderate to severe hot flashes caused by menopause. News release, May 12, 2023. — fda.gov news release
PubMed Topic Searches
Connections
- All Herbs
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Black Cohosh Overview
- Black Cohosh Benefits Hub
- Black Cohosh for Hormonal Balance
- Black Cohosh for Bone Health
- Black Cohosh for Mood & Sleep
- Menopause
- Perimenopause
- Perimenopause Symptom Tracker
- Maca
- Ashwagandha
- Chamomile
- Hormone Panel
- Anxiety
- Depression
- Stress Management
- History