Perimenopause: Symptom Tracker & Hormonal Testing
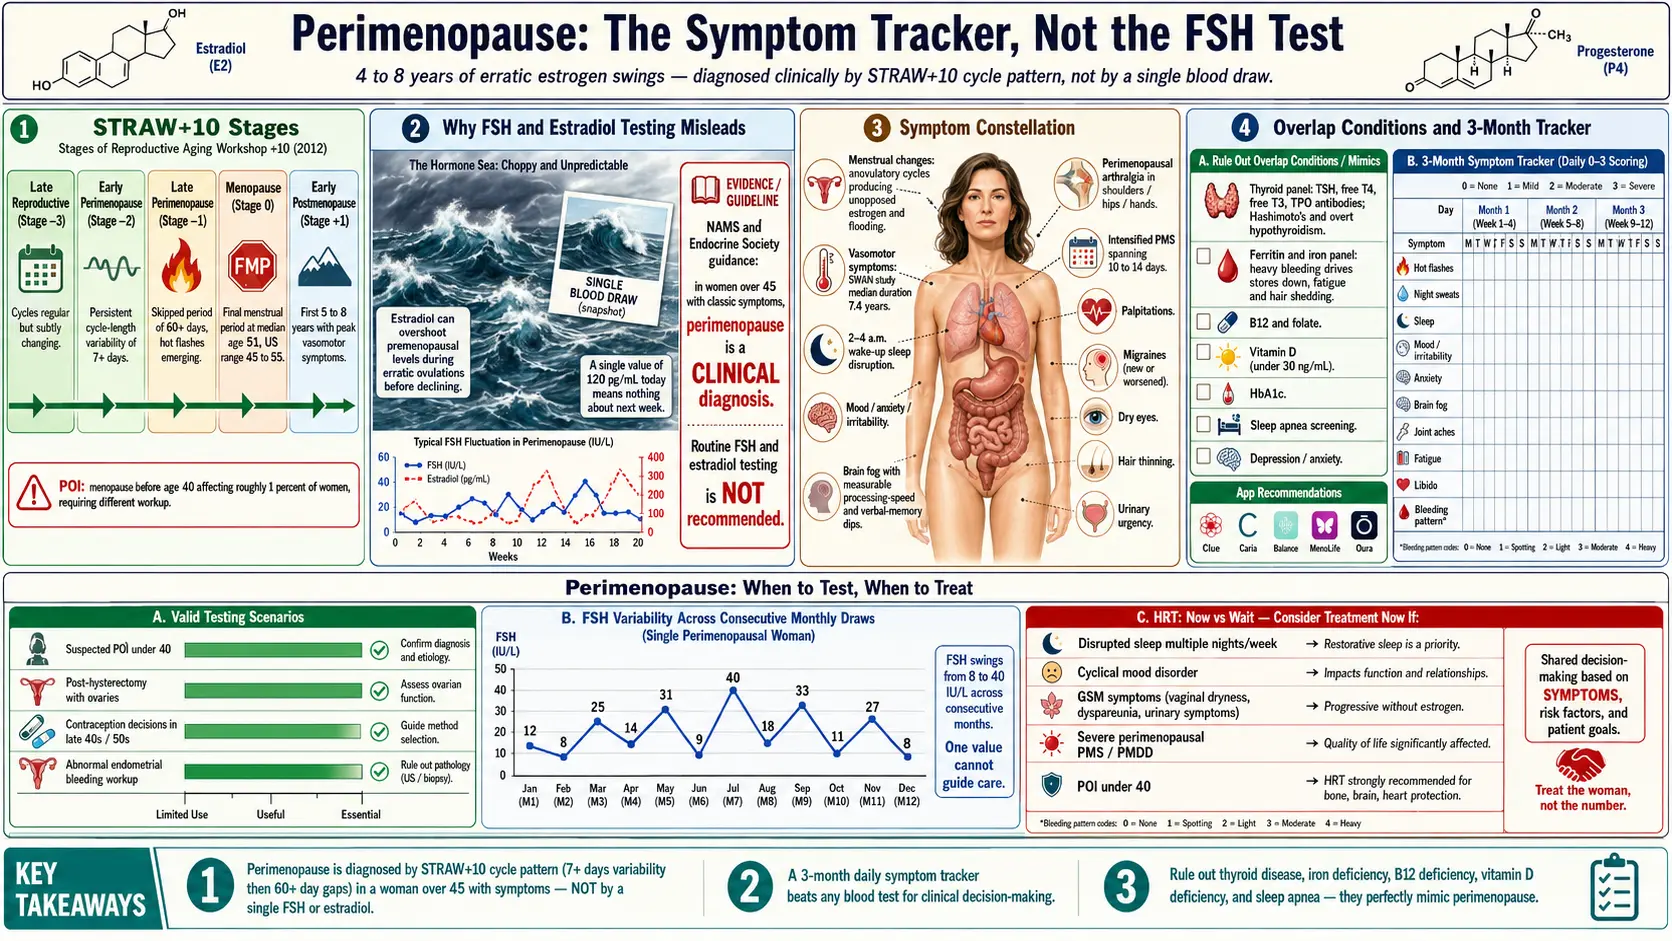
If you are in your 40s and something feels off — your periods are showing up early, late, heavy, light, or not at all; you are waking at 3 a.m. drenched in sweat; your previously reliable brain has started forgetting why you walked into the kitchen; and your PMS has turned into a two-week monster — you are very likely in perimenopause. And if you asked your doctor for a blood test to confirm it, they probably drew a follicle-stimulating hormone (FSH) and estradiol, got a result that said "normal, still premenopausal," and sent you home feeling crazy. You are not crazy. The test was simply the wrong tool for the question.
Perimenopause is the transitional years before your final menstrual period — typically beginning in the mid-40s and lasting on average four to eight years, though it can span anywhere from two to fourteen. During this window, your ovaries do not gracefully ramp down; they sputter. Estrogen levels swing wildly from week to week, sometimes hour to hour. That swinging — not a simple deficiency — is what produces the symptoms. And it is exactly why a single blood draw on a single morning is almost useless for diagnosis in a woman over 45 with a uterus and ovaries.
This guide walks through what perimenopause actually looks like, why the standard hormone panel misleads patients and clinicians alike, when testing does help, the overlap conditions that masquerade as perimenopause (thyroid, iron, B12, vitamin D), and a practical three-month symptom-tracking template you can start today — the single most useful diagnostic tool available to you.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →Table of Contents
- Stages of Perimenopause (STRAW+10)
- The Symptom Constellation
- Why Follicle-Stimulating Hormone and Estradiol Testing Misleads
- When Testing Actually Helps
- Overlap Conditions That Mimic Perimenopause
- A Practical 3-Month Symptom Tracker
- Cycle- and Symptom-Tracking Apps
- Starting Hormone Replacement Therapy Now vs. Waiting
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
Stages of Perimenopause (STRAW+10)
The Stages of Reproductive Aging Workshop + 10 (STRAW+10) criteria, updated in 2012, are the international gold standard for describing where you are in the menopause transition. STRAW+10 uses menstrual cycle patterns as the primary marker and treats hormone levels as secondary — precisely because cycles tell the truth more reliably than a single blood test. The key stages:
- Late Reproductive (Stage -3): Cycles still regular but subtly changing — perhaps a day or two shorter, slightly heavier, or with a harsher PMS week. Follicle-stimulating hormone is usually still normal but may be rising on cycle day 2–5.
- Early Perimenopause (Stage -2): Persistent cycle-length variability of 7 days or more compared with your personal baseline. Your 28-day cycle becomes a 24-day cycle one month, a 35-day cycle the next. This is often the first clear signal.
- Late Perimenopause (Stage -1): A skipped period of 60 days or more. You may go three months without bleeding, then have a heavy flood. Hot flashes and night sweats become more common here. This stage typically lasts one to three years.
- Menopause (Stage 0): The final menstrual period, defined only in retrospect after 12 consecutive months of no bleeding. Average age in the U.S. is 51; the normal range is roughly 45 to 55.
- Early Postmenopause (Stage +1): The first 5–8 years after your final period. Vasomotor symptoms often peak here before gradually easing.
Primary Ovarian Insufficiency (POI) is a separate diagnosis: menopause before age 40. The 2024 international POI guideline reports new data putting it at about 3.5% of women — more common than once thought — and it is diagnosed with hormonal testing (see below).
The Symptom Constellation
Perimenopause is not just hot flashes. It is a system-wide recalibration that touches nearly every organ that has estrogen receptors — which is nearly every organ. The typical constellation:
- Menstrual changes. Shorter cycles first, then longer and skipped cycles. Heavy bleeding, clotting, and flooding are common because anovulatory cycles produce unopposed estrogen that thickens the endometrium.
- Vasomotor symptoms (VMS). Hot flashes and night sweats. Roughly 75–80% of women experience them; for about a third they are severe. Median duration is 7.4 years according to the SWAN study — far longer than the "a year or two" many women are told to expect. In SWAN (1,449 women with frequent hot flashes), they lasted a median 4.5 years after the final period. Women whose frequent hot flashes began while they were still premenopausal or in early perimenopause had them longest (median more than 11.8 years in total, and 9.4 years after the final period); African American women reported the longest total duration (median 10.1 years). Greater stress, symptom sensitivity, depressive symptoms and anxiety when hot flashes began were linked to longer duration.
- Sleep disruption. Classic pattern: falling asleep fine, waking at 2–4 a.m. wide awake, sometimes with a sweat. Even without overt night sweats, estrogen fluctuations destabilize sleep architecture.
- Mood changes. New or worsened anxiety, irritability, low mood, and rage episodes. Women with a history of PMS, postpartum depression, or premenstrual dysphoric disorder (PMDD) are at higher risk. This is biology, not weakness.
- Brain fog. Word-finding trouble, slower recall, losing your train of thought mid-sentence. Objective cognitive testing in SWAN confirmed measurable dips in processing speed and verbal memory that typically recover post-menopause.
- Joint and muscle aches. The "perimenopausal arthralgia" that shows up in shoulders, hips, hands, and knees without any injury. Estrogen modulates cartilage and tendon metabolism; its fluctuation produces genuine musculoskeletal pain.
- Intensified PMS. Many women describe their old two-day PMS expanding into a 10–14-day luteal misery. This is because estrogen peaks are higher and progesterone is often lower — a wider hormonal swing each cycle.
- Other: heart palpitations, migraines (new or worsened), dry eyes, dry mouth, new skin itchiness, hair thinning, urinary urgency, and a decline in vaginal lubrication (the early edge of genitourinary syndrome of menopause).
Why Follicle-Stimulating Hormone and Estradiol Testing Misleads
Here is the core problem. A blood test captures one moment. Perimenopause is defined by variability over time. It is like trying to diagnose a choppy sea by taking a single photograph of one wave.
Follicle-stimulating hormone (FSH) rises when the ovary stops responding to normal pituitary signaling. Many references cite a threshold of follicle-stimulating hormone > 25 international units (IU)/L on cycle day 2–5 as suggestive of the menopause transition. But in perimenopause, follicle-stimulating hormone can be 8 one week and 40 the next. A woman with severe hot flashes and four months of missed periods can have a "premenopausal" follicle-stimulating hormone of 12 on the day she gets tested, and a woman with regular cycles can have an "elevated" follicle-stimulating hormone of 30. Neither result tells you what is happening over the course of a month, much less a year.
Estradiol (E2) is even worse as a snapshot. In perimenopause, estradiol often overshoots premenopausal levels during erratic ovulations before eventually declining. A single estradiol of 120 pg/mL does not mean "you are fine." It may mean "you caught the crest of the wave." Two weeks later the same woman might measure 25 pg/mL with a hot flash.
The North American Menopause Society (NAMS) and the Endocrine Society are both explicit: in a woman over 45 with classic symptoms and cycle changes, the diagnosis of perimenopause is clinical. Routine follicle-stimulating hormone and estradiol testing is not recommended and frequently causes harm by falsely reassuring women that "nothing is wrong."
Anti-Müllerian hormone (AMH) is sometimes proposed as a better marker because it declines more smoothly. AMH can predict the approximate time until final menstrual period in research cohorts, but it still does not change day-to-day management for a symptomatic woman. It is useful for fertility planning, not for perimenopause diagnosis.
When Testing Actually Helps
Hormonal testing is not worthless — it is just narrow. The specific situations where it earns its keep:
- Suspected Primary Ovarian Insufficiency (POI), under age 40. Amenorrhea or markedly irregular cycles plus menopausal symptoms in a woman under 40 is a different clinical situation with long-term cardiovascular, bone, and neurologic implications. Under the 2024 international POI guideline (from ESHRE, the American Society for Reproductive Medicine, CRE-WHiRL and the International Menopause Society; 145 recommendations), one follicle-stimulating hormone measurement > 25 international units/L, along with low estradiol, supports POI; anti-Müllerian hormone (AMH) testing or a repeat follicle-stimulating hormone may be used when the diagnosis is uncertain. The earlier 2015 guideline asked for two measurements at least one month apart. This diagnosis changes treatment: the guideline notes that hormone therapy can lessen some of POI's effects on bone, heart and brain health, and hormone replacement therapy (HRT) is generally continued at least until the average age of natural menopause.
- After hysterectomy (with ovaries intact). Without periods to track, cycle-based diagnosis is impossible. Serial follicle-stimulating hormone and symptom review can help time the transition and hormone replacement therapy decisions.
- Contraception decisions in the late 40s and early 50s. A woman who has been on a hormonal contraceptive for years and wants to stop may use follicle-stimulating hormone (measured off-pill for 4–6 weeks) to estimate whether pregnancy is still possible. Two follicle-stimulating hormone values > 30 international units/L a few weeks apart in a woman over 50 who has been off hormonal contraception suggest contraception can be discontinued — though guidelines differ.
- Endometrial bleeding that is abnormal. Here testing is not for hormones but for cause: endometrial biopsy, pelvic ultrasound, and sometimes thyroid panel. Heavy, prolonged, intermenstrual, or postcoital bleeding deserves evaluation, not dismissal as "just perimenopause."
- Atypical presentations. Young age, rapid progression, or symptoms that do not fit — testing helps narrow the differential.
Overlap Conditions That Mimic Perimenopause
One reason perimenopause is under-diagnosed and over-diagnosed is that several common conditions produce an almost identical symptom picture. A good workup rules these out before assuming every symptom is hormonal — and before assuming nothing is hormonal. The tests commonly used:
- Thyroid panel (thyroid-stimulating hormone (TSH), free T4, and ideally free T3 + TPO antibodies). Hypothyroidism and Hashimoto's cause fatigue, weight gain, cold intolerance, depression, hair loss, menstrual irregularity, and brain fog. Hyperthyroidism causes heat intolerance, palpitations, anxiety, sleep disruption, and weight loss. Both are common in women in their 40s. See Thyroid Disorders.
- Ferritin and a full iron panel. Heavy perimenopausal bleeding drives iron stores down. Low ferritin (below 30–50 ng/mL in most lab frameworks) produces fatigue, brain fog, hair shedding, restless legs, and exercise intolerance — all indistinguishable from perimenopause at first glance.
- Vitamin B12 and folate. B12 deficiency causes fatigue, paresthesias, memory complaints, mood changes, and palpitations. Long-term metformin use, proton pump inhibitor (PPI) use, vegan/vegetarian diets, and atrophic gastritis raise the risk.
- Vitamin D (25-hydroxy). Practitioners link low vitamin D to joint aches, low mood, fatigue, and sleep disruption. The Institute of Medicine's 2011 report treats a blood level of at least 20 ng/mL (50 nmol/L) as meeting the needs of at least 97.5% of people (Recommended Dietary Allowance 600 IU a day to age 70, 800 IU after 70), and found the evidence for effects beyond bone — cancer, heart disease, diabetes, autoimmune disease — inconsistent. Some practitioners use 30 ng/mL as their own cut-off.
- Fasting glucose and hemoglobin A1c (HbA1c). Insulin resistance and early type 2 diabetes produce fatigue, weight shifts, and brain fog.
- Sleep apnea screening. Women are chronically under-diagnosed. Midlife weight gain plus estrogen decline increases the risk; classic "hot flash waking" can actually be an apnea arousal. See Insomnia.
- Depression and anxiety. Not mutually exclusive with perimenopause — the two amplify each other. Both are treatable conditions in their own right.
A baseline lab set commonly used for a woman in early perimenopause: thyroid-stimulating hormone, free T4, ferritin, complete blood count (CBC), vitamin B12, 25-OH vitamin D, hemoglobin A1c, comprehensive metabolic panel. See the Hormone Panel page for which hormone tests are worth ordering and which are not.
A Practical 3-Month Symptom Tracker
This is the single most valuable tool you can bring to a clinician visit. Three months of daily data beats any blood test for diagnosing perimenopause and for judging whether hormone replacement therapy or another intervention is working. It also protects you from the common experience of being told "your labs look fine" when your life clearly does not.
A tracker simple enough to keep up every day works best. A notebook, a phone notes app, or a spreadsheet all work. Each day, record the following on a 0–3 scale (0 = none, 1 = mild, 2 = moderate, 3 = severe):
- Hot flashes (count the number during the day)
- Night sweats (count the number of wake-ups)
- Sleep quality (0 = great, 3 = awful)
- Mood / irritability
- Anxiety
- Brain fog / concentration
- Joint aches
- Fatigue
- Libido (0–3 where 0 = none, 3 = normal-for-you)
- Bleeding (none / spotting / light / medium / heavy / flooding)
Each month also note:
- Start and end dates of any bleeding (cycle length is the "first day of one period to first day of the next").
- Any migraines, palpitations, or unusual symptoms.
- Alcohol, caffeine, and exercise patterns (hot flashes and sleep both respond).
- Any medication changes.
After three months, look at the data as a whole. You will see patterns that no single day reveals: cycles that used to be 28 now swinging 24–36; hot flash counts clustered in the week before a period; sleep collapsing during the luteal phase; mood scores tracking inversely with cycle day. That pattern is the diagnosis. A record like this gives a clinician visit something concrete for a treatment discussion, which another follicle-stimulating hormone draw does not.
Cycle- and Symptom-Tracking Apps
For people who do not want a spreadsheet, a number of apps do most of this work. No app is perfect, and privacy concerns are real — apps differ in what they do with health data, which their data policies describe. The main kinds of app with perimenopause-specific features:
- Period- and symptom-tracking apps — cycle tracking, with a specific perimenopause mode in some.
- Menopause symptom apps — built around menopause symptom tracking and education; some turn a symptom score into a report that can be printed for appointments, and some show links between symptoms and lifestyle.
- Smart rings that log skin temperature, and phone health apps — for people who already wear a tracker, the temperature, sleep, and heart-rate variability (HRV) data can add detail, particularly for night sweats and sleep fragmentation.
The app matters less than the consistency: the pattern only shows after about 90 days of daily entries.
Starting Hormone Replacement Therapy Now vs. Waiting
The modern NAMS and international consensus is that for healthy women under 60 or within 10 years of their final menstrual period, the benefits of systemic hormone therapy generally outweigh the risks for moderate-to-severe symptoms. That consensus does not require waiting until a woman is "fully postmenopausal"; starting during perimenopause is common practice when symptoms meaningfully impair sleep, mood, relationships, or work.
On November 10, 2025, the U.S. Food and Drug Administration (FDA) and the Department of Health and Human Services announced the removal of the boxed ("black box") warning from menopausal hormone therapy products. The new labels drop the "lowest effective dose for the shortest duration" mandate and add guidance on starting hormone therapy within 10 years of menopause or before age 60 (Sriprasert 2026).
Situations in which menopause clinicians commonly discuss starting hormone replacement therapy now rather than waiting:
- Hot flashes or night sweats disrupting sleep several nights a week.
- New or worsened depression or anxiety linked to cycle timing.
- Genitourinary symptoms (vaginal dryness, painful sex, recurrent urinary tract infections, UTIs) — these respond best to vaginal estrogen specifically; see GSM & Vaginal Estrogen.
- Joint aches or migraines with a clear cyclical pattern.
- Severe perimenopausal PMS / PMDD that has not responded to other treatments.
- Early menopause (< 45) or POI (< 40) — here hormone replacement therapy is used for bone, cardiovascular, and brain protection, not just symptom relief; the 2024 international POI guideline notes that hormone therapy can lessen some of POI's effects on bone, heart and brain health.
Situations in which waiting, or a non-hormonal route first, is common:
- Symptoms mild and manageable with lifestyle changes (sleep hygiene, exercise, alcohol reduction, weight management).
- A contraindication to systemic estrogen (history of estrogen-sensitive breast cancer, active thromboembolic disease, active liver disease) — see hormone replacement therapy Risks and Non-Hormonal Options.
- Unresolved abnormal bleeding — its cause is normally found before treatment starts.
- Personal preference after informed discussion of risk and benefit.
In perimenopause specifically, hormone replacement therapy often looks like a transdermal estradiol patch (see Estradiol Routes) combined with cyclic or continuous micronized progesterone (see Progesterone vs. Progestins). For women who still need contraception, a combined hormonal contraceptive or a levonorgestrel IUD plus low-dose estrogen is sometimes used instead. The point is that options exist, they can be started during perimenopause, and the decision is individual — not dictated by a follicle-stimulating hormone number.
Key Research Papers
- Harlow SD, et al. Executive summary of the Stages of Reproductive Aging Workshop + 10: addressing the unfinished agenda of staging reproductive aging. J Clin Endocrinol Metab. 2012;97(4):1159–1168. — doi:10.1210/jc.2011-3362
- The 2022 Hormone Therapy Position Statement of The North American Menopause Society. Menopause. 2022;29(7):767–794. — doi:10.1097/GME.0000000000002028
- Avis NE, et al. Duration of menopausal vasomotor symptoms over the menopause transition (SWAN). JAMA Intern Med. 2015;175(4):531–539. — doi:10.1001/jamainternmed.2014.8063
- Randolph JF Jr, et al. Change in follicle-stimulating hormone and estradiol across the menopausal transition: effect of age at the final menstrual period. J Clin Endocrinol Metab. 2011;96(3):746–754. — doi:10.1210/jc.2010-1746
- Santoro N, et al. Menstrual cycle hormone changes in women traversing menopause: Study of Women's Health Across the Nation. J Clin Endocrinol Metab. 2017;102(7):2218–2229. — doi:10.1210/jc.2016-4017
- Panay N, Anderson RA, Bennie A, Cedars M, et al. Evidence-based guideline: premature ovarian insufficiency (ESHRE, ASRM, CRE-WHiRL and IMS Guideline Group on POI). Hum Reprod Open. 2024;2024(4):hoae065. — doi:10.1093/hropen/hoae065
- Ross AC, Manson JE, Abrams SA, Aloia JF, et al. The 2011 report on dietary reference intakes for calcium and vitamin D from the Institute of Medicine: what clinicians need to know. J Clin Endocrinol Metab. 2011;96(1):53–58. — doi:10.1210/jc.2010-2704
- Sriprasert I, Hodis HN, Mack WJ, Rosser M, Evans ML, Xu X, Wright JD. Elimination of the black box warning on menopausal hormone therapy. Obstet Gynecol. 2026;147(5):642–646. — doi:10.1097/AOG.0000000000006226
PubMed Topic Searches
- STRAW+10 menopause staging criteria
- Perimenopause follicle-stimulating hormone variability and diagnosis
- SWAN study vasomotor symptom duration
- Primary ovarian insufficiency diagnosis and management
- Anti-Müllerian hormone and menopause prediction
- Perimenopause and depression or anxiety
- Perimenopause and sleep fragmentation
- Perimenopause cognition and "brain fog"
- Perimenopause symptom tracking and digital health apps
- Thyroid dysfunction and perimenopause symptom overlap
Connections
- Reproductive Medicine
- Perimenopause: History and Discovery — where the staging and the testing came from — the ancient climacteric, Gardanne coining “menopause,” the SWAN and Melbourne cohort studies, and the 2001/2011 STRAW criteria.
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Hormone Replacement Therapy Risks: Breast Cancer, Clots and Stroke
- Hormone Panel
- Insomnia
- Thyroid Disorders
- Micronized Progesterone vs Synthetic Progestins
- Estradiol Formulations: Patch, Gel, Oral Routes
- Genitourinary Syndrome of Menopause and Vaginal Estrogen
- Non-Hormonal Options: Selective Serotonin Reuptake Inhibitors, Gabapentin, Fezolinetant
- Perimenopause
- Testosterone Therapy for Women
- Vasomotor Symptoms: Hot Flashes and Night Sweats
- Bone Loss Prevention and Hormone Replacement Therapy
- Ashwagandha
- Menopause and Hormone Replacement Therapy
- Depression
- Anxiety
- Thyroid Panel
- Fatigue
- Menopause — the endpoint this transition leads to, and how it is defined.