⚠ Evidence warning: Clinical trials or other evidence do not support the claims that women with estrogen-receptor-positive breast cancer history can use black cohosh under an oncologist's supervision and that the scientific consensus is unambiguously that it is not estrogenic. This page keeps it as a report of what people, websites or other media say.
Black Cohosh for Hormonal Balance (Non-Estrogenic Mechanism)
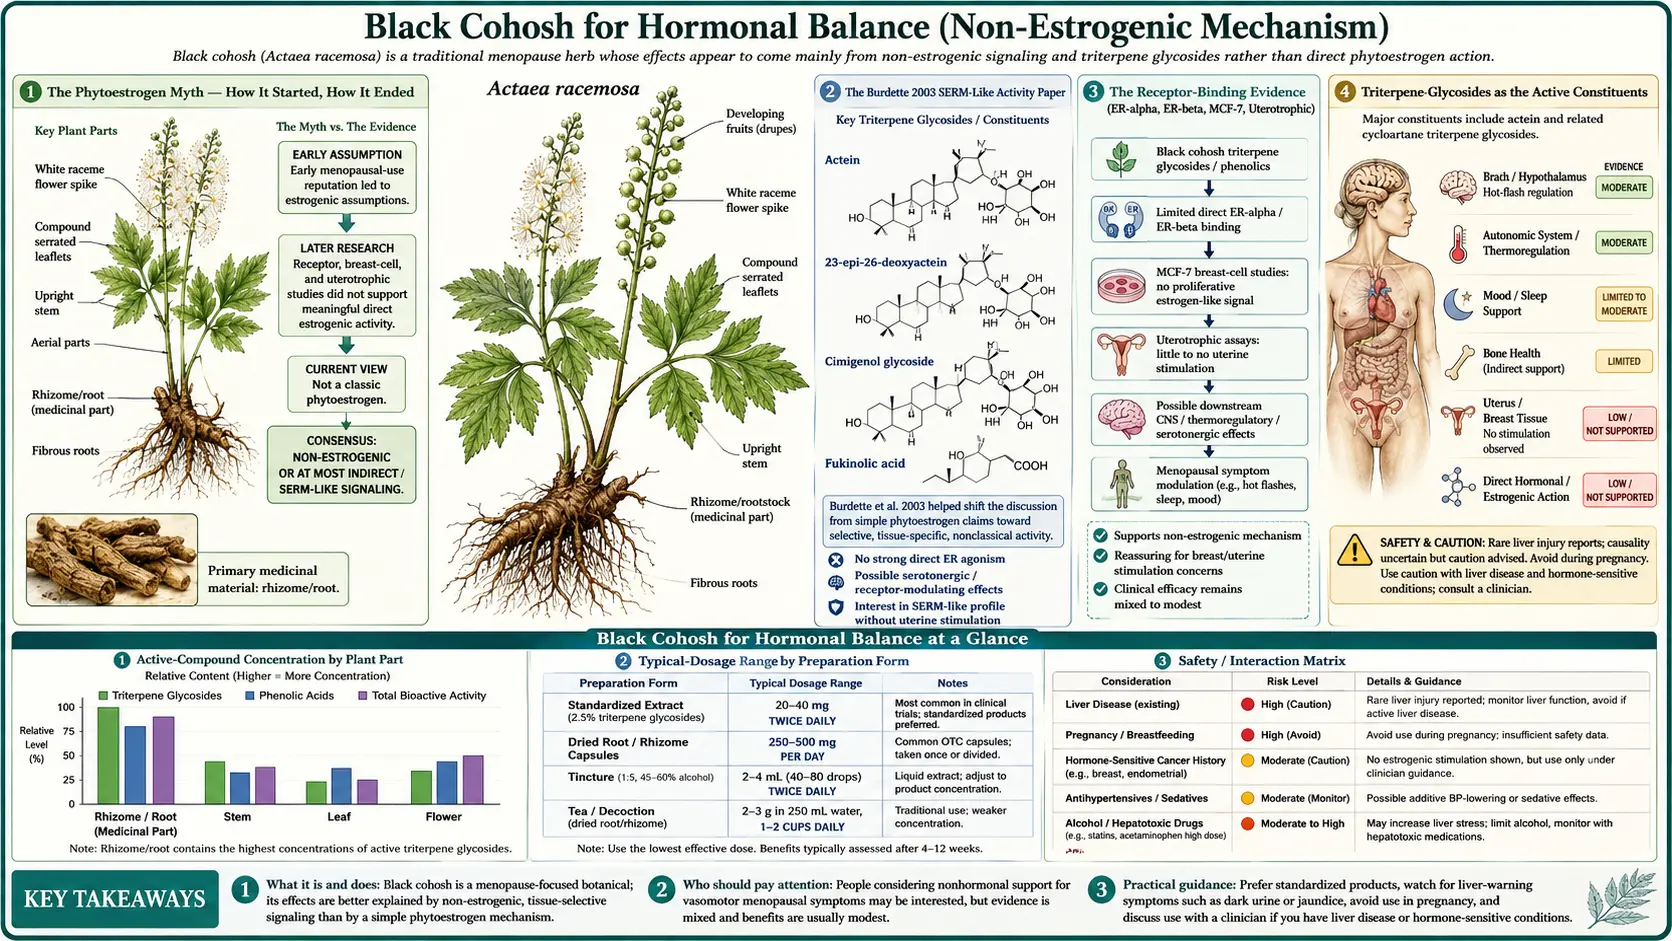
The single most important — and most commonly misunderstood — fact about Black Cohosh is that, in most studies, it does not behave like a phytoestrogen. For most of the twentieth century, the herb was assumed to act like soy isoflavones or red clover — binding weakly to estrogen receptors, producing a partial-agonist effect that mimicked low-dose estrogen. That model was largely set aside after a series of rigorous receptor-binding, gene-expression, and animal-model studies between 2002 and 2008, most notably the Burdette 2003 finding that Black Cohosh extract acts as a mixed competitive ligand at the serotonin 5-HT7 receptor and showed no estrogen-like effect in ovariectomized rats; a few studies still report some estrogen-like effects, so the evidence is mixed rather than settled. The corrected mechanism is multi-target neurotransmitter modulation by the triterpene glycosides actein, 23-epi-26-deoxyactein, and cimicifugoside, with secondary contributions from cinnamic-acid esters. This distinction is why Black Cohosh has been studied in women with a history of estrogen-receptor-positive breast cancer, a group in whom true phytoestrogens raise concern; a German medical-records study of 18,861 breast-cancer patients found no increase in recurrence among the 1,102 who took an isopropanolic extract (see below). Clinically, this distinction matters enormously: women with estrogen-receptor-positive breast cancer history can use Black Cohosh under their oncologist's supervision in a way that they cannot use any true phytoestrogen.
Table of Contents
- The Phytoestrogen Myth — How It Started, How It Ended
- The Burdette 2003 Serotonin-Receptor Paper
- The Receptor-Binding Evidence (ER-alpha, ER-beta, MCF-7, Uterotrophic)
- Triterpene Glycosides as the Active Constituents
- Serotonergic Mechanism (5-HT7, 5-HT1A)
- Dopaminergic and Opioid-Receptor Mechanisms
- Effects on the Hypothalamic-Pituitary-Ovarian (HPO) Axis (Follicle-Stimulating Hormone, Luteinizing Hormone, Estradiol, Prolactin)
- The KNDy Neuron Model and Why It Fits Black Cohosh
- Implications for Breast-Cancer Survivors
- What Black Cohosh Does Not Do (Genitourinary Symptoms, Bone — Mostly)
- What the Liver Reports Show
- Key Research Papers
- Connections
- Featured Videos
The Phytoestrogen Myth — How It Started, How It Ended
The "Black Cohosh is a phytoestrogen" idea originated in the 1980s, when European laboratory work suggested that crude Black Cohosh extracts had estrogen-like activity in some in vitro and animal-model assays. The compound formononetin — an isoflavonoid found in trace amounts in some Black Cohosh preparations — was identified as a possible candidate for the estrogenic activity. The story was clean, mechanistically appealing, and quickly absorbed into the herbal-medicine literature: a North American herb whose traditional use for menopausal symptoms made sense because it was a mild plant estrogen, like soy.
The story began to unravel in the mid-1990s when more careful analyses found that formononetin content in authenticated Actaea racemosa is too low to account for any clinical estrogenic effect — and that several of the original "estrogenic" Black Cohosh samples had been adulterated with red clover (which is genuinely high in formononetin). Receptor-binding studies with purified triterpene glycosides showed no measurable affinity for ER-alpha or ER-beta, although one 2007 study (Bolle) found that a fat-soluble sub-fraction of an extract switched on the human estrogen receptor alpha in a yeast test. Gene-expression studies of estrogen-responsive cells exposed to Black Cohosh extract showed no induction of the expected estrogen-target genes. The Wuttke group's 2003 ovariectomized-rat model showed no uterotrophic effect (a sensitive in vivo assay for estrogen activity).
The capstone study was Burdette 2003 (Journal of Agricultural and Food Chemistry), which found no change in uterine weight or vaginal cells in ovariectomized rats given a 40% 2-propanol extract, then tested the extract against 10 serotonin receptor subtypes and found strong binding to 5-HT1A, 5-HT1D and 5-HT7, most potently at 5-HT7. Subsequent work by the Bolton laboratory at the University of Illinois at Chicago, the Wuttke laboratory at Göttingen, and several other groups built out a much more textured mechanism map involving serotonergic, dopaminergic, GABAergic, and mu-opioid pathways. The evidence on estrogen-like activity is mixed rather than settled: most receptor and hormone studies find no estrogen-like action, but a 2003 trial by the Wuttke group found more surface cells in vaginal smears with both a black cohosh extract and conjugated estrogens and proposed that the extract has selective estrogen receptor modulator (SERM) activity, and Bolle 2007 found estrogen-receptor activation by one sub-fraction in a yeast test. The current scientific consensus, codified in the European Medicines Agency monograph and the German Commission E review, is unambiguous: Black Cohosh is not estrogenic.
The phytoestrogen description persists in consumer-facing materials, on supplement labels, and in many older medical and herbal-medicine textbooks because the correction is not commercially convenient — "natural plant estrogen for menopause" is a simpler marketing message than "multi-target serotonergic modulator with bone-protective triterpene glycosides."
The Burdette 2003 Serotonin-Receptor Paper
Joanna Burdette and colleagues at the Bolton laboratory at the University of Illinois at Chicago published the paper that fundamentally changed the Black Cohosh mechanism story in Journal of Agricultural and Food Chemistry in 2003. The study first gave ovariectomized rats a 40% 2-propanol extract of Actaea racemosa rhizome for 2 weeks, with or without estradiol: there was no effect on uterine weight or on vaginal cell cornification, so in this model the extract showed neither estrogenic nor antiestrogenic properties. The same extract was then tested against 10 subtypes of the human serotonin (5-HT) receptor.
The extract showed strong binding to the 5-HT1A, 5-HT1D and 5-HT7 subtypes, and blocked binding at the human 5-HT7 receptor (IC50 2.4 µg/mL) more potently than at the rat 5-HT1A receptor (IC50 13.9 µg/mL). A methanol extract behaved as a mixed competitive ligand of 5-HT7 and raised cyclic AMP in cells carrying the receptor, which the authors read as partial agonism. The 5-HT7 receptor is particularly relevant because it is expressed in the hypothalamic preoptic area — the brain region that regulates core body temperature setpoint and that is centrally involved in the generation of hot flashes. Paroxetine, venlafaxine, and other selective serotonin reuptake inhibitors/serotonin-norepinephrine reuptake inhibitors reduce hot-flash frequency by approximately 30–50% in clinical trials — and these drugs work by increasing synaptic serotonin, which then engages serotonin receptors including 5-HT7.
The authors concluded that reductions in hot flashes in some women taking black cohosh “may not be due to estrogenic properties” and that serotonin receptors are other possible targets. The paper's title describes a serotonin-receptor ligand; the SERM idea comes from a different 2003 trial by the Wuttke group (see below).
The Receptor-Binding Evidence (ER-alpha, ER-beta, MCF-7, Uterotrophic)
The case that Black Cohosh is not estrogenic rests on several lines of evidence, and a few studies point the other way:
- Direct ER-alpha and ER-beta radioligand-binding assays — Black Cohosh extract does not displace tritiated estradiol from either receptor isoform at any concentration tested (Liu 2001; Wuttke 2003). The IC50 is at or above the upper limit of solubility — effectively no binding.
- Estrogen-response-element (ERE) luciferase reporter assays — transfected cell lines expressing ER and an ERE-luciferase reporter construct produce a strong luminescent signal when exposed to estradiol or true phytoestrogens (genistein, daidzein). Black Cohosh extract produces no signal above background. Co-incubation with estradiol does not block the estradiol response (no antagonism).
- MCF-7 breast-cancer cell proliferation — the MCF-7 line is the standard in vitro screening tool for estrogenic activity. ER-alpha expression in MCF-7 drives proliferation in response to estrogens. Black Cohosh extract does not stimulate MCF-7 proliferation; some preparations actually suppress it. Critically, Black Cohosh does not block tamoxifen-induced growth inhibition (Bodinet 2002; Hostanska 2004) — if it were an estrogen agonist, it would partially reverse tamoxifen's effect, which it does not.
- Uterotrophic assay in ovariectomized rats — the classic in vivo sensitive assay for estrogen activity. An ovariectomized rat has minimal endogenous estrogen and a thin uterine epithelium. A true estrogen, given for 3 days, induces measurable uterine weight increase and epithelial thickening. Black Cohosh extract at therapeutic equivalent doses produces no uterotrophic response (Wuttke 2003; Burdette 2003; Bolle 2007). In contrast, conjugated estrogens produce a robust response in the same model. In the Bolle 2007 study, however, a fat-soluble (lipophilic) sub-fraction of the extract activated the human estrogen receptor alpha in a yeast test, and the authors suggest it may bind an as-yet-unidentified estrogen receptor.
- Endometrial thickness in clinical trials — the human equivalent of the uterotrophic assay. A 2003 double-blind trial by Wuttke and colleagues (62 postmenopausal women, 3 months) compared the black cohosh extract BNO 1055 with 0.6 mg conjugated estrogens and placebo, measuring the womb lining by transvaginal ultrasound. Conjugated estrogens significantly thickened the lining; the black cohosh extract had no effect on it. This is arguably the strongest single piece of in vivo human evidence for the non-estrogenic claim. In the same trial, however, vaginal surface (superficial) cells increased with both the extract and the estrogens, and the authors proposed that the extract contains substances with SERM activity.
- Vaginal cytology (Frank/Papanicolaou) maturation index — estrogen causes vaginal-epithelial maturation toward squamous cells with cornified nuclei; the Frank/Papanicolaou maturation index is sensitive to estrogen exposure. Liske 2002 (24 weeks, no placebo group) included this endpoint and found no change in vaginal cytology — unlike the vaginal-cell increase in the Wuttke 2003 trial above.
The convergence across six independent assay systems — three in vitro, two animal-model, one human clinical — is what gives the non-estrogenic conclusion its weight.
Most of these assay systems point away from an estrogen-like action, but the Wuttke 2003 vaginal-cell finding and the Bolle 2007 yeast result mean the evidence is mixed rather than unanimous.
Triterpene Glycosides as the Active Constituents
Phytochemical fractionation studies have identified the triterpene glycosides as the dominant pharmacologically active class in Actaea racemosa rhizome. The principal compounds are:
- Actein — the most abundant; used as a quantitative marker for extract standardization. Has been studied for anti-cancer effects in breast and pancreatic cell lines and for bone-stimulatory effects.
- 23-epi-26-deoxyactein (formerly called 27-deoxyactein) — chemically related to actein; the second most abundant. Shows similar serotonergic and bone-stimulatory activity in in-vitro assays.
- Cimicifugoside — structurally distinct triterpene glycoside.
- Cimiracemoside A–F — a family of related triterpene glycosides specific to A. racemosa, used as chemotaxonomic markers to distinguish authentic North American Black Cohosh from the adulterating Asian Cimicifuga species.
The triterpene glycosides are not water-soluble; they extract preferentially into iso-propanol, ethanol, or methylene chloride. This is one reason an isopropanolic black cohosh extract has the most-studied pharmacological profile — the extraction solvent matches the solubility profile of the active compounds. (BNO 1055, used in the Wuttke 2003 and Hernández Muñoz 2003 trials, is a different extract.) Aqueous teas and water-extracted preparations contain a different and probably less active phytochemical profile.
The cinnamic-acid esters (fukinolic acid, cimicifugic acids A–F) are secondary contributors. Some in vitro work suggests these compounds have antioxidant and anti-inflammatory activity that may contribute to the overall clinical effect, but they are not the primary mediators of the serotonergic and hormonal effects.
Serotonergic Mechanism (5-HT7, 5-HT1A)
The serotonergic mechanism is the most-studied and most-likely-relevant for the clinical effect on hot flashes. The relevant pharmacology:
- 5-HT7 receptor — Gs-coupled receptor expressed in the hypothalamic preoptic area, the suprachiasmatic nucleus, the cortex, and several limbic structures. Centrally involved in thermoregulatory setpoint, circadian rhythm, and mood. 5-HT7 antagonism produces antidepressant-like and pro-thermoregulatory effects in animal models. In laboratory tests, Black Cohosh extract acts as a mixed-competitive partial agonist (Burdette 2003; Powell 2008) — meaning it both displaces serotonin from the receptor and partially activates the receptor itself, producing a net effect that resembles low-level chronic 5-HT7 stimulation.
- 5-HT1A receptor — Gi-coupled receptor expressed on serotonergic neurons (autoreceptor) and on hippocampal and cortical pyramidal neurons (heteroreceptor). 5-HT1A is the principal target of the anxiolytic drug buspirone. Black Cohosh extract has weaker but measurable 5-HT1A binding (Burdette 2003), which is the mechanistic basis for the modest anxiolytic effect documented in the Mood & Sleep deep-dive.
- 5-HT1D receptor — weaker binding; clinical significance unclear.
The 5-HT7 binding has been proposed as the link to hot flashes: the hypothalamic preoptic area integrates serotonergic, noradrenergic, and KNDy-neuron signals to set the core temperature setpoint. The narrowed thermoneutral zone characteristic of menopause — where small upward shifts in core temperature trigger a vasodilation-and-sweating heat-dissipation cascade that the patient experiences as a hot flash — is partly serotonin-mediated. Drugs that increase serotonergic tone (selective serotonin reuptake inhibitors, serotonin-norepinephrine reuptake inhibitors) widen the thermoneutral zone and reduce hot flashes. The proposal is that Black Cohosh, by partially agonizing 5-HT7 in the preoptic area, produces a similar widening with a different molecular mechanism; this has not been shown in people.
The clinical results so far do not match the laboratory picture. A 2012 Cochrane review (Leach and Moore) pooled 16 randomised trials with 2,027 perimenopausal or postmenopausal women, who took a median of 40 mg of black cohosh a day for an average of 23 weeks. In the three trials (393 women) that counted hot flushes, black cohosh did not differ significantly from placebo (a difference of 0.07 flushes a day), and menopausal symptom scores did not differ in four trials (357 women). Hormone therapy reduced symptom scores more than black cohosh did. The reviewers found “insufficient evidence to support the use of black cohosh for menopausal symptoms”, noted that the quality of the trials was generally unclear, and judged further studies justified.
Dopaminergic and Opioid-Receptor Mechanisms
Dopaminergic activity: In vitro studies (Jarry 2003; Powell 2008) have documented Black Cohosh extract binding to dopamine D2 receptors with moderate affinity. The D2 receptor is the primary target of prolactin-suppressing drugs like bromocriptine and cabergoline (D2 agonism on lactotrophs in the anterior pituitary suppresses prolactin secretion). Some clinical studies have documented mild prolactin reduction in women on Black Cohosh, consistent with weak D2 agonism. The dopaminergic effect may also contribute to mood modulation through mesolimbic and tuberoinfundibular pathways. The clinical magnitude is modest — Black Cohosh is not a substitute for cabergoline in true hyperprolactinemia and is not a clinically significant antipsychotic-effect modifier.
Mu-opioid receptor activity: Reame and colleagues (2008) studied postmenopausal women before and after 12 weeks of unblinded treatment with a black cohosh supplement at 40 mg a day. Brain scans with a tracer that binds mu-opioid receptors (positron emission tomography, PET, in 5 women) showed mu-opioid receptor binding rising by 10% to 61% in several brain regions involved in emotion and thinking, and a naloxone challenge (6 women) changed luteinizing hormone pulses; the authors read both as a central opioid action. The clinical significance is debated. The opioid-receptor hypothesis is mechanistically interesting because the hypothalamic KNDy-neuron system (kisspeptin/neurokinin B/dynorphin) that is now understood as the central regulator of vasomotor symptoms is itself opioid-modulated — dynorphin is a kappa-opioid agonist and is a key inhibitory signal in the KNDy negative-feedback loop. A drug that engages opioid receptors in this circuit could plausibly modulate the entire vasomotor-symptom-generating system. This remains an active research area without clear clinical-evidence translation yet.
The opioid hypothesis also raises a safety question about possible opioid-receptor desensitization, tolerance, or withdrawal with chronic Black Cohosh use. The clinical-trial data through 12 months of use show no withdrawal syndrome on discontinuation and no progressive tolerance, but the data do not address all the questions that the opioid mechanism raises. In the trials pooled by the 2012 Cochrane review, treatment lasted 23 weeks on average, so use beyond a year has been studied less. This is one reason that clinically the recommendation is to limit Black Cohosh courses to 6–12 months with monitoring rather than indefinite use.
Effects on the Hypothalamic-Pituitary-Ovarian (HPO) Axis (Follicle-Stimulating Hormone, Luteinizing Hormone, Estradiol, Prolactin)
If Black Cohosh were genuinely estrogenic, you would expect to see negative-feedback suppression of follicle-stimulating hormone (FSH) (which is elevated in postmenopausal women due to loss of ovarian estrogen feedback). You would expect to see suppression of luteinizing hormone (LH) for the same reason. You would expect to see measurable serum estradiol elevation if the herb itself or its metabolites were binding circulating sex-hormone-binding globulin or being measured in the estradiol immunoassay. None of these are observed.
- Follicle-stimulating hormone: Multiple clinical trials (Liske 2002; Bai 2007; Wuttke 2006) have measured serum follicle-stimulating hormone before and after Black Cohosh treatment for 12–52 weeks. No statistically significant change. This is a strong piece of evidence that the hypothalamic-pituitary system does not perceive the herb as estrogen.
- Luteinizing hormone: Same pattern — no change in serum luteinizing hormone on Black Cohosh therapy.
- Estradiol: No change in serum estradiol measured by immunoassay or LC-MS/MS. Black Cohosh metabolites do not cross-react with the standard estradiol assays.
- SHBG: No change in sex-hormone-binding globulin (which is upregulated by oral estrogen exposure via first-pass hepatic effect).
- Prolactin: Slight reduction documented in some studies; consistent with the weak D2-agonist activity described above.
- Inhibin B, AMH, kisspeptin: Not systematically studied. Would be interesting follow-up given the KNDy hypothesis.
Two trials give a sense of the numbers. In Liske 2002, perimenopausal and postmenopausal women took 39 mg or 127.3 mg a day of an isopropanolic extract for 24 weeks: symptoms fell at both doses (responder rates 70% and 72%), the higher dose did no better on any end point, and vaginal cytology and gynecologically relevant hormones showed no significant change; the study had no placebo group. In Bai 2007, a double-blind trial, 244 Chinese women aged 40–60 took the isopropanolic extract (40 mg of crude herb a day) or tibolone 2.5 mg a day for 3 months: the Kupperman Menopause Index fell from 24.7 to 7.7 with black cohosh and to 7.5 with tibolone, which the authors judged non-inferior; adverse events were less frequent with black cohosh, and none of the postmenopausal women on black cohosh had vaginal bleeding, against 17 cases on tibolone.
Because these hormone levels did not change in the trials, hormone tests do not track Black Cohosh's effect; the safety concern that has been reported is liver injury (see the liver section below). Symptom response and liver-function monitoring are the relevant clinical parameters. See the Hormone Panel page for the relevant baseline-assessment context.
The KNDy Neuron Model and Why It Fits Black Cohosh
The current best model of hot-flash generation centers on the KNDy neurons — arcuate-nucleus neurons that co-express kisspeptin, neurokinin B, and dynorphin. In premenopausal women, these neurons receive negative-feedback signals from circulating estrogen, which keeps their tonic firing rate suppressed. After menopause, estrogen drops, the KNDy neurons hypertrophy (documented in human autopsy studies), and their now-disinhibited firing produces a heightened input to the hypothalamic thermoregulatory center.
The KNDy neurons release neurokinin B (an NK3 receptor agonist) onto the preoptic-area thermoregulatory neurons, which narrows the thermoneutral zone and triggers a heat-dissipation cascade (cutaneous vasodilation, sweating) at lower-than-normal core-temperature triggers. The clinical proof of this mechanism came in 2019–2020 with the demonstration that NK3-receptor antagonists (fezolinetant, elinzanetant) reduce hot-flash frequency by 60–75% in randomized trials — an effect size approaching that of systemic estrogen. Fezolinetant was approved by the U.S. Food and Drug Administration (FDA) in 2023 for moderate-to-severe vasomotor symptoms; elinzanetant followed on October 24, 2025.
The KNDy model is relevant to Black Cohosh because the proposed serotonergic, dopaminergic, and opioid mechanisms of Black Cohosh all converge on the KNDy neurons and their downstream targets. 5-HT7 stimulation in the preoptic area widens the thermoneutral zone. D2 agonism in the arcuate nucleus modulates KNDy firing. Mu-opioid engagement parallels endogenous dynorphin's inhibitory role within the KNDy cell itself. The molecular targets are different from NK3 antagonism; whether the system-level effect is similar — restoration of a wider thermoneutral zone — has not been shown, and the 2012 Cochrane review found no significant difference between black cohosh and placebo in daily hot flushes.
In this converging-pathway model, both Black Cohosh and selective serotonin reuptake inhibitors/serotonin-norepinephrine reuptake inhibitors act on the serotonergic input to the same hypothalamic circuit, by different molecular mechanisms. The 2023 position statement of the North American Menopause Society (NAMS) lists these drugs among the recommended nonhormone options for hot flashes (Level I evidence) and lists supplements and herbal remedies as not recommended (Levels I–II).
Implications for Breast-Cancer Survivors
The non-estrogenic mechanism is the single most clinically consequential fact about Black Cohosh because it is why Black Cohosh has been studied for vasomotor symptoms (hot flashes and sweats) in women with a personal history of estrogen-receptor-positive breast cancer.
The evidence so far:
- In vitro: Black Cohosh extract does not stimulate MCF-7 proliferation; some preparations suppress it; it does not block tamoxifen's growth-inhibitory effect.
- Animal models: Black Cohosh in mammary-tumor-bearing rodents does not accelerate tumor growth; some models show modest tumor-growth suppression.
- Clinical trials in breast-cancer survivors: The Hernández Muñoz 2003 open-label randomised trial enrolled 136 young premenopausal breast-cancer survivors aged 35–52 on tamoxifen (90 given the BNO 1055 extract plus tamoxifen, 46 tamoxifen alone) for 12 months: severe hot flushes were reported by 24.4% of the extract group and 73.9% of the tamoxifen-only group. The Rostock 2011 prospective observational study gave an isopropanolic extract to 50 tamoxifen-treated breast-cancer patients for 6 months; the total menopause rating scale (MRS II) score fell from 17.6 to 13.6, with hot flashes, sweating, sleep problems and anxiety improving. It did not study recurrence.
- Recurrence: A German medical-records study (Henneicke-von Zepelin 2007) of 18,861 breast-cancer patients, 1,102 of whom took an isopropanolic black cohosh extract, followed for a mean of 3.6 years, found no increase in recurrence (hazard ratio 0.83, 95% confidence interval 0.69–0.99). It is an observational study, not a randomised trial.
- 2023 NAMS position statement: The 2023 nonhormone therapy statement lists “supplements/herbal remedies” under “Not recommended” for hot flashes (Levels I–II evidence). It names hormone therapy as the most effective treatment and, for women who are not candidates for it (for example because of estrogen-dependent cancers), lists cognitive-behavioral therapy, clinical hypnosis, selective serotonin reuptake inhibitors/serotonin-norepinephrine reuptake inhibitors, gabapentin and fezolinetant as recommended (Level I).
In the breast-cancer studies above, the extract was taken for 6 to 12 months alongside tamoxifen. The safety concern reported for Black Cohosh is liver injury (see the liver section below); some chemotherapy drugs can also harm the liver. The principal monitoring requirement is liver function (the hepatotoxicity warning applies with extra force in patients who may be on hepatotoxic chemotherapy). See the Menopause & Hot Flashes deep-dive for the trial-specific evidence.
What Black Cohosh Does Not Do (Genitourinary Symptoms, Bone — Mostly)
Areas where Black Cohosh has not been shown to help much:
- Genitourinary syndrome of menopause (GSM) — vaginal dryness, vulvar atrophy, dyspareunia, urinary urgency and recurrent urinary tract infection (UTI). These symptoms are driven by direct loss of estrogen action on the vaginal and vulvar epithelium and urinary tract. They respond well to local vaginal estrogen (which has minimal systemic absorption), to ospemifene (an oral SERM), to DHEA prasterone (vaginal), and to vaginal moisturizers. Black Cohosh has not been shown to treat GSM.
- Bone protection (mostly) — Black Cohosh shows a measurable but small positive effect on bone-resorption markers in clinical trials. It is not a substitute for bisphosphonates, denosumab, teriparatide, or systemic estrogen for established osteoporosis. See the Bone Health deep-dive for the detail.
- Cardiovascular and cognitive benefits associated with hormone replacement therapy (HRT) — not demonstrated for Black Cohosh.
- Severe depressive episodes — Black Cohosh has mild anxiolytic and mood-stabilizing activity but does not substitute for selective serotonin reuptake inhibitor (SSRI)/serotonin-norepinephrine reuptake inhibitor (SNRI) therapy in moderate-to-severe major depression. Black cohosh–St. John's Wort combination products have been studied for milder mood symptoms; see the Mood & Sleep deep-dive.
- Severe vasomotor symptoms unresponsive to first-line therapy — for the most severe cases, the new NK3 antagonists (fezolinetant, elinzanetant) and systemic estrogen produce the largest effect size; the 2012 Cochrane review found that hormone therapy reduced symptom scores more than Black Cohosh did.
What the Liver Reports Show
In 2008 the Dietary Supplement Information Expert Committee of the United States Pharmacopeia (USP) reviewed safety information on black cohosh products, after regulators in Australia, Canada and the European Union had issued statements on a “potential association” with liver damage. The committee analysed 30 non-duplicate reports of liver damage, gathered from the European Medicines Agency, Health Canada, the Australian Therapeutic Goods Administration and the US Food and Drug Administration, using the Naranjo causality scale. All 30 were rated “possible” causality; none were rated “probable” or “certain”. Animal toxicology and pharmacokinetic data showed nothing unfavourable. The committee nevertheless decided that black cohosh products should carry a cautionary label statement — a change from its 2002 decision, which required none.
Yellowing of the skin or eyes (jaundice), dark urine and pain in the upper right belly are signs of liver injury that hospitals treat as urgent.
Key Research Papers
- Burdette JE, Liu J, Chen SN et al. (2003). Black cohosh acts as a mixed competitive ligand and partial agonist of the serotonin receptor. Journal of Agricultural and Food Chemistry 51(19):5661-70. — PubMed PMID: 12952416
- Liu J, Burdette JE, Xu H et al. (2001). Evaluation of estrogenic activity of plant extracts for the potential treatment of menopausal symptoms. Journal of Agricultural and Food Chemistry 49(5):2472-9. — PubMed PMID: 11368622
- Wuttke W, Jarry H, Becker T et al. (2003). Phytoestrogens: endocrine disrupters or replacement for hormone replacement therapy? Maturitas 44 Suppl 1:S9-20. — PubMed PMID: 12609555
- Bodinet C, Freudenstein J (2002). Influence of Cimicifuga racemosa on the proliferation of estrogen receptor-positive human breast cancer cells. Breast Cancer Research and Treatment 76(1):1-10. — PubMed PMID: 12408370
- Hostanska K, Nisslein T, Freudenstein J et al. (2004). Cimicifuga racemosa extract inhibits proliferation of estrogen receptor-positive and negative human breast carcinoma cell lines by induction of apoptosis. Breast Cancer Research and Treatment 84(2):151-60. — PubMed PMID: 14999145
- Powell SL et al. (2008). In vitro serotonergic activity of black cohosh and identification of N(omega)-methylserotonin as a potential active constituent. Journal of Agricultural and Food Chemistry 56(24):11718-26. — PubMed PMID: 19049296
- Reame NE et al. (2008). Black cohosh has central opioid activity in postmenopausal women: evidence from naloxone blockade and positron emission tomography neuroimaging. Menopause 15(5):832-40. — PubMed PMID: 18521048
- Jarry H, Metten M, Spengler B et al. (2003). In vitro effects of the Cimicifuga racemosa extract BNO 1055. Maturitas 44 Suppl 1:S31-8. — PubMed PMID: 12609557
- Bolle P, Mastrangelo S, Perrone F et al. (2007). Estrogen-like effect of a Cimicifuga racemosa extract sub-fraction as assessed by in vivo, ex vivo and in vitro assays. Journal of Steroid Biochemistry and Molecular Biology 107(3-5):262-9. — PubMed PMID: 17689956
- Ruhlen RL et al. (2007). Black cohosh: insights into its mechanism(s) of action. Integrative Medicine Insights 2:21-32. — PubMed
- Rostock M, Fischer J, Mumm A et al. (2011). Black cohosh (Cimicifuga racemosa) in tamoxifen-treated breast cancer patients with climacteric complaints — a prospective observational study. Gynecological Endocrinology 27(10):844-8. — PubMed PMID: 21231853
- Henneicke-von Zepelin HH, Meden H, Kostev K et al. (2007). Isopropanolic black cohosh extract and recurrence-free survival after breast cancer. International Journal of Clinical Pharmacology and Therapeutics 45(3):143-54. — PubMed PMID: 17416109
- Wuttke W, Seidlová-Wuttke D, Gorkow C (2003). The Cimicifuga preparation BNO 1055 vs. conjugated estrogens in a double-blind placebo-controlled study: effects on menopause symptoms and bone markers. Maturitas 44 Suppl 1:S67-77. — PubMed PMID: 12609561
- Hernández Muñoz G, Pluchino S (2003). Cimicifuga racemosa for the treatment of hot flushes in women surviving breast cancer. Maturitas 44 Suppl 1:S59-65. — PubMed PMID: 12609560
- Liske E, Hänggi W, Henneicke-von Zepelin HH et al. (2002). Physiological investigation of a unique extract of black cohosh (Cimicifugae racemosae rhizoma): a 6-month clinical study demonstrates no systemic estrogenic effect. Journal of Women's Health & Gender-Based Medicine 11(2):163-74. — PubMed PMID: 11975864
- Bai W, Henneicke-von Zepelin HH, Wang S et al. (2007). Efficacy and tolerability of a medicinal product containing an isopropanolic black cohosh extract in Chinese women with menopausal symptoms: a randomized, double blind, parallel-controlled study versus tibolone. Maturitas 58(1):31-41. — PubMed PMID: 17587516
- Leach MJ, Moore V (2012). Black cohosh (Cimicifuga spp.) for menopausal symptoms. Cochrane Database of Systematic Reviews 2012(9):CD007244. — PubMed PMID: 22972105
- Mahady GB, Low Dog T, Barrett ML et al. (2008). United States Pharmacopeia review of the black cohosh case reports of hepatotoxicity. Menopause 15(4 Pt 1):628-38. — PubMed PMID: 18340277
- The North American Menopause Society (2023). The 2023 nonhormone therapy position statement of The North American Menopause Society. Menopause 30(6):573-590. — PubMed PMID: 37252752
PubMed Topic Searches
Connections
- All Herbs
- Black Cohosh Overview
- Black Cohosh Benefits Hub
- Black Cohosh for Menopause & Hot Flashes
- Black Cohosh for Bone Health
- Black Cohosh for Mood & Sleep
- Perimenopause
- Perimenopause Symptom Tracker
- Polycystic Ovary Syndrome
- Hormone Panel
- Maca
- Ashwagandha
- Chamomile
- Lemon Balm
- Stress Management
- History