⚠ Evidence warning: Clinical trials or other evidence do not support the claim that fezolinetant is often the single best option for a woman with a breast cancer history who has uncontrolled hot flashes on tamoxifen. This page keeps it as a report of what people, websites or other media say.
Non-Hormonal Options: Selective Serotonin Reuptake Inhibitors, Gabapentin, Fezolinetant
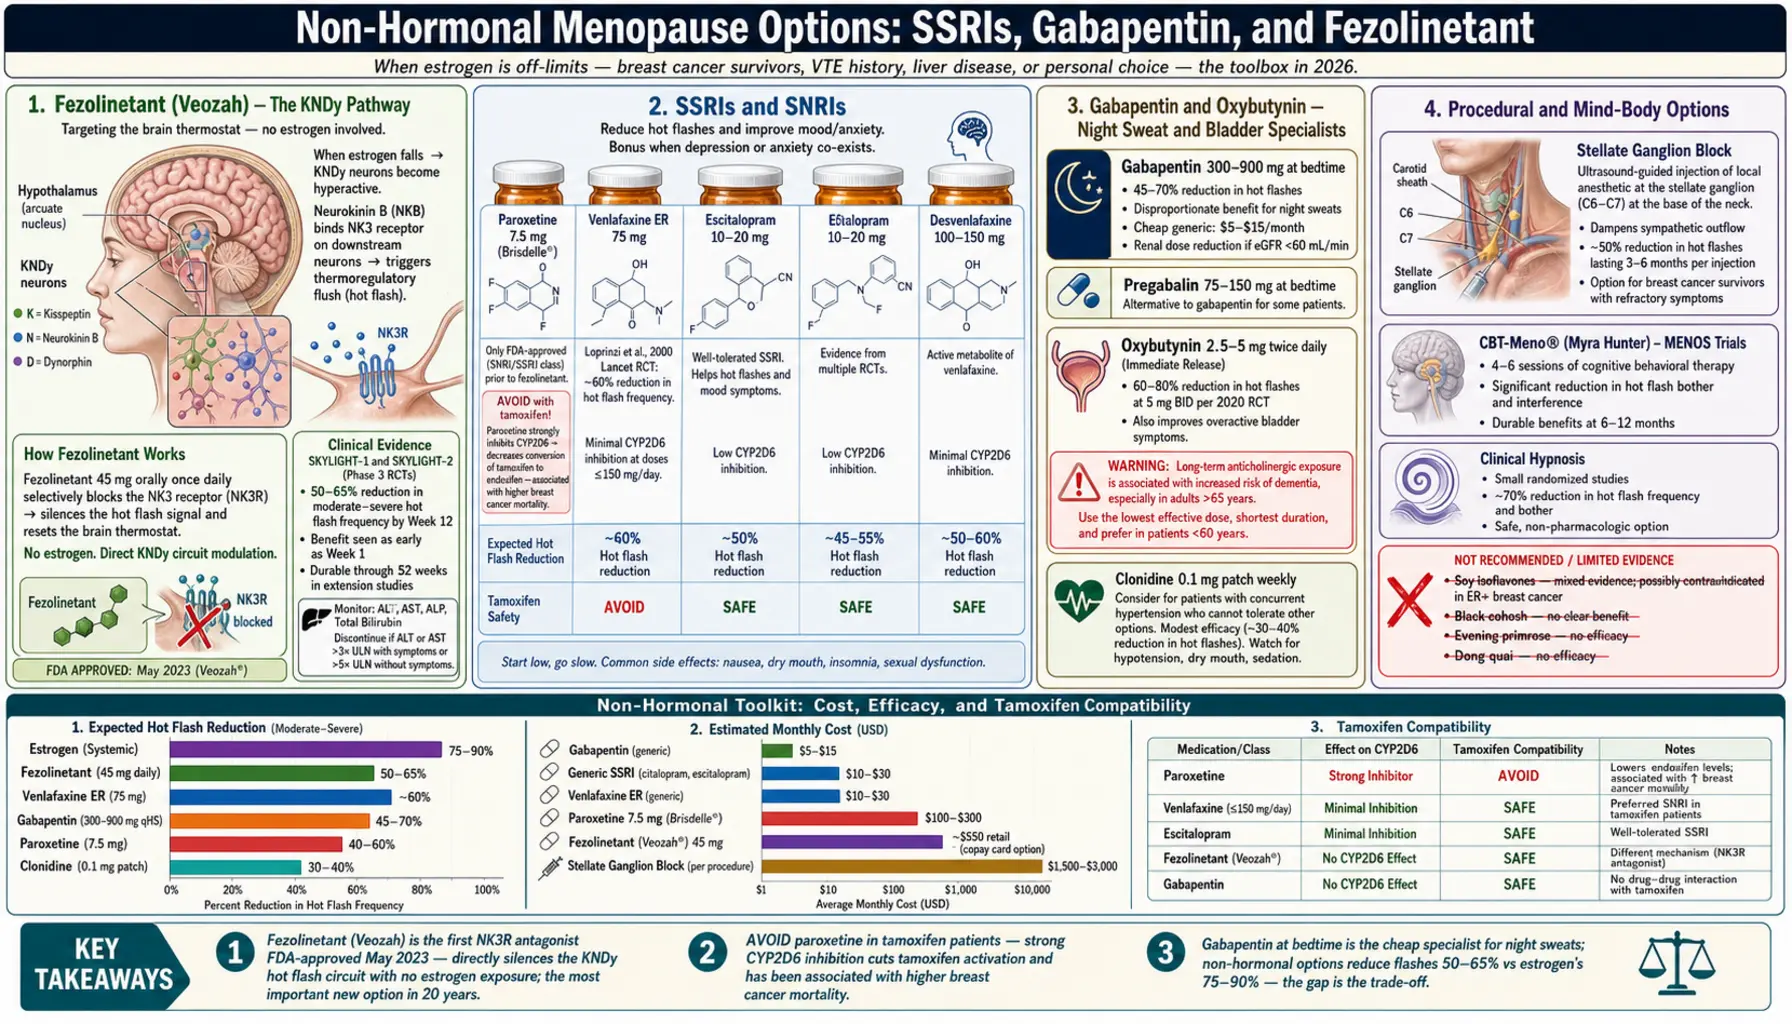
You may have very good reasons not to take hormone therapy. A personal or strong family history of breast cancer. A prior blood clot, stroke, or known thrombophilia. Active liver disease. Unexplained vaginal bleeding. Or simply — after reading the risks and talking to your clinician — the decision that estrogen is not the right tool for you. None of that means you have to white-knuckle your way through hot flashes, 3 a.m. drenching sweats, and the brain fog that rides along with them.
The good news: the non-hormonal toolbox has expanded dramatically, including a first-in-class drug (fezolinetant) approved in 2023 that targets the brain circuit driving hot flashes directly. The not-so-good news: most non-hormonal options deliver roughly a 50–65% reduction in vasomotor symptoms, compared with the 75–90% reduction estrogen typically provides. That gap matters, and it is the main reason non-hormonal therapy sometimes leads back to a second conversation about hormone replacement therapy (HRT).
This article walks through every evidence-backed non-hormonal option currently used in 2026, with realistic expectations, dosing, side effects, and costs.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone (FSH) climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →Table of Contents
- Who This Article Is For
- What the 2023 North American Menopause Society Statement Recommends
- Fezolinetant — The New Neurokinin 3 Receptor (NK3R) Antagonist
- Elinzanetant, the Second Brain-Targeted Pill
- Selective Serotonin Reuptake Inhibitors and Serotonin-Norepinephrine Reuptake Inhibitors — Paroxetine, Venlafaxine, and Cousins
- Gabapentin and Pregabalin — Night-Sweat Specialists
- Clonidine and Oxybutynin
- Stellate Ganglion Block
- Cognitive Behavioral Therapy, Hypnosis, and Mindfulness
- Herbs, Soy, and Supplements
- Acupuncture, Cooling Devices, and Weighted Blankets
- When to Reopen the Hormone Replacement Therapy Conversation
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
Who This Article Is For
Non-hormonal therapy is standard of care if you fall into any of these groups:
- Personal history of hormone-sensitive breast cancer (ER-positive), and especially if you are on tamoxifen or an aromatase inhibitor.
- Prior deep vein thrombosis, pulmonary embolism, or stroke, or a known thrombophilia (Factor V Leiden, prothrombin mutation, antiphospholipid syndrome).
- Active liver disease or recent unexplained elevated liver enzymes.
- Unexplained vaginal bleeding that has not yet been worked up.
- Coronary artery disease or recent heart attack, particularly if you are more than 10 years past menopause.
- Personal preference — you read about hormone replacement therapy and decided it is not for you. That is a valid reason, and a good clinician will work with it.
For everyone else, non-hormonal options are still reasonable either as first-line (if you prefer) or as add-ons to hormone replacement therapy when estrogen alone is not fully controlling symptoms.
What the 2023 North American Menopause Society Statement Recommends
In 2023 The North American Menopause Society (NAMS, now The Menopause Society) published a position statement on non-hormone treatment of hot flashes and night sweats (vasomotor symptoms). Its panel graded the evidence as Level I (good and consistent evidence), Level II (limited or inconsistent evidence) or Level III (consensus and expert opinion), and listed each option as recommended or not recommended. The table reports the statement's position; it does not cover elinzanetant, which was approved in 2025, after the statement was written.
| Statement's position | Options | Evidence level |
|---|---|---|
| Recommended | Cognitive behavioral therapy; clinical hypnosis; selective serotonin reuptake inhibitors and serotonin-norepinephrine reuptake inhibitors; gabapentin; fezolinetant | Level I |
| Recommended | Oxybutynin | Levels I–II |
| Recommended | Weight loss; stellate ganglion block | Levels II–III |
| Not recommended | Paced breathing (paced respiration) | Level I |
| Not recommended | Supplements and herbal remedies | Levels I–II |
| Not recommended | Cooling techniques; avoiding triggers; exercise; yoga; mindfulness-based intervention; relaxation; suvorexant; soy foods and soy extracts; the soy metabolite equol; cannabinoids; acupuncture; calibration of neural oscillations | Level II |
| Not recommended | Chiropractic interventions; clonidine | Levels I–III |
| Not recommended | Dietary modification; pregabalin | Level III |
The statement also concludes that hormone therapy remains the most effective treatment for vasomotor symptoms. "Not recommended" in this table is the panel's judgement of the evidence for hot flashes; several of these options are still used for comfort, sleep or other reasons, and are described below.
Fezolinetant — The New Neurokinin 3 Receptor (NK3R) Antagonist
Fezolinetant is the first drug designed specifically to silence the brain circuit that causes hot flashes. It was U.S. Food and Drug Administration-approved in May 2023 for moderate-to-severe vasomotor symptoms of menopause. For women who cannot take estrogen, this is the most important new tool in 20 years.
How it works. When ovarian estrogen falls, a cluster of neurons in the hypothalamus called KNDy neurons (kisspeptin, neurokinin B, dynorphin) become hyperactive. These neurons release neurokinin B, which binds the NK3 receptor and triggers the thermoregulatory flush — the cascade you feel as a hot flash. Fezolinetant blocks the NK3 receptor. No estrogen involved. The brain thermostat resets without touching breast, uterine, or clotting tissue.
Dose. 45 mg orally once daily, any time of day, with or without food.
What to expect. In the SKYLIGHT-1 and SKYLIGHT-2 phase 3 trials, women taking fezolinetant had roughly a 50–65% reduction in the frequency of moderate-to-severe hot flashes by week 12, with significant improvement as early as week 1. Severity scores also dropped. Benefit maintained through 52 weeks of open-label extension.
Boxed warning for liver injury (added December 2024). The current U.S. label (revised February 2026) carries a boxed warning — the U.S. Food and Drug Administration's (FDA's) strongest kind — stating that liver injury (hepatotoxicity) has occurred with fezolinetant since it reached the market. The label calls for liver blood tests (alanine aminotransferase (ALT), aspartate aminotransferase (AST), alkaline phosphatase and bilirubin) before starting, and states that the drug is not started if ALT or AST, or total bilirubin, is 2 or more times the upper limit of normal. Follow-up liver tests are listed monthly for the first 3 months, then at 6 months and 9 months. The label lists these signs of possible liver injury, on which the drug is stopped at once and liver tests are done: new tiredness, poor appetite, nausea, vomiting, itching, yellow skin or eyes (jaundice), pale stools, dark urine or belly pain. Known cirrhosis is a contraindication (a condition in which the label says the drug is not to be used). In the SKYLIGHT 1 trial, liver enzyme rises were uncommon and were generally without symptoms and temporary.
One-year safety trial (SKYLIGHT 4). In this 52-week trial, 1,830 postmenopausal women took placebo, fezolinetant 30 mg or fezolinetant 45 mg daily. Side effects were about as common on placebo (64.1%) as on fezolinetant (67.9% at 30 mg, 63.9% at 45 mg). Among women who had womb-lining (endometrial) biopsies, 1 of 203 on 45 mg had endometrial hyperplasia (a thickened lining) and 1 of 210 on 30 mg had endometrial cancer, with no cases on placebo; the trial judged these rates against the FDA's guidance limit of 1% or less. Liver enzymes above 3 times the upper limit of normal occurred in 12 of 589 women on 45 mg, 8 of 590 on 30 mg and 6 of 583 on placebo, with no cases meeting the definition of severe drug-induced liver injury. Changes in bone density were similar in all groups.
Side effects. Abdominal pain, diarrhea, insomnia, back pain, and hot flash (paradoxically, as the body adjusts). Most are mild.
Drug interactions and kidney disease. Fezolinetant is primarily metabolized by the liver enzyme CYP1A2. The label lists use together with any CYP1A2 inhibitor — weak, moderate or strong — as a contraindication, because these drugs raise fezolinetant levels in the blood. Examples of CYP1A2 inhibitors include ciprofloxacin, fluvoxamine and mexiletine. Severe kidney disease (severe renal impairment or end-stage renal disease) is also a contraindication on the label.
Cost reality. List price is approximately $550 per month in the U.S. (about $6,600/year). Coverage is improving but still inconsistent — many commercial plans require step therapy (trial of a selective serotonin reuptake inhibitor or gabapentin first) before approving fezolinetant. The manufacturer runs a patient assistance program and a copay card for commercially insured patients that can bring out-of-pocket cost to as low as $5–$30/month; prescribing clinicians' offices often help with enrollment. Without insurance or assistance, cost is a real barrier. A second drug that works on the same brain pathway, elinzanetant, was approved by the FDA on 24 October 2025 (see the next section).
Where it fits. Fezolinetant is one of the options the 2023 North American Menopause Society statement recommends at its strongest evidence level (Level I). For a woman with breast cancer history who is miserable on tamoxifen with uncontrolled flashes, fezolinetant is often the single best option. It is new enough that some clinicians are still unfamiliar with it.
Elinzanetant, the Second Brain-Targeted Pill
Elinzanetant was approved by the U.S. Food and Drug Administration on 24 October 2025 for moderate to severe hot flashes and night sweats (vasomotor symptoms) due to menopause. It blocks two brain receptors, neurokinin 1 (NK1) and neurokinin 3 (NK3); fezolinetant blocks NK3 only. The label dose is 120 mg (two 60 mg capsules) once daily at bedtime.
OASIS 1 and 2 (Pinkerton 2024, JAMA). Two 26-week trials each enrolled about 400 postmenopausal women aged 40 to 65 who started with about 13 to 16 moderate-to-severe hot flashes a day. Compared with placebo, elinzanetant cut moderate-to-severe hot flashes by about 3 more per day at week 4 (3.3 and 3.0 in the two trials) and at week 12 (3.2 in both), lowered their severity, and improved sleep disturbance and menopause-related quality of life at week 12.
OASIS 4 (Cardoso 2025, New England Journal of Medicine). This trial enrolled women aged 18 to 70 whose hot flashes came from hormone (endocrine) therapy for hormone receptor-positive breast cancer or for its prevention: 316 were assigned to elinzanetant and 158 to placebo. They started with about 11.4 hot flashes a day. By week 12 these fell by 7.8 a day on elinzanetant and 4.2 on placebo — about 3.4 more with the drug. In weeks 1–12, 69.8% on elinzanetant and 62.0% on placebo reported at least one side effect, most often headache, fatigue and sleepiness (somnolence); serious side effects occurred in 2.5% and 0.6%.
What the label warns.
- Sleepiness and daytime impairment: across the three OASIS trials, nervous-system effects (sleepiness, fatigue, vertigo, dizziness, near-fainting) occurred in 11.9% of women on elinzanetant and 3.5% on placebo; the label advises against driving or hazardous work until these effects have passed.
- Liver: liver blood tests before starting (the drug is not started if ALT or AST, or total bilirubin, is 2 or more times the upper limit of normal) and a follow-up test 3 months after starting; the drug is stopped at once if signs of liver injury appear.
- Pregnancy: contraindicated, because it may cause pregnancy loss or stillbirth.
- Seizures were reported, and the label calls for caution in people with a history of seizures.
- Interactions: the label lists strong CYP3A4 inhibitors, grapefruit juice and CYP3A4 inducers as combinations to avoid, and lowers the dose to 60 mg with moderate CYP3A4 inhibitors.
Selective Serotonin Reuptake Inhibitors and Serotonin-Norepinephrine Reuptake Inhibitors — Paroxetine, Venlafaxine, and Cousins
Antidepressants in the selective serotonin reuptake inhibitor (SSRI) and serotonin-norepinephrine reuptake inhibitor (SNRI) families reduce hot flashes through serotonin and norepinephrine pathways in the hypothalamus. The effect appears within 1–2 weeks — much faster than their antidepressant effect, which takes 4–6 weeks.
Paroxetine 7.5 mg
The only U.S. Food and Drug Administration-approved non-hormonal treatment for hot flashes before fezolinetant. The 7.5 mg product is a low-dose paroxetine formulation (7.5 mg) specifically dosed below the antidepressant range to minimize side effects while retaining hot flash benefit.
- Dose: 7.5 mg at bedtime.
- Expected benefit: 40–60% reduction in hot flash frequency.
- Big warning: Paroxetine and tamoxifen are a known problem combination. Paroxetine is a strong inhibitor of cytochrome P450 2D6 (CYP2D6), the enzyme that converts tamoxifen into its active metabolite endoxifen. Co-administration can cut tamoxifen's effectiveness and has been associated with higher breast cancer mortality in retrospective studies. For women on tamoxifen, the drugs usually used instead are venlafaxine, desvenlafaxine, escitalopram, or citalopram.
- Side effects: Nausea (usually transient), headache, drowsiness. Less sexual side effects at 7.5 mg than at antidepressant doses.
- Discontinuation: Paroxetine is tapered slowly — it has the worst discontinuation syndrome of any selective serotonin reuptake inhibitor, and stopping it suddenly brings that syndrome on.
Venlafaxine — Off-Label but Widely Used
Venlafaxine is a serotonin-norepinephrine reuptake inhibitor that became the de facto standard for non-hormonal hot flash treatment after Charles Loprinzi's landmark 2000 Lancet trial in breast cancer survivors.
- Dose: Usually 37.5 mg extended-release for 1 week, then 75 mg daily. In the 2000 trial (191 women with complete data, 4 weeks of treatment), median hot-flash scores fell 27% on placebo, 37% at 37.5 mg, 61% at 75 mg and 61% at 150 mg — so 150 mg gave no extra benefit over 75 mg, while dry mouth, decreased appetite, nausea and constipation were more common at 75 mg and 150 mg than on placebo.
- Expected benefit: About 60% reduction in hot flash score (number and severity combined) at 75 mg.
- Safe with tamoxifen — minimal cytochrome P450 2D6 inhibition.
- Side effects: Nausea (first 1–2 weeks), dry mouth, decreased appetite, mild blood pressure elevation at doses >150 mg, sexual dysfunction.
- Discontinuation syndrome: Usually tapered over 2–4 weeks. Venlafaxine has a short half-life and missed doses feel unpleasant quickly ("brain zaps").
Escitalopram, Citalopram, and Desvenlafaxine
- Escitalopram 10–20 mg — roughly 50% hot flash reduction; tamoxifen-safe; generally well tolerated.
- Citalopram 10–20 mg — similar efficacy to escitalopram; heart-rhythm (QT interval) prolongation is a concern at doses above 20 mg in older women.
- Desvenlafaxine 100–150 mg — active metabolite of venlafaxine; U.S. Food and Drug Administration-studied specifically for vasomotor symptoms though not U.S. Food and Drug Administration-labeled for them; reasonable alternative for women who had gastrointestinal (GI) side effects on venlafaxine.
If you already have co-existing depression or anxiety, choosing a selective serotonin reuptake inhibitor/serotonin-norepinephrine reuptake inhibitor that treats both at once is elegant — two birds, one daily pill. See the depression article for a broader overview of these drugs.
Gabapentin and Pregabalin — Night-Sweat Specialists
Gabapentin is an anticonvulsant originally developed for seizures and nerve pain. It turns out to blunt hot flashes too, and its sedating side effect is a feature, not a bug, if you take it at bedtime: it simultaneously quiets night sweats and helps you sleep through what is left.
- Dose: Start 300 mg at bedtime for 3 nights. Increase to 600 mg at bedtime if tolerated. Can go up to 900 mg at bedtime or split as 300 mg three times daily (total 900 mg) if daytime flashes remain.
- Expected benefit: 45–70% reduction in hot flash frequency, with disproportionate benefit for night sweats because of the timing and sedation.
- Best candidates: Women whose dominant complaint is drenching 2 a.m. sweats that wreck sleep. The sleep benefit is often the biggest quality-of-life win.
- Side effects: Drowsiness (usually wears off in 1–2 weeks), dizziness on standing, mild weight gain, rarely ankle swelling. In older women, it raises the risk of falls.
- Renal dosing: Gabapentin is cleared by the kidneys. The dose is reduced when estimated glomerular filtration rate (eGFR) is below 60 mL/min.
- Cheap and generic. Typical U.S. cost with a discount card: $5–$15/month.
Pregabalin 75–150 mg at bedtime is similar in mechanism and effect. Slightly better bioavailability than gabapentin, but more expensive (though now generic) and controlled schedule V in the U.S. Some clinicians use it as a second choice when gabapentin is not tolerated; the 2023 North American Menopause Society statement does not recommend pregabalin for hot flashes (Level III).
Clonidine and Oxybutynin
Clonidine 0.1 mg Patch
Clonidine is a central alpha-2 adrenergic agonist originally used for high blood pressure. It reduces hot flashes modestly — about 30–40% reduction — and has fallen out of first-line use since better options appeared. Some clinicians still use it for women who also have mild high blood pressure; the 2023 North American Menopause Society statement does not recommend clonidine for hot flashes (Levels I–III).
- Form: 0.1 mg/24-hour transdermal patch, changed weekly. Oral dosing (0.05–0.1 mg twice daily) also works but causes more dry mouth and rebound hypertension if missed.
- Side effects: Dry mouth, dizziness, drowsiness, rebound hypertension on sudden withdrawal.
Oxybutynin 2.5–5 mg
Oxybutynin is an anticholinergic normally used for overactive bladder. In a 2020 randomized trial (150 women with or without breast cancer, 6 weeks, 2.5 mg or 5 mg twice daily; both doses beat placebo, with more dry mouth, difficulty urinating and abdominal pain) it cut hot flashes by about 60–80% at 5 mg twice daily — a striking result. But there is a serious caveat.
The dementia concern. Chronic anticholinergic exposure has been associated with higher dementia risk in long-term observational studies, particularly in women over 65. The effect seems dose- and duration-dependent. For that reason, clinicians who use oxybutynin for hot flashes describe using it:
- At the lowest dose that works (2.5 mg twice daily first).
- For the shortest duration possible (bridge therapy, a few months to a couple of years, not a 20-year plan).
- In women under 60 rather than women 70+.
- If overactive bladder is also a problem, this is an elegant two-for-one.
Other side effects: dry mouth, constipation, blurred vision, urinary retention. It is not used in people with narrow-angle glaucoma.
Stellate Ganglion Block
A stellate ganglion block is an ultrasound-guided injection of local anesthetic into the stellate ganglion — a cluster of sympathetic nerves at the base of the neck. It is a procedural option, not a drug, and it is performed by pain-medicine or anesthesia specialists.
- What it does: Temporarily silences sympathetic nervous system output above the neck. For reasons that are still being worked out, this dampens the thermoregulatory misfiring that drives hot flashes.
- Expected benefit: In small randomized trials, roughly 50% reduction in moderate-to-severe hot flashes lasting 3–6 months per injection. Some women get 9–12 months.
- Who might consider it: Breast cancer survivors with severe refractory hot flashes who cannot or will not take medication daily, or who have failed multiple oral options.
- Risks: Temporary Horner's syndrome (droopy eyelid, small pupil, flushed face on one side) is common and expected; resolves in hours. Rare serious risks: hoarseness from recurrent laryngeal nerve block, bleeding, nerve injury, pneumothorax, intravascular injection.
- Cost and access: $1,500–$3,000 per procedure; insurance coverage is inconsistent and often requires specific documentation (failed medical therapy, breast cancer context). Not widely available outside academic pain centers.
Cognitive Behavioral Therapy, Mindfulness, and Hypnosis
Cognitive Behavioral Therapy for Menopausal Symptoms (Cognitive Behavioral Therapy-Meno)
This is not generic cognitive behavioral therapy (CBT). Myra Hunter's group in the UK developed a structured 4–6 session protocol that specifically targets the cognitive and behavioral components of hot flashes, night sweats, and mood around menopause. The MENOS trials (MENOS-1, MENOS-2, MENOS-4) consistently show clinically meaningful reductions in hot flash bother — the subjective impact — even when the frequency of flashes changes less.
- Format: Four to six weekly sessions, either individual or group, in-person or via telehealth. Self-help workbooks and apps (such as the NHS-used "Women's Health cognitive behavioral therapy" program) work nearly as well as face-to-face in randomized data.
- What it teaches: Recognizing and reframing catastrophic thoughts during a flash ("everyone is staring, I'm going to faint"), paced breathing at the onset of a flash, sleep hygiene, and behavioral activation for mood.
- Best for: Women who tell their clinician "the flashes aren't even that frequent but they are ruining my life." cognitive behavioral therapy closes the gap between physiology and suffering.
- Combinable: Works alongside every other option on this page and alongside hormone replacement therapy.
Clinical Hypnosis and Mindfulness
Clinical hypnosis (protocols developed by Gary Elkins' group) is one of the options the 2023 North American Menopause Society statement recommends at Level I. In a 2008 trial in 60 breast cancer survivors (51 completed), five weekly hypnosis sessions lowered hot-flash scores (frequency times severity) by 68%, with better anxiety, depression and sleep than in women given no treatment. In a 2013 trial in 187 postmenopausal women in general, five weekly sessions cut reported hot flashes by 74% by week 12, compared with 17% in a structured-attention control group.
Hypnosis at home. A 2025 trial of 250 postmenopausal women (62 of them with a history of breast cancer) tested self-administered hypnosis audio recordings with cooling imagery for 6 weeks against white-noise recordings used the same way (an active sham). Hot-flash scores fell 53.4% with hypnosis and 40.9% with white noise, daily interference from hot flashes fell 49.3% versus 37.4%, and 90.3% versus 64.3% felt they had benefited — a format that needs no therapist visits.
Mindfulness-based stress reduction (MBSR, 8-week group format) is a separate case. Practitioners report that it lessens how much hot flashes bother people more than how often they occur, but the 2023 North American Menopause Society statement lists mindfulness-based intervention as not recommended for hot flashes (Level II). Both hypnosis and mindfulness are safe, have no drug interactions, and layer well with other therapies.
Herbs, Soy, and Supplements
Most over-the-counter menopause supplements have weaker evidence than the pharmaceutical options above, but several are popular and some women report a good response. The 2023 North American Menopause Society statement does not recommend supplements and herbal remedies for hot flashes (Levels I–II), nor soy foods, soy extracts or equol (Level II). Here is a grounded look.
Black Cohosh (Cimicifuga racemosa)
Black cohosh is the most-studied herb for menopause. Trials are mixed — some show modest benefit, others show no difference from placebo. The German Commission E monograph endorsed it for menopausal symptoms, and it remains widely used in Europe as standardized black cohosh extract.
- Typical dose: 40–80 mg of standardized extract daily.
- Expected benefit: Small, around 20–30% reduction in hot flash frequency in responders; no effect in many.
- Liver concern: Rare case reports of hepatotoxicity, probably idiosyncratic. Fatigue, dark urine or right-upper-quadrant pain while taking it are signs of possible liver injury, which liver enzyme tests check for. Existing liver disease raises the concern.
- Mechanism: Not estrogenic in most studies, so theoretically acceptable in breast cancer survivors, but data are thin and guidelines vary.
Soy Isoflavones and S-Equol
Soy isoflavones (genistein, daidzein) are phytoestrogens that bind estrogen receptor beta preferentially. Whole-soy-food diets, including fermented soy foods such as natto, miso and tempeh, appear safer and possibly more effective than concentrated supplements.
- S-equol is a bacterial metabolite of daidzein. Only about 30% of Western women (vs 50–60% of Japanese women) have the gut bacteria to produce it. Direct S-equol supplements (10 mg twice daily) bypass that genetic lottery and have shown modest benefit (around 30% flash reduction) in small trials.
- Breast cancer survivors: Evidence now suggests dietary soy is not harmful and may be modestly protective, but high-dose isolated isoflavone supplements remain a gray area. Whole-food soy is the safer choice.
Options with Weak or No Evidence
- Evening primrose oil — randomized trials show no benefit for hot flashes.
- Red clover — trials are inconsistent; meta-analyses show either no effect or very modest effect. Contains isoflavones similar to soy.
- Vitamin E 400 international units (IU) — a classic Loprinzi trial showed about 1 fewer hot flash per day than placebo. Minimal benefit; at 400 international units the dose is safe for most women but higher doses have been linked to increased all-cause mortality in meta-analyses.
- Dong quai, wild yam cream, maca, ginseng — limited or negative evidence.
See the ashwagandha page for an adaptogen that has better evidence for perimenopausal anxiety and sleep than for hot flashes specifically.
Acupuncture, Cooling Devices, and Weighted Blankets
Acupuncture
Meta-analyses are mixed. The 2016 Acupuncture in Menopause (AIM) trial compared acupuncture with a waitlist, not with sham acupuncture: 209 women aged 45 to 60 received up to 20 treatments either in the first 6 months or (the waitlist group) in the second 6 months. Hot-flash frequency fell 36.7% at 6 months with acupuncture and rose 6.0% in the waitlist group; at 12 months it was still 29.4% below baseline. Improvement appeared after three treatments and peaked after a median of eight. Because AIM had no sham arm, it cannot separate the effect of the needling itself from nonspecific effects, which some researchers argue explain much of the benefit; the 2023 North American Menopause Society statement lists acupuncture as not recommended for hot flashes (Level II). The treatment is safe, many women enjoy it, and the regular ritual itself can reduce menopause-related stress.
Cooling Pillows, Mattress Pads, and Fans
The 2023 North American Menopause Society statement lists cooling techniques as not recommended for treating hot flashes (Level II); the comfort described here is what users report.
- Gel-core cooling pillows: Cheap (~$30), no downside, meaningfully improve the night-sweat wake-up experience.
- Active-cooling mattress pads (~$500–$1,500) — circulate cool water or air under you and drop core temperature during the flash. Many women describe these as life-changing for sleep.
- Bedside fan: cheap, effective, and the sound doubles as a sleep aid.
- Moisture-wicking pajamas (bamboo, merino, technical fabrics) — spare your partner and the mattress.
Weighted Blankets
A paradox — they are warm but also calming. Small sleep studies show modest improvement in insomnia, particularly in women with co-existing anxiety. If your sweats are night-dominant, a weighted blanket may make flashes worse; a cooling pad plus a lighter blanket is a better combination. If your problem is anxiety-driven insomnia more than temperature, a weighted blanket can help.
When to Reopen the Hormone Replacement Therapy Conversation
Many women start non-hormonal therapy convinced that hormone replacement therapy is off the table, then rediscover — after a fair trial — that the symptom relief is not enough to live a full life. That is not a failure; it is data. A reasonable trigger list for revisiting hormone replacement therapy with a clinician:
- Two or more non-hormonal options tried for at least 8–12 weeks each at adequate dose, without acceptable symptom control.
- Sleep is still destroyed — waking more than 3 times per night from sweats after gabapentin and cooling measures.
- Work performance or relationships are suffering.
- Your original reason for avoiding hormone replacement therapy has changed — for example, your breast cancer history is now 5+ years out with no recurrence and your oncologist has softened on vaginal estrogen or even on low-dose systemic therapy.
- Vaginal and urinary symptoms persist. Low-dose vaginal estrogen has minimal systemic absorption and is generally considered safe even in most breast cancer survivors after a conversation with their oncologist.
Non-hormonal therapy and hormone replacement therapy are not mutually exclusive. Some women do best on a low-dose estradiol patch plus gabapentin at night, or on fezolinetant plus vaginal estrogen, or on cognitive behavioral therapy plus a selective serotonin reuptake inhibitor. The goal is the minimum intervention that lets you sleep through the night and get through the day feeling like yourself.
Key Research Papers
- Lederman S, Ottery FD, Cano A, Santoro N, Shapiro M, Stute P, Thurston RC, English M, Franklin C, Lee M, Neal-Perry G. Fezolinetant for treatment of moderate-to-severe vasomotor symptoms associated with menopause (SKYLIGHT 1): a phase 3 randomised controlled study. Lancet. 2023;401(10382):1091–1102. — PubMed PMID: 36924778
- Johnson KA, Martin N, Nappi RE, Neal-Perry G, Shapiro M, Stute P, Thurston RC, Wolfman W, English M, Franklin C, Lee M, Santoro N. Efficacy and safety of fezolinetant in moderate to severe vasomotor symptoms associated with menopause: a phase 3 RCT (SKYLIGHT 2). J Clin Endocrinol Metab. 2023;108(8):1981–1997. — doi:10.1210/clinem/dgad058
- Neal-Perry G, Cano A, Lederman S, Nappi RE, Santoro N, Wolfman W, English M, Franklin C, Valluri U, Ottery FD. Safety of fezolinetant for vasomotor symptoms associated with menopause: a randomized controlled trial (SKYLIGHT 4). Obstet Gynecol. 2023;141(4):737–747. — PubMed PMID: 36897180
- Fezolinetant tablets, U.S. prescribing information (boxed warning for hepatotoxicity added 12/2024; revised 02/2026). DailyMed, U.S. National Library of Medicine. — DailyMed label
- Pinkerton JV, Simon JA, Joffe H, Maki PM, Nappi RE, Panay N, Soares CN, Thurston RC, Caetano C, Haberland C, Haseli Mashhadi N, Krahn U, Mellinger U, Parke S, Seitz C, Zuurman L. Elinzanetant for the treatment of vasomotor symptoms associated with menopause: OASIS 1 and 2 randomized clinical trials. JAMA. 2024;332(16):1343–1354. — PubMed PMID: 39172446
- Cardoso F, Parke S, Brennan DJ, Briggs P, Donders G, Panay N, Haseli-Mashhadi N, Block M, Caetano C, Francuski M, Haberland C, Laapas K, Seitz C, Zuurman L. Elinzanetant for vasomotor symptoms from endocrine therapy for breast cancer. N Engl J Med. 2025;393(8):753–763. — PubMed PMID: 40454634
- Elinzanetant capsules, U.S. prescribing information (initial U.S. approval 2025). DailyMed, U.S. National Library of Medicine. — DailyMed label
- Stearns V, Beebe KL, Iyengar M, Dube E. Paroxetine controlled release in the treatment of menopausal hot flashes: a randomized controlled trial. JAMA. 2003. — doi:10.1001/jama.289.21.2827
- Loprinzi CL, Kugler JW, Sloan JA, et al. Venlafaxine in management of hot flashes in survivors of breast cancer: a randomised controlled trial. Lancet. 2000;356(9247):2059–2063. — PubMed PMID: 11145492
- The 2023 nonhormone therapy position statement of The North American Menopause Society. Menopause. 2023;30(6):573–590. — doi:10.1097/GME.0000000000002200
- Ayers B, Smith M, Hellier J, Mann E, Hunter MS. Effectiveness of group and self-help cognitive behavior therapy in reducing problematic menopausal hot flushes and night sweats (MENOS 2): a randomized controlled trial. Menopause. 2012;19(7):749–759. — PubMed PMID: 22336748
- Leon-Ferre RA, Novotny PJ, Wolfe EG, Faubion SS, Ruddy KJ, Flora D, Dakhil CSR, Rowland KM, Graham ML, Le-Lindqwister N, Smith TJ, Loprinzi CL. Oxybutynin vs placebo for hot flashes in women with or without breast cancer: a randomized, double-blind clinical trial (ACCRU SC-1603). JNCI Cancer Spectr. 2020;4(1):pkz088. — PubMed PMID: 32337497
- Elkins G, Marcus J, Stearns V, Perfect M, Rajab MH, Ruud C, Palamara L, Keith T. Randomized trial of a hypnosis intervention for treatment of hot flashes among breast cancer survivors. J Clin Oncol. 2008;26(31):5022–5026. — PubMed PMID: 18809612
- Elkins GR, Fisher WI, Johnson AK, Carpenter JS, Keith TZ. Clinical hypnosis in the treatment of postmenopausal hot flashes: a randomized controlled trial. Menopause. 2013;20(3):291–298. — PubMed PMID: 23435026
- Elkins G, Arring N, Morgan G, Lorenz T, Muniz V, Lafferty C, Scheffrahn K, Alldredge C, Barton D. Self-administered hypnosis vs sham hypnosis for hot flashes: a randomized clinical trial. JAMA Netw Open. 2025;8(11):e2542537. — PubMed PMID: 41217756
- Avis NE, Coeytaux RR, Isom S, Prevette K, Morgan T. Acupuncture in Menopause (AIM) study: a pragmatic, randomized controlled trial. Menopause. 2016;23(6):626–637. — PubMed PMID: 27023860
PubMed Topic Searches
For current peer-reviewed literature on each option, these PubMed searches return the most relevant recent work:
- Fezolinetant and vasomotor symptoms
- Paroxetine and menopausal hot flashes
- Venlafaxine for hot flashes in breast cancer survivors
- Gabapentin for menopausal night sweats
- Oxybutynin for hot flashes
- Stellate ganglion block for hot flashes
- CBT for menopausal hot flashes (MENOS trials)
- Black cohosh randomized trials in menopause
- Soy isoflavones and S-equol for hot flashes
- Nonhormonal therapy position statements
Connections
- Reproductive Medicine
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Depression
- Ashwagandha
- Genitourinary Syndrome of Menopause and Vaginal Estrogen
- Insomnia
- Micronized Progesterone vs Synthetic Progestins
- Estradiol Formulations: Patch, Gel, Oral Routes
- Hormone Replacement Therapy Risks: Breast Cancer, Clots and Stroke
- Testosterone Therapy for Women
- Vasomotor Symptoms: Hot Flashes and Night Sweats
- Perimenopause Symptom Tracker and Hormonal Testing
- Bone Loss Prevention and Hormone Replacement Therapy
- Perimenopause
- Menopause and Hormone Replacement Therapy
- Black Cohosh
- Anxiety
- Hypertension
- Sleep Hygiene
- Dementia
- Breast Cancer
- Dong Quai (Angelica sinensis) — the “limited or negative evidence” entry above, spelled out: a negative 24-week randomized trial for hot flushes, plus a documented warfarin bleeding interaction