⚠ Evidence warning: Clinical trials or other evidence do not support the claim that black cohosh protects bone or gives a "bonus skeletal benefit" in postmenopausal women: the human evidence is limited to bone-turnover markers measured over about 3 months in small trials, no trial has measured fractures, and a 2012 Cochrane review found too few data to pool any bone-health result. This page keeps it as a report of what people, websites or other media say.
Black Cohosh for Bone Health
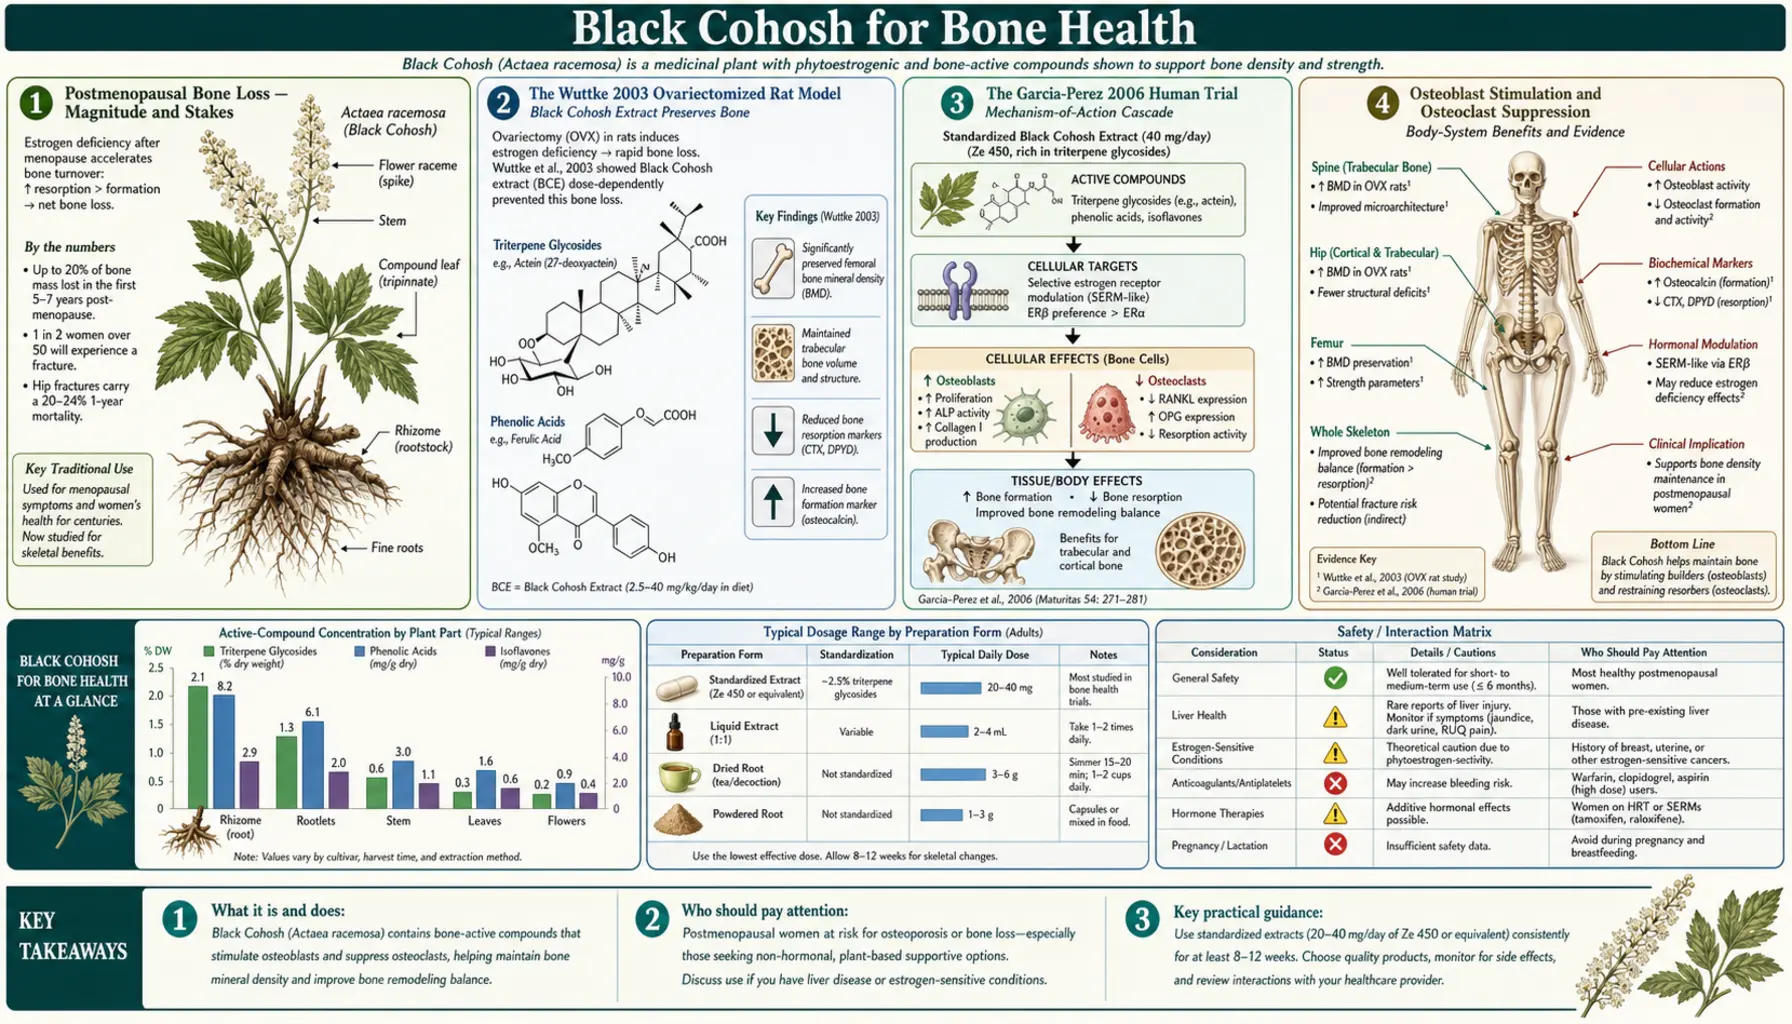
Postmenopausal bone loss is one of the most consequential downstream effects of estrogen withdrawal — women lose 5–10% of bone mineral density in the first five years after menopause and an additional 1–2% per year thereafter, with cumulative consequences for fracture risk in the seventh and eighth decades of life. The evidence on Black Cohosh and bone is modest, and the studies cited here describe it as acting like a selective estrogen-receptor modulator (SERM) — estrogen-like in bone, not in the uterus. In ovariectomized rats (rats with the ovaries removed, a model of menopause), a standardized black cohosh extract significantly reduced the loss of bone mineral density over 3 months. In a 3-month human trial of 62 postmenopausal women (Wuttke 2003), the same extract and 0.6 mg conjugated estrogens a day both showed beneficial effects on bone-turnover markers in the blood, and in the García-Pérez 2009 report, postmenopausal women taking an isopropanolic extract showed a fall in a urinary bone-breakdown marker and a rise in a bone-formation marker at the third month. The proposed mechanism is a direct effect on bone cells: in laboratory studies the extract raised osteoprotegerin, a natural brake on bone breakdown, in human bone-building cells (osteoblasts) through the estrogen receptor, actein stimulated mouse osteoblast cells, and another black cohosh triterpene glycoside blocked the formation of bone-resorbing cells (osteoclasts). Black Cohosh has not been tested as a stand-alone osteoporosis therapy: no trial has tested it against fractures, while bisphosphonates, denosumab, teriparatide and systemic estrogen have fracture-reduction data from large trials. Where it is discussed is as part of a broader bone-protective strategy for women in early-to-mid postmenopause who use it mainly for hot flushes (vasomotor symptoms), with any skeletal benefit described as a bonus.
Table of Contents
- Postmenopausal Bone Loss — Magnitude and Stakes
- The Wuttke 2003 Ovariectomized Rat Model
- The García-Pérez 2009 Human Study
- Osteoblast Stimulation and Osteoclast Suppression
- RANKL/OPG Modulation — Proposed Molecular Mechanism
- Actein as the Putative Bone-Active Triterpene
- Comparison to Hormone Replacement Therapy for Bone Density
- Comparison to Bisphosphonates, Denosumab, Teriparatide
- Clinical Positioning — Supplementary, Not Stand-Alone
- The Comprehensive Bone-Health Stack
- Key Research Papers
- Connections
- Featured Videos
Postmenopausal Bone Loss — Magnitude and Stakes
The skeleton is in constant remodeling throughout adult life, with osteoclasts resorbing existing bone and osteoblasts laying down new bone in a tightly coupled cycle. The cycle is regulated by mechanical loading, parathyroid hormone, calcitonin, vitamin D, calcitriol, and crucially by estrogen. Estrogen acts on both cell types: it suppresses osteoclast formation and accelerates osteoclast apoptosis (reducing resorption), and it supports osteoblast lifespan (preserving formation). With adequate estrogen, the formation-resorption balance is approximately even, and adult bone mass is maintained.
Menopause withdraws this estrogenic brake. Within months of the final menstrual period, bone-resorption markers (urinary CrossLaps, serum C-terminal telopeptide (CTX)) increase by 50–100%, and bone-formation markers (osteocalcin, procollagen type 1 N-terminal propeptide (P1NP)) increase only modestly — the formation/resorption coupling is broken in favor of net resorption. The result is rapid bone loss in the first five years after menopause:
- Lumbar spine: 1–3% loss per year in early postmenopause, decelerating to 0.5–1% per year long-term
- Femoral neck: 0.5–1.5% loss per year, more sustained over time
- Cumulative 30-year loss: 30–50% of premenopausal peak bone mass at the spine in untreated women
The clinical translation is fracture risk. By age 75, approximately 40% of women have experienced an osteoporotic fracture (vertebral, hip, distal radius, or other). Hip fractures specifically carry a 20–30% one-year mortality and result in permanent loss of independence for 50% of survivors. This is the public-health backdrop against which the question "does Black Cohosh protect bone?" matters.
For more on postmenopausal bone disease, see our Perimenopause page and the broader Hormone Panel context.
The Wuttke 2003 Ovariectomized Rat Model
The Wuttke group at the University of Göttingen developed the most-cited animal-model evidence for Black Cohosh's osteoprotective effect, published in Maturitas in 2003 and confirmed in subsequent papers. The model: female Sprague-Dawley rats were ovariectomized to induce a rapid menopausal-equivalent state with measurable bone loss within 4–6 weeks. Animals were then randomized to:
- A standardized black cohosh extract, given in the food, at doses approximating the human therapeutic equivalent
- 17-beta-estradiol at a positive-control dose
- Vehicle placebo
Treatment continued for 3 months, after which bone mineral density of the tibia (by quantitative computed tomography (CT)), bone-turnover markers in the blood (osteocalcin, a bone-formation marker, and CrossLaps, a bone-breakdown marker), uterine wet weight (uterotrophic assay for estrogenicity), and estrogen-regulated genes in the uterus were assessed.
Findings:
- Bone mineral density: Over 3 months, both estradiol and the black cohosh extract significantly reduced the loss of bone mineral density in the tibia (Seidlová-Wuttke 2003, Maturitas). In the companion study in the European Journal of Endocrinology, control rats lost more than 50% of the metaphyseal bone mass of the tibia within 3 months; estradiol prevented this loss, and the black cohosh extract prevented it partially.
- Bone-resorption marker: Only estradiol, not the black cohosh extract, reduced serum CrossLaps.
- Bone-formation marker: Serum osteocalcin was significantly reduced by both treatments.
- Uterine weight: Estradiol produced the expected uterotrophic response (uterine wet weight increased 3-4x). Black Cohosh produced no effect on uterine weight or on estrogen-regulated uterine genes — the pattern of a selective estrogen-receptor modulator (see the Hormonal Balance deep-dive).
The implication: in these rat studies, the black cohosh extract reduced bone loss — significantly in one study, partially in the other, where estradiol prevented it fully — without producing the uterine estrogenic response. The authors concluded that the extract has estrogenic effects in the bone (particularly in osteoblasts) but not in the uterus, and contains substances with selective estrogen-receptor modulator (SERM) activity.
A separate rat study (Nisslein and Freudenstein 2003) gave ovariectomized Sprague-Dawley rats an isopropanolic black cohosh extract in the diet. The extract significantly lowered the urinary bone-breakdown markers pyridinoline and deoxypyridinoline and reduced the bone loss measured by bone-density scans; the reversal of bone loss began 2–5 weeks after treatment started and continued through at least 7 weeks, with results similar in quality and magnitude to raloxifene, a selective estrogen-receptor modulator drug.
The García-Pérez 2009 Human Study
A short human report by García-Pérez and colleagues, published in Fertility and Sterility in 2009, followed postmenopausal women treated with an isopropanolic Black Cohosh extract. Its abstract reports:
- A decrease in the urinary concentration of N-telopeptides, a marker of bone breakdown (resorption), at the third month of therapy.
- An increase in alkaline phosphatase, a marker of bone formation, at the third month of therapy.
- Serum from the treated women, added to the MC3T3-E1 osteoblast cell line in the laboratory, did not change alkaline phosphatase activity or the expression of three bone-building genes (runt-related transcription factor-2 (Runx-2), alkaline phosphatase and osteocalcin).
The two Wuttke trials of a standardized black cohosh extract (62 postmenopausal women, 40 mg of herbal drug a day, compared with 0.6 mg conjugated estrogens a day and placebo for 3 months) add safety observations: the black cohosh extract had no effect on endometrial thickness, which conjugated estrogens significantly increased (2003), and no significant effects were seen on coagulation markers or liver enzymes in the blood (2006).
A 2012 Cochrane review of 16 randomized trials (2,027 perimenopausal or postmenopausal women; median dose 40 mg a day for a mean of 23 weeks) found too few data to pool results for bone health, and no significant difference between black cohosh and placebo in the frequency of hot flushes.
Interpretation: the changes in bone-turnover markers are directionally favorable. The 3-month duration was not long enough to assess change in actual bone mineral density on a dual-energy X-ray absorptiometry (DEXA) scan. Larger and longer trials with bone-density endpoints would be needed to translate the bone-marker findings into a definitive statement about fracture prevention. As of 2026 those trials have not been done — the human bone-density evidence for Black Cohosh remains at the bone-turnover-marker level rather than the DEXA-change or fracture-incidence level.
Osteoblast Stimulation and Osteoclast Suppression
In vitro work has documented direct effects of Black Cohosh triterpene glycosides on the two principal bone cell types:
Osteoblast effects: Normal human osteoblasts exposed to an isopropanolic Black Cohosh extract (Viereck 2005) and mouse MC3T3-E1 osteoblast cells exposed to purified actein (Lee and Choi 2014) showed, in these laboratory studies:
- Increased alkaline phosphatase activity (a marker of osteoblast differentiation)
- Increased osteocalcin gene expression and protein secretion
- Increased collagen synthesis (collagen is the principal bone matrix protein; actein study)
- Increased mineralization (actein study)
Osteoclast effects: Osteoclast precursor cultures exposed to Black Cohosh compounds are reported to show:
- Reduced TRAP (tartrate-resistant acid phosphatase)-positive multinucleated osteoclast formation
- Reduced bone-resorption activity in pit-formation assays
- Reduced cathepsin K and matrix metalloproteinase-9 expression (osteoclast effector enzymes)
The study located for this page on osteoclasts (Qiu 2007) tested one triterpene glycoside isolated from black cohosh, 25-acetylcimigenol xylopyranoside (ACCX): in cell culture it potently blocked osteoclast formation triggered by either RANKL or tumor necrosis factor-alpha (TNF-alpha), by shutting down the NF-kappaB and ERK signaling pathways, and in a live-animal test it reduced TNF-alpha-induced bone loss.
The combination — pro-osteoblast and anti-osteoclast — is the desirable pharmacological profile for a bone-anabolic agent. It resembles the profile of teriparatide (a recombinant parathyroid hormone (PTH) 1-34 fragment that is anabolic) more than that of bisphosphonates (which are purely anti-resorptive). The magnitudes are much smaller than teriparatide, of course, but the mechanism direction is consistent.
RANKL/OPG Modulation — Proposed Molecular Mechanism
The RANKL/OPG/RANK axis is the central molecular regulator of osteoclast biology. RANKL (Receptor Activator of Nuclear Factor kappa-B Ligand) is produced by osteoblasts and stromal cells and binds the RANK receptor on osteoclast precursors, driving their differentiation into mature bone-resorbing osteoclasts. OPG (Osteoprotegerin) is a decoy receptor also produced by osteoblasts that binds RANKL and prevents it from engaging RANK — a brake on osteoclast formation. The RANKL/OPG ratio is the single most important regulator of osteoclast-mediated bone resorption.
The drug denosumab is a fully human monoclonal antibody against RANKL that mimics OPG's decoy function and produces dramatic reduction in bone resorption — one of the most effective osteoporosis therapies available. The clinical effect size of denosumab (68% reduction in vertebral fracture risk, 40% reduction in hip fracture risk at 3 years) demonstrates how powerful RANKL/OPG modulation can be.
In laboratory work with normal human osteoblasts (Viereck 2005), an isopropanolic Black Cohosh extract raised OPG — the body's natural RANKL blocker — 2- to 3-fold in gene activity and protein secretion, and 3- to 5-fold as early as 12 hours. It also raised two bone-building markers, bone-specific alkaline phosphatase (up to 4-fold) and osteocalcin (up to 3-fold). RANKL itself was expressed at very low levels and was not changed by the extract, so the OPG-to-RANKL ratio rose through the OPG side. The OPG effect disappeared when the estrogen receptor was blocked with the pure estrogen-receptor antagonist ICI 182,780 — so this effect runs through the estrogen receptor. A different black cohosh triterpene glycoside blocked RANKL-driven osteoclast formation in cell culture (Qiu 2007, above). The molecular mechanism is not fully worked out but appears to involve effects on the canonical Wnt/beta-catenin pathway in osteoblasts and possibly direct effects on NF-kappa-B signaling in osteoclast precursors.
The clinical magnitudes are not in the same league as denosumab — a rise in OPG in cultured cells is not the near-complete RANKL blockade that denosumab achieves — but the directional consistency with one of the most effective bone drugs ever developed lends mechanistic plausibility to the modest clinical signal.
Actein as the Putative Bone-Active Triterpene
Among the dozen-plus triterpene glycosides in Black Cohosh extract, actein has emerged as the most-studied for bone-related effects. In the actein study located for this page (Lee and Choi 2014, a laboratory study), purified actein raised alkaline phosphatase activity, collagen synthesis, osteocalcin production and mineralization in mouse MC3T3-E1 osteoblast cells; the OPG and osteoclast findings above come from other black cohosh preparations, not from actein.
Actein is also the most abundant triterpene in authenticated Actaea racemosa rhizome (typically 0.1–0.5% of dried rhizome by high-performance liquid chromatography (HPLC) quantification) and is used as a quantitative marker for extract standardization. The 23-epi-26-deoxyactein closely related congener has similar in vitro activity. The other triterpenes (cimicifugoside, cimiracemoside variants) have less-studied bone-relevant profiles but probably contribute additively.
Outside bone biology, actein has been investigated for direct anti-cancer effects (breast cancer cell-cycle arrest, pancreatic cancer apoptosis induction) and for hepatoprotective and hepatotoxic effects in different model systems — an unresolved puzzle that may be relevant to the rare clinical hepatotoxicity signal. The hepatotoxicity question is covered in detail on the Benefits hub Hepatotoxicity section.
Comparison to Hormone Replacement Therapy for Bone Density
Systemic estrogen is one of the most effective bone-preservation therapies available — the Women's Health Initiative documented a 33% reduction in hip fractures and a 34% reduction in vertebral fractures with conjugated estrogens plus medroxyprogesterone acetate. The effect size is comparable to the best bisphosphonates and to denosumab. Even low-dose estrogen (0.3 mg conjugated estrogens or 0.025 mg transdermal estradiol) produces measurable bone preservation.
In head-to-head comparison with 0.6 mg conjugated estrogens a day, the Wuttke trials found beneficial effects of both on bone-turnover markers: the 2003 report described the black cohosh extract's effect on bone metabolism as equipotent to the estrogen, and the 2006 report (62 women, 12 weeks) found a different pattern — black cohosh stimulated bone-forming (osteoblast) activity, whereas conjugated estrogens inhibited bone-resorbing (osteoclast) activity. The García-Pérez 2009 abstract describes no comparison group. The clinical translation to fracture risk is unknown because no Black Cohosh trial has been powered for or has duration to assess fracture outcomes.
For a woman in early postmenopause who needs both vasomotor-symptom relief and bone preservation, low-dose systemic estrogen does both more effectively than Black Cohosh. The case for Black Cohosh in this context is limited to women for whom estrogen is contraindicated or undesired, where Black Cohosh provides some bone-protective benefit as a bonus on top of its primary vasomotor-symptom effect.
Comparison to Bisphosphonates, Denosumab, Teriparatide
For women with established osteoporosis (T-score < −2.5 on DEXA) or with osteopenia and high fracture risk by Fracture Risk Assessment Tool (FRAX) score, no trial has tested black cohosh against fractures; the drugs below have fracture-reduction data from large trials. The comparison:
- Bisphosphonates (alendronate, risedronate, zoledronic acid): 40–50% reduction in vertebral fracture risk, 20–40% reduction in hip fracture risk at 3–5 years. Strong evidence base across hundreds of thousands of patient-years. First-line therapy for postmenopausal osteoporosis.
- Denosumab: 68% reduction in vertebral fractures, 40% in hip fractures (FREEDOM trial). Subcutaneous injection every 6 months. First-line for high-risk patients and for patients with renal impairment that contraindicates bisphosphonates.
- Teriparatide and abaloparatide: Bone-anabolic agents (rather than anti-resorptive) producing genuine increase in bone density. Reserved for severe osteoporosis or post-fracture. Daily subcutaneous injection.
- Romosozumab: Sclerostin antibody, dual anabolic and anti-resorptive. Most-recent addition to the osteoporosis armamentarium.
- Systemic estrogen: 30–35% reduction in both vertebral and hip fractures, with the breast-cancer and thromboembolic risks attached.
- Black Cohosh: Modest changes in bone-turnover markers; no fracture-endpoint data. Effect size at most 10–20% of any of the above pharmaceutical options.
The clinical translation: with no fracture data, Black Cohosh has not been shown to fill the role of osteoporosis therapy.
Clinical Positioning — Supplementary, Not Stand-Alone
In the research described above, Black Cohosh appears as a possible supplementary contributor in a broader bone-protective strategy, not as a primary therapy:
- Context studied: The human bone-marker trials enrolled postmenopausal women taking Black Cohosh at 40 mg/day, a dose studied mainly for vasomotor symptoms; any modest bone-protective effect is described as a bonus on top of the symptom benefit.
- Not tested as stand-alone osteoporosis therapy: For established osteopenia/osteoporosis with elevated fracture risk, the treatments with fracture-reduction data are the drugs above; Black Cohosh has no fracture data.
- The foundational bone-health stack: The factors usually listed alongside it are dietary protein, calcium intake (1,000–1,200 mg/day, with food sources often described as preferable to supplements), vitamin D status (serum 25-hydroxyvitamin D (25-OH-D) of 30–50 ng/mL is a commonly cited range), vitamin K2 (especially menaquinone-7, MK-7), weight-bearing exercise (resistance training, walking, jumping), and not smoking or drinking alcohol heavily.
- Monitoring: Black Cohosh use does not change standard postmenopausal bone-health monitoring, which typically involves a baseline DEXA scan at around age 60–65 in most women (earlier with risk factors) and a repeat scan every 2 years if abnormal or if on bone-active therapy. Bone-turnover markers (CTX, P1NP) are used clinically to assess response to anti-resorptive therapy at 3–6 months.
A 2026 systematic review written to inform the International Menopause Society's recommendations (Maunder and colleagues, 158 studies) found moderate-certainty evidence for black cohosh for hot flushes and menopausal symptom scores. Its abstract does not list bone health among black cohosh's outcomes; the bone-related outcome with moderate-certainty evidence was vitamin D for fracture risk.
The Comprehensive Bone-Health Stack
Bone protection after menopause is usually described as a broader stack, in which Black Cohosh would be one item:
- Protein intake — 1.0–1.2 g/kg body weight daily, spread across meals, is a commonly cited range. Protein deficiency is a common under-recognized contributor to postmenopausal bone loss.
- Calcium — 1,000–1,200 mg/day total intake is the usual reference range; food sources include dairy, sardines with bones, kale and broccoli. Calcium supplements above 500 mg per dose are poorly absorbed, and some studies report a cardiovascular safety signal with high-dose supplements, which is why food sources are often described as preferable.
- Vitamin D3 — sufficient to maintain serum 25-OH-D between 30 and 50 ng/mL. Intakes of 1,000–2,000 international units (IU)/day are commonly described for maintenance, with higher loading doses used for deficiency. See our Vitamin D3 page.
- Vitamin K2 — particularly menaquinone-7 (MK-7), commonly described at 100–200 mcg/day. K2 activates osteocalcin (which then binds calcium into the bone matrix) and matrix Gla protein (which inhibits arterial calcification). See our Vitamin K page.
- Magnesium — 300–400 mg/day is the usual reference range; magnesium is a necessary cofactor for vitamin D activation and bone-matrix mineralization.
- Boron — commonly described at 3–6 mg/day; reported to support bone health and proposed to reduce vasomotor symptoms.
- Weight-bearing exercise — often described as the most important non-pharmaceutical factor; programs described include resistance training 2–3 days/week, walking 30–60 minutes most days, and jumping or impact exercise where joints permit.
- Smoking, excessive alcohol, chronic high-dose acid-suppression therapy — all are linked with faster bone loss.
- Black Cohosh 40 mg/day — the dose used in the trials; when it is used for vasomotor symptoms, any modest bone-supportive effect is described as a bonus.
- Pharmaceutical osteoporosis therapy — for established osteopenia/osteoporosis, the bisphosphonates, denosumab, or anabolic agents discussed above.
The point is that bone health is a multi-input problem with no single dominant intervention. Black Cohosh is one of the smaller inputs in this list but is not negligible if a woman is taking it anyway.
Key Research Papers
- Wuttke W, Seidlová-Wuttke D, Gorkow C (2003). The Cimicifuga preparation BNO 1055 vs. conjugated estrogens in a double-blind placebo-controlled study: effects on menopause symptoms and bone markers. Maturitas 44 Suppl 1:S67-77. — PubMed PMID: 12609561
- Wuttke W, Gorkow C, Seidlová-Wuttke D (2006). Effects of black cohosh (Cimicifuga racemosa) on bone turnover, vaginal mucosa, and various blood parameters in postmenopausal women: a double-blind, placebo-controlled, and conjugated estrogens-controlled study. Menopause 13(2):185-96. — PubMed PMID: 16645532
- García-Pérez MA, Pineda B, Hermenegildo C et al. (2009). Isopropanolic Cimicifuga racemosa is favorable on bone markers but neutral on an osteoblastic cell line. Fertility and Sterility 91(4 Suppl):1347-50. — PubMed PMID: 18555220
- Seidlová-Wuttke D, Jarry H, Becker T et al. (2003). Pharmacology of Cimicifuga racemosa extract BNO 1055 in rats: bone, fat and uterus. Maturitas 44 Suppl 1:S39-50. — PubMed PMID: 12609558
- Seidlova-Wuttke D, Hesse O, Jarry H et al. (2003). Evidence for selective estrogen receptor modulator activity in a black cohosh (Cimicifuga racemosa) extract: comparison with estradiol-17beta. European Journal of Endocrinology 149(4):351-62. — PubMed PMID: 14514351
- Nisslein T, Freudenstein J (2003). Effects of an isopropanolic extract of Cimicifuga racemosa on urinary crosslinks and other parameters of bone quality in an ovariectomized rat model of osteoporosis. Journal of Bone and Mineral Metabolism 21(6):370-6. — PubMed PMID: 14586793
- Viereck V, Gründker C, Friess SC et al. (2005). Isopropanolic extract of black cohosh stimulates osteoprotegerin production by human osteoblasts. Journal of Bone and Mineral Research 20(11):2036-43. — PubMed PMID: 16234977
- Qiu SX, Dan C, Ding LS et al. (2007). A triterpene glycoside from black cohosh that inhibits osteoclastogenesis by modulating RANKL and TNFalpha signaling pathways. Chemistry & Biology 14(7):860-9. — PubMed PMID: 17656322
- Lee YS, Choi EM (2014). Actein isolated from black cohosh promotes the function of osteoblastic MC3T3-E1 cells. Journal of Medicinal Food 17(4):414-23. — PubMed PMID: 24552231
- Beck V, Rohr U, Jungbauer A (2005). Phytoestrogens derived from red clover: an alternative to estrogen replacement therapy? Journal of Steroid Biochemistry and Molecular Biology 94(5):499-518. — PubMed PMID: 15876415
- Cassidy A, Albertazzi P, Lise Nielsen I et al. (2006). Critical review of health effects of soyabean phyto-oestrogens in post-menopausal women. Proceedings of the Nutrition Society 65(1):76-92. — PubMed PMID: 16441947
- Cummings SR, San Martin J, McClung MR et al. (2009). Denosumab for prevention of fractures in postmenopausal women with osteoporosis (FREEDOM trial). New England Journal of Medicine 361(8):756-65. — PubMed PMID: 19671655
- Leach MJ, Moore V (2012). Black cohosh (Cimicifuga spp.) for menopausal symptoms. Cochrane Database of Systematic Reviews 2012(9):CD007244. — PubMed PMID: 22972105
- Maunder A, Mardon AK, Rao V et al. (2026). Complementary therapies for management of menopausal symptoms: a systematic review to inform the update of the International Menopause Society recommendations on women's midlife health. Climacteric 29(2):165-209. — PubMed PMID: 41498229
PubMed Topic Searches
Connections
- All Herbs
- Black Cohosh Overview
- Black Cohosh Benefits Hub
- Black Cohosh for Menopause & Hot Flashes
- Black Cohosh for Hormonal Balance
- Black Cohosh for Mood & Sleep
- Vitamin D3 (Bone Stack)
- Vitamin K2 (Bone Stack)
- Magnesium (Bone Stack)
- Calcium
- Boron
- Perimenopause
- Hormone Panel
- Maca
- Ashwagandha
- Osteoporosis — the condition Black Cohosh may support but cannot treat on its own.
- History