⚠ Evidence warning: Clinical trials or other evidence do not support the claims that black cohosh is not estrogenic at all, does not bind estrogen receptors or stimulate breast tissue, and can be used safely with periodic monitoring by people with normal baseline liver function. This page keeps it as a report of what people, websites or other media say.
Black Cohosh — Benefits Deep Dive
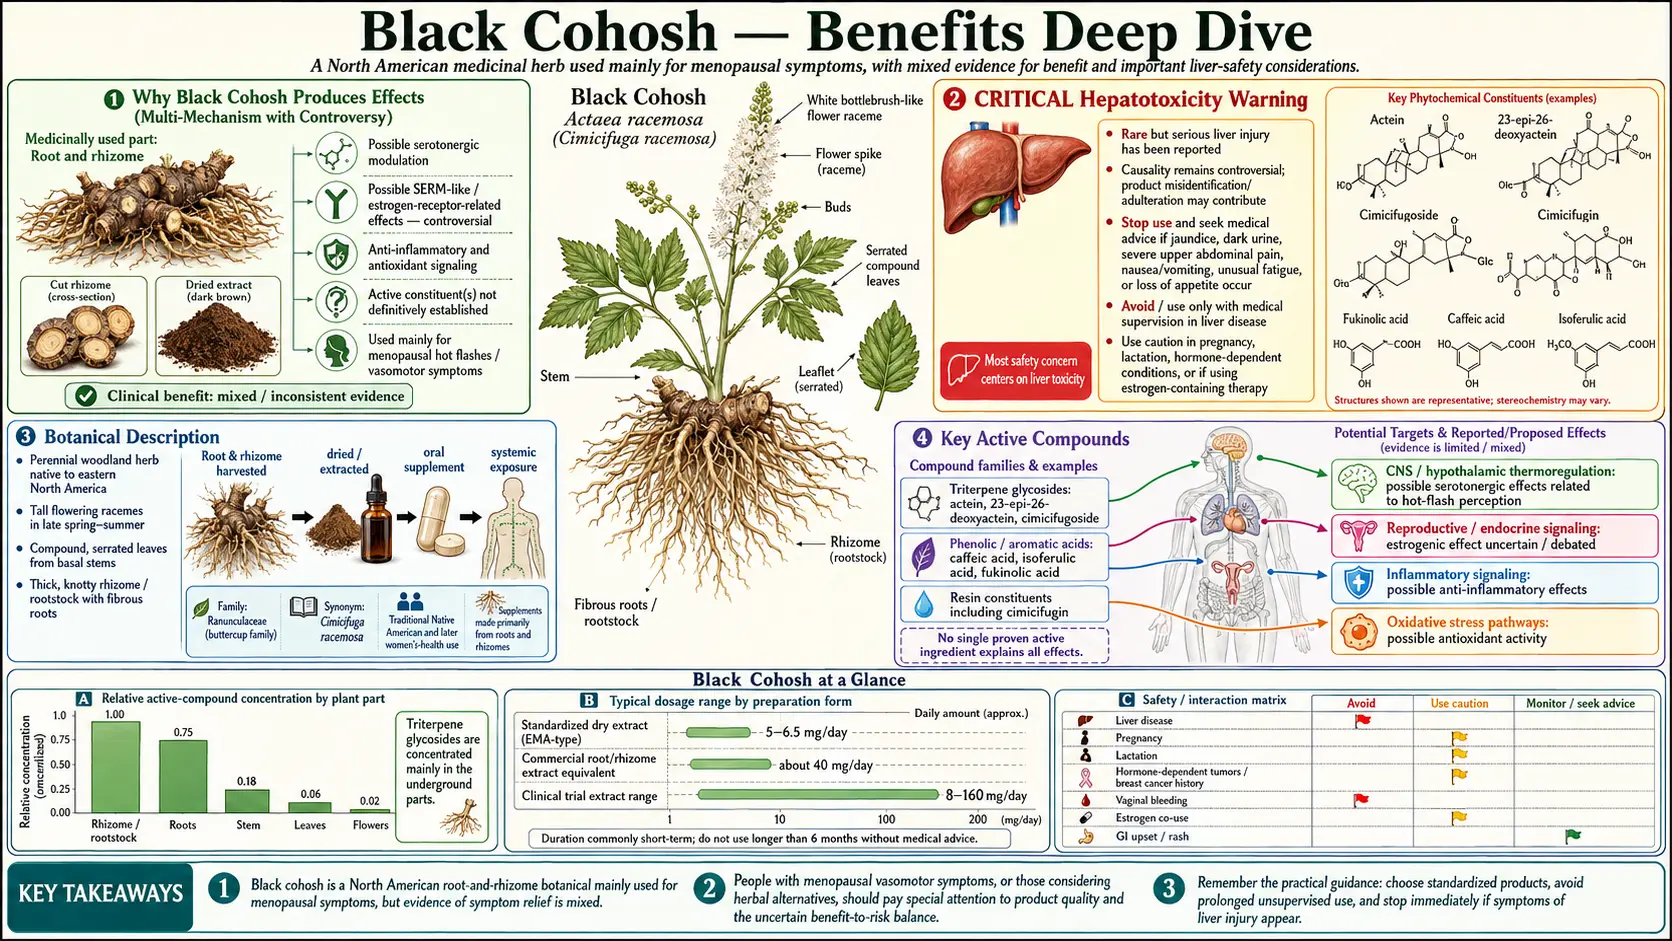
Black Cohosh (Actaea racemosa, formerly Cimicifuga racemosa) is a North American woodland perennial whose dark, gnarled rhizome was used for centuries by Native American peoples — the Cherokee, Iroquois, Algonquian, and Penobscot — for "female complaints," rheumatism, and as a parturient. Nineteenth-century Eclectic physicians adopted it under the common name "squaw root" or "black snakeroot." Modern phytochemistry has identified the dominant active constituents as triterpene glycosides (actein, 23-epi-26-deoxyactein, cimiracemoside, cimicifugoside) along with cinnamic-acid esters and small amounts of formononetin. For nearly a century the herb was assumed to be a phytoestrogen, but studies after 2002 have found little or no classic estrogenic action — in rats an extract did not increase uterine weight (Burdette 2003), and in women it did not thicken the womb lining (Wuttke 2003) — although the same human trial found a weak estrogen-like effect on the vaginal lining, and its authors proposed a selective, SERM-like (selective estrogen receptor modulator) action. Rigorous receptor-binding and microarray studies after 2002 have established that it is NOT estrogenic — it does not bind estrogen receptor alpha (ER-alpha) or estrogen receptor beta (ER-beta), does not stimulate estrogen-responsive breast tissue, and does not induce uterine proliferation. The proposed mechanisms are serotonergic, dopaminergic, GABAergic, and opioid-receptor effects; in laboratory work the serotonin activity traced mainly to a serotonin-like compound in the root, N-omega-methylserotonin, rather than to the triterpene glycosides (Powell 2008). Black Cohosh is one of the most-studied herbs in the world for menopausal symptoms: the Wuttke 2003 trial of the extract BNO 1055 (40 mg of herb a day, 62 women, 3 months) found it as effective as 0.6 mg conjugated estrogens and better than placebo on the Menopause Rating Scale, while the 2012 Cochrane review of 16 trials found no difference from placebo for hot flushes. Four benefit pages below cover the clinical evidence, the mechanism controversy, the bone-density signal, and the perimenopausal mood/sleep applications.
Deep-Dive Articles
Menopause & Hot Flashes
The Wuttke 2003 BNO 1055 trial comparing a black cohosh extract to 0.6 mg conjugated estrogens, the Cochrane 2012 mixed-evidence review, the canonical 40 mg/day standardized iso-propanolic extract dose, the 8–12 week response timeline (most patients see benefit by week 4), comparison to hormone replacement therapy (HRT) for women with breast-cancer history, and why the trial-to-trial heterogeneity exists (extract standardization, placebo response, study population).
Read the deep dive →Hormonal Balance (Non-Estrogenic Mechanism)
Why the long-assumed phytoestrogen label is wrong, the Burdette 2003 rat and serotonin-receptor study that found no estrogenic effect, extract binding to serotonin 5-HT7 and 5-HT1A receptors, dopamine D2 modulation, mu-opioid receptor engagement, the absence of effect on follicle-stimulating hormone (FSH)/luteinizing hormone (LH)/estradiol/prolactin, and the practical implication for women with estrogen-sensitive breast cancer history.
Read the deep dive →Bone Health
Postmenopausal bone data from the Wuttke 2003 ovariectomized-rat model and the García-Pérez 2009 human bone-marker study, comparison to estradiol's osteoprotective effect, the proposed actein-mediated osteoblast stimulation and osteoclast suppression mechanism, RANKL/OPG modulation, and the clinical reality that Black Cohosh is supplementary — not a stand-alone osteoporosis therapy.
Read the deep dive →Mood & Sleep
Perimenopausal mood swings and anxiety, the Liske 2002 two-dose study (Kupperman Menopause Index and Self-Rating Depression Scale, no placebo group), traditional Native American (Cherokee, Iroquois) use as a parturient and nervine, the serotonergic and GABAergic mechanism behind the mood effect, sleep-architecture improvements in vasomotor-symptom-driven insomnia, and combination protocols with St. John's Wort for moderate depression in perimenopause.
Read the deep dive →Table of Contents
Why Black Cohosh Produces Effects (Multi-Mechanism with Controversy)
Most herbal therapies for menopausal symptoms (red clover, soy isoflavones, hops) are phytoestrogens — plant compounds that bind weakly to estrogen receptors and produce a partial-agonist effect. Black Cohosh is the conspicuous exception. For most of the 20th century it was assumed to belong to the same category, but a series of receptor-binding and gene-expression studies after 2002 largely dismantled that assumption. The proposed alternatives involve at least four distinct non-estrogenic pathways.
- Serotonergic activity — black cohosh extracts bind serotonin 5-HT1A, 5-HT1D and 5-HT7 receptors and act as a partial agonist at 5-HT7 (Burdette 2003, laboratory and rat study). A follow-up laboratory study found the triterpenoids themselves bound only weakly to 5-HT7, and identified N-omega-methylserotonin as the likely source of the serotonin activity (Powell 2008). The 5-HT7 binding is proposed to explain the thermoregulatory effect on hot flashes, because the 5-HT7 receptor in the hypothalamic preoptic area is centrally involved in core-temperature setpoint regulation. The 5-HT1A binding contributes to anxiolytic and mood-stabilizing effects, similar in pathway (though weaker in magnitude) to buspirone. See the Mood & Sleep deep-dive for the clinical applications.
- Dopaminergic modulation — in vitro studies show triterpene-glycoside affinity for dopamine D2 receptors. The D2 effect may explain the observation that Black Cohosh occasionally lowers prolactin in women with mild hyperprolactinemia, and may contribute to mood and vasomotor effects via the tubero-infundibular pathway.
- Opioid-receptor engagement — in 2008, a US study (Reame and colleagues) gave postmenopausal women a standardized isopropanolic black cohosh extract, 40 mg a day, for 12 weeks without blinding. Brain scans (positron emission tomography) in 5 women showed mu-opioid receptor binding 10–61% higher in brain regions involved in emotion and thinking, and a naloxone challenge in 6 women changed the pattern of luteinizing hormone pulses. It is a tiny, unblinded study, but it points to an action on the brain's own opioid system. Opioid signaling in the hypothalamus modulates the luteinizing hormone/follicle-stimulating hormone pulse generator and is implicated in hot-flash generation through the KNDy (kisspeptin/neurokinin B/dynorphin) neuron system that has emerged as the central thermoregulatory player in menopause.
- Bone-protective effects — actein and related triterpenes appear to stimulate osteoblast activity and suppress osteoclast differentiation in vitro and in ovariectomized rat models. The mechanism is independent of estrogen receptors and may involve RANKL/OPG modulation. The clinical magnitude is smaller than estradiol but measurable. See the Bone Health deep-dive.
The controversy — and there is genuine controversy — arises from two facts. First, the older literature (pre-2002) is full of papers describing Black Cohosh as estrogenic, and these claims are repeated uncritically in textbooks and consumer-facing materials decades after they have been overturned by careful receptor-binding and microarray studies. In ovariectomized rats, a black cohosh extract did not increase uterine weight or vaginal cornification, alone or with estradiol (Burdette 2003). In women, the Wuttke 2003 trial found no thickening of the womb lining, though vaginal surface cells increased, and its authors proposed that the extract contains compounds with SERM activity; a 2006 report from the same trial described a weak estrogen-like effect on the vaginal lining. Black Cohosh extract did not bind ER-alpha or ER-beta in radioligand-binding assays, did not stimulate estrogen-response-element-luciferase reporter constructs, did not stimulate MCF-7 breast-cancer cell proliferation, and did not produce uterotrophic effects in ovariectomized rats, and Black Cohosh is classified as non-estrogenic. Second, the clinical-trial evidence for symptom relief is genuinely mixed. Some trials showed no benefit over placebo: the Herbal Alternatives for Menopause trial (HALT, published as Newton 2006; 351 women, black cohosh 160 mg a day) found no difference from placebo at 3, 6 or 12 months, and in Frei-Kleiner 2005 (122 women, 12 weeks) the main analysis showed no superiority over placebo — only the women with at least moderate symptoms (Kupperman Index 20 or more) improved more (47% against 21%). The Wuttke 2003 trial (also reported in 2006) found the extract as effective as conjugated estrogens and better than placebo. A 2008 systematic review of 6 trials with 1,112 women (Borrelli and Ernst, Pharmacological Research) found the trials did not consistently show an effect and called efficacy uncertain. The plausible explanation offered for the mixed results is extract heterogeneity — the standardized European extracts used in the positive trials (an isopropanolic extract and the BNO 1055 preparation) are not pharmaceutically equivalent to the various ethanolic, methanolic, and CO2 extracts marketed in North America. See the Menopause & Hot Flashes deep-dive for the trial-by-trial breakdown.
The largest pooled review is the 2012 Cochrane review (Leach and Moore): 16 randomized trials with 2,027 women, at a median dose of 40 mg a day for an average of 23 weeks. It found no difference between black cohosh and placebo in daily hot flushes (3 trials, 393 women) or in menopause symptom scores (4 trials, 357 women), while hormone therapy reduced hot flushes and symptom scores more than black cohosh. Its authors concluded that there is currently insufficient evidence to support black cohosh for menopausal symptoms, and that further, better-reported trials are justified.
The North American Menopause Society's 2023 position statement on non-hormone treatments for hot flashes lists supplements and herbal remedies, black cohosh among them, as “not recommended” (Levels I–II evidence). The options it does recommend include cognitive-behavioral therapy, clinical hypnosis, the antidepressant classes SSRIs and SNRIs (selective serotonin or serotonin-norepinephrine reuptake inhibitors), gabapentin and fezolinetant, and it names hormone therapy as the most effective treatment for hot flashes.
CRITICAL Hepatotoxicity Warning
REGULATORY WARNING: The U.S. Food and Drug Administration, the European Medicines Agency (EMA), and the Australian Therapeutic Goods Administration have all issued warnings since 2006 about rare cases of idiosyncratic liver injury associated with Black Cohosh use. European Medicines Agency-required labeling on all Black Cohosh products in the European Union states: "Black cohosh may cause liver damage. Take medical advice if signs and symptoms suggestive of liver injury (tiredness, loss of appetite, yellowing of the skin and eyes or severe upper stomach pain with nausea and vomiting or dark urine) develop. Stop taking Black cohosh immediately and consult a doctor."
The hepatotoxicity question has been studied extensively in the two decades since the first case reports emerged. Several points are well-established:
- The events are real but very rare. Case reports of suspected Black Cohosh liver injury have been published since the early 2000s, against an estimated population exposure of tens of millions of women-years of use. At trial level, a 2011 meta-analysis (Naser and colleagues) of 5 randomized, double-blind trials of an isopropanolic black cohosh extract (1,117 women aged 40–60, 40–128 mg a day for 3–6 months) found no change in the liver enzymes aspartate aminotransferase (AST), alanine aminotransferase (ALT) or gamma-glutamyl transferase (GGT) compared with control groups — a reassuring trial-level result that sits alongside the case reports. The Teschke 2011 expert RUCAM (Roussel Uclaf Causality Assessment Method) analysis of reported cases found that only a minority met the threshold for "probable" causation; many had confounders (concomitant hepatotoxic drugs, pre-existing liver disease, contaminated or adulterated product).
- The mechanism is idiosyncratic, not dose-related. Unlike acetaminophen hepatotoxicity, the Black Cohosh signal does not correlate with dose or duration. This is the hallmark of an idiosyncratic immune-mediated drug-induced liver injury (DILI), typically involving a genetic-susceptibility component. The estimated incidence is on the order of one to a few per million users per year — rare in absolute terms, comparable to the idiosyncratic DILI rate for many prescription drugs that remain on the market.
- Black cohosh is on the short list of botanicals most often reported in herbal liver injury. A 2024 analysis of the US National Health and Nutrition Examination Survey (NHANES, 2017 to March 2020; Likhitsup and colleagues) named turmeric, green tea extract, Garcinia cambogia, black cohosh, red yeast rice and ashwagandha as the most frequently reported liver-toxic botanicals, and estimated that about 15.6 million US adults had used at least one of the six in the past 30 days; 19 of the 9,685 adults surveyed reported black cohosh.
- Product quality matters. A significant fraction of "Black Cohosh" products marketed in North America have been shown by high-performance liquid chromatography (HPLC) and DNA-barcoding analysis to be adulterated with related but distinct Asian Cimicifuga species (C. dahurica, C. foetida, C. heracleifolia) which have different triterpene profiles and may carry different hepatotoxicity risk. Authenticated Actaea racemosa in the standardized isopropanolic extract has the longest safety record.
Safety facts and monitoring practice:
- Baseline liver function tests (LFTs) are commonly taken before starting in women with any prior history of liver disease, current alcohol use, statin use, or other potentially liver-toxic medications.
- Repeat LFTs at 6 months and every 6–12 months thereafter are a monitoring schedule some clinicians use for women continuing beyond 6 months. The 6-month checkpoint is recommended by the German Commission E monograph and adopted by most quality clinicians.
- Pre-existing liver disease is listed as a contraindication — hepatitis B or C, autoimmune hepatitis, non-alcoholic steatohepatitis (NASH), alcoholic liver disease, primary biliary cholangitis, cirrhosis of any cause.
- Other liver-toxic drugs and herbs taken at the same time — high-dose acetaminophen, methotrexate, isoniazid, ketoconazole, kava kava — add to the load on the liver.
- Warning signs of liver injury are dark urine, jaundice (yellow skin or eyes), pain under the right ribs, unusual tiredness, loss of appetite and nausea; hospitals treat these as urgent, and the EU label quoted above tells users to stop the herb immediately if they appear.
- Product identity matters — the standardized isopropanolic extract has been the most-studied and has the cleanest safety record. No-name bulk powders and products whose label does not specify Actaea racemosa from North American sourcing carry the adulteration risk described above.
The bottom line: the hepatotoxicity risk is real but small, the regulatory warnings are appropriate, and in randomized trials of the isopropanolic extract liver enzymes did not change (Naser 2011). Informed patients with normal baseline liver function can use Black Cohosh safely with periodic monitoring. The media coverage in 2006–2010 substantially overstated the population risk — estimates from that era suggested the per-user risk is comparable to or lower than the hepatotoxicity risk from common prescription medications that are not subject to the same warnings.
Key Research Papers
- Wuttke W, Seidlová-Wuttke D, Gorkow C (2003). The Cimicifuga preparation BNO 1055 vs. conjugated estrogens in a double-blind placebo-controlled study: effects on menopause symptoms and bone markers. Maturitas 44 Suppl 1:S67-77. — PubMed PMID: 12609561
- Burdette JE, Liu J, Chen SN et al. (2003). Black cohosh acts as a mixed competitive ligand and partial agonist of the serotonin receptor. Journal of Agricultural and Food Chemistry 51(19):5661-70. — PubMed PMID: 12952416
- Liske E, Hänggi W, Henneicke-von Zepelin HH et al. (2002). Physiological investigation of a unique extract of black cohosh (Cimicifugae racemosae rhizoma): a 6-month clinical study demonstrates no systemic estrogenic effect. Journal of Women's Health and Gender-Based Medicine 11(2):163-74. — PubMed PMID: 11975864
- Leach MJ, Moore V (2012). Black cohosh (Cimicifuga spp.) for menopausal symptoms. Cochrane Database of Systematic Reviews 9:CD007244. — PubMed PMID: 22972105
- Naser B, Schnitker J, Minkin MJ et al. (2011). Suspected black cohosh hepatotoxicity: no evidence by meta-analysis of randomized controlled clinical trials for isopropanolic black cohosh extract. Menopause 18(4):366-75. — PubMed PMID: 21228727
- Wuttke W, Gorkow C, Seidlová-Wuttke D (2006). Effects of black cohosh (Cimicifuga racemosa) on bone turnover, vaginal mucosa, and various blood parameters in postmenopausal women: a double-blind, placebo-controlled, and conjugated estrogens-controlled study. Menopause 13(2):185-96. — PubMed PMID: 16645532
- Powell SL, Gödecke T, Nikolic D et al. (2008). In vitro serotonergic activity of black cohosh and identification of N(omega)-methylserotonin as a potential active constituent. Journal of Agricultural and Food Chemistry 56(24):11718-26. — PubMed PMID: 19049296
- Reame NE, Lukacs JL, Padmanabhan V et al. (2008). Black cohosh has central opioid activity in postmenopausal women: evidence from naloxone blockade and positron emission tomography neuroimaging. Menopause 15(5):832-40. — PubMed PMID: 18521048
- Newton KM, Reed SD, LaCroix AZ et al. (2006). Treatment of vasomotor symptoms of menopause with black cohosh, multibotanicals, soy, hormone therapy, or placebo: a randomized trial. Annals of Internal Medicine 145(12):869-79. — PubMed PMID: 17179056
- Frei-Kleiner S, Schaffner W, Rahlfs VW et al. (2005). Cimicifuga racemosa dried ethanolic extract in menopausal disorders: a double-blind placebo-controlled clinical trial. Maturitas 51(4):397-404. — PubMed PMID: 16039414
- Borrelli F, Ernst E (2008). Black cohosh (Cimicifuga racemosa) for menopausal symptoms: a systematic review of its efficacy. Pharmacological Research 58(1):8-14. — PubMed PMID: 18585461
- The North American Menopause Society (2023). The 2023 nonhormone therapy position statement of The North American Menopause Society. Menopause 30(6):573-590. — PubMed PMID: 37252752
- García-Pérez MA, Pineda B, Hermenegildo C et al. (2009). Isopropanolic Cimicifuga racemosa is favorable on bone markers but neutral on an osteoblastic cell line. Fertility and Sterility 91(4 Suppl):1347-50. — PubMed PMID: 18555220
- Likhitsup A, Chen VL, Fontana RJ (2024). Estimated Exposure to 6 Potentially Hepatotoxic Botanicals in US Adults. JAMA Network Open 7(8):e2425822. — PubMed PMID: 39102266
External Authoritative Resources
- U.S. National Institutes of Health (NIH) National Center for Complementary and Integrative Health — Black Cohosh — the U.S. government's primary patient-facing summary; covers efficacy, safety, and the hepatotoxicity warnings
- U.S. National Institutes of Health Office of Dietary Supplements — Black Cohosh Fact Sheet (Health Professionals) — comprehensive scientific summary with full reference list
- European Medicines Agency — Cimicifugae rhizoma (Black Cohosh) — the European Medicines Agency herbal monograph including the mandatory hepatotoxicity labeling
- North American Menopause Society (NAMS) — now The Menopause Society; position statements on non-hormonal menopausal therapies including Black Cohosh
- LiverTox (U.S. National Institutes of Health) — Black Cohosh
- PubMed — All research on Black Cohosh / Actaea racemosa (~1,500+ papers)
Connections
- All Herbs
- Black Cohosh (Main Page)
- Black Cohosh for Menopause & Hot Flashes
- Black Cohosh for Hormonal Balance
- Black Cohosh for Bone Health
- Black Cohosh for Mood & Sleep
- Maca
- Ashwagandha
- Chamomile
- Lemon Balm
- Perimenopause
- Perimenopause Symptom Tracker
- Polycystic Ovary Syndrome
- Anxiety
- Depression
- Hormone Panel
- Stress Management
- History