Ashwagandha for Sleep Quality
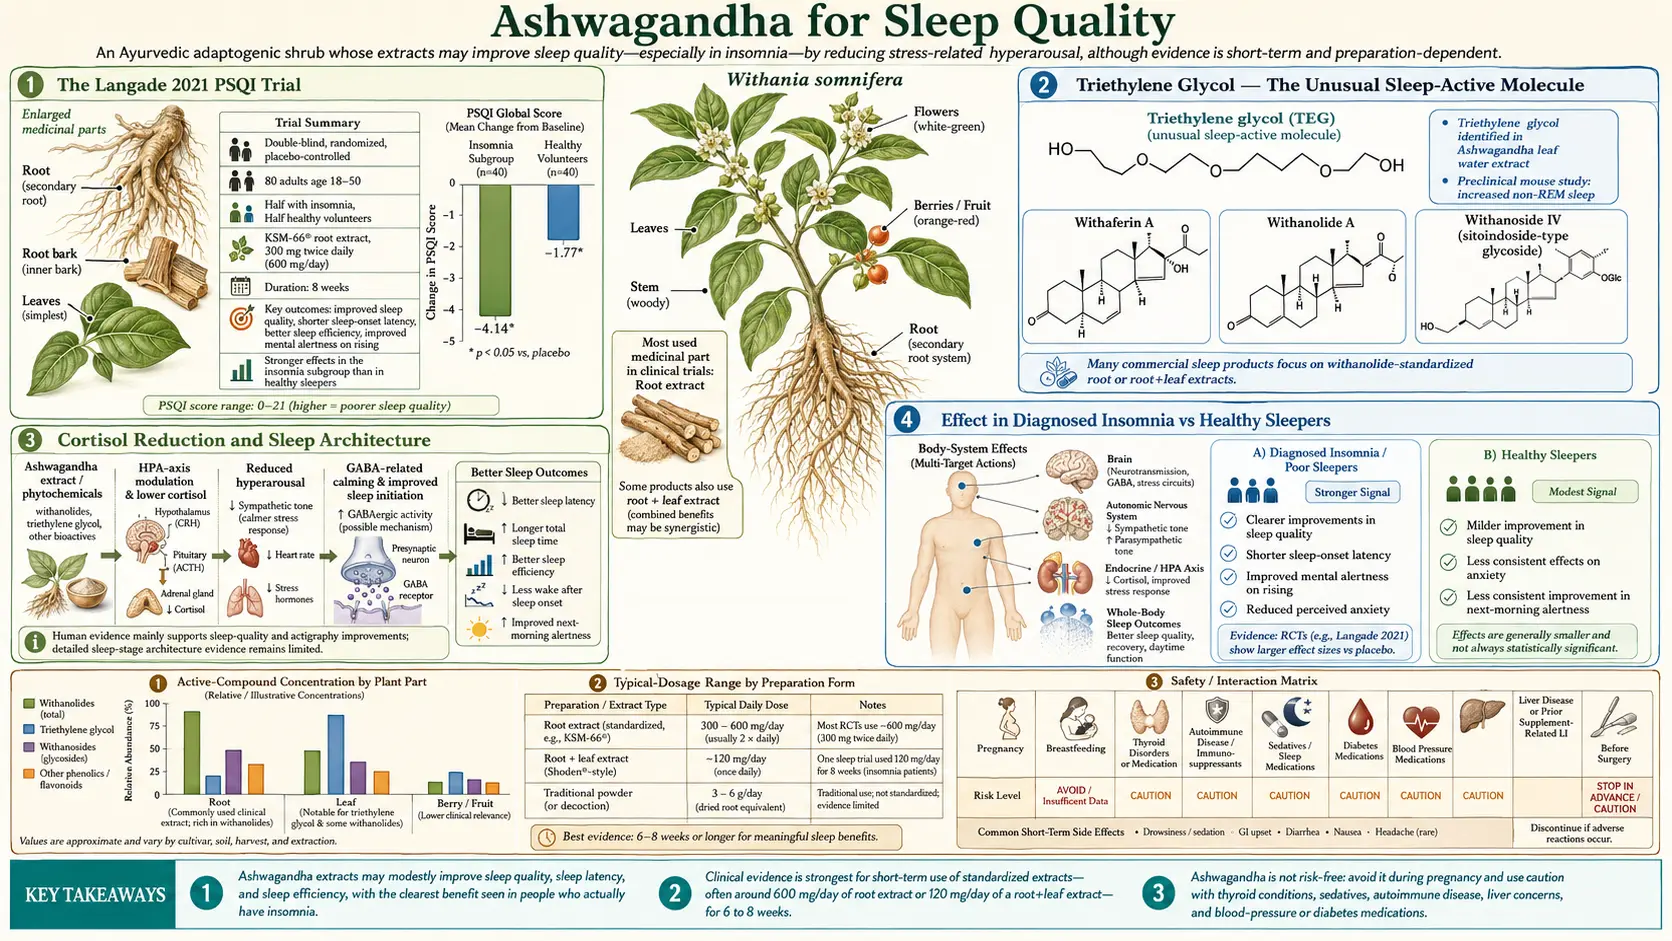
Ashwagandha is one of the few botanical sleep aids studied in randomized trials that measured sleep with a wrist activity monitor (actigraphy) and validated self-report questionnaires, rather than only by subjective testimonial. The pivotal trial — Langade 2021, an 8-week randomized double-blind placebo-controlled study in 80 subjects (40 with diagnosed insomnia, 40 healthy volunteers) — reported that root extract shortened the time to fall asleep (sleep onset latency), improved total sleep time, reduced wake-after-sleep-onset, and improved the Pittsburgh Sleep Quality Index (PSQI). The mechanism is the most unusual story in botanical pharmacology: triethylene glycol, a small water-soluble molecule found in water extracts of Ashwagandha leaves, increased non-rapid-eye-movement sleep in mice; how it acts in the brain was not tested. Combined with the lower morning cortisol seen with root extract in a stress trial, which points to the hypothalamic-pituitary-adrenal (HPA) axis, the proposed explanation is a botanical that helps both falling asleep and staying asleep; night-time cortisol itself has not been measured in the trials cited here. This page walks through the trial evidence, the triethylene glycol discovery, the mechanism, and the practical comparison with melatonin, magnesium glycinate, valerian, and L-theanine.
Table of Contents
- The Langade 2021 PSQI Trial
- Triethylene Glycol — The Unusual Sleep-Active Molecule
- Cortisol Reduction and Sleep Architecture
- Effect in Diagnosed Insomnia vs Healthy Sleepers
- Sleep Onset Latency, Total Sleep Time, and Efficiency
- Comparison with Melatonin
- Comparison with Magnesium Glycinate and L-Theanine
- Comparison with Valerian and Herbal Sedatives
- Dosing and Timing for Sleep Indications
- Cautions for Sleep-Focused Use
- Key Research Papers
- Connections
- Featured Videos
The Langade 2021 PSQI Trial
Langade and colleagues published the most rigorous Ashwagandha-for-insomnia trial in the Journal of Ethnopharmacology in 2021. The design was a double-blind, randomized, parallel-group, placebo-controlled study running for 8 weeks. Eighty subjects were enrolled in two strata: 40 healthy volunteers (PSQI < 5) and 40 patients with diagnosed insomnia (PSQI > 5 and meeting ICSD-3 criteria). Within each stratum, subjects were randomized 1:1 to either 300 mg of a standardized root extract twice daily, or matched placebo.
Outcomes were measured at baseline, 6 weeks, and 8 weeks using the Pittsburgh Sleep Quality Index (PSQI — the gold standard self-report instrument with seven component scores: subjective sleep quality, sleep onset latency, sleep duration, habitual sleep efficiency, sleep disturbances, use of sleep medication, daytime dysfunction). Anxiety and overall mental alertness were tracked as secondary outcomes.
Results at 8 weeks, as given in the published summary (Ashwagandha vs placebo; the summary gives significance levels, not the minute-by-minute values):
- Sleep onset latency — significantly improved in the insomnia group (p = 0.013); in the combined analysis, sleep onset latency and sleep efficiency were the most improved measures (both p < 0.0001)
- Total sleep time — improved (p < 0.002)
- Wake after sleep onset — reduced (p < 0.040)
- Anxiety (Hamilton Anxiety Rating Scale, HAM-A) and sleep quality — significantly improved in the insomnia group (p < 0.05)
- Mental alertness on rising — improved significantly in the insomnia group (p = 0.01)
- Tolerability — the extract was well tolerated by all participants, whatever their health condition and age
In the healthy-volunteer subgroup, improvements were less marked than in the insomnia group (these subjects started with adequate sleep); the before-and-after changes in the sleep measures were statistically significant, but the changes in anxiety (HAM-A) and mental alertness were not. This pattern — larger effect in the symptomatic population, smaller-but-real effect in healthy subjects — is characteristic of restorative interventions rather than pure sedatives.
An earlier trial by the same research group (Langade, Kanchi, Salve and colleagues, 2019) enrolled 60 patients with insomnia and anxiety, randomized 2:1 (40 to the extract, 20 to placebo). They took a full-spectrum root extract, 300 mg twice daily with milk or water, for 10 weeks, and sleep was measured with a wrist activity monitor (actigraphy), not in a sleep laboratory. After 10 weeks, the time to fall asleep was 29.0 minutes on the extract versus 33.9 minutes on placebo (p = 0.019), and sleep efficiency rose from 75.6 to 83.5 on the extract versus 75.1 to 79.7 on placebo. Because it shares authors with the 2021 trial, it is not an independent replication.
Triethylene Glycol — The Unusual Sleep-Active Molecule
The most surprising finding in Ashwagandha pharmacology over the past decade was published by Kaushik and colleagues in PLOS ONE in 2017. The team, at the University of Tsukuba's International Institute for Integrative Sleep Medicine in Japan working with a laboratory of the National Institute of Advanced Industrial Science and Technology, was investigating which component of Ashwagandha leaves was responsible for sleep induction. They gave mice different leaf extracts by mouth and recorded their sleep with brain-wave (EEG) and muscle (EMG) electrodes. The alcohol extract, which held a high amount of the withanolides, did not induce sleep. The water extract, whose major component is triethylene glycol, induced a significant amount of non-rapid-eye-movement (non-REM) sleep with only a slight change in REM sleep — so the active part was small, polar, and water-soluble, not the fat-soluble withanolides that had been assumed to drive sleep activity.
The molecule, triethylene glycol, had been identified earlier as an active component of water extracts of Ashwagandha leaves; this paper tested it for sleep. It is a simple polyethylene glycol (HOCH2CH2OCH2CH2OCH2CH2OH, also known as TEG or 2,2'-ethylenedioxydiethanol). This was a startling result: TEG is a common industrial solvent and humectant, present in liquid laundry detergents, household disinfectants, and as a base for many cosmetic preparations. It would not have appeared on any reasonable list of expected botanical sleep actives.
Commercially available triethylene glycol, given to mice by mouth at 10-30 mg per mouse, also increased non-REM sleep, more at higher doses. The paper did not test how TEG acts in the brain (no receptor experiment was reported), and no human study of TEG appears in the literature cited here — the finding is from mice only.
The clinical implications are still being worked out. Most commercial Ashwagandha products are root extracts, which would contain little or no leaf-derived TEG. Root-and-leaf extracts contain both withanolides and any TEG present in the leaf material. Traditional Ayurvedic kshirapaka preparations (root powder simmered in milk) would not extract much TEG either. The Langade trials used root extract and reported sleep improvements without leaf TEG, suggesting that root components — the morning-cortisol drop seen in a stress trial, and the GABA-like activity a 1991 laboratory study found in a root extract — may be enough for the sleep benefit; TEG may be an additional contribution rather than the primary actor.
Cortisol Reduction and Sleep Architecture
The hypothalamic-pituitary-adrenal-axis story explored in the Stress & Anxiety deep dive is half the explanation for the sleep effect. Cortisol follows a strong diurnal rhythm in healthy individuals: peak in the first hour after waking (the "cortisol awakening response"), gradual decline through the day, and a nadir near the start of sleep that supports both initiation of sleep and the deep slow-wave sleep that dominates the first half of the night.
In chronic stress and insomnia, this pattern flattens or inverts. Evening cortisol fails to fall to the normal nadir. Subjects experience a "wired and tired" state at bedtime — physically exhausted but mentally activated. Sleep onset is prolonged. Once asleep, elevated nocturnal cortisol suppresses growth hormone release (which normally peaks during the first slow-wave episode), reduces REM sleep duration, and increases wake-after-sleep-onset (WASO) and early-morning awakening.
What the trial evidence shows about cortisol is narrower. In the Lopresti 2019 trial, 60 stressed but healthy adults took 240 mg of a standardized root extract or placebo once a day for 60 days. Cortisol was measured in one morning fasting blood sample (taken at about 8 am): it fell 23% on ashwagandha versus a 0.5% rise on placebo. DHEA-S (dehydroepiandrosterone sulphate, another adrenal hormone) fell 8.2% versus a 2.5% rise on placebo. Evening and night-time cortisol were not measured, so whether ashwagandha restores the normal day-to-night cortisol pattern is not known from this trial.
The proposed downstream effect on sleep architecture is restored slow-wave sleep, longer REM episodes, and improved sleep efficiency. The human trials cited on this page measured sleep with wrist actigraphy and questionnaires, which record sleep timing and efficiency but not sleep stages, so changes in slow-wave and REM sleep have not been shown. People describe sleep that "feels deeper" and easier morning rising.
Effect in Diagnosed Insomnia vs Healthy Sleepers
One of the strengths of the Langade 2021 design was stratifying the analysis into diagnosed insomnia patients and healthy volunteers. The dual analysis answers a clinically important question: is Ashwagandha a sleep aid only for people with insomnia, or does it produce gains in normal sleepers too?
The answer is mostly the former. The published summary reports that the improvement was more marked in the insomnia patients than in the healthy subjects; it does not give the minute-by-minute figures for each group.
This restorative pattern (large effect on dysfunction, small effect in normal) is what would be expected from a normalizing adaptogen rather than a pharmacologic sedative. A sedative-hypnotic like zolpidem would produce similar dose-dependent sedation regardless of baseline status — it would put both groups to sleep faster, with attendant risks of over-sedation in normal sleepers. Ashwagandha's pattern matches the broader Ayurvedic concept of a rasayana that restores balance rather than imposing a uniform effect.
This means the trial evidence fits people with measured sleep disturbance, chronic stress, evening anxiety, or signs of hypothalamic-pituitary-adrenal-axis dysregulation. It does not cover occasional jet lag in a normal sleeper (melatonin, a body-clock hormone, is the supplement used for that) or purely behavioral sleep restriction in shift workers (where sleep hygiene and chronotherapy are the usual approaches).
A 2021 pooled analysis (meta-analysis) of five randomized trials with 400 adults found a small but significant improvement in overall sleep (standardized mean difference -0.59). The effect was larger in adults diagnosed with insomnia, at doses of 600 mg a day or more, and with treatment lasting 8 weeks or longer. Ashwagandha also improved mental alertness on rising and anxiety, but not quality of life. No serious side effects were reported, but the authors note that data on serious side effects are limited and more safety data are needed before long-term use can be judged safe.
Sleep Onset Latency, Total Sleep Time, and Efficiency
Three core sleep metrics deserve unpacking because they are the most commonly improved by Ashwagandha:
- Sleep onset latency (SOL) — the time from "lights out" to the first epoch of consensus-scored sleep. Normal SOL is approximately 10-20 minutes. SOL > 30 minutes is considered abnormal; SOL > 60 minutes is severe sleep onset insomnia. Ashwagandha trials consistently show 25-30% reduction in SOL, most dramatic in subjects with baseline SOL > 30 minutes.
- Total sleep time (TST) — the cumulative duration of actual sleep across the time-in-bed window. Normal adult TST is 7-9 hours. TST < 6 hours is associated with adverse cardiovascular and metabolic outcomes. Total sleep time was one of the measures that improved in the Langade 2021 trial (p < 0.002).
- Sleep efficiency — TST as a percentage of total time in bed (TIB). Healthy sleep efficiency is > 85%. Sleep efficiency < 80% is the central diagnostic feature of insomnia — the patient is allocating adequate time to sleep but spending too much of it awake. Ashwagandha-treated subjects in the 2019 Langade trial moved from 75.6% to 83.5% sleep efficiency (placebo: 75.1% to 79.7%).
The improvement in sleep efficiency is particularly important because it reduces the most distressing subjective experience of insomnia — lying in bed awake, watching the clock, anticipating tomorrow's exhaustion. Reducing wake-after-sleep-onset and reducing the late-night anxiety cycle that develops around chronic insomnia are often more clinically meaningful than the headline total-sleep-time number.
A 2024 meta-analysis of five randomized trials (254 people with anxiety or insomnia) found that ashwagandha improved time to fall asleep, total sleep time, Pittsburgh Sleep Quality Index (PSQI) score and sleep efficiency, but not time awake after falling asleep or total time in bed. The trials differed widely from one another (heterogeneity I² = 98% for the anxiety result), and the authors call for larger studies.
Comparison with Melatonin
Melatonin and Ashwagandha occupy different niches in the sleep-supplement landscape. They are often combined, not competing.
Melatonin (0.3 to 5 mg, 30-60 minutes before bedtime) is fundamentally a circadian-rhythm shift agent — it is the hormone the pineal gland releases when darkness falls, signaling night to the suprachiasmatic nucleus and downstream sleep circuits. It is most effective for delayed sleep phase disorder, jet lag, shift work disorder, and for older adults whose endogenous melatonin production has declined. It is less effective as a pure sleep aid in chronic insomnia in otherwise healthy adults, because the deficit there is not melatonin signaling but cortisol dysregulation and behavioral conditioning.
Ashwagandha works through cortisol reduction and GABAergic anxiolysis, not through circadian phase shift. It is most effective for chronic stress-induced insomnia, anxiety-driven sleep onset difficulty, and sleep maintenance problems associated with elevated nocturnal cortisol. It is less useful for purely circadian disorders like jet lag.
The combination practitioners describe:
- Melatonin 0.5-1 mg at 9 pm to entrain the circadian signal
- Ashwagandha 300 mg root extract with dinner and 300 mg one hour before bed for cortisol/anxiety
- Optional magnesium glycinate at bedtime for additional GABAergic support
Practitioners in integrative sleep medicine describe this three-component stack as a common starting point for people with chronic insomnia who prefer not to use prescription hypnotics. None of the trials cited on this page tested this exact stack.
One trial has compared the two directly. In a 2026 randomized, double-blind, placebo-controlled study by the Langade group, 200 men and women aged 18-50 took root extract (300 mg twice daily), melatonin (3 mg a day), both together, or placebo for eight weeks, with sleep measured by actigraphy. Ashwagandha alone and melatonin alone gave moderate and similar improvements; the combination gave the greatest improvement in time to fall asleep, and also improved total sleep time, time awake after falling asleep and sleep efficiency. Mild side effects occurred in all groups, with no meaningful difference between them.
Comparison with Magnesium Glycinate and L-Theanine
Magnesium glycinate (200-400 mg elemental magnesium at bedtime) and L-theanine (200 mg, 1-3 times daily including bedtime) are the other two commonly stacked nutritional sleep supports.
Magnesium glycinate provides two simultaneous interventions. First, magnesium is a N-methyl-D-aspartate (NMDA) receptor antagonist (blocking glutamate-mediated neural excitation) and a positive modulator at gamma-aminobutyric acid-A. Second, the glycine moiety is itself a primary inhibitory neurotransmitter in the brainstem and spinal cord. Most stressed adults are mildly magnesium-deficient. Replacing the deficit with the well-tolerated glycinate form improves sleep onset and sleep quality in the meta-analyses, particularly in older adults and stressed populations. Magnesium glycinate complements Ashwagandha well — they work through different mechanisms.
L-theanine increases alpha-wave electroencephalogram (EEG) activity (the "relaxed but alert" pattern), increases brain gamma-aminobutyric acid (GABA) and glycine, and modulates dopamine and serotonin in ways that produce subjective calming. It does not directly sedate. Its strength is in reducing the racing thoughts and ruminative anxiety that often delay sleep onset. L-theanine and Ashwagandha can be combined safely — they act through different molecular targets.
How practitioners commonly match a supplement to the sleep pattern (practice, not trial results):
- Sleep onset difficulty with racing thoughts — L-theanine is usually tried first, with Ashwagandha added if it persists
- Sleep onset difficulty with general anxiety and elevated cortisol — Ashwagandha is usually tried first
- Sleep maintenance difficulty (wake at 3 am, can't return to sleep) — cortisol pattern is dysregulated; Ashwagandha most likely to help
- Delayed sleep phase (can't fall asleep until 2 am, would sleep until 10 am if allowed) — melatonin is usually tried first
- Restless sleep with muscle tension or cramping — magnesium glycinate is usually tried first
Comparison with Valerian and Herbal Sedatives
Valerian, passionflower, lemon balm, and hops are the classical Western herbal sedatives, all acting primarily through gamma-aminobutyric acid-A facilitation. Valerian root extract at 300-600 mg before bedtime has modest efficacy in some trials and no benefit in others; meta-analyses suggest a small effect on subjective sleep quality with high heterogeneity.
Compared to valerian, Ashwagandha:
- Has stronger evidence base (multiple positive randomized controlled trials (RCTs) vs mixed results for valerian)
- Addresses cortisol pathology in addition to gamma-aminobutyric acid
- Lacks the distinctive odor that makes valerian capsules unpleasant for many users
- Does not produce the "hangover" feeling some users report with valerian
- Has documented daytime use without sedation (valerian is purely bedtime)
For purely situational acute insomnia (one-night sleep difficulty before a big event), practitioners describe a fast-acting herbal sedative like passionflower or lemon balm at bedtime as a closer fit than Ashwagandha, which takes weeks to build its full effect. For chronic insomnia and stress-related sleep disturbance, Ashwagandha has more positive randomized trials behind it than valerian.
Dosing and Timing for Sleep Indications
The Langade trial used a standardized root extract at 300 mg twice daily, taken with breakfast and dinner. This dosing pattern produces continuous coverage and avoids the trap of expecting a single bedtime dose to act like a hypnotic.
Sleep-focused dosing patterns used in trials and in practice:
- Standard — 300 mg of a standardized root extract with dinner, 300 mg one hour before bedtime. It is commonly taken with food (the withanolides are fat-soluble; absorption improves with a small fat-containing meal or a teaspoon of nut butter).
- Root-and-leaf extract for evening focus — 125-250 mg of a standardized root-and-leaf extract one hour before bedtime, often combined with magnesium glycinate. The higher withanolide concentration and leaf TEG content may produce a stronger acute effect than a root-only extract; no trial cited here compared the two.
- Traditional kshirapaka — 3-5 grams of root powder simmered in 1 cup whole milk with a pinch of cardamom and a teaspoon of ghee, consumed one hour before bedtime. Pleasant taste, decent withanolide extraction, the calming ritual itself contributes to sleep readiness.
- Stacked sleep formula — 300 mg of a standardized root extract + 200 mg L-theanine + 200 mg magnesium glycinate + 0.5 mg melatonin, all one hour before bed. Four mechanisms (cortisol/gamma-aminobutyric acid, alpha-wave/glycine, N-methyl-D-aspartate antagonism, circadian phase). Practitioners describe it as often more effective than any single component for chronic refractory insomnia; this combination has not been tested in a trial cited here.
The trials ran for 8-10 weeks, and practitioners describe 4-8 weeks for the full sleep effect. The acute GABAergic component may produce mild perceptible calming from the first dose, but the durable architecture improvements emerge as cortisol patterns remodel.
Cautions for Sleep-Focused Use
- Pregnancy — listed as an absolute contraindication. Among other sleep aids, magnesium glycinate is generally accepted as safe in pregnancy, melatonin is controversial but used, and benzodiazepines and Z-drugs are contraindicated.
- Driving and machinery the next morning — Ashwagandha generally does not produce daytime sedation, but a small subset of users report mild morning grogginess on initial days of use, which is why some people start on a weekend or low-demand period.
- Sedative interaction — additive with benzodiazepines, opioids, alcohol, and prescription hypnotics. Patients tapering off prescription hypnotics commonly use Ashwagandha as part of the transition. Stopping a benzodiazepine suddenly can cause withdrawal reactions, including seizures, which is why these tapers are normally done under medical supervision.
- Sleep apnea — Ashwagandha is not a treatment for obstructive sleep apnea (OSA). Loud snoring, witnessed pauses in breathing, and heavy daytime sleepiness are the typical signs of obstructive sleep apnea, which Ashwagandha does not resolve. Adding any GABAergic agent to untreated severe OSA can worsen nocturnal hypoxemia.
- Hyperthyroidism — Ashwagandha mildly increases thyroid output, which can worsen insomnia in hyperthyroid patients. In insomnia caused by hyperthyroidism, this effect works in the wrong direction.
- Restless legs syndrome / periodic limb movement disorder — Ashwagandha does not directly help; iron status, dopamine agonists, and other targeted treatments are the ones studied for these conditions.
- Insomnia secondary to depression — if the insomnia is the somatic feature of major depression, it is treatment of the depression itself that addresses it. Ashwagandha may be a reasonable adjunct (it has weak antidepressant signal in some trials) but is not a standalone treatment for depression-related insomnia.
A 2025 review of 14 randomized trials in people with a diagnosed mental disorder (360 treated with ashwagandha, 353 controls; median dose 600 mg a day, median follow-up 8 weeks) found improvements in anxiety, stress and sleep quality (standardized mean difference -1.35 for sleep quality), and no significant difference from the comparison treatments in safety and tolerability. The authors note the small number of studies and call for more trials before ashwagandha's role in insomnia treatment is clear.
See our Insomnia page for the broader evaluation and management framework, and our Sleep Hygiene page for the foundational behavioral interventions commonly paired with any pharmacologic or supplement strategy.
Key Research Papers
- Langade D, Thakare V, Kanchi S, Kelgane S (2021). Clinical evaluation of the pharmacological impact of ashwagandha root extract on sleep in healthy volunteers and insomnia patients: a double-blind, randomized, parallel-group, placebo-controlled study. Journal of Ethnopharmacology. — PubMed PMID: 32818573
- Langade D, Kanchi S, Salve J, Debnath K, Ambegaokar D (2019). Efficacy and safety of ashwagandha (Withania somnifera) root extract in insomnia and anxiety: a double-blind, randomized, placebo-controlled study. Cureus. — PubMed PMID: 31728244
- Kaushik MK, Kaul SC, Wadhwa R, Yanagisawa M, Urade Y (2017). Triethylene glycol, an active component of Ashwagandha (Withania somnifera) leaves, is responsible for sleep induction. PLOS ONE. — PubMed PMID: 28207892
- Deshpande A, Irani N, Balkrishnan R, Benny IR (2020). A randomized, double blind, placebo controlled study to evaluate the effects of ashwagandha (Withania somnifera) extract on sleep quality in healthy adults. Sleep Medicine. — PubMed PMID: 32540634
- Cheah KL, Norhayati MN, Husniati Yaacob L, Abdul Rahman R (2021). Effect of ashwagandha (Withania somnifera) extract on sleep: a systematic review and meta-analysis. PLOS ONE. — PubMed PMID: 34559859
- Lopresti AL, Smith SJ, Malvi H, Kodgule R (2019). An investigation into the stress-relieving and pharmacological actions of an ashwagandha extract. Medicine (Baltimore). — PubMed PMID: 31517876
- Salve J, Pate S, Debnath K, Langade D (2019). Adaptogenic and anxiolytic effects of ashwagandha root extract in healthy adults: a double-blind, randomized, placebo-controlled clinical study. Cureus. — PubMed PMID: 32021735
- Kelgane SB, Salve J, Sampara P, Debnath K (2020). Efficacy and tolerability of ashwagandha root extract in the elderly for improvement of general well-being and sleep: a prospective, randomized, double-blind, placebo-controlled study. Cureus. — PubMed PMID: 32226684
- Speers AB, Cabey KA, Soumyanath A, Wright KM (2021). Effects of Withania somnifera on stress and stress-related neuropsychiatric disorders anxiety, depression, and insomnia. Current Neuropharmacology. — PubMed PMID: 34254920
- Verma N, Gupta SK, Tiwari S, Mishra AK (2021). Safety of ashwagandha root extract: a randomized, placebo-controlled, study in healthy volunteers. Complementary Therapies in Medicine. — PubMed PMID: 33338583
- Mehta AK, Binkley P, Gandhi SS, Ticku MK (1991). Pharmacological effects of Withania somnifera root extract on GABA-A receptor complex. Indian Journal of Medical Research. — PubMed PMID: 1660034
- Pandey A, Bani S, Dutt P, Kumar Satti N, Avtar Suri K, Nabi Qazi G (2018). Multifunctional neuroprotective effect of withanone, a compound from Withania somnifera roots in alleviating cognitive dysfunction. Cytokine. — PubMed PMID: 29108796
- Fatima K, Malik J, Muskan F, Raza G, Waseem A, Shahid H, Jaffery SF, Khan U, Zaheer MK, Shaikh Y, Rashid AM (2024). Safety and efficacy of Withania somnifera for anxiety and insomnia: systematic review and meta-analysis. Human Psychopharmacology. — PubMed PMID: 39083548
- Marchi M, Grenzi P, Travascio A, Uberti D, De Micheli E, Quartaroli F, Laquatra G, Pingani L, Ferrari S, Galeazzi GM (2025). The effect of Withania somnifera (Ashwagandha) on mental health symptoms in individuals with mental disorders: systematic review and meta-analysis. BJPsych Open. — PubMed PMID: 41140145
- Movva N, Salve J, Wankhede K, Thakare V, Langade D (2026). Comparative evaluation of Ashwagandha (Withania somnifera) root extract and melatonin for improving sleep quality in adults: a prospective, randomized, double-blind, placebo-controlled study. Clocks & Sleep. — PubMed PMID: 42029558
PubMed Topic Searches
- PubMed: Ashwagandha sleep RCTs
- PubMed: Withania sleep latency
- PubMed: TEG and sleep
- PubMed: Ashwagandha PSQI
- PubMed: Evening cortisol
- PubMed: Ashwagandha in the elderly
- PubMed: Sleep architecture
- PubMed: Ashwagandha sleep meta-analysis
- PubMed: Melatonin vs ashwagandha
- PubMed: Root-extract sleep trials
- PubMed: Adaptogen sleep effects
- PubMed: GABA-A mechanism