Ashwagandha for Testosterone and Vitality
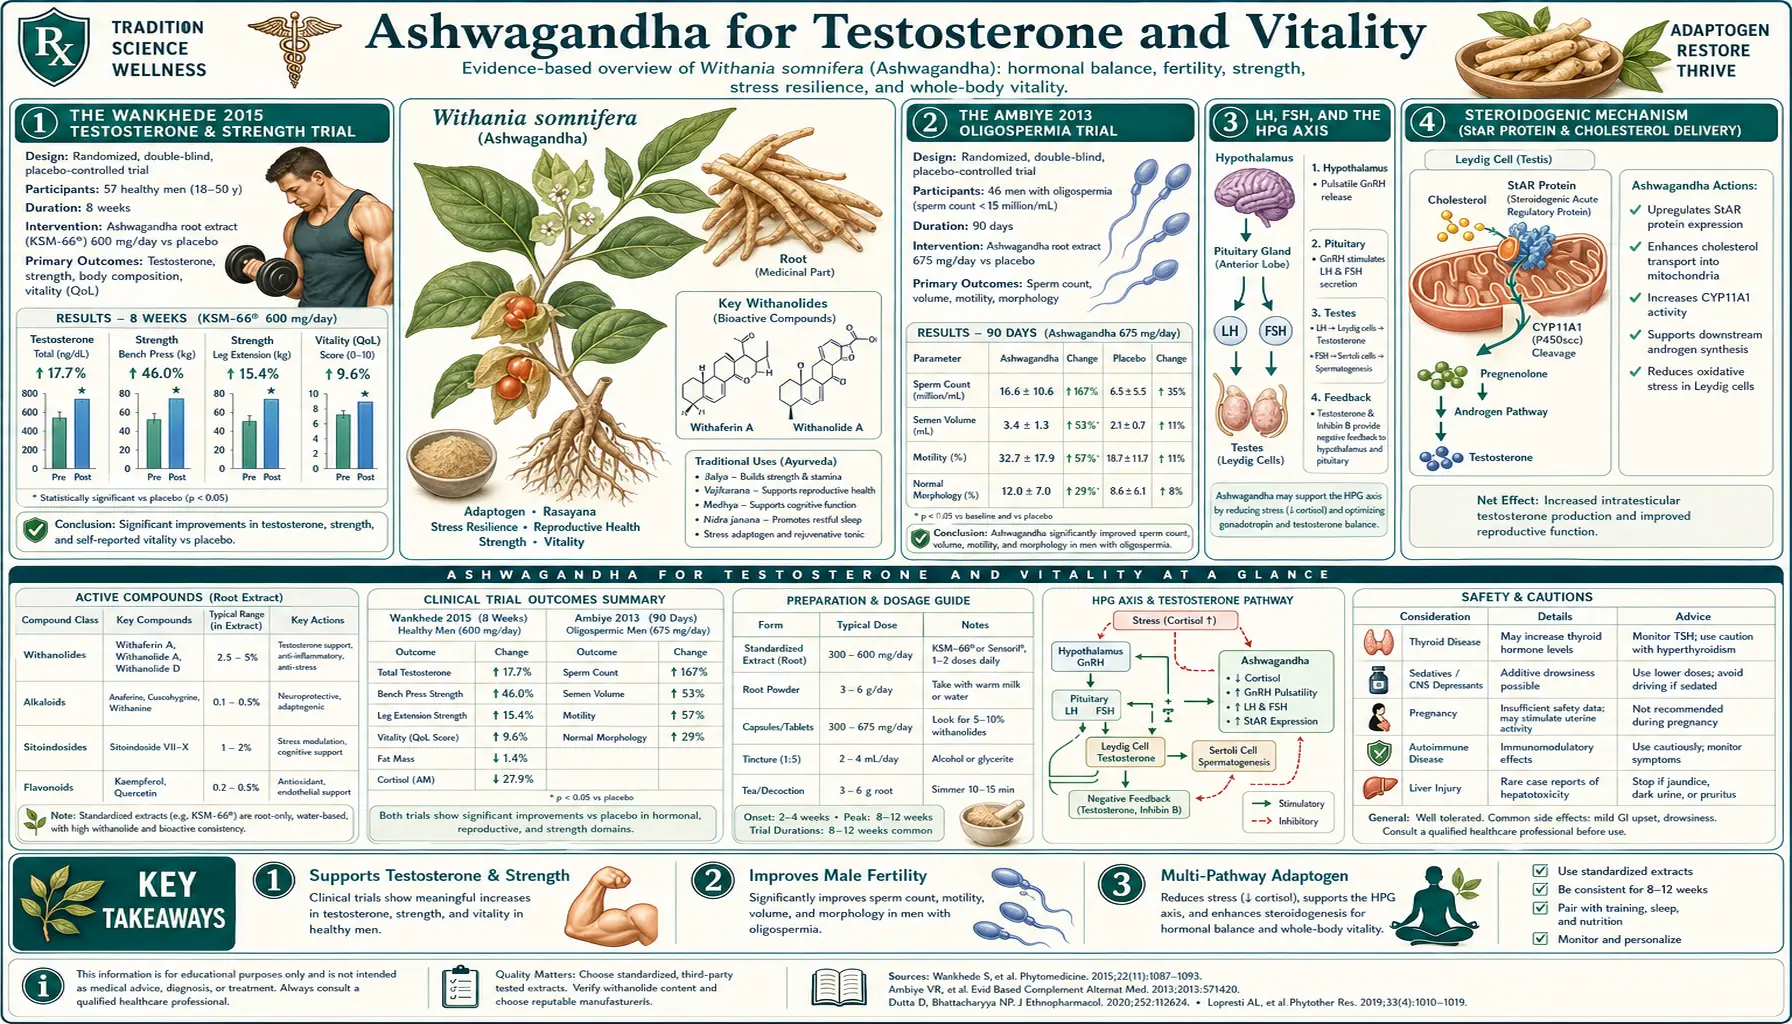
A 2021 systematic review of herbs and testosterone (Smith and colleagues) found that two herbal extracts — fenugreek seed extracts and ashwagandha root and root/leaf extracts — have positive effects on testosterone in men, while adding that further research is required before definitive conclusions. The Wankhede 2015 trial — published in the Journal of the International Society of Sports Nutrition, randomizing 57 resistance-untrained men aged 18-50 to 600 mg a day of a root-only extract or placebo over 8 weeks of identical strength training — reported a rise in serum testosterone of 96.2 ng/dL in the active group versus 18.0 ng/dL on placebo, accompanied by larger strength gains (one-rep-max bench press +46.0 vs +26.4 kg; leg extension +14.5 vs +9.8 kg) and larger muscle growth (arm size +8.6 vs +5.3 cm²; chest +3.3 vs +1.4 cm), with significantly larger reductions in body fat percentage and post-exercise muscle damage markers. The earlier Ambiye 2013 trial in 46 men with low sperm counts (oligospermia; 21 given the extract, 25 placebo) documented increases in sperm concentration (167%), motility (57%), and serum testosterone (17%), with a corresponding increase in serum luteinizing hormone (LH), consistent with a steroidogenic upregulation rather than direct hormonal supplementation. The mechanism converges on three pathways: (1) hypothalamic-pituitary-adrenal-axis cortisol reduction that releases the cortisol-induced suppression of the hypothalamic-pituitary-gonadal axis; (2) direct upregulation of steroidogenic acute regulatory protein (StAR) and the rate-limiting cholesterol side-chain cleavage enzyme in Leydig cells; (3) Nrf2-mediated reduction of testicular oxidative stress. This page covers the trial evidence, the mechanism, the comparative endocrinology of Ashwagandha versus testosterone replacement therapy, and the practical application to men with documented low testosterone, oligospermia, exercise performance, and the broader concept of male "vitality."
Table of Contents
- The Wankhede 2015 Testosterone & Strength Trial
- The Ambiye 2013 Oligospermia Trial
- Luteinizing Hormone, Follicle-Stimulating Hormone, and the Hypothalamic-Pituitary-Gonadal Axis
- Steroidogenic Mechanism (StAR Protein, Cholesterol Cleavage)
- The Cortisol-Testosterone Inverse Relationship
- Exercise Performance, Strength, and Recovery
- Cardiorespiratory Fitness (VO2max) Effects
- Sperm Concentration, Motility, and Morphology
- Female Vitality, Libido, and Reproductive Effects
- Comparison with Testosterone Replacement Therapy
- Dosing for Testosterone and Vitality Indications
- Stacking with Zinc, Vitamin D, Boron, and Tongkat Ali
- Cautions
- Key Research Papers
- Connections
- Featured Videos
The Wankhede 2015 Testosterone & Strength Trial
Wankhede, Langade, Joshi, Sinha, and Bhattacharyya published in the Journal of the International Society of Sports Nutrition in 2015 the trial that established Ashwagandha as a serious candidate for testosterone and exercise performance applications. The design was randomized, double-blind, placebo-controlled, 8 weeks duration. Fifty-seven male subjects aged 18-50 with little prior resistance training experience were randomized to receive either 300 mg of a root-only extract twice daily, or matched placebo, alongside an identical supervised progressive resistance training program (3 sessions per week of standardized barbell and machine exercises).
Outcomes measured at baseline and 8 weeks:
- Muscular strength — one-rep maximum (1RM) on bench press and leg extension
- Muscular size — arm circumference, chest circumference
- Body composition — body fat percentage by skinfold
- Exercise-induced muscle damage — serum creatine kinase
- Hormonal — serum total testosterone
- Recovery — perceived muscle soreness
Results (Ashwagandha vs placebo, all p < 0.05):
- Bench press 1RM — +46.0 kg vs +26.4 kg
- Leg extension 1RM — +14.5 kg vs +9.8 kg
- Arm muscle size — +8.6 cm² vs +5.3 cm²
- Chest circumference — +3.3 cm vs +1.4 cm
- Body fat percentage — -3.5% vs -1.5%
- Serum testosterone — +96.2 ng/dL vs +18.0 ng/dL (from average starting levels of about 630 and 675 ng/dL)
- Creatine kinase (muscle damage) — significantly lower at 24h post-exercise
Related trials have since been published. Lopresti 2019 gave overweight men aged 40-70 with mild fatigue an ashwagandha extract delivering 21 mg of withanolide glycosides a day, in 8-week arms of a 16-week crossover trial (57 enrolled, 43 completed): testosterone measured in saliva rose 14.7% more, and DHEA-S 18% more, than on placebo, with no significant between-group differences in fatigue, vigor, or sexual well-being. Ziegenfuss 2018 gave 38 recreationally active men 500 mg/day of a root-and-leaf extract or placebo during 12 weeks of resistance training and reported larger upper- and lower-body strength gains; it did not report testosterone results. The trials used different preparations and doses — a root-only extract, a root-and-leaf extract, a withanolide-glycoside extract, and, in the infertility studies below, plain root powder at 5 g a day.
The Ambiye 2013 Oligospermia Trial
Ambiye, Langade, Dongre, Aptikar, Kulkarni, and Dongre published in Evidence-Based Complementary and Alternative Medicine in 2013 a pilot trial of Ashwagandha for idiopathic male oligospermia. Forty-six men with oligospermia (sperm concentration < 20 million/mL) were randomized: 21 took 675 mg of a full-spectrum root extract daily (divided as 225 mg three times daily) for 90 days and 25 took placebo. Sperm parameters and two reproductive hormones (testosterone and luteinizing hormone) were measured at baseline and study end.
Results at 90 days:
- Sperm concentration — increased by 167% (from 9.6 to 25.6 million/mL on average)
- Sperm motility — increased by 57% (from 18.6% to 29.2% motile)
- Semen volume — increased by 53%
- Serum testosterone — increased by 17%
- Serum luteinizing hormone — increased by 34%
- Pregnancy outcomes — the study did not directly track conception outcomes but the sperm parameter improvements moved many subjects from clearly subfertile into reference-range fertility
The earlier Ahmad 2010 trial (75 men, infertile) and the Mahdi 2009 trial (60 infertile men with normal sperm counts, including men under psychological stress) found similar magnitudes of effect on sperm concentration, motility, and oxidative stress markers in seminal plasma. A 2018 systematic review by Durg and colleagues found four clinical trials (mostly observational, only one randomized controlled trial (RCT)) and concluded that the available data, though promising, are too limited to provide sufficiently robust evidence of benefit in male infertility; it called for larger, high-quality randomized trials.
In practice: practitioners describe using Ashwagandha in men with unexplained low sperm counts (idiopathic oligospermia) alongside the standard checks for varicocele, hypogonadism, infection, genetic causes, and lifestyle factors. The regimen they describe is 600-1000 mg/day for at least 90 days (one full spermatogenic cycle), with sperm re-tested at 90 days; the Ambiye trial used 675 mg/day.
Luteinizing Hormone, Follicle-Stimulating Hormone, and the Hypothalamic-Pituitary-Gonadal Axis
Testosterone production in men is regulated by the hypothalamic-pituitary-gonadal (HPG) axis. The hypothalamus releases gonadotropin-releasing hormone (GnRH) in pulsatile fashion. GnRH stimulates the anterior pituitary to release luteinizing hormone (LH) and follicle-stimulating hormone (FSH). Luteinizing hormone acts on Leydig cells in the testes to stimulate testosterone synthesis. Follicle-stimulating hormone acts on Sertoli cells to support spermatogenesis. Testosterone exerts negative feedback at the hypothalamus and pituitary, closing the loop.
The Ambiye 2013 finding that serum luteinizing hormone increased by 34% alongside the testosterone increase is mechanistically informative. It tells us that Ashwagandha's effect is upstream of the testes — the brain and pituitary are sending stronger signals to the testes, and the testes are responding with more testosterone. This is fundamentally different from how exogenous testosterone (TRT) works, which bypasses the entire HPG axis and shuts down endogenous luteinizing hormone/follicle-stimulating hormone/testosterone production.
The proximate cause of the increased luteinizing hormone appears to be reduced cortisol suppression of GnRH pulsatility. Chronic high cortisol is a potent suppressor of the HPG axis — this is the mechanism by which severe chronic stress, overtraining, and chronic illness reduce testosterone in men and disrupt menstruation in women. Ashwagandha's 20-30% reduction in serum cortisol releases the brake, allowing GnRH pulsatility to recover and the downstream luteinizing hormone/testosterone production to normalize.
A secondary mechanism is direct hypothalamic effects of withanolides on GnRH neurons, demonstrated in rodent models, but the magnitude of this direct effect appears to be small compared to the indirect cortisol-mediated effect.
Steroidogenic Mechanism (StAR Protein, Cholesterol Cleavage)
At the Leydig cell level, the rate-limiting step in testosterone synthesis is the transport of cholesterol from the outer to the inner mitochondrial membrane, where the side-chain cleavage enzyme P450scc (CYP11A1) converts cholesterol to pregnenolone (the obligate precursor for all subsequent steroid hormones including testosterone). The cholesterol transport is performed by steroidogenic acute regulatory protein (StAR), and StAR expression is the proximate regulator of testosterone output.
Withanolides have been shown in Leydig cell culture and in rodent models to upregulate StAR expression at the mRNA and protein level. This is a direct steroidogenic effect, independent of the luteinizing hormone-mediated signal from above. The combined effect — more luteinizing hormone signal arriving at Leydig cells, plus more responsive StAR-mediated cholesterol delivery to the steroidogenic machinery — produces the observed clinical testosterone increase.
Withanolides also support the activity of downstream steroidogenic enzymes (3-beta-hydroxysteroid dehydrogenase, 17-alpha-hydroxylase, 17,20-lyase, 17-beta-hydroxysteroid dehydrogenase) in the testosterone biosynthetic pathway. The net effect is that the entire pathway from cholesterol to testosterone runs more efficiently.
One additional contributor: Nrf2 activation in testicular tissue reduces oxidative damage to Leydig and Sertoli cells. Oxidative stress is a major factor in age-related testicular function decline, idiopathic oligospermia, and the testicular damage caused by environmental toxins, certain medications, and chronic illness. Ashwagandha's antioxidant activity in the testes preserves the cellular machinery that produces testosterone and sperm.
The Cortisol-Testosterone Inverse Relationship
The cortisol-testosterone relationship is one of the most clinically important hormonal axes in adult men, and it explains much of why Ashwagandha appears to "work" for testosterone in men who are not classically hypogonadal.
Cortisol and testosterone exhibit an inverse relationship in three ways:
- Hypothalamic suppression — chronic high cortisol suppresses GnRH pulsatility, reducing the luteinizing hormone signal to the testes, reducing testosterone production. This is the dominant mechanism by which chronic stress, sleep deprivation, overtraining, severe illness, and major depression all lower testosterone.
- Adrenal-testicular substrate competition — cortisol and testosterone are both synthesized from cholesterol via pregnenolone. Under conditions of high adrenal demand (chronic stress), the "pregnenolone steal" hypothesis posits that pregnenolone is preferentially shunted toward cortisol production, reducing substrate available for testosterone. The strict version of this hypothesis is controversial, but the directional effect is well-documented.
- SHBG modulation — chronic high cortisol can affect sex hormone-binding globulin levels, altering the free testosterone fraction available to tissues.
The result is that most modern adult men with marginal-to-low testosterone are not primary hypogonadal (the testes are structurally fine and can produce testosterone if signaled to); they are functionally hypogonadal due to chronic cortisol-mediated HPG suppression. The intervention that works is not necessarily exogenous testosterone — it is restoration of normal cortisol patterns. Ashwagandha is traditionally used in Ayurveda against stress, which is why it is studied for that purpose.
This is the explanation offered for the Wankhede trial's testosterone rise (96.2 ng/dL, against 18.0 ng/dL on placebo) in resistance-training men who started with normal-range baseline testosterone (about 630-675 ng/dL). They were not deficient in any classical sense; the theory is that their cortisol was modestly elevated from the combination of life stress and training stress, and reducing that cortisol released the HPG axis to produce more testosterone.
Exercise Performance, Strength, and Recovery
The Wankhede 2015 trial documented effects on both performance (strength gains, muscle hypertrophy) and recovery (lower creatine kinase, reduced muscle soreness). The mechanisms are multiple:
- Testosterone-mediated muscle protein synthesis — the testosterone increase seen in the Wankhede trial is proposed to contribute to greater training-induced hypertrophy
- Cortisol-mediated catabolic suppression — the lowered training cortisol reduces the protein-catabolic effect of intense exercise
- Nrf2-mediated antioxidant induction — reduced post-exercise oxidative damage to muscle tissue
- Improved sleep quality — via the cortisol mechanism, better sleep means more efficient overnight muscle repair and growth hormone release
- Improved mitochondrial function — documented in cardiac and skeletal muscle in rodent models
Athletes and trained individuals commonly include Ashwagandha in sports nutrition stacks. Ashwagandha itself is not a banned substance, but no sports body keeps a list of approved supplements: the U.S. Anti-Doping Agency (USADA) supplement guide states that the U.S. Food and Drug Administration, the World Anti-Doping Agency and USADA do not approve dietary supplements, describes normal-looking products later found contaminated with ingredients that break anti-doping rules, and says the use of any dietary supplement is at the athlete's own risk. The Wankhede trial used 300 mg of a root-only extract twice daily.
The Sandhu 2010 trial in 40 healthy young adults (10 per group) found that 500 mg a day of an Ashwagandha root extract for 8 weeks increased speed, power, and VO2max, and a separate trial by Shenoy and colleagues (2012) in 40 elite Indian cyclists found significant improvement in VO2max and time to exhaustion with 500 mg of an aqueous root extract twice daily for 8 weeks — an aerobic-performance effect that is less explored than the strength effect but consistent with the broader vitality enhancement.
Cardiorespiratory Fitness (VO2max) Effects
Beyond strength and hypertrophy, Ashwagandha has been studied for cardiorespiratory fitness. A 2020 systematic review and meta-analysis by Pérez-Gómez and colleagues (five randomized trials, four of them pooled, 142 participants) found that VO2max rose by an average of 3.00 mL/kg/min more with Ashwagandha (95% confidence interval 0.18 to 5.82), but the authors cautioned that the number of studies is limited and the heterogeneity was high, so further research is needed to confirm it.
The mechanism is not fully resolved but appears to include:
- Improved cardiac function (left ventricular ejection fraction, stroke volume)
- Enhanced mitochondrial biogenesis and oxidative capacity in skeletal muscle
- Improved erythropoiesis (modest hemoglobin increases in some trials)
- Reduced exercise-induced oxidative stress allowing higher sustained output
For middle-aged and older adults beginning an exercise program after years of inactivity, Ashwagandha may improve the rate of fitness gain during the first months when most de-conditioned individuals struggle. For elite endurance athletes already near genetic ceiling, the additive effect is smaller but still detectable in carefully controlled trials.
Sperm Concentration, Motility, and Morphology
The Ambiye 2013 results in oligospermic men have been reproduced and extended:
- Mahdi 2009 — 60 infertile men with normal sperm counts (20 heavy smokers, 20 under psychological stress, 20 with unexplained infertility), Ashwagandha root powder 5 g daily for 3 months, significant increases in sperm concentration and motility, with decreases in seminal oxidative stress markers (lipid peroxidation, protein carbonyl content)
- Ahmad 2010 — 75 normozoospermic and oligozoospermic infertile men, Ashwagandha root powder 5 g daily, improvements in all major semen parameters, rises in serum testosterone and luteinizing hormone, and falls in follicle-stimulating hormone (FSH) and prolactin
- Gupta 2013 — metabolomics study of seminal plasma in 180 infertile men taking Ashwagandha root powder 5 g a day for 3 months, compared with 50 healthy men, showing normalization of multiple metabolite pathways related to energy production, oxidative balance, and lipid composition
- Durg 2018 systematic review — found four clinical trials (five publications: four observational, one randomized), too few for a meta-analysis of randomized trials; pooling the observational before-and-after studies gave average gains of 0.28 mL in semen volume, 13.57 million/mL in sperm concentration, and 8.50% in motility, and the authors judged the data too limited to provide sufficiently robust evidence
The mechanism converges on the cortisol-LH-testosterone-Leydig cell story for hormonal effects, plus the Nrf2-mediated reduction in seminal oxidative stress for direct sperm-protective effects. The seminal antioxidant effect is particularly important because mature spermatozoa have minimal endogenous antioxidant capacity and are highly vulnerable to oxidative damage in the post-testicular environment.
For couples in fertility testing, practitioners describe Ashwagandha at 600-1000 mg/day for at least 90 days as part of the male partner's preparation before conception, and describe it as compatible with continued IVF or IUI treatment. See our Reproductive Medicine section for the broader fertility context.
Female Vitality, Libido, and Reproductive Effects
The Ashwagandha-and-vitality literature is heavily male-skewed because most of the early industry-sponsored trials targeted the testosterone and athletic-performance markets. Female-focused trials are smaller but consistent.
The Dongre 2015 trial in 50 women aged 21-50 with sexual dysfunction (Female Sexual Function Index < 26) randomized to 300 mg of a root extract twice daily or placebo for 8 weeks. The active group showed significant improvements in arousal, lubrication, orgasm, satisfaction, and number of successful sexual encounters. Mechanism likely includes the cortisol-mediated stress reduction (chronic stress is a leading cause of female sexual dysfunction), improved sleep, and modest effects on serum testosterone (women have measurable circulating testosterone from adrenal and ovarian production, and modest increases can support libido).
The Gopal 2021 trial in 100 perimenopausal women (91 completed; 300 mg of a root extract twice daily for 8 weeks) showed improvements in menopause symptom scores and quality of life. Serum estradiol rose significantly and follicle-stimulating hormone and luteinizing hormone fell compared with placebo, while testosterone did not differ. Ashwagandha is not phytoestrogenic in the way that soy isoflavones or red clover are; the mechanism here is thought to be the hypothalamic-pituitary-adrenal-axis and serotonergic effects rather than any direct estrogenic activity.
Perimenopause and stress-related loss of libido, energy, and well-being are the situations these women's trials studied. See our Perimenopause page for the broader context.
Comparison with Testosterone Replacement Therapy
Testosterone replacement therapy (TRT) and Ashwagandha occupy fundamentally different niches in male endocrinology.
TRT (transdermal gel, intramuscular injection, subcutaneous pellets, or oral testosterone undecanoate) provides exogenous testosterone, raising serum levels to whatever target the prescriber chooses. The effect is fast (weeks), large (testosterone can be raised from 200 ng/dL to 800-1000 ng/dL), and reliable. The trade-offs are significant: TRT shuts down endogenous luteinizing hormone/follicle-stimulating hormone production and causes testicular atrophy and infertility for as long as treatment continues; it requires ongoing administration indefinitely; it has cardiovascular safety questions still being studied; it requires monitoring for erythrocytosis, sleep apnea exacerbation, and prostate effects; it is contraindicated in untreated obstructive sleep apnea, breast cancer, and prostate cancer.
Ashwagandha works by enhancing endogenous testosterone production through the natural HPG axis. The magnitude is much smaller (in the Wankhede trial, a 96.2 ng/dL rise against 18.0 ng/dL on placebo; in the Lopresti trial, 14.7% more than placebo in saliva). It does not suppress endogenous production; it stimulates it. It is compatible with fertility. Trials have reported it as well tolerated, with rare liver-injury cases described under Cautions. It is much less expensive.
How the options are usually matched:
- Primary hypogonadism (Klinefelter syndrome, testicular damage from chemo/radiation/trauma, absent or non-functional testes) — testosterone replacement is the standard treatment; Ashwagandha cannot bypass missing or non-functional testicular tissue.
- Secondary hypogonadism from pituitary disease — treated with TRT or hCG/follicle-stimulating hormone replacement.
- Functional hypogonadism from chronic stress, sleep deprivation, obesity, or chronic illness — the usual approach starts with the underlying cause (sleep hygiene, weight loss, stress management), with Ashwagandha described by practitioners as an adjunct and TRT kept for when function does not recover with lifestyle and adaptogen support.
- Age-related testosterone decline ("low T" without classical hypogonadism) — controversial; practitioners often start with lifestyle and Ashwagandha, with TRT considered for men with symptoms after weighing its risks and the fertility loss it causes.
- Active fertility goal — TRT shuts down sperm production for as long as it is taken (see above), so it conflicts with this goal; Ashwagandha does not suppress the axis.
Dosing for Testosterone and Vitality Indications
- Athletic / strength performance — 300 mg of a root-only extract twice daily was the Wankhede 2015 protocol, with strength and hormones measured at 8 weeks. Practitioners describe taking it with breakfast and either before or after training.
- Male oligospermia / fertility — practitioners describe 600-1000 mg of extract daily, often divided as 225-350 mg three times daily (the Ambiye protocol used 675 mg/day), for at least 90 days (one full spermatogenic cycle of approximately 74 days plus epididymal maturation time) before semen is re-tested.
- Functional hypogonadism / "low T" symptoms — practitioners describe 600 mg of extract daily in divided doses, combined with better sleep, stress management, weight loss where relevant, and correcting low zinc or vitamin D, with testosterone re-checked at 12 weeks.
- Female libido / perimenopause — 300 mg of a root extract twice daily was used in the Dongre and Gopal trials. The Gopal trial found that ashwagandha itself raised estradiol and lowered FSH and LH, a point that matters for women who also use hormone replacement therapy (HRT).
- General male vitality / age-related decline — practitioners describe 600 mg of extract daily, often as part of a broader supplement routine with zinc, vitamin D3, magnesium, and omega-3 fatty acids.
Stacking with Zinc, Vitamin D, Boron, and Tongkat Ali
- Zinc (30-50 mg elemental, with food, is a commonly stacked amount) — the Institute of Medicine sets the adult upper limit for total zinc from food and supplements at 40 mg a day, because 60 mg a day lowered copper status, so a 30-50 mg supplement on top of food zinc can pass that limit. Zinc is essential for testosterone synthesis and is one of the most commonly deficient micronutrients in stressed and exercising men. Repletion of zinc deficiency reliably increases testosterone; supraphysiologic dosing in zinc-replete men does not. See our Zinc page.
- Vitamin D3 (some practitioners use 2000-5000 international units (IU) daily, aiming for a serum 25-OH-D level of 40-60 ng/mL) — the Institute of Medicine sets the adult upper limit at 4,000 IU a day; its 2011 report says serum levels above 30 ng/mL are not consistently associated with more benefit and that there may be reason for concern above 50 ng/mL (125 nmol/L). Vitamin D receptors are present in Leydig cells; deficiency is associated with reduced testosterone; repletion of frank deficiency raises testosterone modestly. Practitioners often pair it with vitamin K2 (menaquinone-7 (MK-7) 100-200 mcg), describing it as helping calcium handling. See our Vitamin D3 page.
- Magnesium glycinate (200-400 mg elemental) — the Institute of Medicine's upper limit for magnesium from supplements is 350 mg a day for adults and children over 8, set because diarrhea is the first sign of too much; magnesium from food is not counted. Magnesium supports the HPG axis, sleep quality, and exercise recovery. Modest direct effect on free testosterone via reduction of SHBG binding. See our Magnesium page.
- Boron (3-10 mg daily) — the Naghii 2011 study showed that boron supplementation increases free testosterone (likely via SHBG reduction) and reduces estradiol modestly. Limited but consistent evidence; safe at the doses used in supplements.
- Tongkat Ali (Eurycoma longifolia, 100-400 mg of standardized extract daily) — another HPG-axis modulator with testosterone-raising effect; complementary mechanism to Ashwagandha (works through reduced SHBG binding); often stacked with Ashwagandha in commercial testosterone-support formulas.
- Omega-3 fatty acids (2-4 g eicosapentaenoic acid (EPA)+docosahexaenoic acid (DHA) daily) — supports membrane fluidity in Leydig cells, reduces inflammation, supports sperm membrane integrity.
- Very high zinc doses — the Institute of Medicine found that zinc at 60 mg a day already lowered copper status (the basis of its 40 mg upper limit), and lists suppressed immune response, lower HDL cholesterol, and reduced copper status among the adverse effects of long-term supplemental zinc.
Cautions
- Pregnancy — listed as an absolute contraindication. Practitioners describe use while trying to conceive, stopped once pregnancy is established.
- Hyperthyroidism — Ashwagandha mildly increases thyroid output, which is the concern for people with an overactive thyroid (hyperthyroidism).
- Hormone-sensitive cancers — theoretically the testosterone-raising effect could be relevant in untreated prostate cancer, and the Gopal trial found estradiol rose in women. These hormone effects are the concern for people with active prostate cancer, breast cancer, or other hormone-responsive cancers, whose growth can be driven by these hormones.
- Autoimmune disease — mild immunomodulatory effects could theoretically exacerbate Th1-dominant autoimmunity (lupus, rheumatoid arthritis, Hashimoto's).
- Sedative interaction — additive with benzodiazepines and other central nervous system (CNS) depressants.
- Anticoagulant interaction — modest theoretical antiplatelet effect; not clinically significant in most patients but worth noting in those on warfarin or strong antiplatelets.
- Polycythemia / erythrocytosis — unlike TRT, Ashwagandha has not been associated with significant increases in hemoglobin or hematocrit, so polycythemia risk is minimal.
- Sleep apnea — unlike TRT, Ashwagandha does not exacerbate sleep apnea (it may improve it via cortisol reduction and weight effects).
- Hepatotoxicity (liver injury) case reports — rare. A 2020 case series from Iceland and the US Drug-Induced Liver Injury Network described five people who developed yellowing of the skin and eyes (jaundice) with nausea, tiredness, itching, and stomach discomfort 2-12 weeks after starting ashwagandha supplements; the injury was of the bile-flow type (cholestatic) or mixed, no one developed liver failure, and liver tests returned to normal within 1-5 months in the four people followed up. Jaundice is a sign of liver injury that hospitals treat as urgent.
- Drug testing for athletes — Ashwagandha is not a banned substance and does not produce testosterone or anabolic steroid metabolites detectable on standard sports drug tests. The U.S. Anti-Doping Agency warns that supplements can be contaminated with banned ingredients the label does not show, and that no agency approves dietary supplements.
Key Research Papers
- Wankhede S, Langade D, Joshi K, Sinha SR, Bhattacharyya S (2015). Examining the effect of Withania somnifera supplementation on muscle strength and recovery: a randomized controlled trial. Journal of the International Society of Sports Nutrition. — PubMed PMID: 26609282
- Ambiye VR, Langade D, Dongre S, Aptikar P, Kulkarni M, Dongre A (2013). Clinical evaluation of the spermatogenic activity of the root extract of ashwagandha in oligospermic males: a pilot study. Evidence-Based Complementary and Alternative Medicine. — PubMed PMID: 24371462
- Lopresti AL, Drummond PD, Smith SJ (2019). A randomized, double-blind, placebo-controlled, crossover study examining the hormonal and vitality effects of ashwagandha in aging, overweight males. American Journal of Men's Health. — PubMed PMID: 30854916
- Ziegenfuss TN et al. (2018). Effects of an aqueous extract of Withania somnifera on strength training adaptations and recovery: the STAR trial. Nutrients. — PubMed PMID: 30463324
- Mahdi AA, Shukla KK, Ahmad MK, Rajender S, Shankhwar SN, Singh V, Dalela D (2009). Withania somnifera improves semen quality in stress-related male fertility. Evidence-Based Complementary and Alternative Medicine. — PubMed
- Ahmad MK, Mahdi AA, Shukla KK, Islam N, Rajender S, Madhukar D, Shankhwar SN, Ahmad S (2010). Withania somnifera improves semen quality by regulating reproductive hormone levels and oxidative stress in seminal plasma of infertile males. Fertility and Sterility. — PubMed PMID: 19501822
- Gupta A, Mahdi AA, Shukla KK, Ahmad MK, Bansal N, Sankhwar P, Sankhwar SN (2013). Efficacy of Withania somnifera on seminal plasma metabolites of infertile males: a proton NMR study at 800 MHz. Journal of Ethnopharmacology. — PubMed PMID: 23796876
- Dongre S, Langade D, Bhattacharyya S (2015). Efficacy and safety of ashwagandha (Withania somnifera) root extract in improving sexual function in women: a pilot study. BioMed Research International. — PubMed PMID: 26504795
- Sandhu JS, Shah B, Shenoy S, Chauhan S, Lavekar GS, Padhi MM (2010). Effects of Withania somnifera (ashwagandha) and Terminalia arjuna (arjuna) on physical performance and cardiorespiratory endurance in healthy young adults. International Journal of Ayurveda Research. — PubMed
- Shenoy S, Chaskar U, Sandhu JS, Paadhi MM (2012). Effects of eight-week supplementation of Ashwagandha on cardiorespiratory endurance in elite Indian cyclists. Journal of Ayurveda and Integrative Medicine. — PubMed PMID: 23326093
- Pérez-Gómez J, Villafaina S, Adsuar JC, Merellano-Navarro E, Collado-Mateo D (2020). Effects of Ashwagandha (Withania somnifera) on VO2max: a systematic review and meta-analysis. Nutrients. — PubMed PMID: 32316411
- Durg S, Shivaram SB, Bavage S (2018). Withania somnifera (Indian ginseng) in male infertility: an evidence-based systematic review and meta-analysis. Phytomedicine. — PubMed PMID: 30466985
- Gopal S et al. (2021). Effect of an ashwagandha (Withania somnifera) root extract on climacteric symptoms in women during perimenopause. Journal of Obstetrics and Gynaecology Research. — PubMed PMID: 34553463
- Smith SJ, Lopresti AL, Teo SYM, Fairchild TJ (2021). Examining the effects of herbs on testosterone concentrations in men: a systematic review. Advances in Nutrition. — PubMed PMID: 33150931
- Björnsson HK, Björnsson ES, Avula B, Khan IA, Jonasson JG, Ghabril M, Hayashi PH, Navarro V (2020). Ashwagandha-induced liver injury: a case series from Iceland and the US Drug-Induced Liver Injury Network. Liver International. — PubMed PMID: 31991029
PubMed Topic Searches
- PubMed: Ashwagandha testosterone RCTs
- PubMed: Ashwagandha and sperm
- PubMed: Withania LH/FSH
- PubMed: Ashwagandha and resistance training
- PubMed: Steroidogenic mechanism
- PubMed: VO2max and endurance
- PubMed: Female libido
- PubMed: Perimenopause
- PubMed: Ashwagandha and DHEA
- PubMed: Cortisol-testosterone inverse
- PubMed: Ashwagandha root extract exercise trials
- PubMed: Spermatogenesis oxidative