Bloating

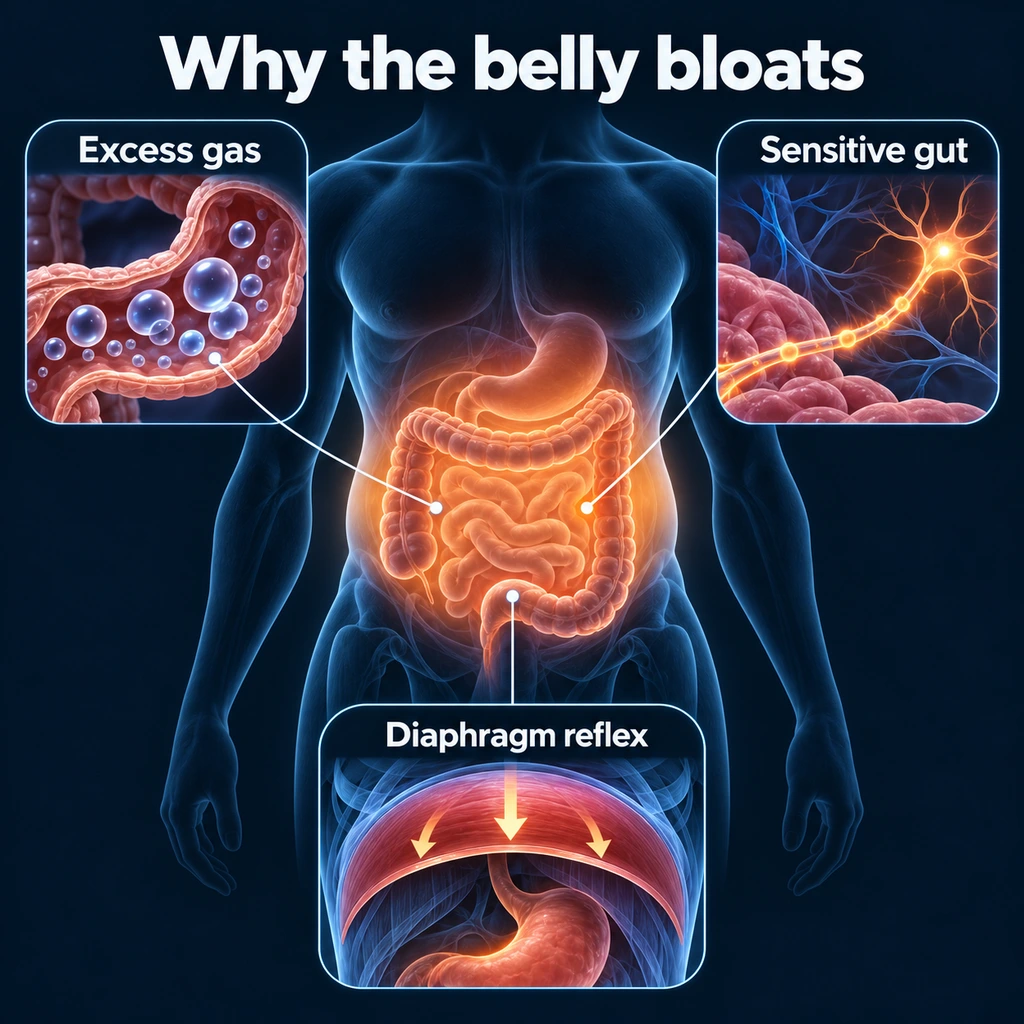
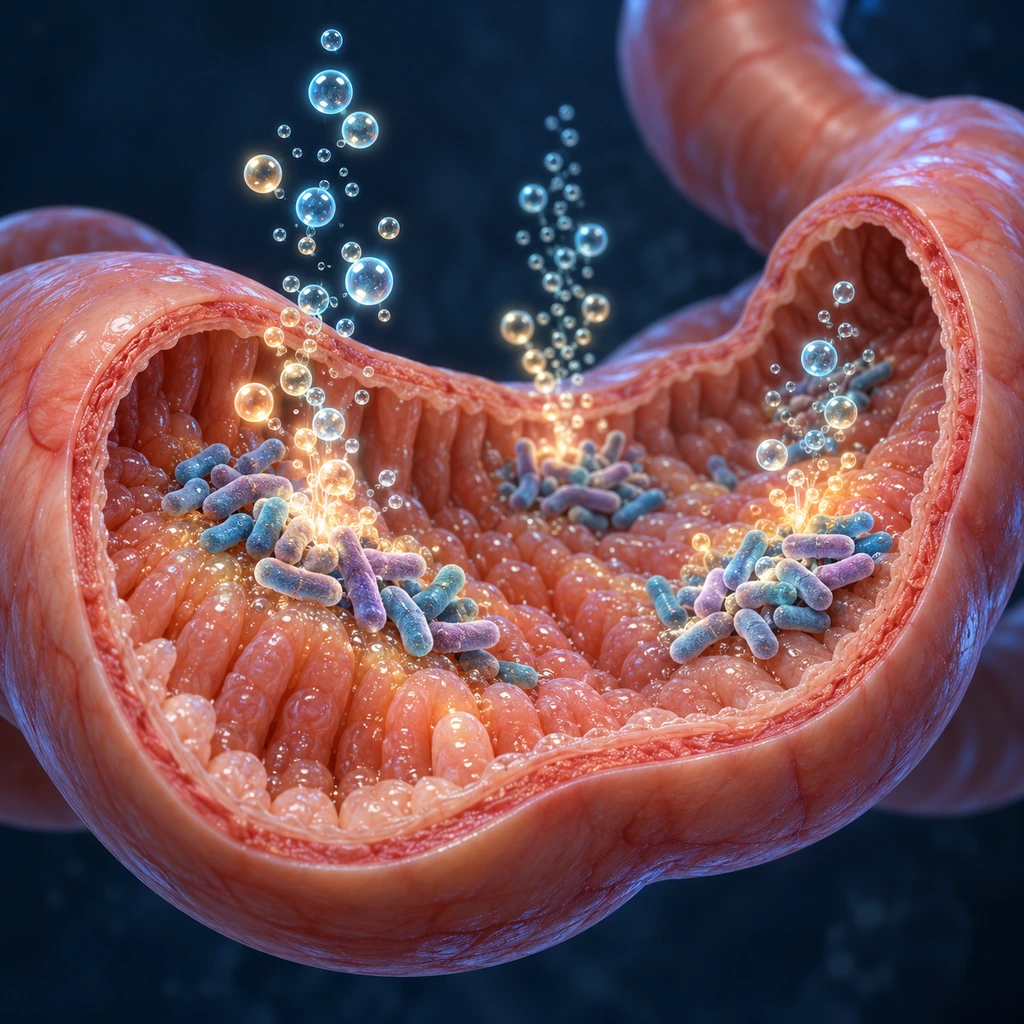
Table of Contents
Overview
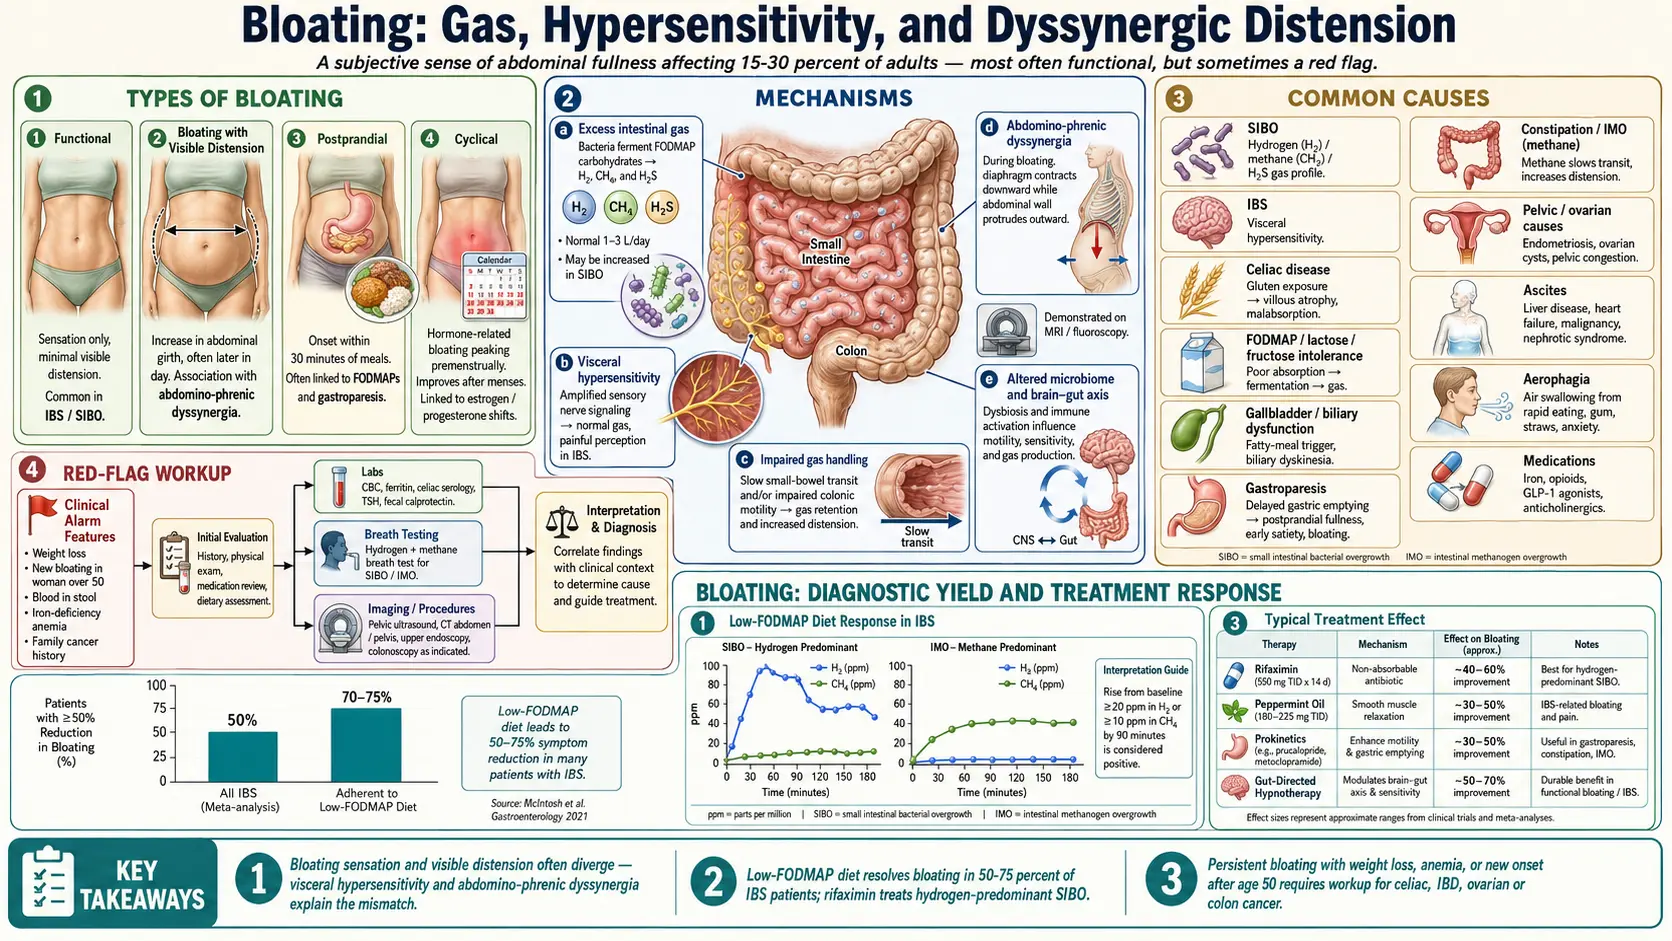
Bloating is the subjective sensation of abdominal fullness, pressure, or trapped gas. It is one of the most common gastrointestinal complaints. Estimates run from 15–30 percent of adults at any given time; in a survey of 51,425 people in 26 countries, nearly 18 percent reported bloating at least once a week, from 11 percent in East Asia to 20 percent in Latin America. In that survey women were about twice as likely as men to report it, it became less common with age, and 61.69 percent of people with weekly abdominal pain also had weekly bloating. A 2023 American Gastroenterological Association expert review says belching, bloating and distention “account for some of the most common reasons for patient visits to outpatient gastroenterology practices.” Bloating may or may not be accompanied by visible abdominal distension — an actual measurable increase in abdominal girth. Most bloating is benign and tied to diet, motility, or visceral hypersensitivity, but persistent bloating with weight loss, anemia, or change in bowel habits is a pattern doctors investigate for malignancy, celiac disease, or chronic obstruction.
Types of Bloating
- Functional bloating — sensation of pressure or fullness without an identifiable structural cause. Common in irritable bowel syndrome (IBS), functional dyspepsia, and small intestinal bacterial overgrowth (SIBO).
- Bloating with distension — both the sensation and a visible increase in girth. Often involves abdomino-phrenic dyssynergia, where the diaphragm pushes down and the abdominal wall protrudes outward in response to even normal gas volumes.
- Postprandial bloating — develops within 30 minutes to a few hours of eating and resolves overnight. Typical of food intolerances (lactose, fructose, and fermentable oligosaccharides, disaccharides, monosaccharides and polyols, known as FODMAPs), gastroparesis, and gallbladder disease.
- Persistent or progressive bloating — present most days, gradually worsening, or accompanied by enlarging abdominal girth. Doctors investigate this pattern for ascites, ovarian pathology, malignancy, or chronic bowel obstruction.
- Cyclical bloating — tied to the menstrual cycle, peaking premenstrually. Driven by hormonal effects on bowel motility and fluid retention.
Common Causes
- Small intestinal bacterial overgrowth (SIBO) — bacteria normally confined to the colon ferment carbohydrates in the small intestine, producing hydrogen, methane, or hydrogen sulfide gas. The hallmark is bloating that worsens through the day and after meals.
- Irritable bowel syndrome (IBS) — the most common functional cause. Bloating in irritable bowel syndrome reflects visceral hypersensitivity to normal gas volumes plus altered motility.
- Celiac disease — gluten-driven small-bowel inflammation impairs digestion of carbohydrates, causing fermentation and bloating along with diarrhea, weight loss, and nutrient deficiencies.
- Lactose, fructose, and FODMAP intolerance — undigested fermentable carbohydrates reach the colon and are fermented by bacteria, producing gas.
- Gallbladder disease and biliary dysfunction — impaired bile flow leaves fat poorly emulsified, leading to maldigestion, postprandial fullness, and bloating, particularly after fatty meals.
- Gastroparesis — delayed gastric emptying, often from diabetes or post-viral nerve injury, produces fullness, early satiety, and bloating after meals.
- Constipation — slow colonic transit allows more time for fermentation and gas accumulation. Common in methane-predominant small intestinal bacterial overgrowth, also called intestinal methanogen overgrowth (IMO) and hypothyroidism.
- Pelvic and gynecologic causes — ovarian cysts, fibroids, endometriosis, and ovarian cancer can present with bloating and an enlarging abdominal girth.
- Ascites — fluid accumulation in the peritoneal cavity from cirrhosis, heart failure, malignancy, or nephrotic syndrome.
- Aerophagia — air swallowing from chewing gum, carbonated drinks, smoking, or anxiety.
- Medications — iron supplements, opioids, calcium-channel blockers, glucagon-like peptide-1 (GLP-1) agonists, and some antidepressants commonly cause bloating.
Mechanisms
Bloating arises from several overlapping mechanisms, and most patients have more than one operating at once:
- Excess intestinal gas — normal flora produce 1–3 liters of gas per day from fermentable carbohydrates. SIBO, FODMAP intolerance, and rapid transit can multiply this many times over.
- Visceral hypersensitivity — the gut perceives normal gas volumes as painful or distending. This is the dominant mechanism in irritable bowel syndrome and explains why total measured gas volumes often look normal in patients who feel severely bloated.
- Abnormal gas handling — impaired ability to propel and expel gas. Patients may have normal amounts of gas but slow transit through the small bowel.
- Abdomino-phrenic dyssynergia — an abnormal motor reflex in which the diaphragm contracts downward and the anterior abdominal wall relaxes in response to gas, producing visible distension out of proportion to gas volume. Identified by magnetic resonance imaging (MRI) or fluoroscopy.
- Altered microbiome — both composition (which species dominate) and location (small bowel vs. colon) influence which substrates are fermented and which gases are produced.
- Brain-gut axis — stress and emotional arousal modulate motility, secretion, and pain perception, often amplifying bloating.
Evaluation
Initial workup is guided by the pattern (functional vs. progressive, postprandial vs. persistent) and any alarm features. The tests commonly used at the start include:
- History and dietary review — timing, triggers, FODMAP exposure, alcohol, fiber load, recent antibiotics, weight change, bowel-habit change.
- Complete blood count, ferritin, comprehensive metabolic panel — screen for anemia, malnutrition, liver dysfunction.
- Celiac serology — tissue transglutaminase immunoglobulin A (IgA) with total immunoglobulin A. The test is run while the person is still eating gluten.
- Thyroid-stimulating hormone (TSH) — rule out hypothyroidism as a constipation/bloating driver.
- Fecal calprotectin — differentiates inflammatory from functional causes.
- Hydrogen and methane breath testing — for SIBO, IMO, and lactose/fructose malabsorption. See the Breath Test Guide for prep, interpretation, and pitfalls.
- Stool studies — ova and parasites, Giardia antigen, fecal elastase (pancreatic insufficiency).
- Abdominal imaging — ultrasound or computed tomography (CT) for ascites, mass, or biliary disease. Pelvic ultrasound for ovarian pathology in women.
- Upper endoscopy with biopsy — if celiac is suspected and serology is positive, or if symptoms include reflux, dysphagia, or anemia.
- Colonoscopy — in patients over 45, with iron deficiency, blood in stool, or unexplained weight loss.
The 2023 American Gastroenterological Association review sorts the costlier tests by situation. It states that abdominal imaging and upper endoscopy are for people with alarm features, recent worsening symptoms, or an abnormal physical examination only, and that gastric emptying studies are not ordered routinely for bloating and distention, though they may be considered if nausea and vomiting are present.
Management
- Treating the underlying cause — rifaximin for hydrogen-predominant small intestinal bacterial overgrowth, gluten-free diet for celiac, levothyroxine for hypothyroidism, prokinetics for gastroparesis. See Rifaximin Protocols for small intestinal bacterial overgrowth dosing.
- Low-FODMAP diet — an elimination-and-reintroduction protocol that resolves bloating in 50–75 percent of irritable bowel syndrome patients. In a crossover trial of 30 people with irritable bowel syndrome, overall symptom scores on a 0–100 mm scale were 22.8 mm on the diet against 44.9 mm on a typical Australian diet, with bloating, pain and passage of wind also reduced. The 2023 American Gastroenterological Association review states that “a gastroenterology dietitian should preferably monitor treatment”; the reintroduction stage exists so that restriction does not stay long-term without need. See the Low-FODMAP Diet overview.
- Targeted food avoidance — lactose, fructose, sugar alcohols (sorbitol, mannitol), and excessive fiber are the most common triggers.
- Prokinetics — low-dose erythromycin, prucalopride, or metoclopramide can improve transit and reduce postprandial bloating; particularly important for small intestinal bacterial overgrowth relapse prevention. See Prokinetics & Relapse Prevention.
- Peppermint oil — enteric-coated peppermint oil reduces bloating and pain in irritable bowel syndrome through smooth-muscle relaxation, supported by multiple meta-analyses. A 2020 Dutch trial of 189 people with irritable bowel syndrome found no significant difference from placebo on its two official endpoints (abdominal pain response 46.8 percent with small-intestinal-release capsules, 34.4 percent with placebo). The small-intestinal-release capsules did reduce abdominal pain, discomfort and symptom severity on secondary measures, and mild side effects were more common with peppermint oil.
- Probiotics — mixed evidence; some strains (Bifidobacterium infantis 35624) modestly reduce bloating in irritable bowel syndrome, while others worsen it in small intestinal bacterial overgrowth. The 2023 American Gastroenterological Association review states: “Probiotics should not be used to treat abdominal bloating and distention.”
- Digestive enzymes — lactase for lactose intolerance, alpha-galactosidase for legume bloating, pancreatic enzymes for documented insufficiency.
- Diaphragmatic breathing and biofeedback — useful for abdomino-phrenic dyssynergia; teaches the diaphragm to relax upward rather than push down. A 2024 randomized placebo-controlled trial tested biofeedback in 42 people with meal-triggered visible swelling. Those who learned to move the diaphragm, using belts that showed their chest and abdominal wall motion, had distention scores fall by about 66 percent; this was not seen in the placebo group.
- Stress management — gut-directed hypnotherapy and cognitive-behavioral therapy reduce visceral hypersensitivity and have effect sizes comparable to pharmacotherapy in irritable bowel syndrome. In a network analysis of 41 trials and 4,072 people, the relative risk of remaining symptomatic was 0.67 with gut-directed hypnotherapy and 0.62 with face-to-face cognitive behavioral therapy; risk of bias was high, and the authors state efficacy is “likely to have been overestimated.”
- Movement — light walking after meals accelerates transit and reduces postprandial bloating.
Warning Signs Doctors Investigate
- Bloating accompanied by unintentional weight loss, especially in adults over 40.
- New-onset bloating in a woman over 50 (ovarian cancer is one cause doctors check for).
- Rapidly progressive abdominal distension or visibly enlarging girth.
- Blood in stool, black or tarry stool, or persistent change in bowel habits.
- Severe persistent abdominal pain, especially with fever or vomiting.
- Iron-deficiency anemia, low albumin, or other signs of malabsorption.
- Bloating with shortness of breath, leg swelling, or known liver or heart disease (a pattern seen with ascites).
- Family history of colon, ovarian, or pancreatic cancer with new persistent bloating.
Connections
- All Symptoms
- Small Intestinal Bacterial Overgrowth
- Irritable Bowel Syndrome
- IMO & Methane Constipation
- Celiac Disease
- Gallbladder Disease
- Small Intestinal Bacterial Overgrowth Breath Test Guide
- Rifaximin Protocols
- Low-FODMAP Diet
- Thyroid Disorders
- Gut Healing
- Abdominal Pain
- Prokinetics & Relapse Prevention
- Gastroesophageal Reflux Disease
- Nausea and Vomiting
- Small Intestinal Bacterial Overgrowth Root Causes
- Pancreatitis
- Probiotics
- Elimination Diet
- Ovarian Cancer
- Herbs covered on this site that discuss this condition: Dandelion (Taraxacum officinale) · Carum / Ajwain (Trachyspermum ammi) · Fennel (Foeniculum vulgare) · Chamomile (Matricaria chamomilla) · Ginger (Zingiber officinale) · Peppermint (Mentha × piperita)
Key Research Papers
Historical Background
Bloating was long dismissed as a vague functional complaint until the late twentieth century, when manometric studies, breath testing, and abdominal imaging made it possible to distinguish gas accumulation from visceral hypersensitivity from abnormal abdominal-wall mechanics. The rediscovery of small intestinal bacterial overgrowth in the 1990s and the formalization of low-FODMAP dietary therapy by Monash University in the 2000s gave clinicians their first reproducible, evidence-based interventions for chronic bloating.
Key Research Papers
- Lacy BE, Cangemi D, Vazquez-Roque M. Management of chronic abdominal distension and bloating. Clinical Gastroenterology and Hepatology. 2021;19(2):219-231. — doi:10.1016/j.cgh.2020.03.056
- Halmos EP, Power VA, Shepherd SJ, Gibson PR, Muir JG. A diet low in FODMAPs reduces symptoms of irritable bowel syndrome. Gastroenterology. 2014;146(1):67-75. — doi:10.1053/j.gastro.2013.09.046
- Pimentel M, Lembo A, Chey WD, et al. Rifaximin therapy for patients with irritable bowel syndrome without constipation. New England Journal of Medicine. 2011;364(1):22-32. — doi:10.1056/nejmoa1004409
- Villoria A, Azpiroz F, Burri E, Cisternas D, Soldevilla A, Malagelada JR. Abdomino-phrenic dyssynergia in patients with abdominal bloating and distension. American Journal of Gastroenterology. 2011;106(5):815-819. — doi:10.1038/ajg.2010.408
- Rezaie A, Buresi M, Lembo A, et al. Hydrogen and methane-based breath testing in gastrointestinal disorders: the North American consensus. American Journal of Gastroenterology. 2017;112(5):775-784. — PubMed PMID: 28323273
- Chey WD, Kurlander J, Eswaran S. Irritable bowel syndrome: a clinical review. JAMA. 2015;313(9):949-958. — doi:10.1001/jama.2015.0954
- Pimentel M, Saad RJ, Long MD, Rao SSC. ACG clinical guideline: small intestinal bacterial overgrowth. American Journal of Gastroenterology. 2020;115(2):165-178. — doi:10.14309/ajg.0000000000000501
- Mearin F, Lacy BE, Chang L, et al. Bowel disorders. Gastroenterology. 2016;150(6):1393-1407. — doi:10.1053/j.gastro.2016.02.031 (Rome IV criteria)
- Khanna R, MacDonald JK, Levesque BG. Peppermint oil for the treatment of irritable bowel syndrome: a systematic review and meta-analysis. Journal of Clinical Gastroenterology. 2014;48(6):505-512. — PubMed PMID: 24100754
- Ford AC, Sperber AD, Corsetti M, Camilleri M. Irritable bowel syndrome. The Lancet. 2020;396(10263):1675-1688. — doi:10.1016/S0140-6736(20)31548-8
- Moshiree B, Drossman D, Shaukat A. AGA Clinical Practice Update on Evaluation and Management of Belching, Abdominal Bloating, and Distention: Expert Review. Gastroenterology. 2023;165(3):791-800.e3. — PubMed PMID: 37452811
- Ballou S, Singh P, Nee J, et al. Prevalence and Associated Factors of Bloating: Results From the Rome Foundation Global Epidemiology Study. Gastroenterology. 2023;165(3):647-655.e4. — PubMed PMID: 37315866
- Barba E, Livovsky DM, Accarino A, Azpiroz F. Thoracoabdominal Wall Motion-Guided Biofeedback Treatment of Abdominal Distention: A Randomized Placebo-Controlled Trial. Gastroenterology. 2024;167(3):538-546.e1. — PubMed PMID: 38467383
- Weerts ZZRM, Masclee AAM, Witteman BJM, et al. Efficacy and Safety of Peppermint Oil in a Randomized, Double-Blind Trial of Patients With Irritable Bowel Syndrome. Gastroenterology. 2020;158(1):123-136. — PubMed PMID: 31470006
- Black CJ, Thakur ER, Houghton LA, et al. Efficacy of psychological therapies for irritable bowel syndrome: systematic review and network meta-analysis. Gut. 2020;69(8):1441-1451. — PubMed PMID: 32276950
PubMed Topic Searches
Featured Videos