Estimated Glomerular Filtration Rate (eGFR): Stages and Interpretation
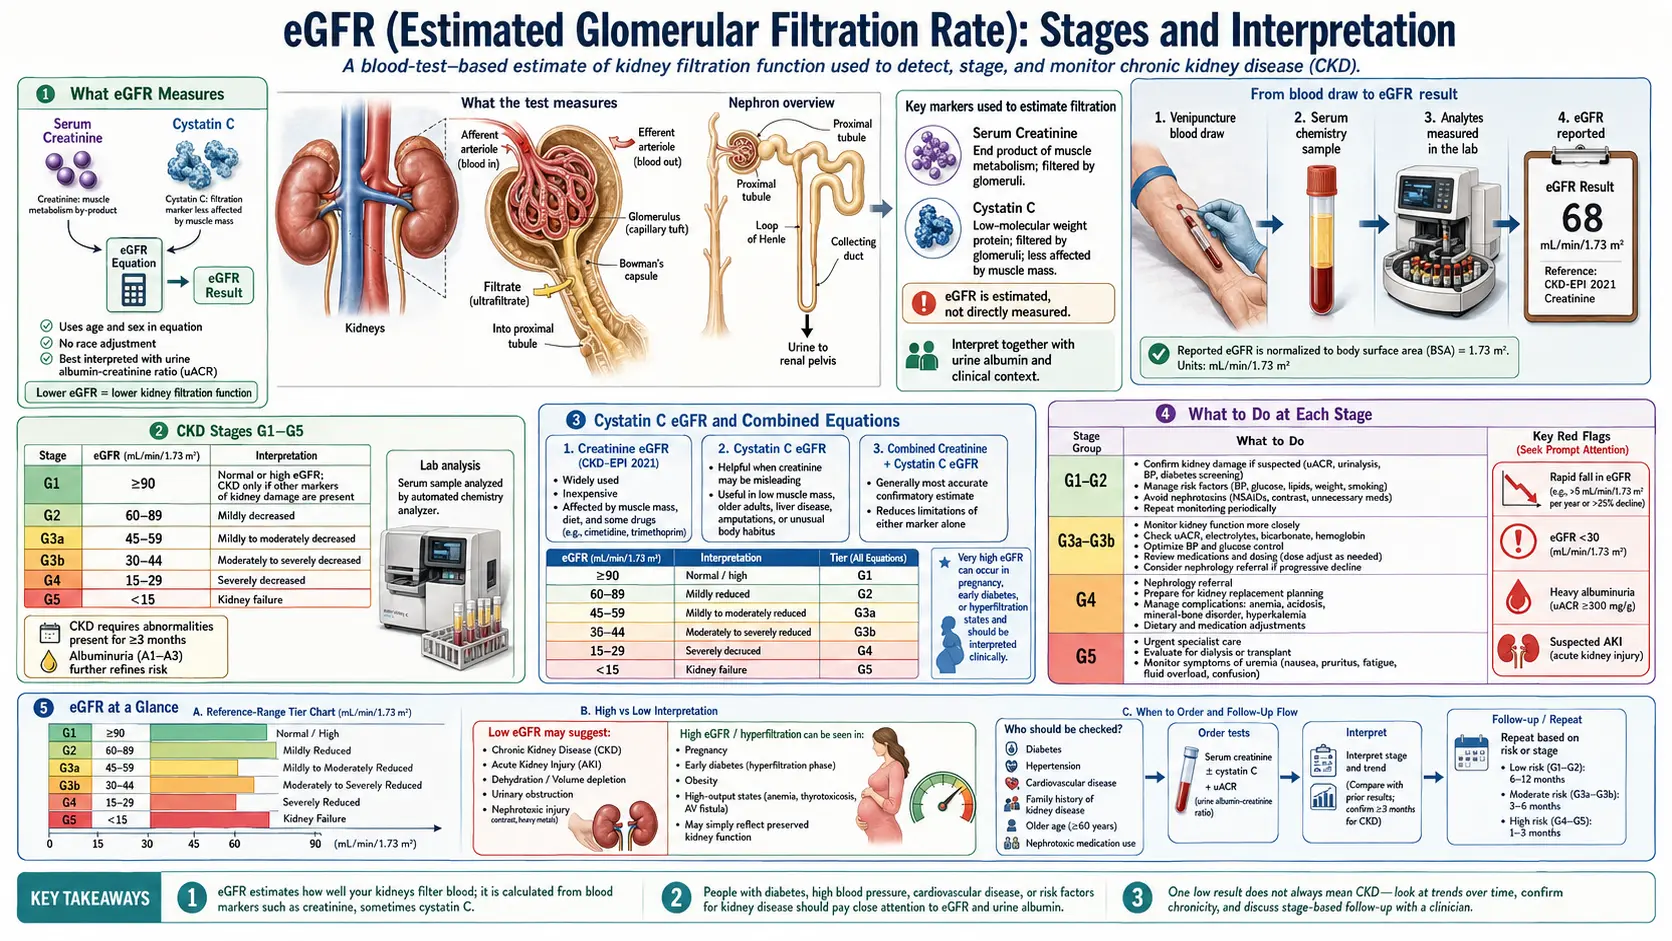
Estimated glomerular filtration rate (eGFR) is the single most important number for staging chronic kidney disease. It is not measured directly — it is calculated from serum creatinine using a regression equation that adjusts for age and sex. The current US standard is the 2021 race-free CKD-EPI equation, which replaced the 2009 version after a 2020 NKF/ASN task force recommended dropping the race coefficient. Combined with urine albumin-to-creatinine ratio (ACR), eGFR forms the backbone of chronic kidney disease (CKD) diagnosis, staging, and risk stratification.
Interactive Visualization Kidney Nephron — watch blood become urine Follow blood into the glomerulus and see filtration and reabsorption turn 180 litres of filtrate into urine — then toggle dehydration or diabetes. Launch →Table of Contents
- What Estimated Glomerular Filtration Rate Measures
- The Equations: CKD-EPI 2021
- Reference Range
- Chronic Kidney Disease Stages G1–G5
- Combined G/A Staging
- Where Estimated Glomerular Filtration Rate Misleads
- Cystatin C Estimated Glomerular Filtration Rate and Combined Equations
- Trajectory Matters More Than Snapshots
- What to Do at Each Stage
- Key Research Papers
- Connections
- Featured Videos
What Estimated Glomerular Filtration Rate Measures
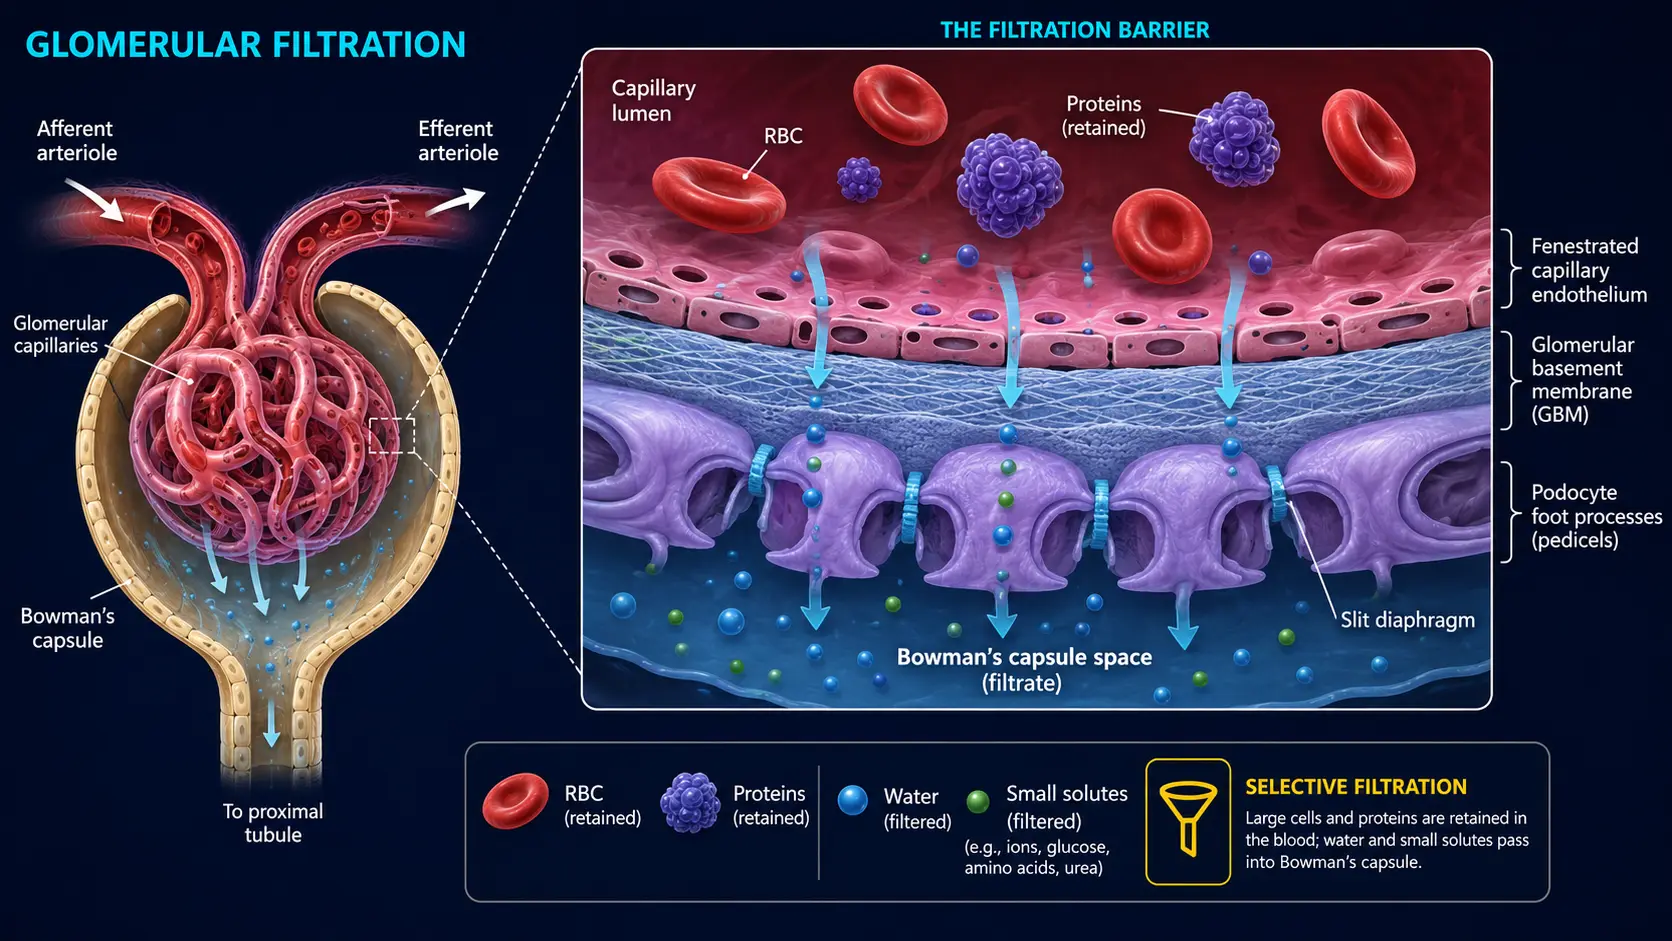
The glomerular filtration rate is the volume of plasma the kidneys clear per minute, normalized to a body surface area of 1.73 m². A young, healthy adult typically has a measured glomerular filtration rate (GFR) around 100–130 mL/min/1.73 m². The "estimated" prefix indicates that the number on your lab report comes from a formula, not a direct measurement of inulin clearance or iohexol clearance (the gold standards, used mainly in research and transplant evaluation).
Estimated glomerular filtration rate is the variable used to stage chronic kidney disease, decide which medications to start or stop, dose-adjust drugs cleared renally, time pre-dialysis education and vascular access creation, and counsel patients about prognosis. Most clinical decisions are anchored to estimated glomerular filtration rate rather than serum creatinine alone, because estimated glomerular filtration rate adjusts for the demographic factors that bend the creatinine–glomerular filtration rate relationship.
The Equations: CKD-EPI 2021
The 2021 CKD-EPI creatinine equation uses serum creatinine, age, and sex (no race coefficient). For most patients, the formula yields:
- Female, creatinine ≤ 0.7 mg/dL: estimated glomerular filtration rate = 142 × (Cr/0.7)-0.241 × 0.9938age × 1.012
- Female, creatinine > 0.7 mg/dL: estimated glomerular filtration rate = 142 × (Cr/0.7)-1.200 × 0.9938age × 1.012
- Male, creatinine ≤ 0.9 mg/dL: estimated glomerular filtration rate = 142 × (Cr/0.9)-0.302 × 0.9938age
- Male, creatinine > 0.9 mg/dL: estimated glomerular filtration rate = 142 × (Cr/0.9)-1.200 × 0.9938age
You don't need to compute it by hand — every modern laboratory information system reports estimated glomerular filtration rate alongside serum creatinine. Online calculators are available at the National Kidney Foundation site if you ever need to recompute one yourself.
Why the change from the 2009 equation? The 2009 CKD-EPI equation included a race coefficient that multiplied results by 1.16 for Black patients. This systematically over-estimated estimated glomerular filtration rate in Black patients, delaying chronic kidney disease diagnosis, transplant listing, and nephrology referral. The 2021 equation drops the coefficient. Most laboratories transitioned during 2022–2023.
Reference Range
Estimated glomerular filtration rate (mL/min/1.73 m²)
The "normal" range collapses with age. A measured glomerular filtration rate of 70 mL/min/1.73 m² in an 80-year-old is consistent with healthy aging; the same value in a 30-year-old is a red flag. Estimated glomerular filtration rate formulas already adjust for age, but the population reference at age 80 is meaningfully lower than at age 30.
Chronic Kidney Disease Stages G1–G5
The KDIGO 2012 framework defines six G-stages based on estimated glomerular filtration rate:
- G1 — estimated glomerular filtration rate ≥ 90: normal or high. Considered chronic kidney disease only with concomitant albuminuria, structural abnormalities, or known kidney pathology.
- G2 — estimated glomerular filtration rate 60–89: mildly decreased. Same caveat as G1; mild reduction alone does not equal chronic kidney disease.
- G3a — estimated glomerular filtration rate 45–59: mildly to moderately decreased. Chronic kidney disease diagnosed regardless of other findings if persistent ≥ 3 months.
- G3b — estimated glomerular filtration rate 30–44: moderately to severely decreased. Risk of cardiovascular events and progression rises sharply; nephrology consultation recommended.
- G4 — estimated glomerular filtration rate 15–29: severely decreased. Mandatory nephrology involvement; patient education on dialysis modalities and transplant; vascular access planning if hemodialysis is anticipated.
- G5 — estimated glomerular filtration rate < 15: kidney failure. Dialysis or transplant evaluation; symptomatic uremia is common.
Combined G/A Staging
KDIGO recommends combining G stage with A stage (urine ACR) because albuminuria predicts cardiovascular events and progression independently of estimated glomerular filtration rate:
- A1: ACR < 30 mg/g (normal to mildly increased)
- A2: ACR 30–300 mg/g (moderately increased; formerly "microalbuminuria")
- A3: ACR > 300 mg/g (severely increased; formerly "macroalbuminuria")
The combined stage (e.g., G3a A2) maps onto risk categories: green (low risk), yellow (moderate), orange (high), red (very high). A patient with estimated glomerular filtration rate 65 (G2) and ACR 250 (A2) has higher cardiovascular and progression risk than a patient with estimated glomerular filtration rate 50 (G3a) and ACR 10 (A1).
Where Estimated Glomerular Filtration Rate Misleads
Because estimated glomerular filtration rate is calculated from creatinine, every limitation of creatinine carries through. The most common pitfalls:
- Extremes of muscle mass — estimated glomerular filtration rate overestimates glomerular filtration rate in frail, sarcopenic, or amputee patients (creatinine is low because of low muscle, not good filtration). It underestimates in heavily muscled patients (creatinine is high because of high muscle). Use cystatin C-based estimated glomerular filtration rate in either case.
- Acute kidney injury — estimated glomerular filtration rate formulas assume steady-state creatinine. During acute kidney injury (AKI), creatinine is rising rapidly, so estimated glomerular filtration rate computed from a single creatinine value overestimates current glomerular filtration rate.
- Pregnancy — physiologic hyperfiltration; standard estimated glomerular filtration rate formulas underestimate true glomerular filtration rate. Pregnancy-specific equations exist but are seldom used clinically.
- Drug-induced creatinine bumps — cimetidine, trimethoprim, fenofibrate, cobicistat, dolutegravir all raise serum creatinine without changing glomerular filtration rate; estimated glomerular filtration rate will appear to drop.
- Children — CKD-EPI is for adults; pediatric nephrology uses the Bedside Schwartz formula.
- Borderline ranges — the difference between an estimated glomerular filtration rate of 58 and 62 is within the equation's confidence interval. Trends over months matter more than single readings near the cut-off.
Cystatin C Estimated Glomerular Filtration Rate and Combined Equations
The 2021 CKD-EPI race-free cystatin C equation gives an estimated glomerular filtration rate independent of muscle mass. The 2021 CKD-EPI creatinine + cystatin C combined equation outperforms either alone in research validation studies. KDIGO 2024 guidelines recommend combined-equation estimated glomerular filtration rate when the creatinine-only result seems implausible for the patient's body composition or when an early chronic kidney disease diagnosis would change management. See the Cystatin C page for a deeper walk-through.
Trajectory Matters More Than Snapshots
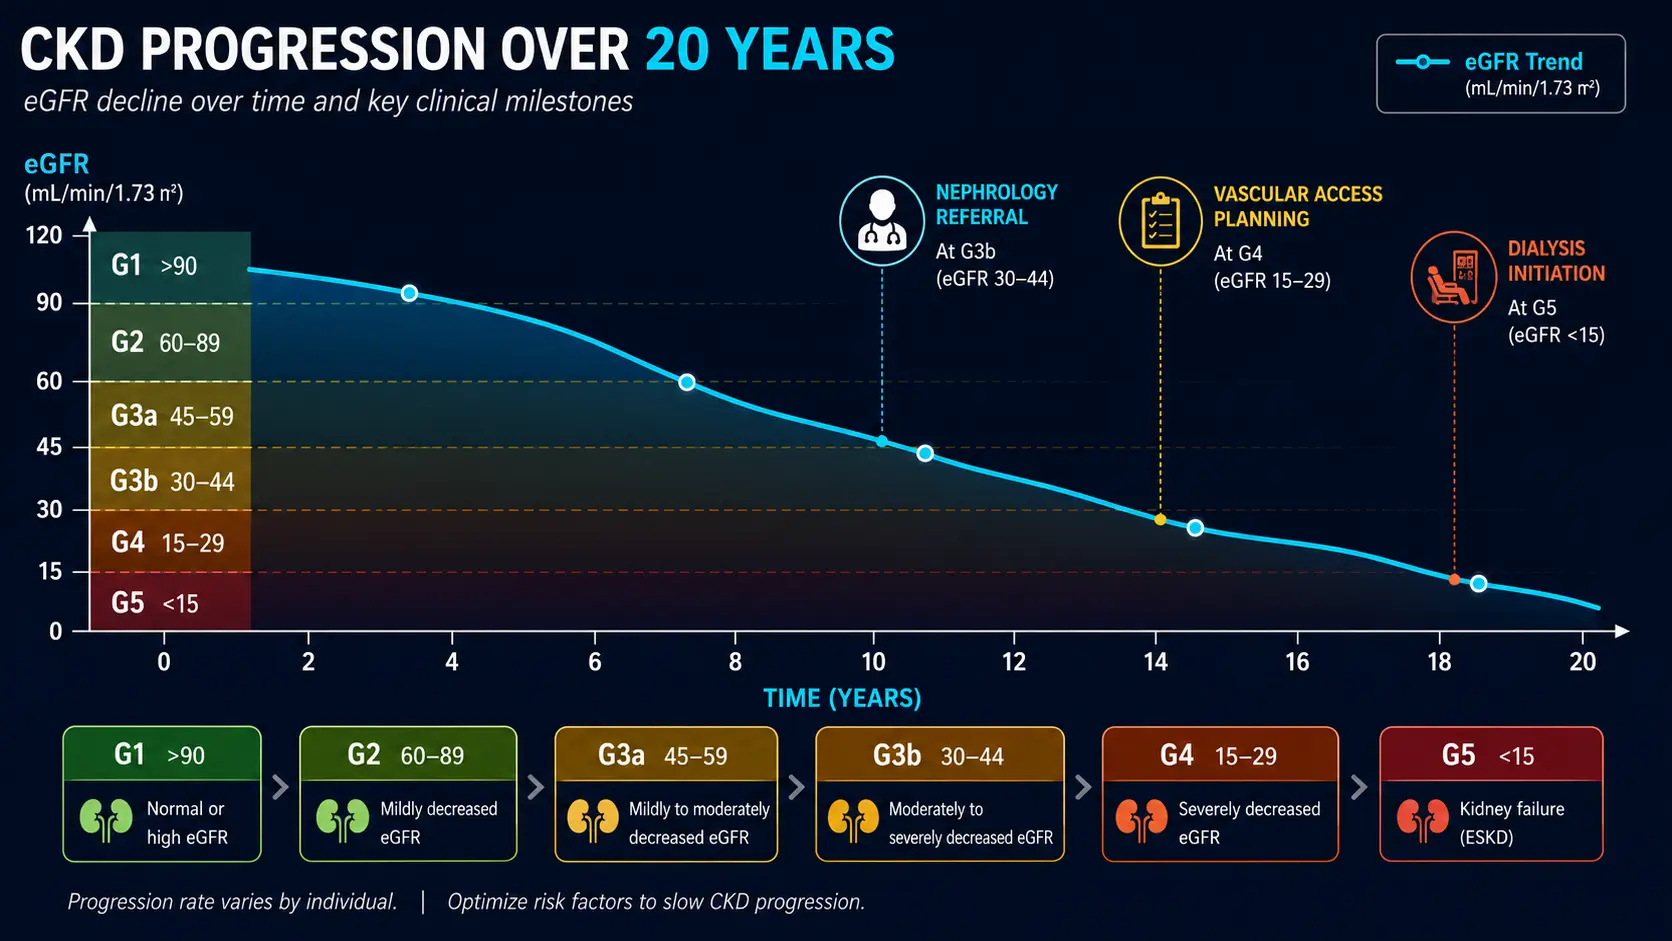
A single estimated glomerular filtration rate is a snapshot. Two trajectories tell two completely different stories:
- Stable chronic kidney disease — estimated glomerular filtration rate around 50 for 5 years. Low risk of dialysis. Manage cardiovascular risk, treat blood pressure, keep blood sugar in range.
- Rapidly progressive chronic kidney disease — estimated glomerular filtration rate has dropped from 75 to 50 in 18 months. Mandatory nephrology referral; rule out reversible causes (obstruction, drugs, autoimmune disease, untreated hypertension).
A loss of more than 5 mL/min/1.73 m² per year is "rapid progression" and warrants intensive workup. The slope, not any single value, drives prognosis.
What to Do at Each Stage
G1–G2 (estimated glomerular filtration rate ≥ 60): Annual screening if at risk (diabetes, hypertension, family history, nonsteroidal anti-inflammatory drugs (NSAIDs), lithium). Treat blood pressure to < 130/80, optimize hemoglobin A1c (HbA1c), avoid chronic nonsteroidal anti-inflammatory drugs, hydrate around contrast.
G3a (estimated glomerular filtration rate 45–59): Confirm with a repeat in 3 months (chronic kidney disease requires persistence). Add angiotensin-converting enzyme inhibitor (ACE inhibitor) or angiotensin receptor blocker (ARB) if proteinuric or hypertensive. Add sodium-glucose cotransporter-2 (SGLT2) inhibitor if diabetic. Annual check of complete blood count (CBC) (anemia of chronic kidney disease), calcium/phosphate/parathyroid hormone (PTH), and vitamin D.
G3b (estimated glomerular filtration rate 30–44): Nephrology consult. Avoid contrast where possible; dose-adjust medications. Active management of bone-mineral disease (phosphate binders if needed). Monitor potassium tightly.
G4 (estimated glomerular filtration rate 15–29): Multidisciplinary chronic kidney disease clinic. Vascular access planning (hemodialysis fistula if > 6 months anticipated). Transplant evaluation. Dietary potassium and phosphate restriction. Anemia management (iron, ESA).
G5 (estimated glomerular filtration rate < 15): Dialysis initiation when symptomatic or when biochemical/fluid issues become unmanageable. Pre-emptive transplant if feasible.
For supportive measures across all stages: anti-inflammatory diet, blood sugar protocols, magnesium, and reviewing the medication list at every visit are the highest-leverage habits.
Key Research Papers
- 2021 race-free CKD-EPI equation — PubMed search
- KDIGO CKD staging guidelines — PubMed search
- EGFR slope and CKD progression — PubMed search
- Cystatin C combined eGFR — PubMed search
- Combined G/A staging and outcomes — PubMed search
- SGLT2 inhibitors and eGFR protection — PubMed search
- ACE inhibitors and CKD progression — PubMed search
External Authoritative Resources
Connections
- All Lab Tests
- Kidney Nephron — interactive animation
- Understanding Your Estimated Glomerular Filtration Rate & Chronic Kidney Disease Stage
- Cystatin C
- Creatinine
- Blood Urea Nitrogen
- Kidney Function Tests
- Comprehensive Metabolic Panel
- Urinalysis
- Kidney Disease
- Acute Kidney Injury
- Hypertension
- Diabetes
- Anemia
- Magnesium
- Potassium
- Anti-Inflammatory Diet
- Blood Sugar
- Phosphorus
- Gout
- Hyperparathyroidism