Bone Loss Prevention & Hormone Replacement Therapy (HRT)
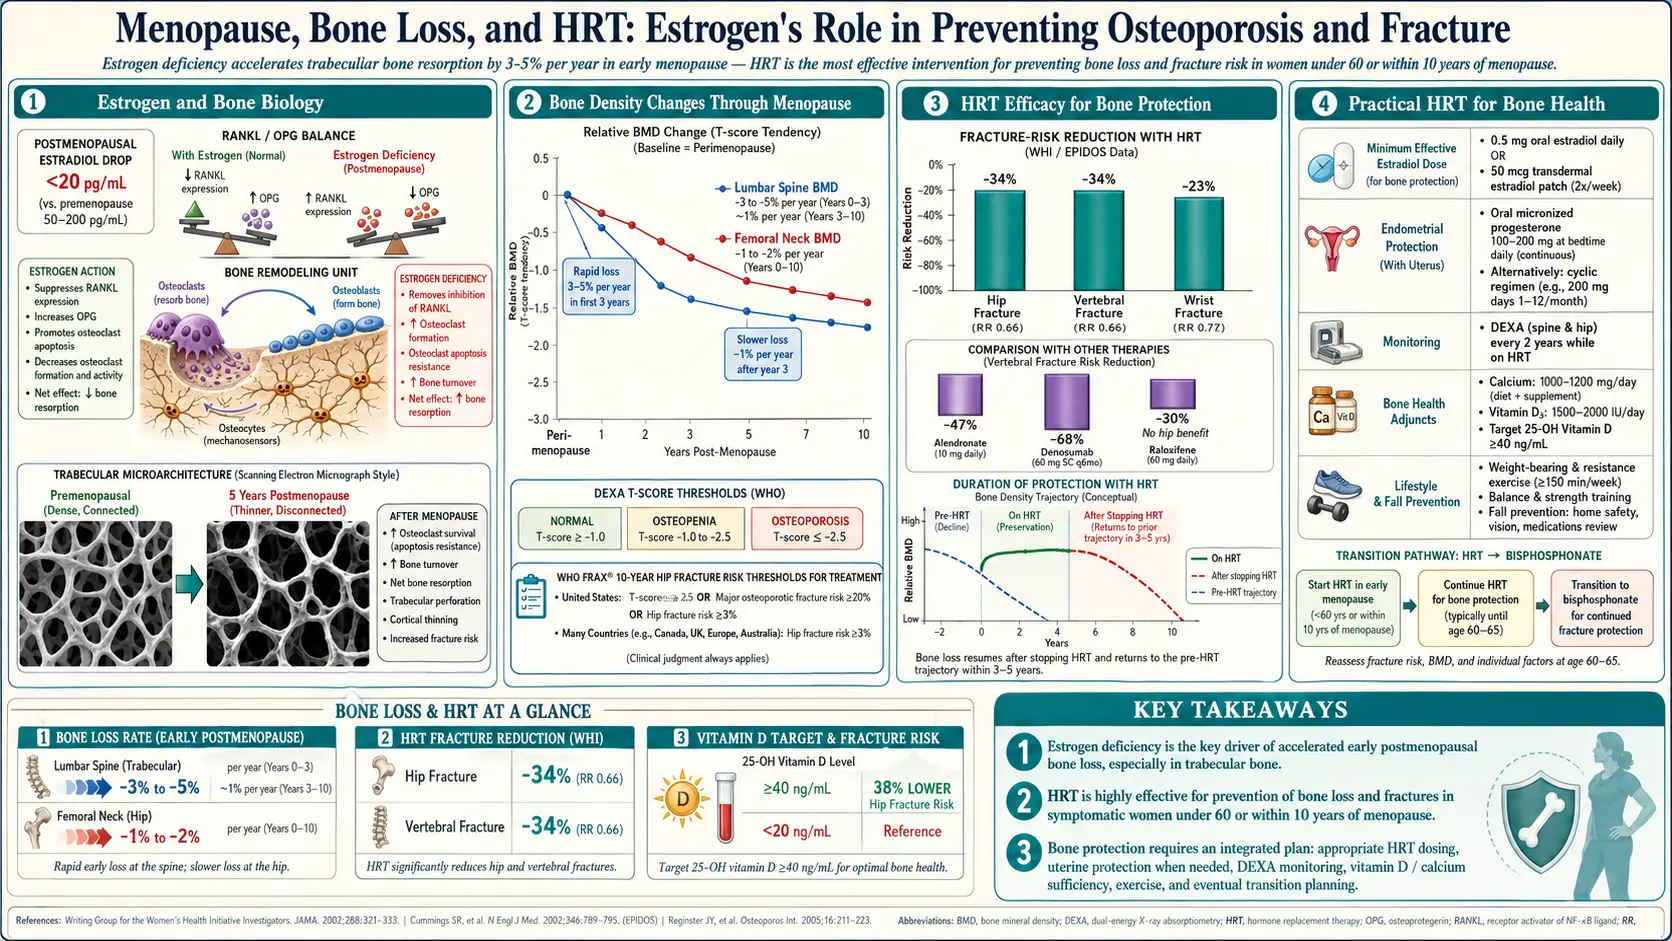
Estrogen is the single most important hormone regulating your skeleton. When it falls at menopause, bone loss accelerates quickly — and for many women, that accelerated loss is the first event that will eventually cause a fracture in their seventies or eighties. This page walks through why that happens, what hormone therapy (hormone replacement therapy, HRT) does to stop it, how hormone replacement therapy compares to the drugs osteoporosis specialists usually reach for (bisphosphonates and denosumab), and which women menopause guidelines describe as candidates for hormone replacement therapy as a bone treatment, as one part of it, or not at all.
This is a patient-facing guide. It is rigorous about numbers and studies, but written for you, not a rheumatology fellow.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone (FSH) climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →Table of Contents
- Why Menopause Accelerates Bone Loss
- What the WHI Actually Showed for Bone
- The U.S. Food and Drug Administration Indication People Forget About
- Who Is a Candidate for Hormone Replacement Therapy-First Bone Strategy
- Effective Doses — Low-Dose Transdermal Works
- Hormone Replacement Therapy vs Bisphosphonates vs Denosumab
- What Happens When You Stop Hormone Replacement Therapy
- Calcium, Vitamin D, K2, and Protein
- Resistance Training and Impact Exercise
- DEXA Intervals and the FRAX Score
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
Why Menopause Accelerates Bone Loss
Bone is living tissue. All through adulthood, small crews of cells called osteoclasts chew away old bone while osteoblasts lay down new bone behind them. As long as the two crews are balanced, your bones stay the same density. Estrogen is one of the referees that keeps them balanced.
Estrogen works largely through a pair of signalling molecules called RANKL (which tells osteoclasts to form and start dissolving bone) and OPG (which blocks RANKL and protects bone). When estrogen is high, OPG is high and osteoclast activity is restrained. When estrogen falls at menopause, RANKL shoots up relative to OPG, osteoclasts become over-active, and bone is dissolved faster than it can be rebuilt.
The practical result: during the first 5–10 years after your final period, most women lose bone mineral density (BMD) at roughly 1–3% per year at the spine and 1–2% per year at the hip. In the first 1–2 years after menopause, trabecular (spongy) bone in the spine can lose as much as 5% in a single year. By age 70, a woman who never used hormone replacement therapy has typically lost 25–30% of her peak bone mass. That is the trajectory that turns into hip fractures at 80.
What the WHI Actually Showed for Bone
The Women's Health Initiative (WHI) is famous for bad news about hormone replacement therapy. Its bone results were almost the opposite — and are often under-reported to the women who could most benefit.
In the estrogen-plus-progestin arm (Rossouw 2002 and Cauley 2003), hormone replacement therapy produced:
- 34% reduction in hip fracture (hazard ratio 0.66).
- 34% reduction in clinical vertebral fracture (hazard ratio (HR) 0.66).
- 24% reduction in total fractures (hazard ratio 0.76).
These were not post-hoc fishing-expedition results. They were prespecified endpoints, statistically significant, and consistent with decades of observational data. Importantly, the fracture benefit appeared in average-risk postmenopausal women — not just women already diagnosed with osteoporosis. No other medication class has shown a hip-fracture reduction in healthy postmenopausal women with normal baseline BMD.
In plain numbers (Cauley 2003): over an average of 5.6 years, 733 of 8,506 women (8.6%) taking estrogen plus progestin had a fracture, compared with 896 of 8,102 (11.1%) on placebo (hazard ratio 0.76). In the 1,024 women whose bone density was scanned, total hip density rose 3.7% after 3 years on estrogen plus progestin, compared with 0.14% on placebo. The lower fracture risk showed up in every subgroup the researchers examined — by age, body weight, smoking, falls, fracture history, calcium intake and bone density. Rossouw 2002 put the hip-fracture benefit at 5 fewer hip fractures per 10,000 women per year. The same trials also counted heart disease, stroke, blood clots in the lungs and breast cancer in a “global index”; with all of those counted, Cauley 2003 found no net benefit, even in women at high risk of fracture.
The estrogen-alone arm (for women without a uterus) showed similar fracture reductions with a cleaner safety profile — no increase in breast cancer during the trial, and a reduction in breast cancer that has persisted in long-term follow-up.
The U.S. Food and Drug Administration Indication People Forget About
One of the official U.S. Food and Drug Administration-approved indications for systemic estrogen in the United States is prevention of postmenopausal osteoporosis. That label has been in place since the 1980s and has never been withdrawn. It sits right alongside the indication for vasomotor symptoms.
Yet if you walk into a primary care office and ask for estrogen specifically to protect your bones, many clinicians still react as if you are asking for something off-label or risky. The North American Menopause Society (NAMS) 2022 position statement explicitly supports hormone replacement therapy for osteoporosis prevention in appropriate candidates, and both the Endocrine Society and the International Menopause Society agree. The statement (NAMS was renamed The Menopause Society in 2023) finds that for women younger than 60 or within 10 years of menopause onset with no contraindications, the benefit–risk ratio is favorable for bothersome hot flashes and for prevention of bone loss.
The 2025 label change. On 10 November 2025 the FDA announced that it is initiating removal of the broad boxed (“black box”) warnings from menopausal hormone therapy products. The agency is working with companies to remove label references to risks of cardiovascular disease, breast cancer and probable dementia; it is not seeking to remove the boxed warning for endometrial cancer on systemic estrogen-alone products. The FDA’s labeled recommendation will be to start systemic hormone therapy within 10 years of menopause onset or before age 60. The announcement noted that women in the Women’s Health Initiative were on average 63 years old — over a decade past the average age of menopause — and took a hormone formulation no longer in common use.
Who Is a Candidate for Hormone Replacement Therapy-First Bone Strategy
Menopause guidelines describe hormone replacement therapy as a first bone option mainly for women who meet all of the following:
- Under age 60 at the time of initiation, and
- Within 10 years of their final menstrual period (the "timing hypothesis" window), and
- Also experiencing vasomotor symptoms (hot flashes, night sweats), genitourinary symptoms (vaginal dryness, urinary urgency), sleep disruption, mood changes, or joint aches — so hormone replacement therapy is doing multiple jobs at once, and
- No contraindications (see the hormone replacement therapy risks page): no active or prior estrogen-sensitive breast cancer, no prior unprovoked blood clot or stroke, no active liver disease, no undiagnosed vaginal bleeding.
For a woman who fits that profile, hormone replacement therapy does five or six useful things at once. In a 52-year-old woman with hot flashes and early bone loss, a bisphosphonate acts on bone only, while estrogen acts on the bone and the flashes and the vaginal symptoms and possibly on cardiovascular risk.
Women who are 60 or older, more than 10 years past menopause, have established osteoporosis (T-score ≤ –2.5), or have already had a fragility fracture usually start with a bisphosphonate or denosumab — those drugs have the direct fracture-reduction randomized controlled trial (RCT) data in that population. For women who start hormone therapy more than 10 years after menopause onset or after age 60, the 2022 NAMS statement finds the benefit–risk ratio less favorable because of the greater absolute risks of coronary heart disease, stroke, venous thromboembolism (blood clots) and dementia.
Effective Doses — Low-Dose Transdermal Works
High-dose estrogen is not needed to protect bone. The bone-sparing dose is lower than the dose many women used in the 1990s for symptom control.
- Transdermal estradiol patch 0.025–0.05 mg/day changed twice weekly — the route many menopause specialists use first.
- Estradiol gel 0.5–1.0 mg/day or spray — comparable bone effect to the patch.
- Oral estradiol 1 mg/day — effective: in an open 2-year trial, Gambacciani and colleagues (2008) gave healthy postmenopausal women low-dose pills (1 mg estradiol + 0.5 mg norethisterone acetate) or ultra-low-dose pills (0.5 mg estradiol + 0.25 mg norethisterone acetate) with 1,000 mg calcium a day. Spine density rose 5.2% and femoral-neck density 2.8% on the low dose, and 2.0% and 1.8% on the ultra-low dose, while women taking calcium alone lost 2.8% at both sites. First-pass liver metabolism of oral estrogen raises clotting factors, so many specialists use transdermal routes first, especially with any cardiovascular risk (see the estradiol formulations page).
Women who still have a uterus take a progestogen alongside estrogen to protect the endometrium (womb lining); estrogen alone raises the risk of endometrial cancer, which is why that boxed warning stays on estrogen-alone labels. A common choice is micronized progesterone 100 mg nightly (continuous) or 200 mg nightly for 12 days/month (cyclic). Micronized progesterone has a better safety profile than older synthetic progestins — detail on the progesterone vs progestins page.
Typical BMD response on a 0.05 mg patch plus adequate calcium and vitamin D: +2 to +5% at the spine and +1 to +3% at the hip over 2 years, compared with a 2–6% loss on placebo over the same interval. That is a 4–11 percentage-point swing — clinically equivalent to what a bisphosphonate achieves over the same period.
Hormone Replacement Therapy vs Bisphosphonates vs Denosumab
Head-to-head, the drug classes look more similar than marketing suggests.
BMD effect (prevention of bone loss in healthy early-postmenopausal women): hormone replacement therapy and bisphosphonates (alendronate 5–10 mg/day or 70 mg/week, risedronate, zoledronic acid) produce roughly comparable spine and hip BMD gains over 1–3 years. Studies that have randomized women directly between the two (EPIC trial and others) show either similar gains or a slight edge to hormone replacement therapy at the spine. In the Early Postmenopausal Intervention Cohort (EPIC) study (Hosking 1998), 1,174 women under 60 were randomized to alendronate 2.5 mg, alendronate 5 mg or placebo, and 435 more women who were prepared to take estrogen-progestin were randomly assigned to one of those treatments or to open-label estrogen-progestin. Over 2 years the placebo group lost bone at every site measured; alendronate 5 mg raised spine density 3.5% and hip density 1.9%; and the responses to estrogen-progestin were 1 to 2 percentage points greater than those to alendronate 5 mg.
Fracture reduction (treatment of established osteoporosis): Bisphosphonates have the larger and more recent randomized controlled trial database in women with T-score ≤ –2.5 or prior vertebral fracture — alendronate, risedronate, and zoledronic acid all reduce vertebral fractures by roughly 40–70% and hip fractures by 30–50%. Denosumab (60 mg subcutaneously every 6 months) produces even larger BMD gains and similar fracture reductions, but it has a dangerous rebound: if you miss a dose or stop without transitioning to a bisphosphonate, vertebral fractures can cluster within 6–18 months.
How specialists commonly sort these options:
- Age 50–59, recently menopausal, T-score –1.0 to –2.4, plus hot flashes: hormone replacement therapy is commonly used first.
- Age 50–59, recently menopausal, no symptoms, T-score borderline: hormone replacement therapy or a bisphosphonate — both are used.
- Age 65+, T-score ≤ –2.5, or prior fragility fracture: a bisphosphonate (oral alendronate or yearly zoledronic acid intravenous, IV) is the usual first-line drug. Denosumab is used when a bisphosphonate is not tolerated; because of the rebound described above, stopping it is normally followed by another bone drug.
- Very high risk (T-score ≤ –3.0, recent vertebral fracture): anabolic (bone-building) therapy is often used first (teriparatide, abaloparatide, or romosozumab), followed by a bisphosphonate or denosumab.
What Happens When You Stop Hormone Replacement Therapy
This is the catch. Hormone replacement therapy protects bone only while it is taken. When estrogen is withdrawn, the RANKL/OPG balance tips back, osteoclasts become more active again, and bone loss resumes. The best measurement comes from the PEPI Safety Follow-up Study (Greendale 2002), which tracked 495 women from the 3-year Postmenopausal Estrogen/Progestin Interventions trial. Women who stopped after 3 years of therapy lost about 1% a year afterwards (−1.01% at the hip, −1.04% at the spine); women who stopped after 1 year lost 0.54% (hip) and 0.81% (spine) a year over the next 2 years. Those rates did not differ significantly from women who never took hormone therapy, and the authors concluded their results “do not support the hypothesis that bone is lost at an unusually fast rate after discontinuation.” Women who kept taking hormone therapy after the 3-year trial showed no further gains in bone density.
Two consequences follow:
- When bone protection is a major reason for taking hormone replacement therapy, stopping at age 60 "because of the WHI" ends that protection: bone loss resumes at the ordinary postmenopausal rate, and in the long-term WHI follow-up (Manson 2013) most of the risks and benefits seen during treatment (the benefits included fewer hip fractures) faded after the women stopped.
- Some specialists move women who taper off onto a bisphosphonate (e.g. yearly zoledronic acid, or 3–5 years of oral alendronate) to hold the BMD gains. This is similar to the now-standard practice of transitioning off denosumab onto a bisphosphonate.
Many current menopause specialists are comfortable continuing hormone replacement therapy well past age 60 or even 65 in healthy low-risk women who are benefiting — the 2022 NAMS position statement explicitly endorses continued use based on ongoing risk–benefit review rather than an arbitrary stop age.
Calcium, Vitamin D, K2, and Protein
No drug works well on a depleted foundation. The nutrition baseline for any bone strategy:
- Calcium 1,000–1,200 mg/day, from food or supplements. Dairy (yogurt 300 mg/cup, milk 300 mg/cup, hard cheese 200 mg/oz), sardines or canned salmon with bones (300–350 mg/can), natto (fermented soybeans, about 217 mg per 100 g according to USDA FoodData Central), collard and turnip greens (250–270 mg/cup cooked), almonds (75 mg/oz), fortified plant milks. High-dose calcium supplements — especially single 1,000 mg pills — have been linked in some analyses to increased cardiovascular and kidney-stone risk; food calcium has not.
- Vitamin D3 800–2,000 international units (IU)/day, adjusted to achieve a 25-hydroxy-vitamin-D blood level of 30–50 ng/mL. Heavier bodies, darker skin, and northern latitudes often need the top of that range. See the Vitamin D3 page.
- Vitamin K2 (menaquinone-7) 100–200 mcg/day. K2 activates osteocalcin, which directs calcium into bone matrix rather than arterial walls. Evidence is strongest from Japanese studies using menaquinone-4 (MK-4) at pharmacologic doses; menaquinone-7 (MK-7) at supplement doses shows smaller but consistent BMD benefits. See the Vitamin K page.
- Protein 1.0–1.2 g/kg/day. A 68 kg (150 lb) woman needs 68–82 g of protein per day, spread across meals. Bone is roughly half protein by volume; under-eating protein in your sixties and seventies is one of the strongest predictors of hip fracture, independent of calcium.
- Magnesium 300–400 mg/day, primarily from leafy greens, nuts, seeds, and whole grains. Magnesium is required for vitamin D activation and parathyroid hormone (PTH) regulation.
Caffeine above ~400 mg/day, heavy alcohol (≥2 drinks/day), and smoking all measurably accelerate bone loss.
Resistance Training and Impact Exercise
Bone responds to mechanical load. Walking is good for your heart and your mood; it does relatively little for your spine and hip BMD. What moves bone density is loading that exceeds what the bone is used to.
- Progressive resistance training 2–3 days/week. Squats, deadlifts, overhead press, row, lunges — compound movements with increasing weight over time. The LIFTMOR trial (Watson 2018) put 101 postmenopausal women with low bone mass (average age 65) through 8 months of twice-weekly, 30-minute supervised sessions of heavy resistance and impact training (5 sets of 5 repetitions at more than 85% of one-rep max) or a home-based low-intensity program. Lumbar-spine density rose 2.9% in the heavy-training group and fell 1.2% in the home group; femoral-neck density rose 0.3% versus a 1.9% fall. Only one adverse event was reported (a minor lower-back spasm), under closely supervised conditions.
- Impact exercise 3–5 days/week. Jumping (10–50 low hops per day), skipping, hopping, step-down drills, and running all load the hip in a way walking does not. Even 10 multidirectional hops a day, done consistently, produces measurable femoral-neck BMD gains.
- Balance and fall prevention. Most hip fractures happen because someone falls, not because bone collapsed on its own. Single-leg stance, tandem walking, tai chi, and targeted ankle and hip stabilizer work reduce fall rate by 20–40%.
- Aggressive spinal flexion carries a fracture risk when spine BMD is already low. Full sit-ups, toe-touches, and loaded forward-bending can crush-fracture weakened vertebrae. Extension-biased work (glute bridges, prone back extensions, farmer's carries) is safer and more useful.
DEXA Intervals and the FRAX Score
DEXA (dual-energy X-ray absorptiometry) is the standard bone density scan. It takes 10 minutes, uses a trivial amount of radiation, and reports two numbers per site (spine, hip, sometimes forearm):
- T-score: standard deviations from the average young adult peak bone mass. −1.0 to −2.4 is osteopenia; ≤−2.5 is osteoporosis.
- Z-score: standard deviations from the average person your age and sex. Useful for younger women and men to flag unexpected loss that warrants a secondary workup.
Full detail on how to read your results is on the DEXA T-score and Z-score explained page.
Screening intervals:
- Baseline DEXA at menopause or age 50 if you have risk factors (family history of hip fracture, low body weight <127 lb, smoking, early menopause before 45, long-term glucocorticoids, celiac or inflammatory bowel disease (IBD), hyperthyroidism). Otherwise, baseline at age 65.
- Repeat every 2 years while on treatment or during the rapid-loss early-menopause window.
- Extend to every 3–5 years once BMD is stable and in the normal range.
FRAX score: the WHO fracture-risk calculator (available free at frax.shef.ac.uk) estimates your 10-year probability of a major osteoporotic fracture and of hip fracture specifically, using your age, sex, weight, height, prior fracture, parental hip fracture, smoking, alcohol, glucocorticoid use, rheumatoid arthritis, and (optionally) femoral-neck BMD. U.S. treatment thresholds are usually ≥20% for major osteoporotic fracture or ≥3% for hip fracture — above those numbers, pharmacologic therapy is recommended regardless of T-score.
Key Research Papers
- Cauley JA, et al. Effects of estrogen plus progestin on risk of fracture and bone mineral density: the Women's Health Initiative randomized trial. JAMA. 2003;290(13):1729–1738. — doi:10.1001/jama.290.13.1729
- Rossouw JE, et al. Risks and benefits of estrogen plus progestin in healthy postmenopausal women: principal results from the Women's Health Initiative randomized controlled trial. JAMA. 2002;288(3):321–333. — doi:10.1001/jama.288.3.321
- The 2022 Hormone Therapy Position Statement of The North American Menopause Society. Menopause. 2022;29(7):767–794. — doi:10.1097/GME.0000000000002028
- Gambacciani M, Cappagli B, Ciaponi M, Pepe A, Vacca F, Genazzani AR. Ultra low-dose hormone replacement therapy and bone protection in postmenopausal women. Maturitas. 2008;59(1):2–6. — PubMed PMID: 18063490
- Watson SL, et al. High-Intensity Resistance and Impact Training Improves Bone Mineral Density and Physical Function in Postmenopausal Women With Osteopenia and Osteoporosis: The LIFTMOR Randomized Controlled Trial. J Bone Miner Res. 2018;33(2):211–220. — doi:10.1002/jbmr.3284
- Greendale GA, Espeland M, Slone S, Marcus R, Barrett-Connor E. Bone mass response to discontinuation of long-term hormone replacement therapy: results from the Postmenopausal Estrogen/Progestin Interventions (PEPI) Safety Follow-up Study. Arch Intern Med. 2002;162(6):665–672. — PubMed PMID: 11911720
- Hosking D, Chilvers CE, Christiansen C, et al. Prevention of bone loss with alendronate in postmenopausal women under 60 years of age. Early Postmenopausal Intervention Cohort Study Group. N Engl J Med. 1998;338(8):485–492. — PubMed PMID: 9443925
- Manson JE, Chlebowski RT, Stefanick ML, et al. Menopausal hormone therapy and health outcomes during the intervention and extended poststopping phases of the Women's Health Initiative randomized trials. JAMA. 2013;310(13):1353–1368. — PubMed PMID: 24084921
- Eastell R, et al. Pharmacological Management of Osteoporosis in Postmenopausal Women: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2019;104(5):1595–1622. — doi:10.1210/jc.2019-00221
PubMed Topic Searches
For further reading, these PubMed searches return current peer-reviewed work on hormone replacement therapy and bone:
- Hormone therapy and postmenopausal bone mineral density
- Transdermal estradiol and bone density
- WHI, hip fracture, estrogen, and progestin
- Estrogen, RANKL, OPG, and osteoclast regulation
- HRT vs bisphosphonate head-to-head bone trials
- Bone loss after stopping hormone therapy
- Resistance training and postmenopausal bone density
- FRAX score and treatment thresholds
- Vitamin K2 (menaquinone) and bone density
Connections
- Reproductive Medicine
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Estradiol Formulations: Patch, Gel, Oral Routes
- Hormone Replacement Therapy Risks: Breast Cancer, Clots and Stroke
- Vitamin D3
- Vitamin K
- Micronized Progesterone vs Synthetic Progestins
- DEXA Scan: T-Score and Z-Score Explained
- Calcium
- Osteoporosis
- Testosterone Therapy for Women
- Vasomotor Symptoms: Hot Flashes and Night Sweats
- Genitourinary Syndrome of Menopause and Vaginal Estrogen
- Non-Hormonal Options: Selective Serotonin Reuptake Inhibitors, Gabapentin, Fezolinetant
- Perimenopause Symptom Tracker and Hormonal Testing
- Menopause and Hormone Replacement Therapy
- Calcium, Vitamin D and Protein Intake
- Bisphosphonates: Alendronate, Risedronate, Zoledronate
- Magnesium
- Perimenopause
- Menopause — the estrogen loss that starts the rapid bone-loss window described here.