Hormone Replacement Therapy (HRT) Risks: Breast Cancer, Clots, and Stroke
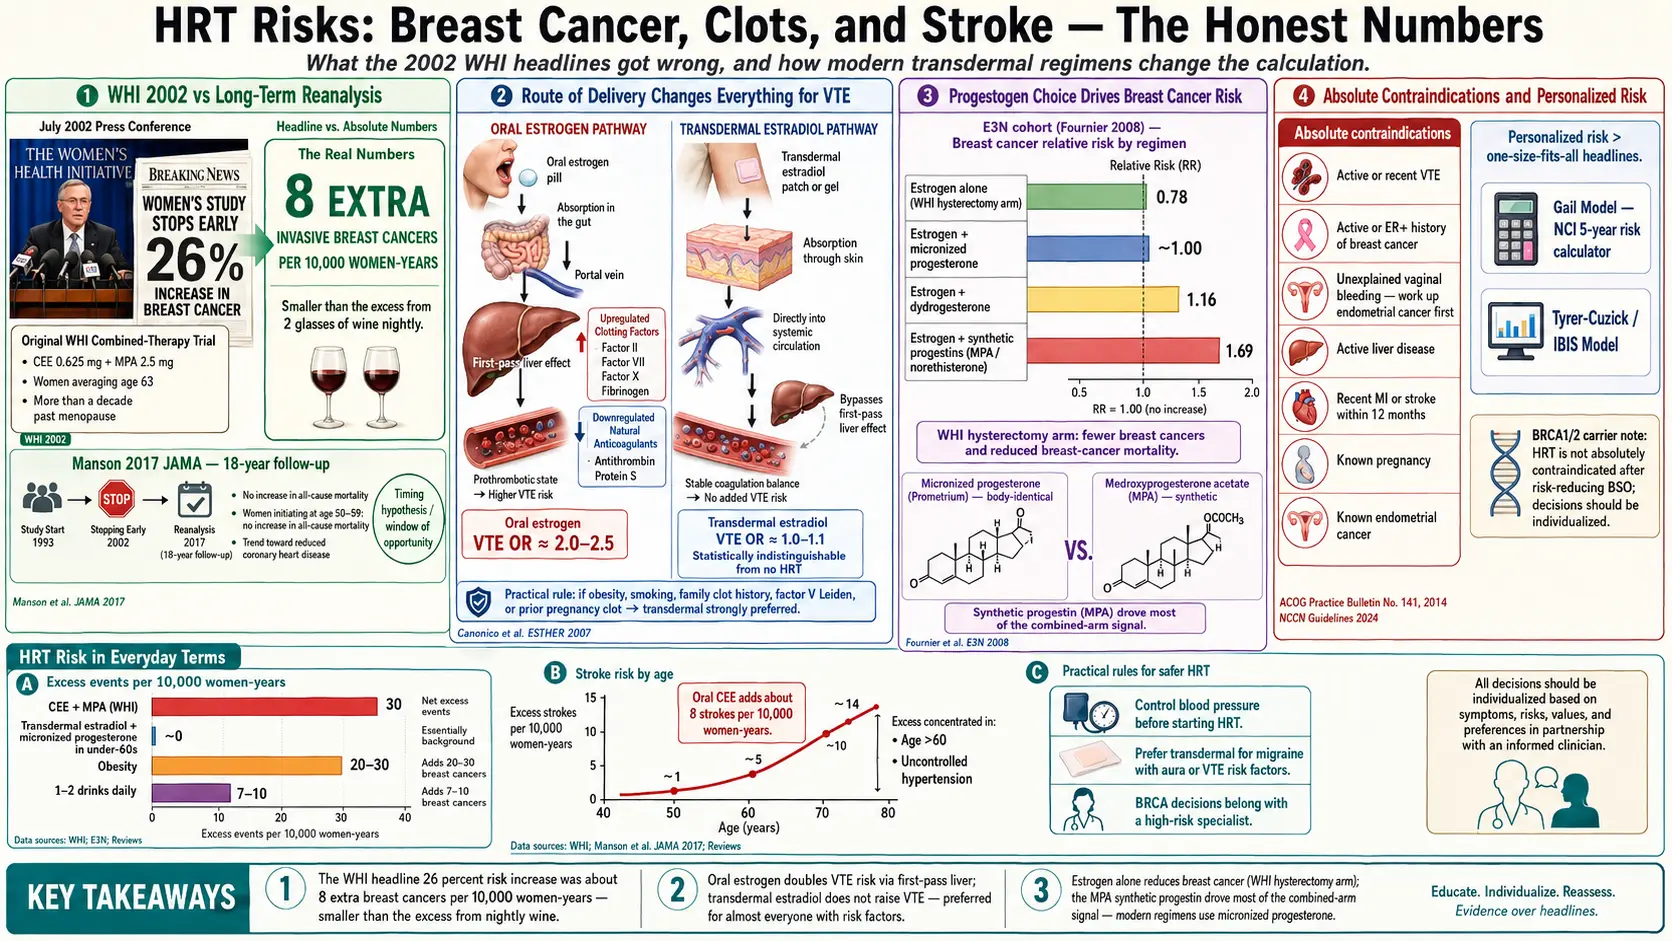
Almost everything most women think they know about hormone therapy risk comes from a single July 2002 press conference — and most of it was wrong, or at least wildly oversimplified. The Women's Health Initiative (WHI) investigators halted the combined estrogen-plus-progestin arm of their trial early, announced a "26% increase in breast cancer," and set off a panic that caused millions of women to throw their patches in the trash overnight. In the United States, prescriptions for hormone replacement therapy (HRT) fell fast: in the first half of 2003, compared with the first half of 2002, prescriptions fell by 66% for the combined estrogen-plus-progestin tablet and by 33% for conjugated estrogens alone (Hersh 2004). What almost nobody reported at the time was the absolute number: 8 extra breast cancer cases per 10,000 women per year. That is smaller than the excess breast-cancer risk from drinking two glasses of wine a night.
This page walks through what modern re-analysis of the WHI data actually shows, how risk varies enormously depending on when you start hormone replacement therapy, what kind of estrogen you take, and how you deliver it. It also lists the contraindications printed on the drug label. The goal is not to minimize risk — blood clots and strokes are real and can kill — but to give you numbers you can compare to the risks you already accept every day.
Interactive Visualization Menopause — run the hormones down and set off a hot flash Empty the ovarian follicle pool and watch estradiol swing, then flatten, while follicle-stimulating hormone (FSH) climbs — then trigger a hot flash and see the narrowed thermoneutral zone behind it. Launch →Table of Contents
- The 2002 WHI Story — and What Went Wrong With the Headlines
- The Timing Hypothesis: Age at Initiation Matters Enormously
- The Estrogen-Alone Surprise
- Blood Clots (VTE): Route of Delivery Changes Everything
- Stroke Risk: Oral Estrogen, Age, and Baseline Risk
- How the Progestogen Changes Risk: Micronized Progesterone vs MPA
- Absolute Contraindications on the Drug Label
- Personalizing Your Risk: Gail, Family History, BRCA
- Putting Hormone Replacement Therapy Risk in Everyday Terms
- The 2025 Removal of the Boxed Warning
- Key Research Papers
- PubMed Topic Searches
- Connections
- Featured Videos
The 2002 WHI Story — and What Went Wrong With the Headlines
The Women's Health Initiative was the largest randomized trial ever run in menopausal women — more than 27,000 participants across two arms. The estrogen-plus-progestin arm used conjugated equine estrogens (CEE) 0.625 mg daily plus medroxyprogesterone acetate (MPA) 2.5 mg daily. The average participant was 63 years old at enrollment — more than a decade past the average age of menopause.
On May 31, 2002, after a mean of 5.2 years of follow-up, the data and safety monitoring board recommended stopping the trial, and the results were made public in July 2002. The headline number: a hazard ratio of 1.26 for invasive breast cancer — a "26% increase." What that actually meant in absolute terms:
- Placebo group: about 30 invasive breast cancers per 10,000 women per year.
- CEE + MPA group: about 38 invasive breast cancers per 10,000 women per year.
- Excess risk: roughly 8 extra cases per 10,000 women-years, or 0.08% per year.
Stated that way, the number is real but small. For comparison: the excess breast-cancer risk from drinking one alcoholic drink per day is roughly 7–10 extra cases per 10,000 women-years. The excess risk from a body mass index (BMI) over 30 is larger still. The story that got told in 2002 — "hormone replacement therapy causes breast cancer" — conflated a modest absolute increase in one specific regimen (oral CEE + oral MPA, started at an average age of 63) with all hormone therapy in all women.
There were also increases in coronary heart disease events and stroke in that arm, plus increased VTE — all real, all in older women started late, all using oral conjugated equine estrogens and a synthetic progestin that modern prescribers rarely use anymore.
The Timing Hypothesis: Age at Initiation Matters Enormously
The long-term follow-up analysis published by JoAnn Manson and colleagues in JAMA in 2017 tracked WHI participants for 18 years. When results were broken down by age at initiation, the picture changed dramatically:
- Women who started hormone replacement therapy between ages 50 and 59 (the group most like real-world new initiators) showed no increase in all-cause mortality. Across all ages, 27.1% of women in the hormone groups and 27.6% in the placebo groups died over the 18 years (hazard ratio 0.99). Compared with women who started at 70–79, women who started at 50–59 did better: the ratio of their hazard ratios for death was 0.61 during the treatment years and 0.87 over the full 18 years.
- Women who started within 10 years of menopause onset showed a trend toward reduced coronary heart disease.
- The harms clustered in women who started after age 60 or more than a decade past menopause — precisely the women already accumulating atherosclerotic plaque, in whom introducing estrogen may destabilize existing lesions.
This is the "timing hypothesis" or "window of opportunity." It is now accepted by the North American Menopause Society (now The Menopause Society), the Endocrine Society, the International Menopause Society, and the British Menopause Society. Their consensus: for symptomatic women under 60 and within 10 years of menopause, the benefits of hormone replacement therapy generally outweigh the risks. After 60 or beyond 10 years, the calculation tilts less favorably, and the decision becomes much more individual.
The Estrogen-Alone Surprise
The WHI ran a second arm for women who had already had a hysterectomy, so they did not need a progestogen to protect the uterine lining. These 10,739 women received CEE 0.625 mg daily alone or placebo. The results, published and updated through 2020:
- Invasive breast cancer decreased in the estrogen-alone group: hazard ratio about 0.78, translating to roughly 7 fewer cases per 10,000 women-years. After more than 20 years of follow-up (Chlebowski 2020), the yearly rate was 0.30% with estrogen alone versus 0.37% with placebo.
- Breast cancer mortality was also reduced (hazard ratio around 0.60 in long-term follow-up): 30 breast-cancer deaths with estrogen alone versus 46 with placebo.
- For comparison, in the same long-term follow-up the combined estrogen-plus-MPA arm had more breast cancer — 0.45% versus 0.36% per year (hazard ratio 1.28) — but no statistically significant difference in breast-cancer deaths (hazard ratio 1.35, 95% confidence interval 0.94–1.95).
Not every study agrees on estrogen alone. In the French E3N cohort of 80,377 women (Fournier 2008), estrogen alone was linked to a 1.29-fold higher breast cancer risk compared with never-use, so the lower risk seen in the WHI trial is not found in every population.
This finding, almost never reported in the mainstream press, strongly suggests that the synthetic progestin MPA — not estrogen itself — drove most of the breast-cancer signal in the combined arm. Estrogen without MPA, in hysterectomy women, actually appears breast-protective.
Whether that protection extends to women who still have a uterus and take some progestogen is the central question of modern hormone replacement therapy practice. The answer depends heavily on which progestogen is used — see section 6 below.
Blood Clots (VTE): Route of Delivery Changes Everything
Venous thromboembolism (VTE) — deep vein thrombosis and pulmonary embolism — is the most clear-cut risk of systemic hormone replacement therapy. But it is almost entirely a risk of oral estrogen, not transdermal.
Here is why. When you swallow an estrogen pill, the hormone is absorbed through the gut and travels through the portal vein directly to the liver in high concentration. The liver responds by upregulating production of clotting factors (fibrinogen, factor VII, factor X) and down-regulating anticoagulants (antithrombin, protein S). A patch or gel delivers estrogen through the skin into the general circulation, so the liver only sees physiologic bloodstream concentrations — not a concentrated first-pass hit.
The French ESTHER case-control study (Canonico et al., 2007) compared 271 women aged 45–70 who had a first clot with 610 matched women who had not, and found:
- Oral estrogen: odds ratio for VTE 4.2 (95% confidence interval 1.5–11.6) vs non-users. Baseline VTE rate in healthy postmenopausal women is about 1–2 per 1,000 per year.
- Transdermal estrogen (patch or gel): odds ratio 0.9 (95% confidence interval 0.4–2.1) — no significant increase over no hormone replacement therapy.
- Progestogens: micronized progesterone (odds ratio 0.7) and pregnane derivatives (odds ratio 0.9) showed no significant link with clots, while norpregnane derivatives carried about a 4-fold higher risk (odds ratio 3.9).
This is one of the clearest risk-reduction choices in hormone therapy. For women with even modestly elevated VTE risk — obesity, smoking, family history of clot, factor V Leiden, prior pregnancy clot, planned surgery — menopause clinicians generally choose transdermal delivery. Many now use transdermal for everyone regardless of baseline risk.
Stroke Risk: Oral Estrogen, Age, and Baseline Risk
Stroke risk on hormone replacement therapy follows a similar pattern but is more sensitive to age and cardiovascular baseline. WHI found an increased ischemic stroke risk on oral CEE: roughly 8 extra strokes per 10,000 women-years, concentrated in women over 60 and those with untreated hypertension.
Observational data on transdermal estradiol suggest no meaningful increase in stroke at doses of 50 mcg/day or lower. Higher-dose patches (100 mcg) do appear to carry some excess risk, though the absolute numbers remain small in women under 60.
How these findings are applied in menopause practice:
- Uncontrolled hypertension is the single biggest amplifier of stroke risk on estrogen, so blood pressure is usually brought under control before hormone replacement therapy starts.
- Transdermal rather than oral estrogen is the usual choice for women with migraine with aura, prior transient ischemic attack (TIA), atrial fibrillation, or other stroke risk factors.
- After age 60 or 10 years post-menopause, the stroke calculus shifts — this is where the "window of opportunity" argument has real weight.
How the Progestogen Changes Risk: Micronized Progesterone vs MPA
Women who still have a uterus take a progestogen alongside systemic estrogen to prevent endometrial hyperplasia and endometrial cancer. The choice of progestogen dramatically changes breast cancer risk.
The French E3N cohort (Fournier et al., 2008) followed 80,377 postmenopausal women for about 8 years and compared breast cancer incidence by hormone replacement therapy regimen:
- Estrogen + micronized progesterone (bio-identical): relative risk about 1.00 — essentially no increase in breast cancer over non-users during the study window.
- Estrogen + dydrogesterone: relative risk about 1.16 — a small increase.
- Estrogen + synthetic progestins (including MPA, norethisterone): relative risk about 1.69 — substantially higher.
Longer-term follow-up does show some signal with micronized progesterone after 5+ years of use, so the protection is not absolute — but the difference between bio-identical progesterone and MPA is large and consistent across cohorts. This is why essentially every modern menopause guideline now prefers micronized progesterone (or the progesterone-releasing intrauterine system) over older synthetic progestins for women starting hormone replacement therapy today. See the companion progesterone vs progestins article for dosing details.
Absolute Contraindications on the Drug Label
An FDA-approved estradiol tablet label (on DailyMed) lists the conditions below as contraindications to systemic estrogen. Vaginal estrogen for GSM is a separate question with a different safety profile — see the GSM article.
- Active deep vein thrombosis (DVT), pulmonary embolism, or a history of these conditions. The label makes no exception for the route of delivery; some menopause clinicians consider transdermal estrogen case by case with hematology input.
- Known, suspected or past breast cancer, except in selected patients being treated for metastatic disease. Non-hormonal options exist for hot flashes.
- Undiagnosed abnormal genital bleeding. The cause is normally identified before any hormone replacement therapy — hormone therapy can mask endometrial cancer.
- Liver dysfunction or disease. Oral estrogen is metabolized hepatically; some clinicians regard transdermal estrogen as acceptable in stable mild disease.
- Active or recent arterial thromboembolic disease such as stroke or myocardial infarction (the label gives "within the past year" as an example).
- Known or suspected pregnancy.
- Known or suspected estrogen-dependent tumors beyond breast (e.g., known endometrial cancer).
- Known allergy (hypersensitivity) to the tablet's ingredients.
Relative contraindications — conditions menopause clinicians weigh case by case — include: migraine with aura, uncontrolled hypertension, gallbladder disease, familial hypertriglyceridemia, BRCA1/2 mutation, and dense breast tissue with strong family history.
Personalizing Your Risk: Gail, Family History, BRCA
The population-average numbers above become much more useful when you translate them to your specific risk profile. The two most common tools:
- Gail Model (NCI Breast Cancer Risk Assessment Tool). Free online. Uses age, race, age at menarche, age at first live birth, number of first-degree relatives with breast cancer, number of prior breast biopsies, and presence of atypia. Outputs a 5-year and lifetime breast cancer risk estimate. A 5-year risk above 1.67% is considered elevated — the threshold at which the U.S. Food and Drug Administration (FDA) approved tamoxifen for prevention. If your baseline 5-year risk is 1.0%, adding the WHI excess (~0.08% per year, ~0.4% over 5 years on CEE+MPA) gives roughly 1.4%. Perspective matters.
- Tyrer-Cuzick (IBIS) Model. More sophisticated than Gail; incorporates breast density, body mass index, and more detailed family history. Often preferred in high-risk clinics.
- BRCA1/2 carriers. Lifetime breast cancer risk is already 55–72% for BRCA1 and 45–69% for BRCA2. Hormone replacement therapy is not absolutely contraindicated after risk-reducing bilateral salpingo-oophorectomy (prophylactic ovary removal), and multiple studies suggest short-term hormone replacement therapy to the natural menopause age (~51) does not erase the risk-reduction benefit of the surgery.
Personal density reports, prior biopsy history showing atypical hyperplasia or lobular carcinoma in situ (LCIS), and first-degree relatives with premenopausal breast cancer are all features that clinicians treat as reasons for extra caution or for non-hormonal options.
Putting Hormone Replacement Therapy Risk in Everyday Terms
Numbers in isolation are meaningless. Consider what other risks look like per 10,000 women-years:
- CEE + MPA (WHI): ~8 extra breast cancers, ~7 extra coronary events, ~8 extra strokes, ~8 extra pulmonary embolisms (clots in the lung) — offset by ~6 fewer colorectal cancers and ~5 fewer hip fractures. The trial's net excess across all the events in its global index was 19 per 10,000 woman-years.
- Transdermal estradiol + micronized progesterone (modern regimen in women under 60): breast-cancer signal at or near background, no excess VTE, no meaningful stroke excess at 50 mcg dosing. Benefits on bone, vasomotor symptoms, and possibly cardiovascular mortality (per timing hypothesis) remain.
- Obesity (body mass index ≥ 30): adds roughly 20–30 extra breast cancers per 10,000 postmenopausal women-years, plus large excesses in cardiovascular and diabetes-related events.
- One to two alcoholic drinks per day: adds 7–10 extra breast cancers per 10,000 women-years.
- Driving a car in the United States: roughly 1 fatal motor vehicle crash per 10,000 drivers per year.
- Combined oral contraceptives in a 30-year-old: VTE rate roughly 3–9 per 10,000 women-years above baseline — comparable to or higher than oral postmenopausal hormone replacement therapy.
This is the context the 2002 headlines left out. Hormone replacement therapy risk is real and deserves informed consent. It is not categorically different from — and in many configurations is smaller than — risks women routinely accept with a glass of wine, a second helping at dinner, or a commute to work. The Menopause Society's 2022 position statement makes this point in clinical language: for women younger than 60 years or within 10 years of menopause onset who have no contraindications, "the benefit-risk ratio is favorable for treatment of bothersome VMS [vasomotor symptoms] and prevention of bone loss."
The 2025 Removal of the Boxed Warning
In 2003 the U.S. Food and Drug Administration (FDA) put a boxed ("black box") warning on menopausal hormone therapy products, based on the WHI oral conjugated equine estrogens plus medroxyprogesterone acetate study. The warning applied to all doses, forms and routes, including vaginal products, along with the instruction to use the "lowest effective dose for the shortest duration."
On November 10, 2025, the U.S. Department of Health and Human Services and the FDA announced the removal of that boxed warning. A 2026 review in Obstetrics & Gynecology (Sriprasert 2026) reports that the decision followed an FDA review of the scientific literature, an expert panel meeting on July 17, 2025, and a 60-day public comment period. The labels move to product-specific wording, drop the "lowest effective dose for the shortest duration" mandate, and add guidance on starting hormone therapy within 10 years of menopause or before age 60.
Key Research Papers
- Rossouw JE, et al. Risks and benefits of estrogen plus progestin in healthy postmenopausal women: principal results from the Women's Health Initiative randomized controlled trial. JAMA. 2002;288(3):321-333. — doi:10.1001/jama.288.3.321
- Manson JE, et al. Menopausal hormone therapy and long-term all-cause and cause-specific mortality: the Women's Health Initiative randomized trials. JAMA. 2017;318(10):927-938. — doi:10.1001/jama.2017.11217
- Canonico M, et al. Hormone therapy and venous thromboembolism among postmenopausal women: impact of the route of estrogen administration and progestogens: the ESTHER study. Circulation. 2007;115(7):840-845. — doi:10.1161/CIRCULATIONAHA.106.642280
- Fournier A, Berrino F, Clavel-Chapelon F. Unequal risks for breast cancer associated with different hormone replacement therapies: results from the E3N cohort study. Breast Cancer Res Treat. 2008;107(1):103-111. — doi:10.1007/s10549-007-9523-x
- The 2022 Hormone Therapy Position Statement of The North American Menopause Society. Menopause. 2022;29(7):767-794. — doi:10.1097/GME.0000000000002028
- Chlebowski RT, et al. Association of menopausal hormone therapy with breast cancer incidence and mortality during long-term follow-up of the Women's Health Initiative randomized clinical trials. JAMA. 2020;324(4):369-380. — doi:10.1001/jama.2020.9482
- Hersh AL, Stefanick ML, Stafford RS. National use of postmenopausal hormone therapy: annual trends and response to recent evidence. JAMA. 2004;291(1):47-53. — doi:10.1001/jama.291.1.47
- Sriprasert I, Hodis HN, Mack WJ, Rosser M, Evans ML, Xu X, Wright JD. Elimination of the black box warning on menopausal hormone therapy. Obstet Gynecol. 2026;147(5):642-646. — doi:10.1097/AOG.0000000000006226
PubMed Topic Searches
For further reading, these PubMed searches pull up current peer-reviewed work on hormone replacement therapy risk:
- WHI hormone therapy long-term follow-up
- Transdermal estradiol and venous thromboembolism
- Micronized progesterone and breast cancer risk
- HRT timing hypothesis and cardiovascular outcomes
- Estrogen-alone and breast cancer in hysterectomy women
- Hormone therapy and stroke risk by route
- E3N cohort, HRT, and breast cancer
- BRCA carriers, HRT, and risk-reducing oophorectomy
- The Menopause Society 2022 position statement
- Absolute vs relative risk communication in HRT
Connections
- Reproductive Medicine
- Menopause: Why the Hormones Fall and What Changes — interactive animation
- Genitourinary Syndrome of Menopause and Vaginal Estrogen
- Micronized Progesterone vs Synthetic Progestins
- Estradiol Formulations: Patch, Gel, Oral Routes
- Testosterone Therapy for Women
- Vasomotor Symptoms: Hot Flashes and Night Sweats
- Non-Hormonal Options: Selective Serotonin Reuptake Inhibitors, Gabapentin, Fezolinetant
- Perimenopause Symptom Tracker and Hormonal Testing
- Bone Loss Prevention and Hormone Replacement Therapy
- Perimenopause
- Cardiovascular Disease
- Menopause and Hormone Replacement Therapy
- Hormone Panel
- Breast Cancer — the disease whose absolute risk on hormone therapy this page quantifies.
- Stroke
- Deep Vein Thrombosis
- Pulmonary Embolism
- Hypertension
- Depression
- Insomnia
- Covered in depth on its own page: Menopause